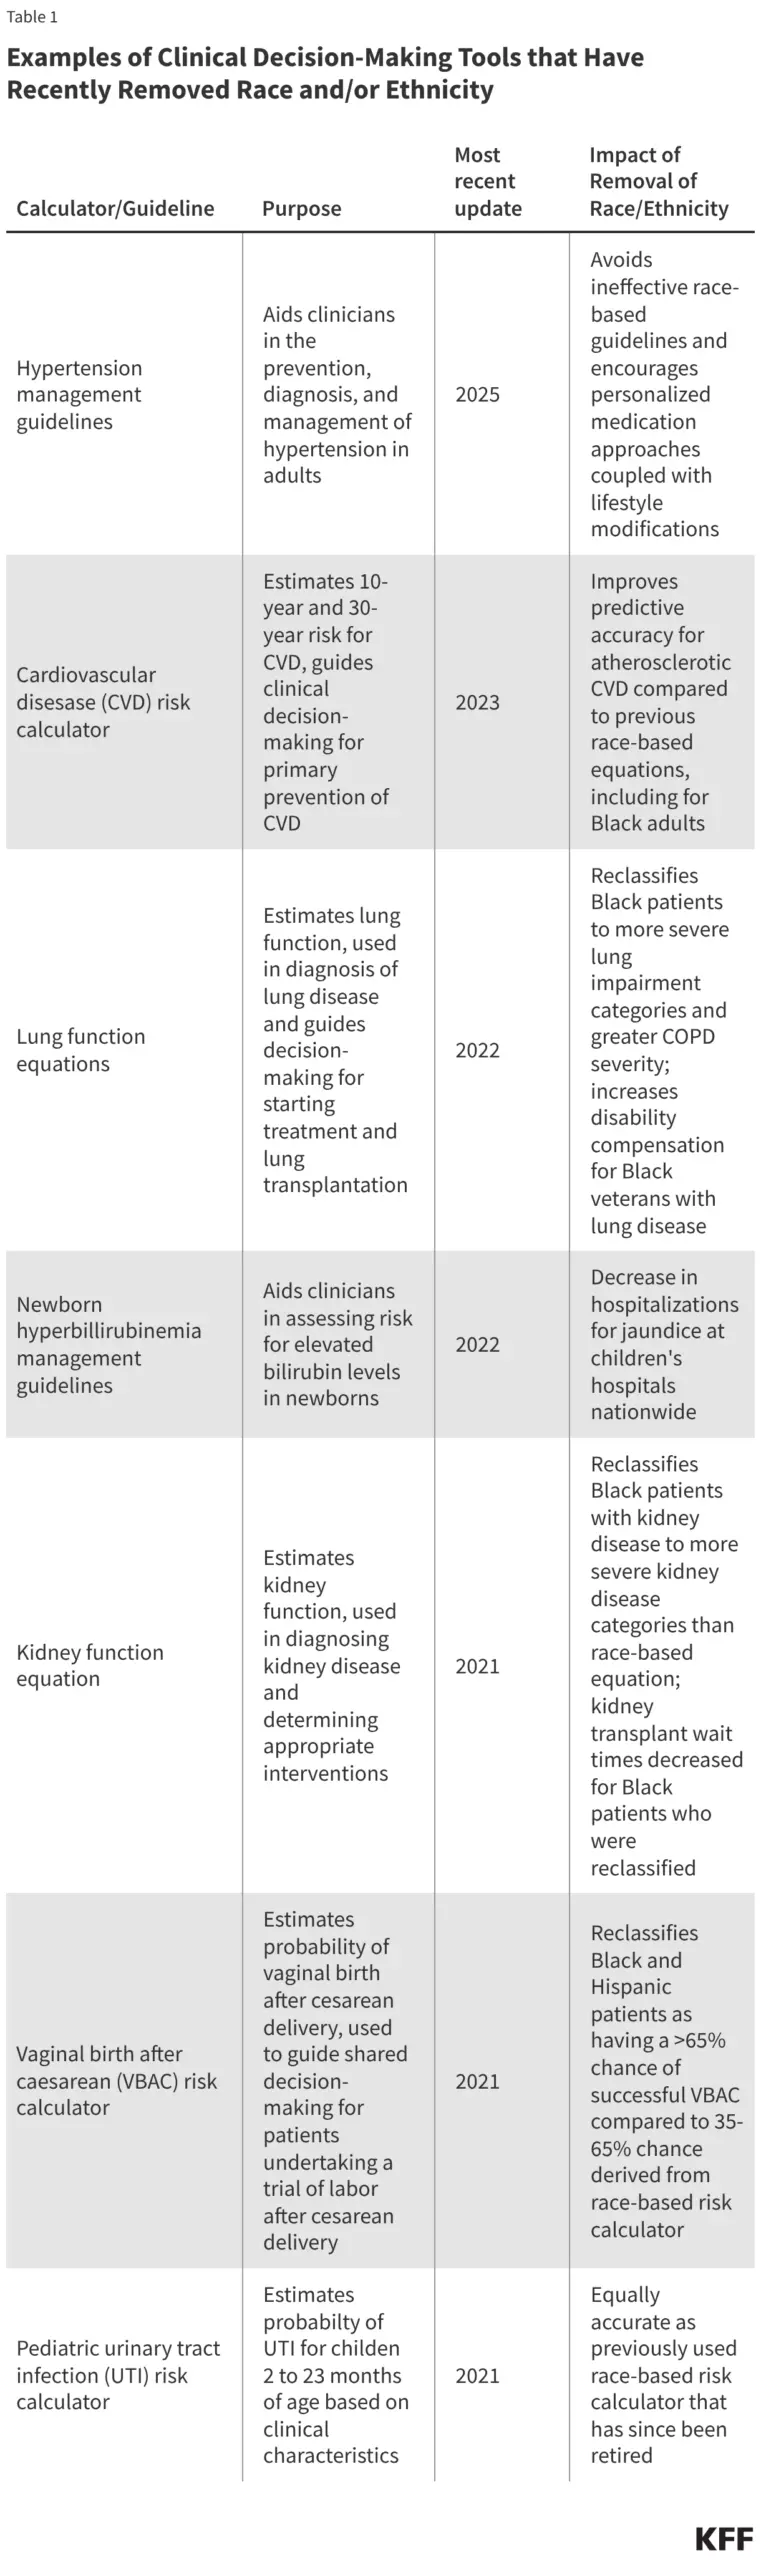
For decades, the standard practice of American medicine relied on algorithms, risk calculators, and clinical guidelines that explicitly factored in a patient’s race or ethnicity. These tools, designed to estimate everything from kidney function to the risk of cardiac events, were long considered essential for "personalized" medicine. However, a growing body of research has revealed a startling reality: many of these tools were not based on biological or genetic evidence, but rather on pseudoscientific notions that have historically exacerbated, rather than mitigated, racial health disparities.
As the medical establishment faces a reckoning with its past, a significant shift is underway. Across the country, hospitals, medical societies, and researchers are systematically stripping race-based variables from clinical tools. This transition represents one of the most profound changes in the philosophy of modern medical practice, forcing a new, necessary debate about how clinicians should account for patient diversity without perpetuating structural inequality.
The Historical Roots of Clinical Bias
To understand the current movement, one must first look at the foundations of medical research. Historically, race has been utilized as a convenient, albeit flawed, proxy for biological difference. This usage stems from a history of social hierarchies—supported by debunked fields like phrenology and eugenics—that sought to categorize humans by race to justify unequal treatment.
Despite a broad scientific consensus that race is a socio-political construct rather than a biological one, medicine continued to conflate the two. When clinicians use race in a calculator, they are often assuming that a patient’s ancestry inherently dictates their disease risk or organ function. This has led to "clinical racism," where false beliefs—such as the persistent, evidence-defying myth that Black patients have less sensitive nerve endings—have translated into documented failures in pain management and diagnosis.
A Chronology of Change
The movement toward "race-free" medicine has accelerated significantly in the last five years, catalyzed by the stark health inequities exposed by the COVID-19 pandemic.
- 2020: The pandemic serves as a national flashpoint, highlighting how structural racism influences health outcomes. Medical researchers begin to audit clinical algorithms for racial bias.
- 2021: A landmark year for reform. Major clinical labs and health systems begin the transition to race-free eGFR (estimated glomerular filtration rate) equations for kidney function. The pediatric urinary tract infection (UTI) risk calculator also removes race as a variable.
- 2022: The American Academy of Pediatrics (AAP) issues a formal policy statement calling for the elimination of race-based medicine. The AAP removes race as a risk factor in the management of neonatal hyperbilirubinemia, leading to improved, more equitable care standards.
- 2025: The American Heart Association (AHA) and the American College of Cardiology end nearly four decades of race-based prescribing guidelines for hypertension, moving away from recommendations that prioritized specific drugs based on a patient’s race.
- 2026: Ongoing studies continue to analyze the long-term impacts of these changes, confirming that removing race often yields equal or superior diagnostic accuracy while reducing systemic bias.
Supporting Data: Why the Shift Matters
The impact of these changes is quantifiable. In the case of the Vaginal Birth After Caesarean (VBAC) risk calculator, removing race in 2021 resulted in a significant reclassification for Black and Hispanic patients. Previously, these patients were often discouraged from attempting a VBAC because the algorithm artificially lowered their projected success rates. Once the bias was removed, their calculated success rates aligned with clinical reality, offering patients more autonomy and access to safer birth options.
Similarly, the adoption of race-free eGFR equations for kidney disease has been a victory for equity. Historically, Black patients were "penalized" by formulas that assumed higher baseline muscle mass, often delaying their placement on transplant waiting lists. By removing race, the new equations ensure that patients are evaluated based on their actual physiology, not a demographic label.
However, data also shows that this is not a panacea. A March 2026 study indicated that even with improved kidney risk assessments, overall transplant rates for Black patients have not yet fully closed the gap, suggesting that structural issues—such as access to specialized follow-up care—remain as major, unaddressed hurdles.
Official Responses and Institutional Reform
The American Medical Association (AMA) has taken a proactive stance, committing to "redress the harms" caused by the historical misuse of race in medicine. Many medical societies are currently conducting audits of their existing guidelines.

However, the path forward is not without tension. Some clinicians argue that removing race entirely blinds providers to the very real impact of systemic racism on health. They contend that if race is removed from a model, it must be replaced by more precise social determinants of health (SDOH)—such as housing stability, zip code, and environmental exposure. Without these variables, there is a fear that medicine might ignore the "lived experience" of patients who are navigating a society where race continues to dictate social and economic outcomes.
The challenge, according to many health policy experts, is that while we are removing the "race variable," we are currently failing to collect robust data on the "racism variable."
The Implications of Future Funding and AI Integration
As the medical community refines its approach, two major external forces are shaping the future: federal policy and artificial intelligence.
The Funding Crisis
The current landscape of disparities research is increasingly fragile. Recent federal budget cuts to diversity and equity-related research are causing deep concern. If the medical community loses the ability to track health outcomes by race, it will be impossible to measure whether the transition to race-free medicine is actually helping or if it is inadvertently masking new disparities. Researchers warn that "colorblind" data collection often leads to "colorblind" policy, which typically fails the most vulnerable populations.
The AI Dilemma
The rise of Artificial Intelligence in health care presents a double-edged sword. On one hand, AI can analyze vast datasets to identify patterns that human clinicians might miss, potentially revealing health inequities in real-time. On the other hand, AI models are trained on historical data. If that data is saturated with the biases of the last 50 years of "race-based" medicine, the AI will likely learn and amplify those prejudices.
The consensus among experts is clear: AI must be designed with "inclusive data." This means moving away from homogeneous clinical trials and intentionally recruiting diverse patient cohorts. Without this, the next generation of clinical decision-making tools risks automating the same racial biases that the medical community is currently trying to dismantle.
Conclusion: A More Nuanced Path Forward
The movement to remove race from clinical decision-making is not merely a bureaucratic change; it is a fundamental shift toward evidence-based, patient-centered care. By acknowledging that race is a proxy for structural inequality rather than biological destiny, medicine is reclaiming its scientific rigor.
Yet, the work is far from complete. Removing race from a calculator is the first step, not the last. The future of medicine requires a dual commitment: first, to ensure that clinical tools are accurate and unbiased; and second, to aggressively invest in research that illuminates the impact of structural racism on health. We must ensure that in our rush to remove race from our algorithms, we do not ignore the persistence of racism in our society. Only by addressing the root causes of health disparities—rather than using race as a shortcut to define them—can the medical community truly achieve equitable outcomes for all patients.
About the Author