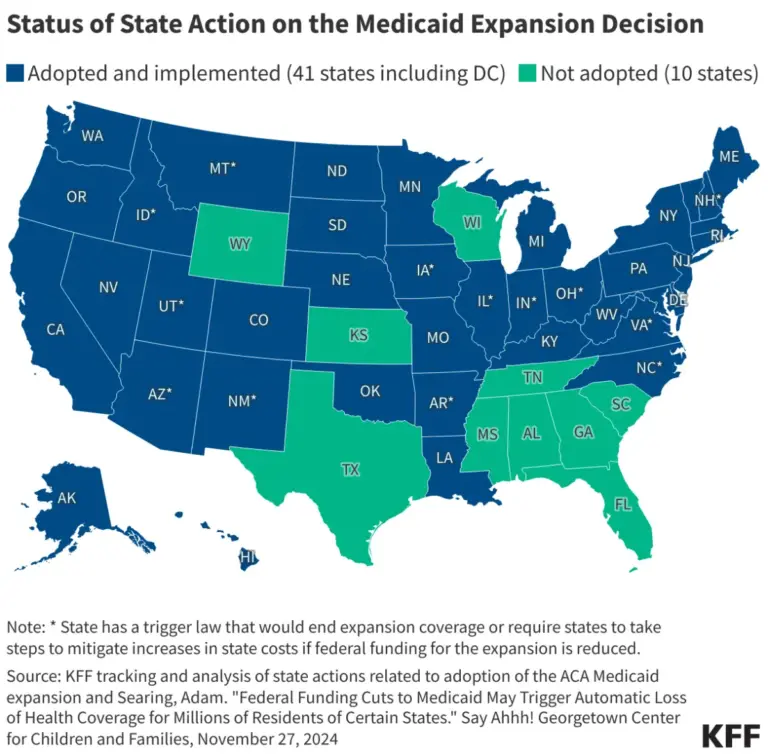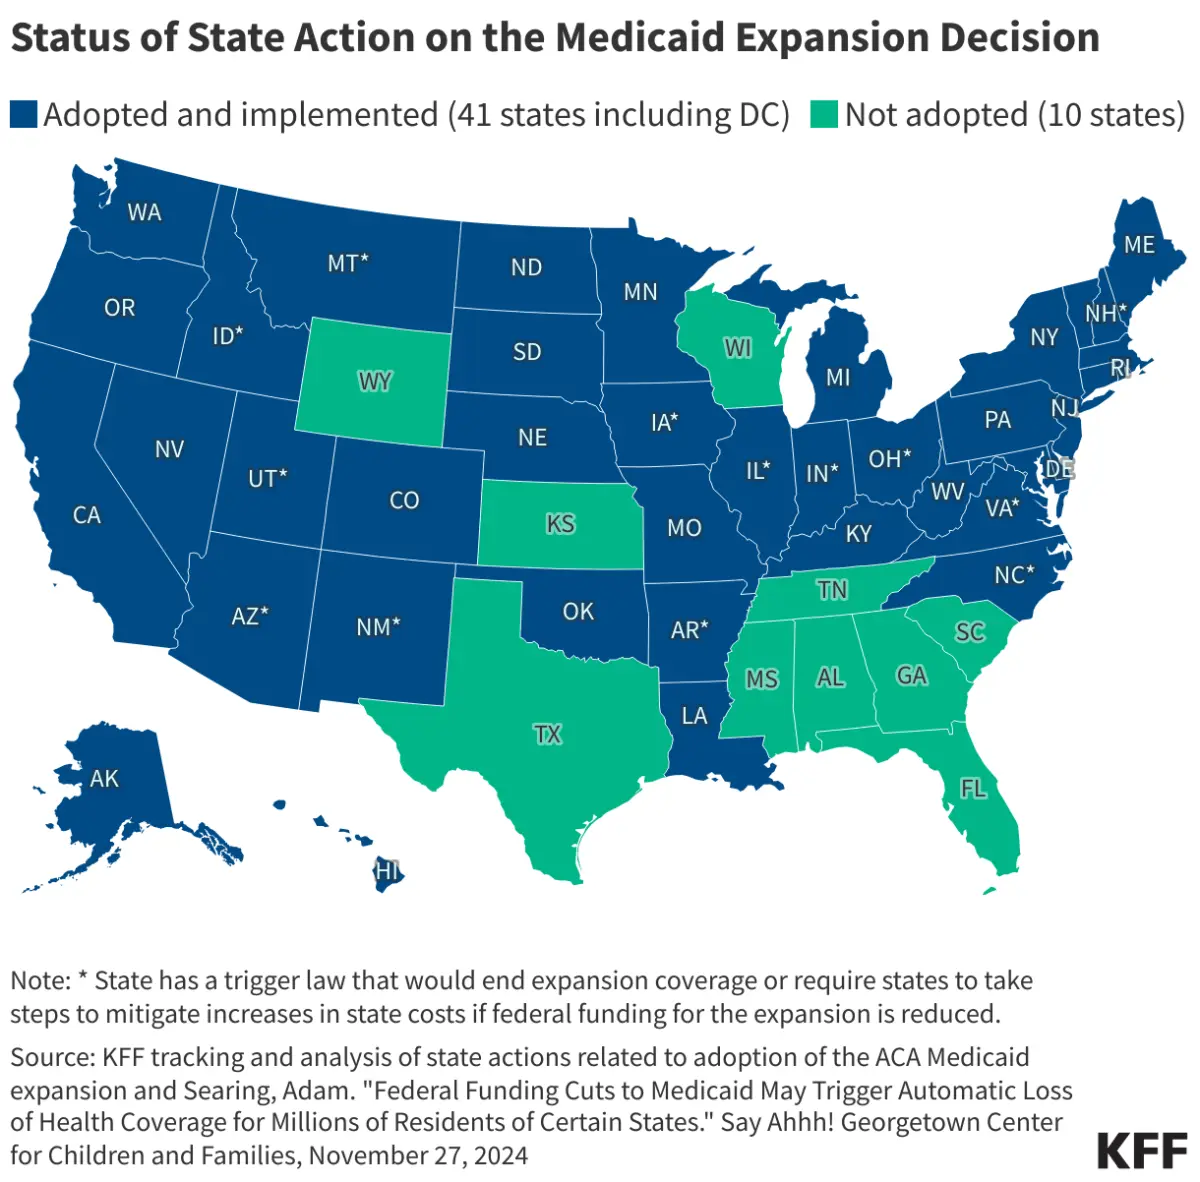
More than a decade after the Affordable Care Act (ACA) was signed into law, the landscape of American public health coverage remains defined by a stark, state-by-state patchwork. At the heart of this divide is the Medicaid expansion—a policy designed to close the "coverage gap" by extending eligibility to nearly all adults with incomes up to 138% of the Federal Poverty Level (FPL). As of 2025, that threshold translates to an annual income of $21,597 for an individual. While the federal government provides an enhanced federal matching rate (FMAP) to incentivize states to adopt the program, the decision ultimately rests with individual state legislatures and executive branches. Today, 41 jurisdictions, including the District of Columbia, have embraced the expansion, while 10 states remain holdouts, leaving millions of low-income Americans in a precarious position regarding access to essential healthcare.
The Mechanics of Expansion: A Fiscal and Social Lever
The ACA’s Medicaid expansion was intended to be the cornerstone of a nationwide safety net. By raising the income eligibility limit, the federal government sought to ensure that individuals who earn too much to qualify for traditional Medicaid but too little to afford private insurance could access comprehensive coverage.
The federal government’s offer was designed to be generous. Under the law, the federal government covers 90% or more of the costs for the expansion population. This enhanced FMAP has served as a primary fiscal motivator for states, many of which have seen improved economic health and reduced uncompensated care costs for hospitals as a result of enrolling more citizens into the program. Despite these financial incentives, the political polarization surrounding the ACA has meant that adoption has been far from universal.
A Chronology of Policy Evolution
The history of Medicaid expansion is not a single narrative but a series of regional developments spanning over a decade.
2010–2012: The Foundation and the Supreme Court
The Affordable Care Act was enacted in 2010, aiming for a nationwide expansion of Medicaid. However, the 2012 Supreme Court ruling in National Federation of Independent Business v. Sebelius fundamentally altered the trajectory of the law. The Court held that the federal government could not coerce states into expanding Medicaid by threatening to withhold existing federal funding. This effectively rendered the expansion optional for states, creating the current fragmented map.
2013–2018: The First Wave of Adoption
Following the ruling, a group of states—primarily those with Democratic leadership—moved quickly to expand. By 2015, the benefits of the expansion, including billions in federal dollars flowing into state economies, began to persuade even some states with Republican governors. This era saw a "pragmatic" wave of adoption, where states like Ohio and Indiana implemented expansion models tailored to their specific political preferences, often utilizing Section 1115 waivers to include work requirements or premiums.
2019–2024: The Grassroots and Ballot Initiative Era
As legislative avenues stalled in the remaining holdout states, advocates turned to the ballot box. Voter-led initiatives became a powerful tool for bypassing skeptical state legislatures. States like Idaho, Nebraska, Utah, and Oklahoma successfully expanded through citizen-initiated ballot measures. These victories shifted the momentum, forcing conservative lawmakers to engage with the reality that their constituents overwhelmingly supported expanding access to care.
2025 and Beyond: The "Trigger Law" Era
The current focus has shifted from initial adoption to the stability of existing programs. Many states have implemented "trigger laws"—statutes that mandate the termination or significant reduction of Medicaid expansion if the federal government reduces its share of the funding (the FMAP). This creates a volatile environment where the health coverage of millions is tied to federal budget negotiations.
Supporting Data: Mapping the Current Status
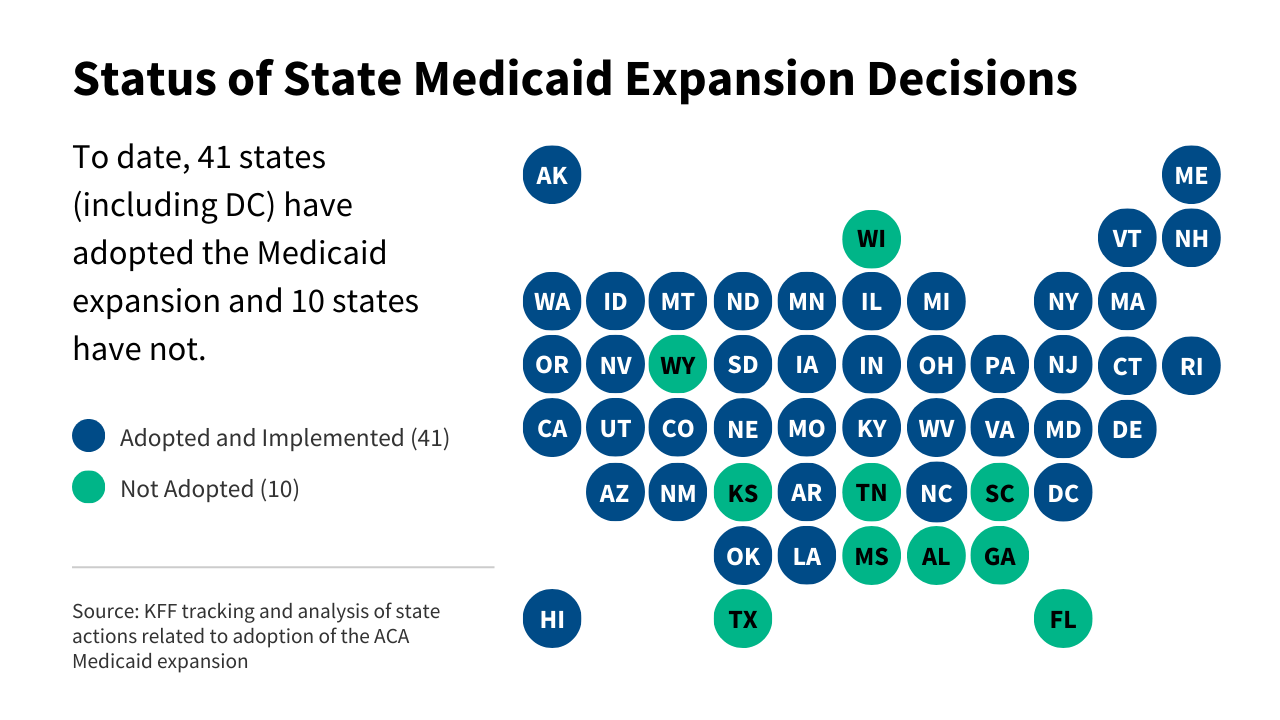
As of the latest tracking by KFF, the map of the United States remains divided. The 41 expansion states are concentrated largely along the coasts and throughout the Northeast and Midwest, while the 10 non-expansion states form a contiguous block primarily in the South and the Great Plains.
The Fiscal Reality
The data shows that states that have expanded Medicaid have experienced significant improvements in public health metrics. Hospitals in these states, particularly in rural areas, report lower rates of uncompensated care. Conversely, the 10 states that have not expanded leave an estimated 1.5 to 2 million people in a "coverage gap," where they earn too little to qualify for subsidized marketplace plans but too much to qualify for traditional Medicaid.
Legislative and Executive Trends
Tracking current activity reveals a complex landscape:
- Legislative Actions: Several states have seen bills introduced that would expand the program, often stalling in committee or facing executive vetoes.
- Budgetary Threats: In states like Virginia, debates have emerged regarding the long-term sustainability of the expansion, with some lawmakers proposing to tie the program’s future to federal funding levels.
- Trigger Law Controversies: The inclusion of trigger laws in state budgets has become a flashpoint. While some states look to strengthen these triggers to protect their general funds, others are debating whether to remove them entirely to provide stability for enrollees.
Official Responses and Political Discourse
The political rhetoric surrounding the Medicaid expansion remains as polarized as it was in 2010.
Proponents’ Arguments
Public health advocates, hospital associations, and many Democratic lawmakers argue that expansion is a moral and economic imperative. They point to the "health-wealth" connection: a healthier population is a more productive workforce. Furthermore, they argue that the federal government’s 90% match makes expansion the most cost-effective way to improve health outcomes, particularly for those suffering from chronic illnesses or substance use disorders.
Opponents’ Perspectives
Opponents, largely concentrated in the remaining non-expansion states, cite concerns over the long-term fiscal liability for states. There is a persistent fear that federal funding will eventually be cut, leaving states to foot the bill for an expanded population they cannot afford to cover. Additionally, some conservative lawmakers argue that Medicaid expansion encourages dependency on government programs rather than private market participation.
The Role of Section 1115 Waivers
The debate has increasingly centered on "flexibility." States are increasingly seeking Section 1115 waivers to add "guardrails" to the expansion, such as work requirements, health savings accounts, or time limits. While the Centers for Medicare & Medicaid Services (CMS) has historically been cautious about approving these, the ongoing dialogue reflects a middle ground where states seek to implement the expansion while maintaining conservative policy principles.
Implications for the Future of Public Health
The implications of the current status quo are profound. For the individuals living in non-expansion states, the lack of coverage is not merely a statistical outlier—it is a daily reality characterized by deferred screenings, untreated chronic conditions, and the ever-present threat of medical bankruptcy.
The Rural Healthcare Crisis
Perhaps the most significant implication of the non-expansion status is the destabilization of rural hospitals. Without the revenue provided by the Medicaid expansion, many rural medical facilities operate on razor-thin margins. When these hospitals close, they take with them not only medical services but also a primary driver of the local economy.
Federal-State Relations
The "trigger law" phenomenon signals a broader shift in federalism. States are increasingly insulating themselves against perceived federal instability. If federal funding for the ACA were to be restructured or reduced, the ripple effects would be felt immediately through state-level automatic coverage terminations, potentially leaving millions without insurance overnight.
The Path Forward
As we move further into 2025, the focus will likely remain on the remaining 10 states. Political analysts suggest that the next wave of expansion will not come from traditional legislative sessions but from continued pressure through voter-led initiatives. Furthermore, the role of the federal government in incentivizing the remaining holdouts remains a central theme. Proposals to increase the federal matching rate further—or to offer "bonus" payments for new expansion states—are frequently discussed in Washington as a means to finally achieve universal adoption.
Conclusion
The ACA Medicaid expansion stands as a testament to both the success and the limitations of American health reform. While it has successfully provided coverage to tens of millions of people and stabilized the finances of the healthcare safety net, the 10-state holdout persists as a significant hurdle. The future of the program rests on a delicate balance between federal fiscal policy and state-level political willpower. Whether the remaining states eventually join the fold, or whether the current patchwork remains a permanent fixture of the American health system, the impact of these decisions will continue to be measured in the lives and health of millions of citizens. As the data suggests, the debate is far from settled, and the movement for universal access to healthcare continues to evolve in response to the shifting political and economic realities of the 21st century.
About the Author