Editorial Note: This report, originally published on January 13, 2026, serves as a comprehensive tracking resource for the implementation of the U.S. government’s new bilateral global health framework. This document was most recently updated on November 6, 2026, to incorporate the latest data and emerging trends in diplomatic health cooperation.
Executive Summary: A Fundamental Shift in Global Health Diplomacy
In September 2025, the United States government unveiled its "America First Global Health Strategy," a policy pivot that effectively redraws the landscape of international health assistance. Moving away from traditional, open-ended aid models, the strategy mandates the establishment of bilateral Memoranda of Understanding (MOUs) with partner nations. These five-year agreements (2026–2030) are designed to transition countries from reliance on U.S. funding toward sustainable, domestic ownership of their national health systems.

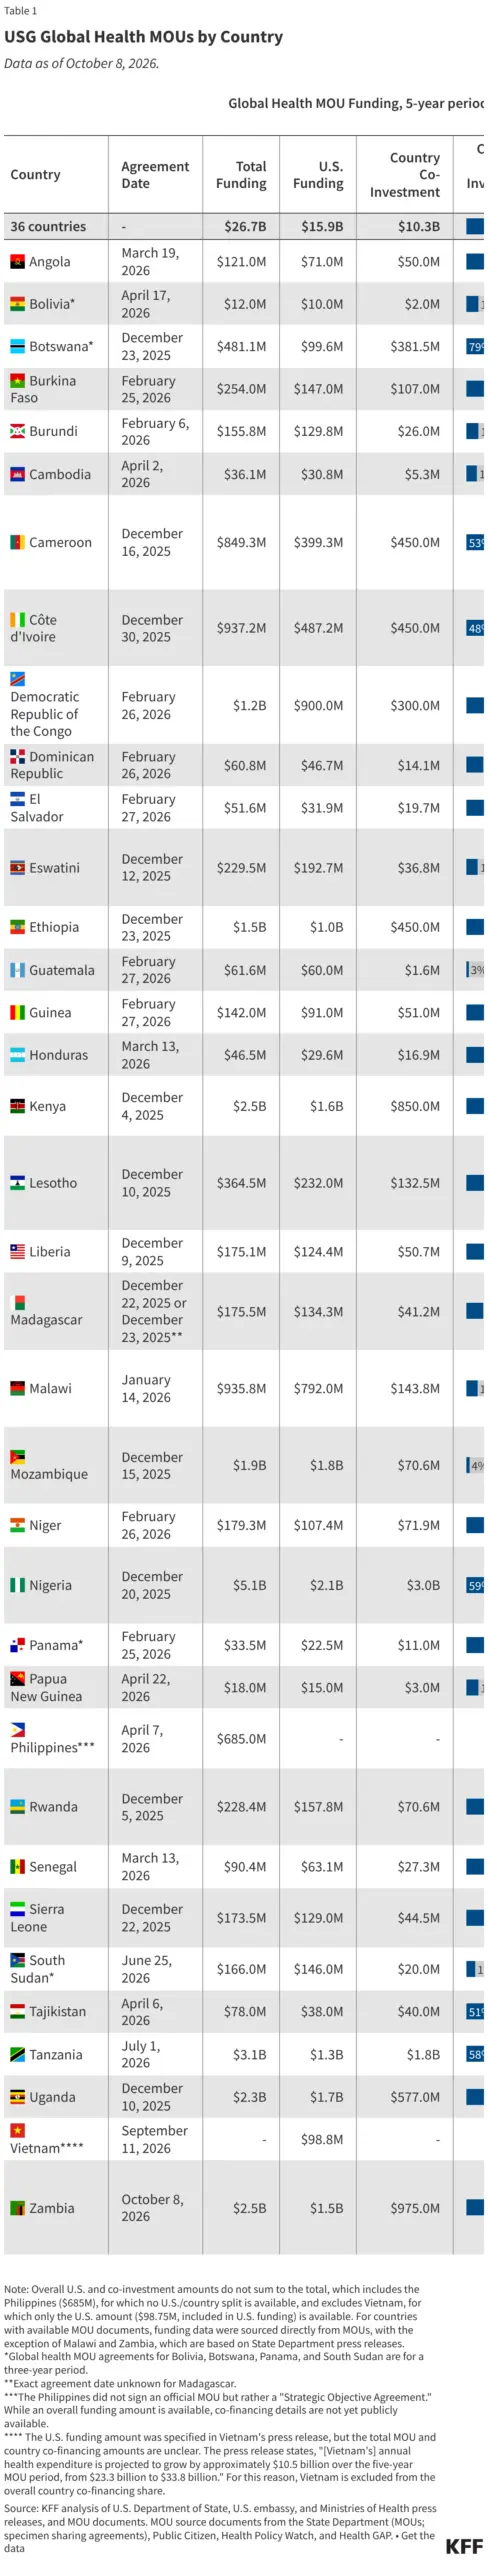
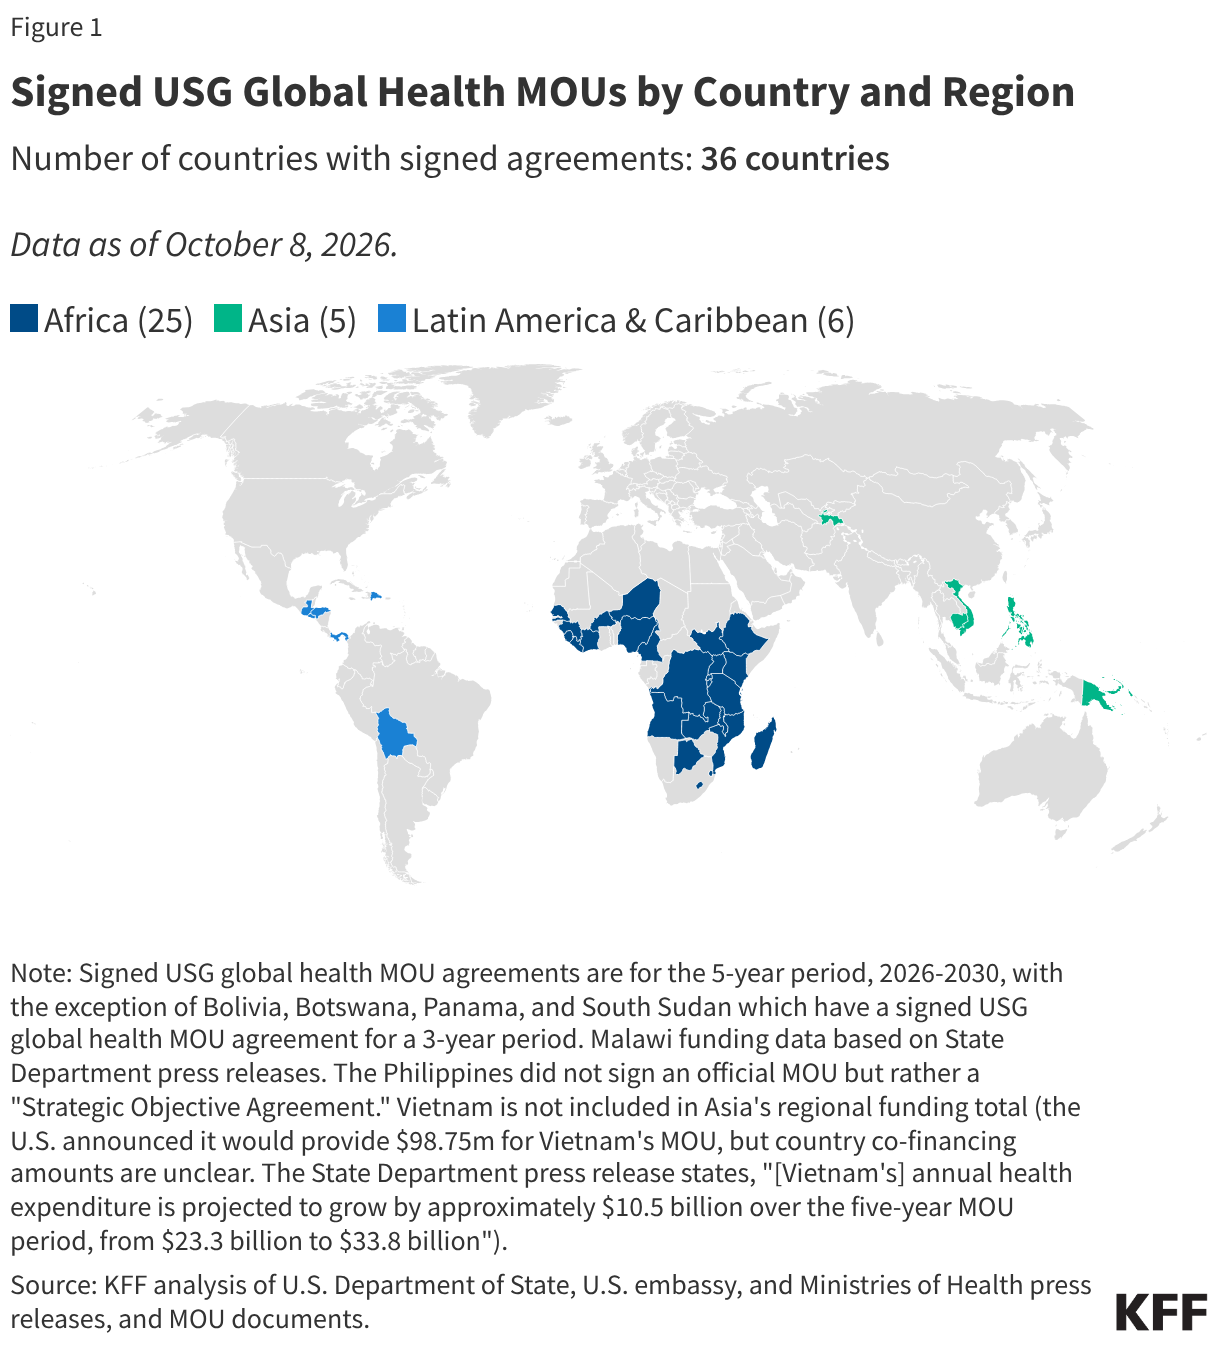
As of November 2026, the U.S. has formalized agreements with 36 nations across Africa, Latin America, the Caribbean, and Asia. This transition represents a significant reallocation of resources, totaling $26.7 billion in combined U.S. and partner-country investments. However, the data reveals a stark reality: while the goal is "resilient and durable health systems," the strategy carries a notable reduction in direct U.S. financial commitment, signaling a new era of "co-investment" where partner nations are expected to pick up an increasingly large share of the fiscal burden.
The Chronology of Implementation
The rollout of the America First Global Health Strategy has been rapid and systematic. Following the official policy launch on September 18, 2025, the State Department initiated a global diplomatic push to codify these new expectations into binding legal frameworks.

- Late 2025: The first wave of MOUs was signed, setting the precedent for the 2026–2030 cycle. Initial agreements focused on long-standing regional partners, emphasizing immediate structural alignment.
- Early–Mid 2026: The implementation phase began. As the transition took hold, observers noted the varied pace of adoption. While most nations signed standard MOUs, others—such as the Philippines—opted for "Strategic Objective Agreements," reflecting unique geopolitical considerations.
- October 2026: The most recent data synthesis confirms 36 active agreements. The process remains ongoing, with the State Department and partner Ministries of Health continuing to negotiate the final terms for additional nations.
Supporting Data: The Fiscal Landscape
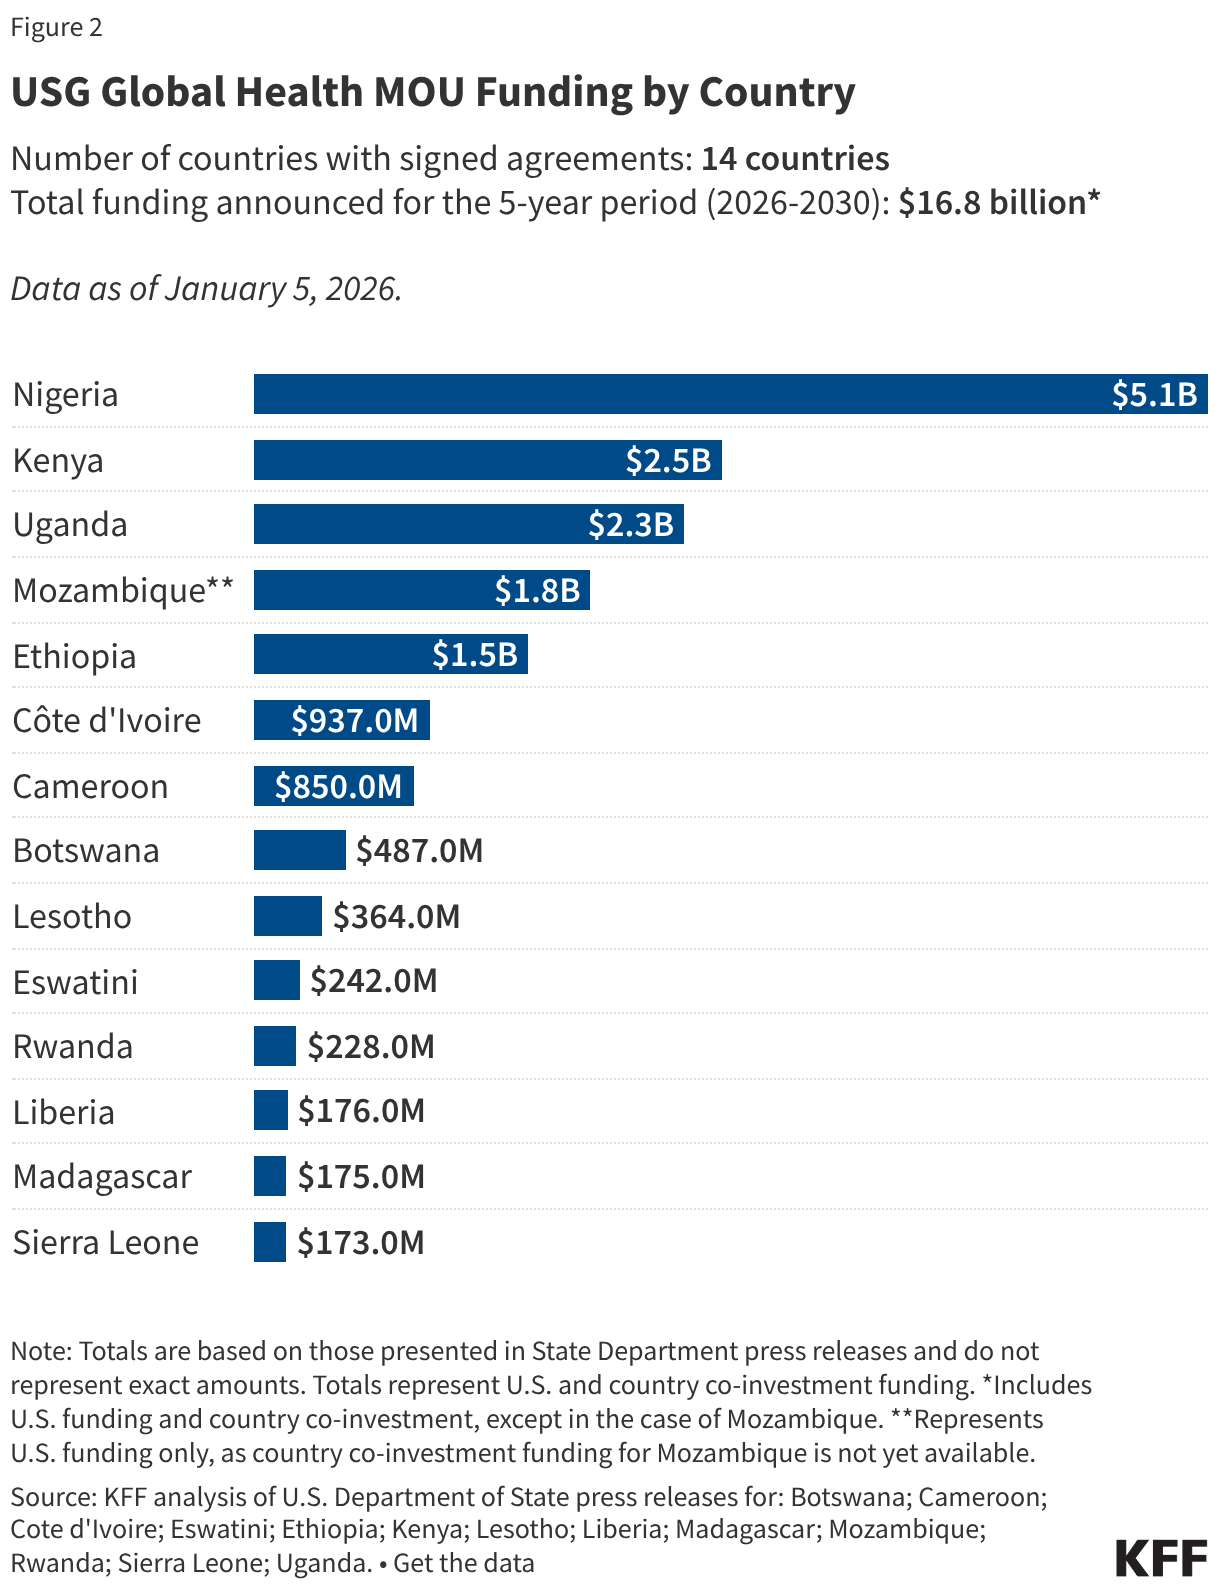
The core of the strategy is built upon the premise of shared fiscal responsibility. According to current projections, the total funding allocated across the 36 signed agreements stands at $26.7 billion.
The Breakdown of Co-Investment
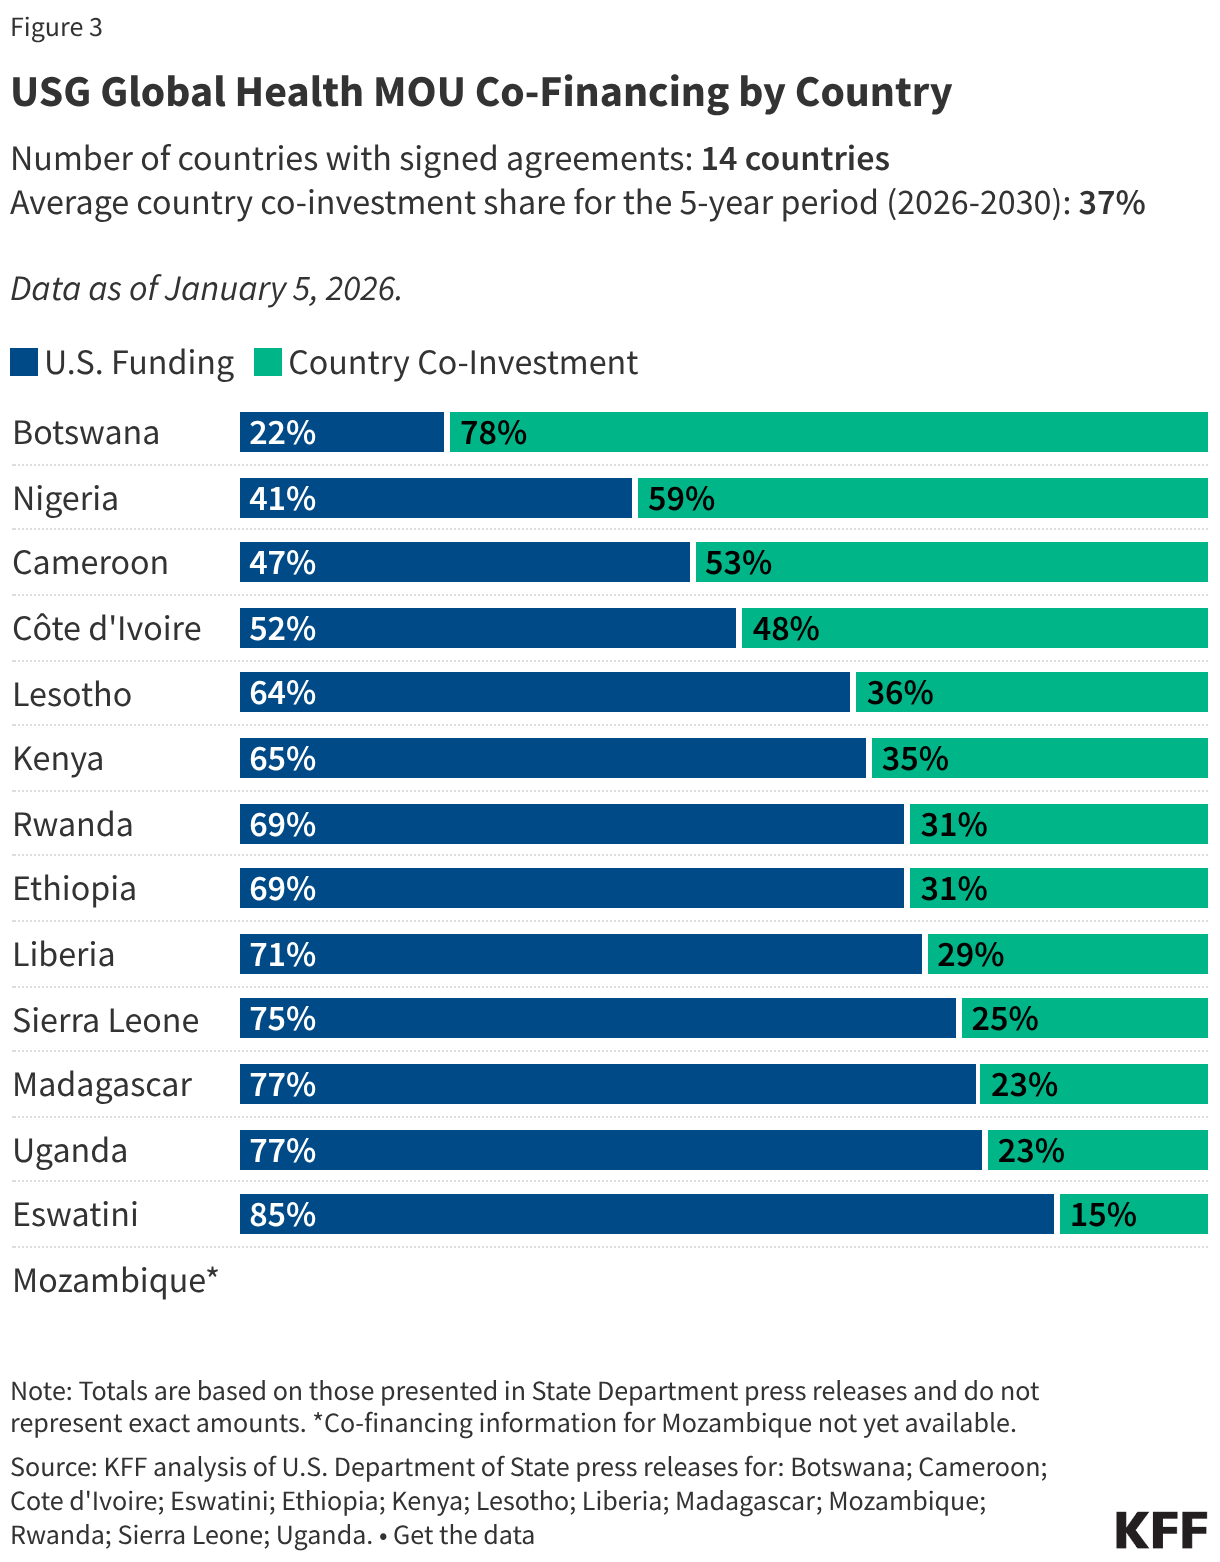
The transition model relies heavily on partner-country participation. Of the total $26.7 billion pool, $15.9 billion is contributed by the U.S., while partner countries are committed to $10.3 billion in domestic co-investment. This establishes an overall co-investment share of 39%.
However, the burden is not distributed evenly. The range of co-investment required from partner nations varies dramatically—from as low as 3% to as high as 79%—depending on the economic capacity and health system maturity of the host nation.
Funding Contraction
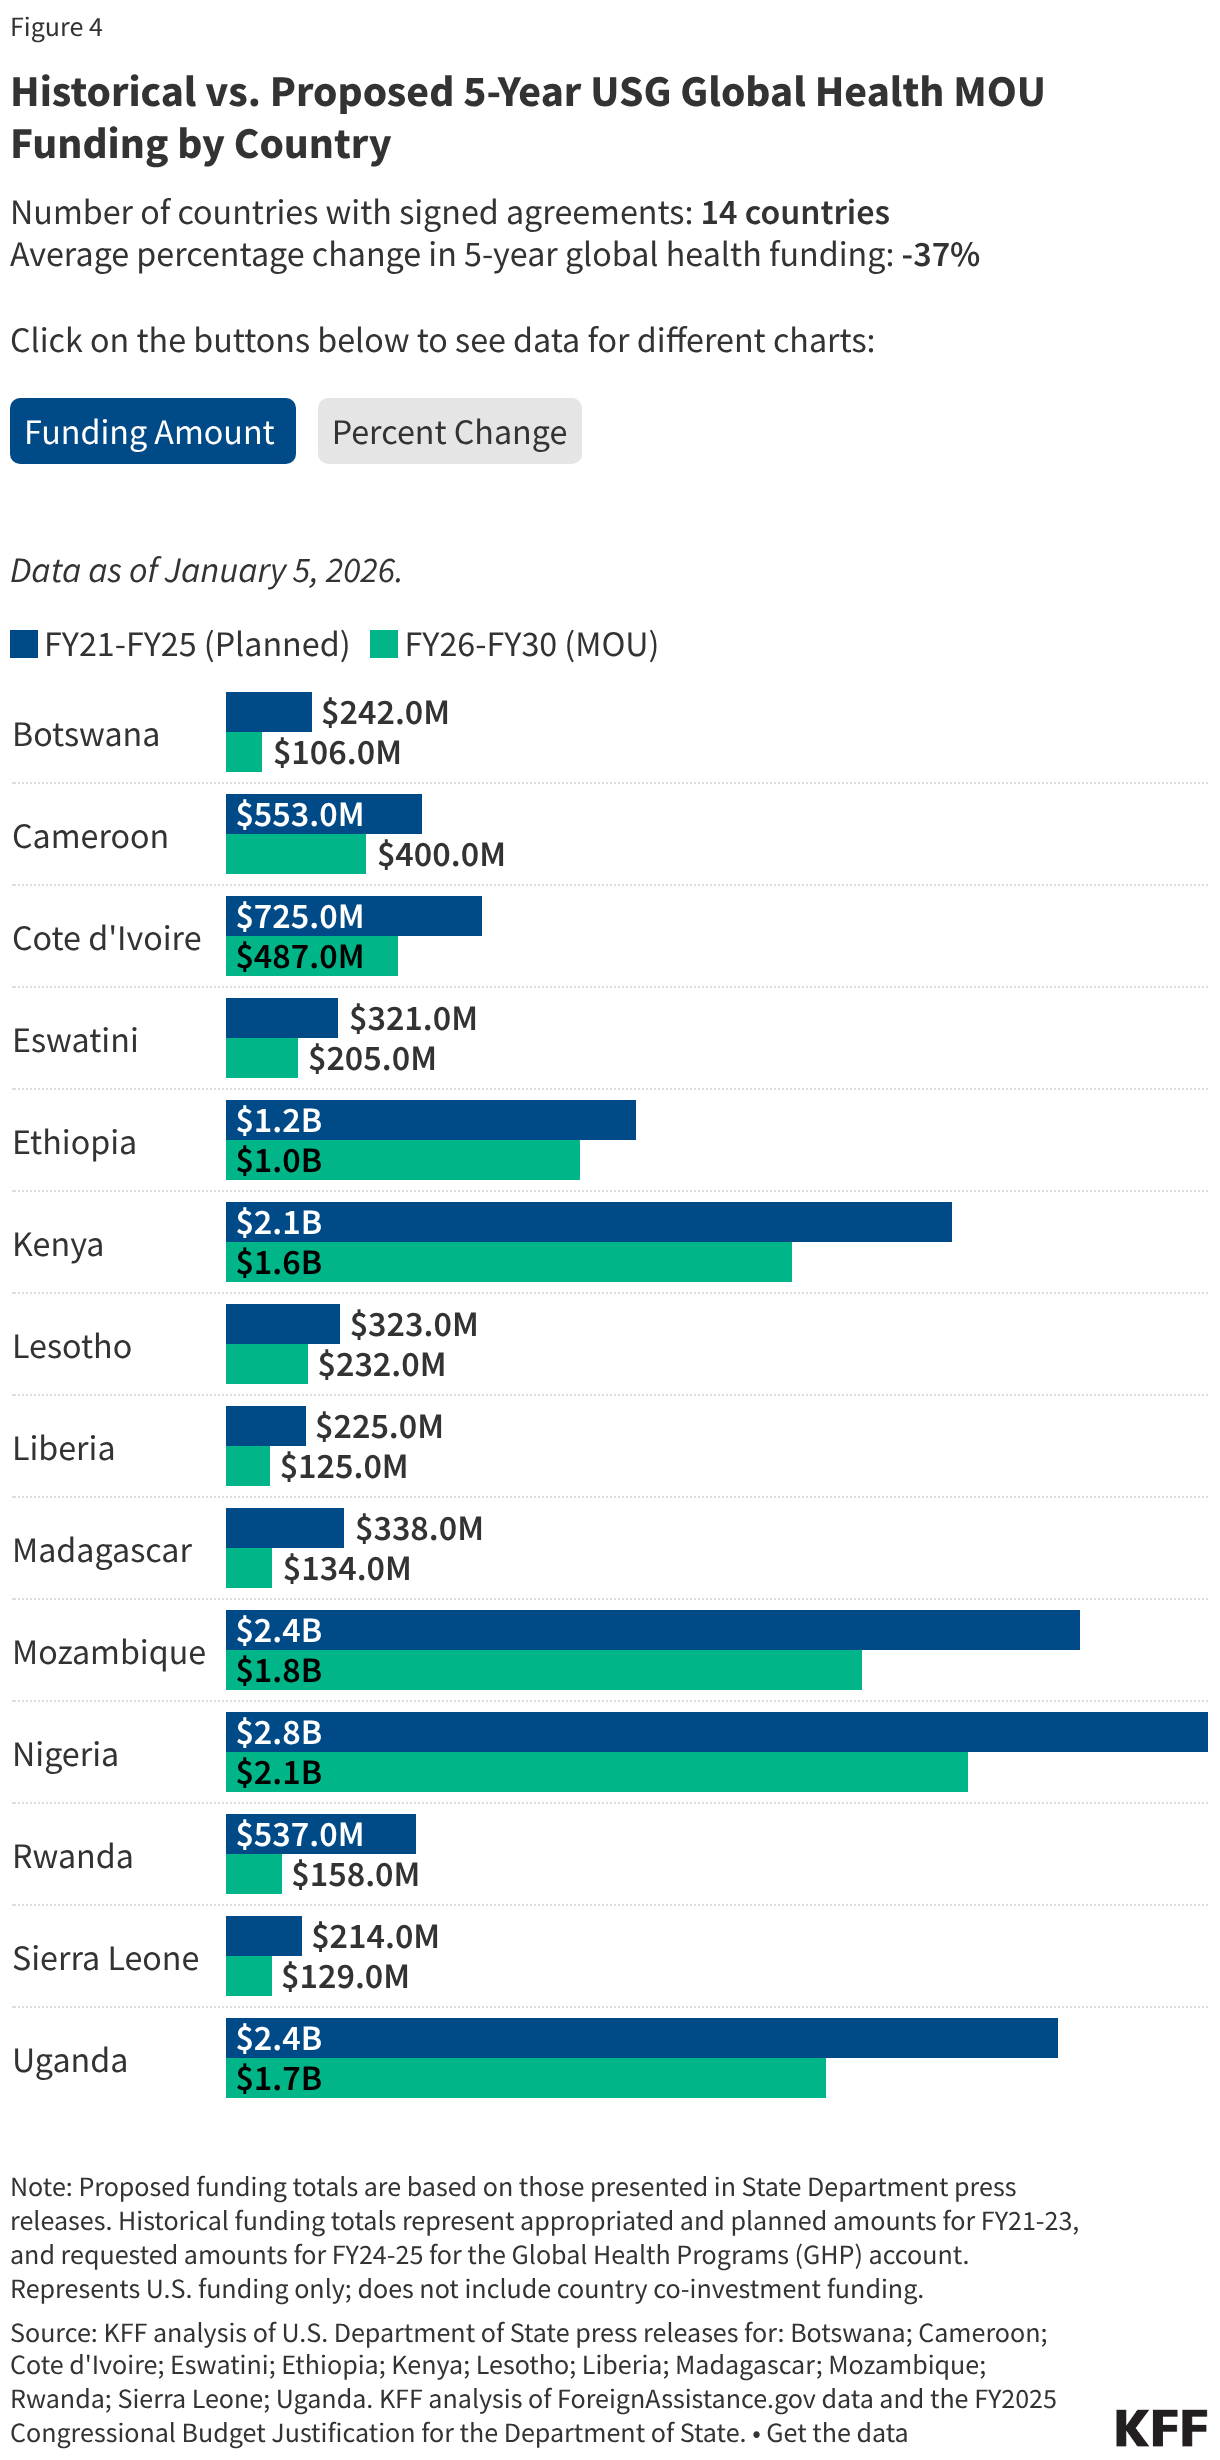
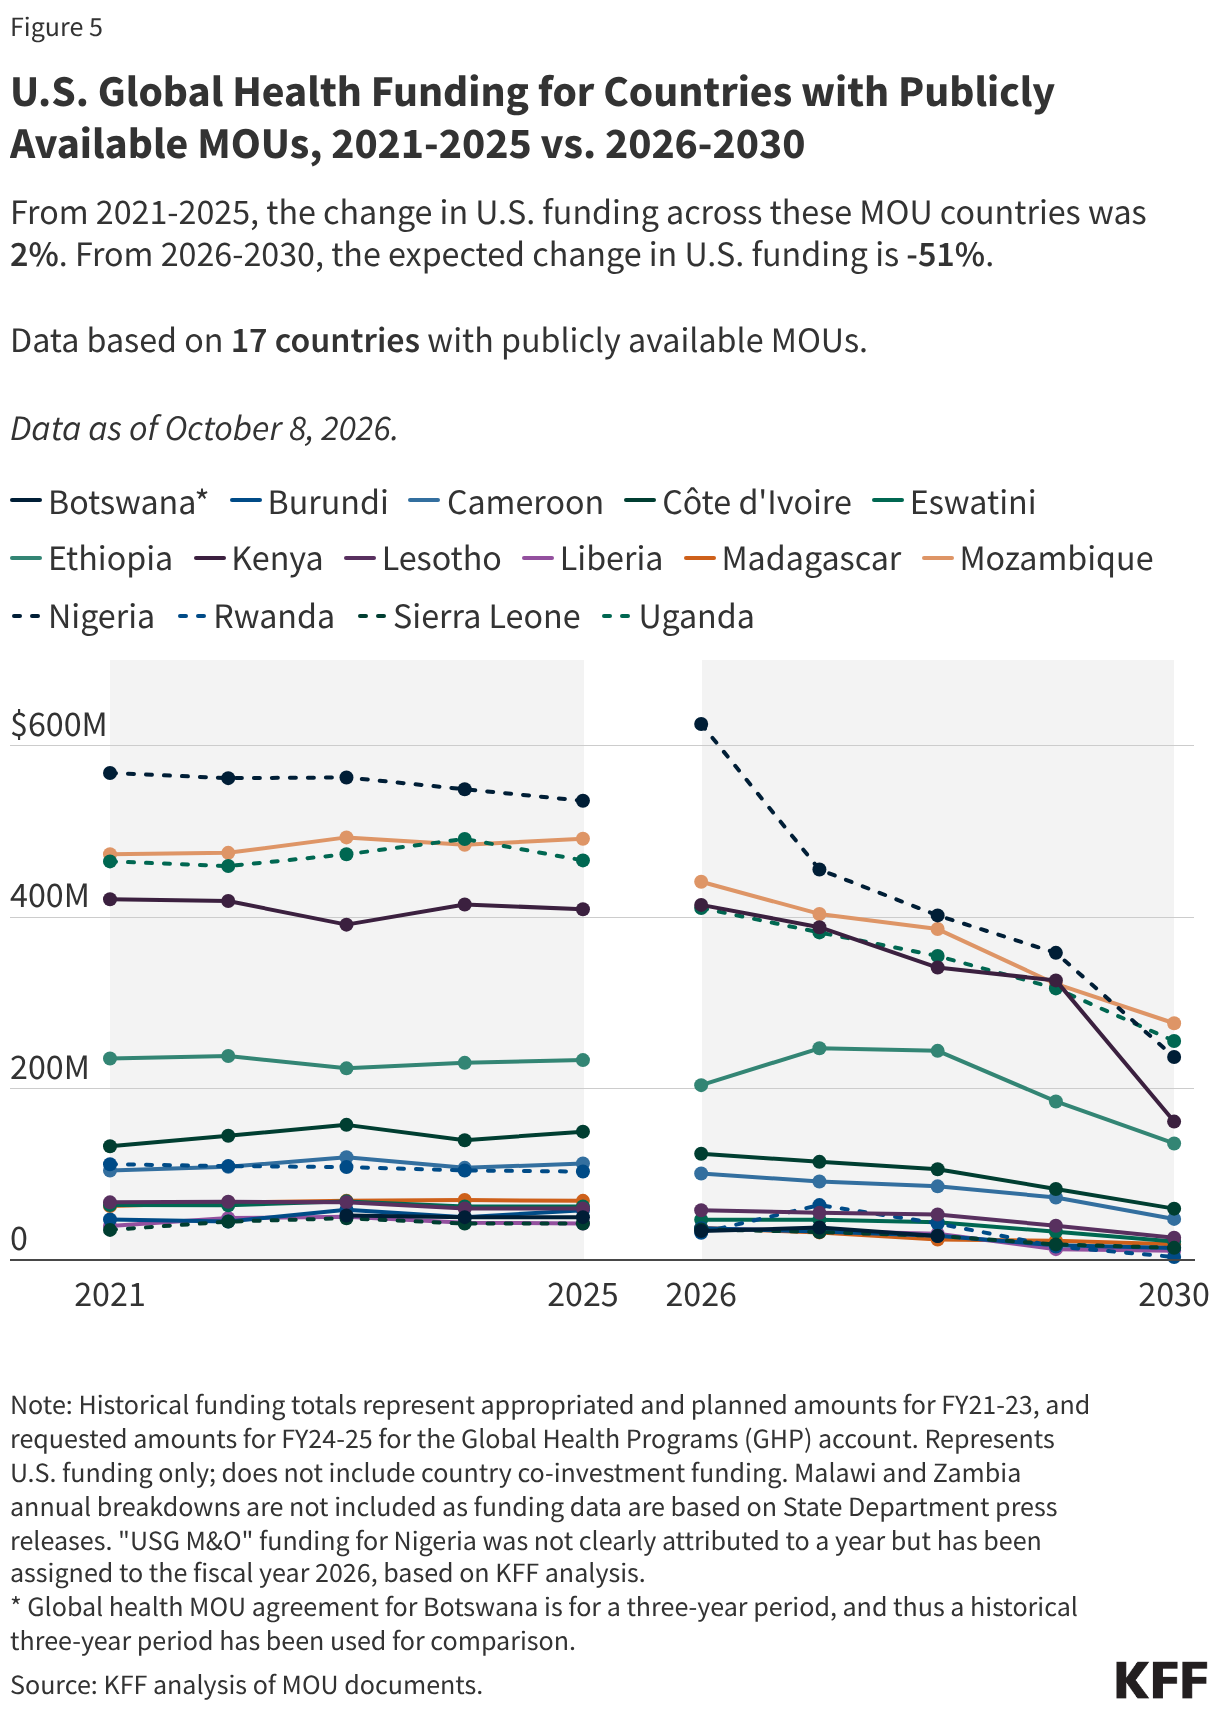
Perhaps the most controversial aspect of the data is the net decline in U.S. support. Compared to the historical funding levels of the 2021–2025 period, the proposed U.S. commitment for 2026–2030 represents a decrease of $8.1 billion, or approximately 34%. This suggests that the "America First" policy is not merely a structural reorganization but a deliberate contraction of U.S. global health expenditure, predicated on the belief that partner countries can and should fill the void.
The Mechanics of the Agreements
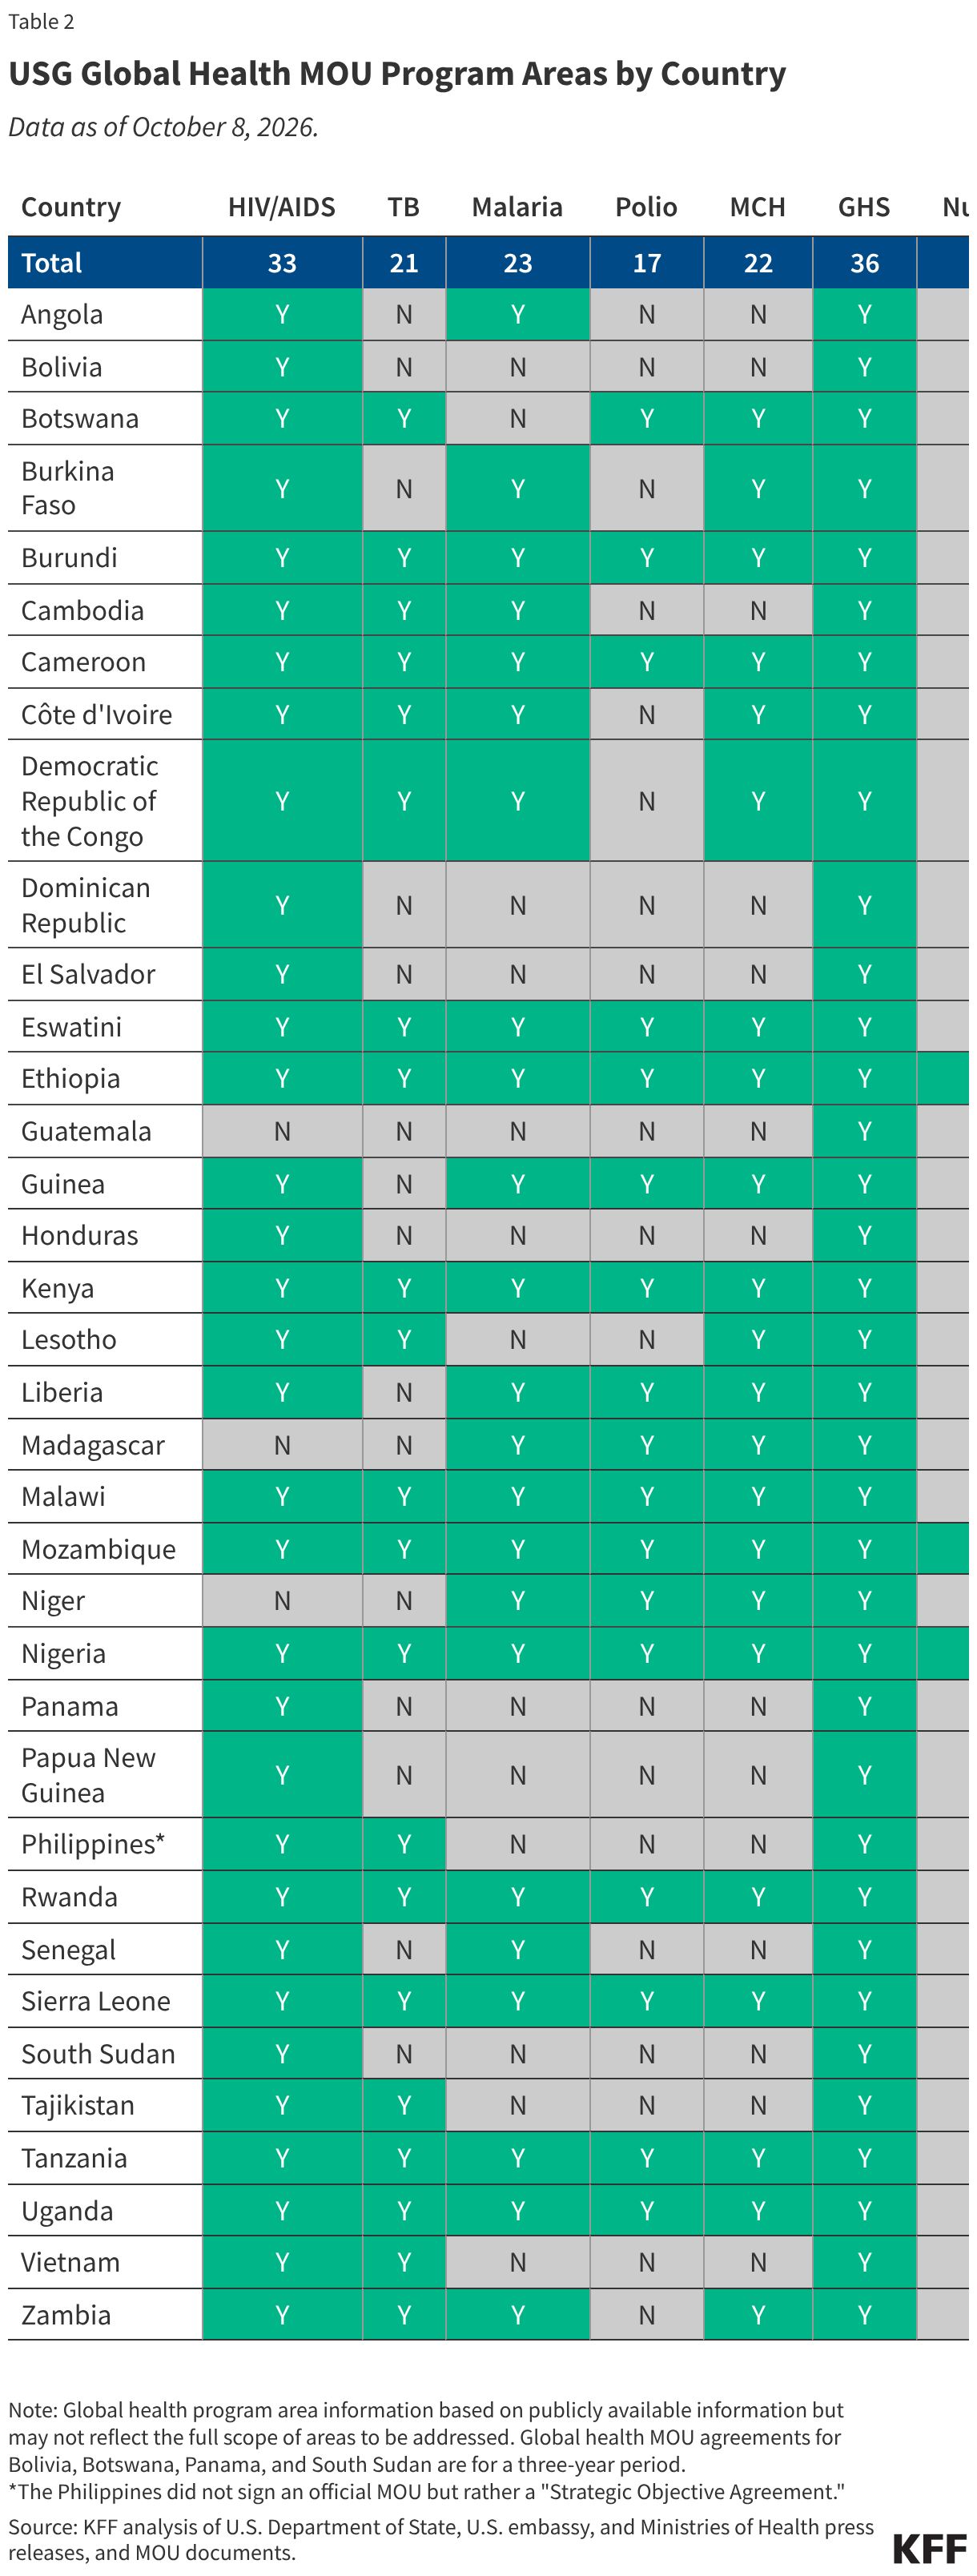
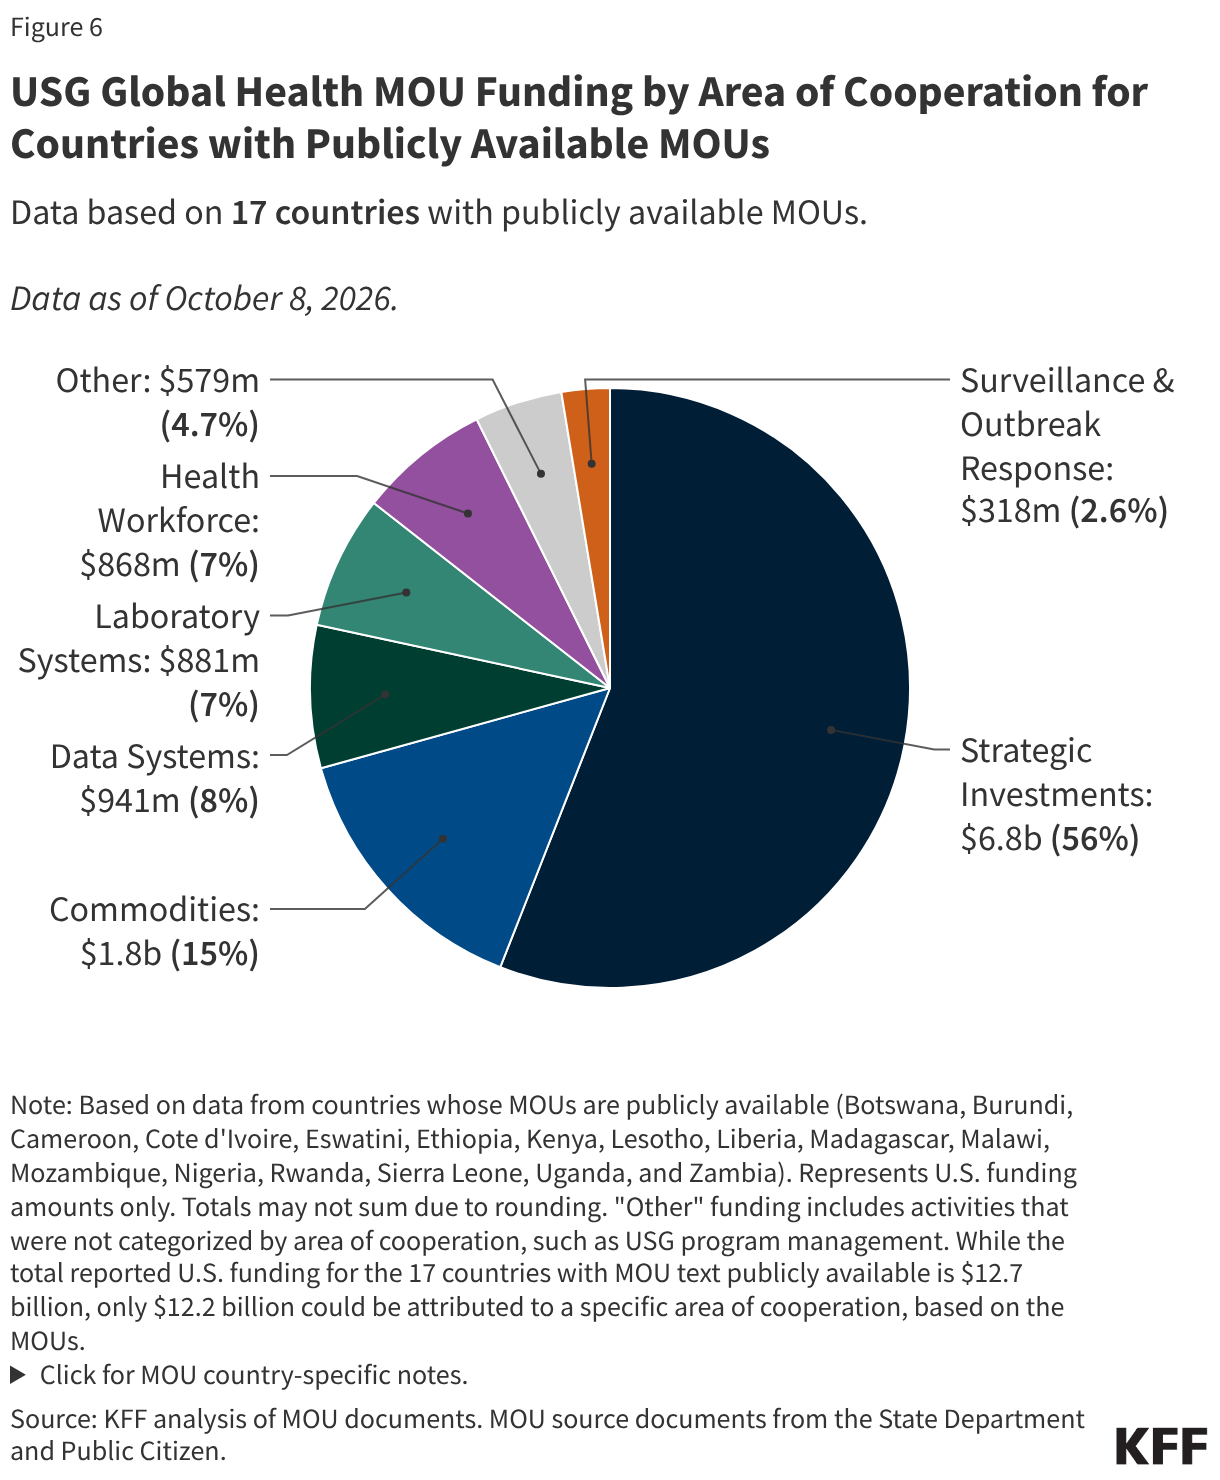
To understand how these funds are allocated, one must look at the six pillars of cooperation defined within the MOUs. These categories serve as the blueprint for how the U.S. envisions a "resilient" health system:
- Surveillance & Outbreak Response: Targeting the rapid detection of pathogens to prevent local crises from becoming global pandemics.
- Laboratory Systems: Focused on both commodities and the professional development of lab technicians.
- Commodities: A broad category covering essential medicines and medical supplies, excluding laboratory-specific items.
- Health Workforce: Dedicated to the recruitment, training, and retention of frontline healthcare workers.
- Data Systems: Investing in the digital infrastructure required to manage patient records and health metrics.
- Strategic Investments: A catch-all for technical assistance and high-level policy guidance.
Data indicates that the prioritization of these areas varies by region. For instance, nations with significant infectious disease burdens are seeing a heavier focus on Surveillance and Lab Systems, whereas nations with more established health systems are seeing funds shift toward Strategic Investments and Data Systems.
Official Perspectives and Skepticism
The State Department maintains that this shift is essential for long-term global stability. By forcing a transition to domestic funding, the U.S. argues it is preventing the "aid trap" where countries remain perpetually dependent on external support. Officials describe the MOUs as "roadmaps to independence," suggesting that by 2030, these nations will have the institutional capacity to manage their own public health crises without the need for significant U.S. intervention.
Conversely, public health advocates and some international analysts have expressed concern regarding the 34% reduction in U.S. funding. The primary critique is that the transition to domestic ownership may be occurring too rapidly for some lower-income nations to absorb the cost. There is a palpable fear that if a partner country fails to meet its co-investment targets due to economic volatility, the resulting funding gap could lead to a collapse in essential services, such as HIV/AIDS care, malaria prevention, or routine childhood vaccinations.
Implications: The Road Ahead (2026–2030)
As we move deeper into the 2026–2030 cycle, the implications of this policy will be tested in real-time. Several key questions remain:
1. The Sustainability of Co-Investment
Will nations be able to sustain the projected increase in health expenditure? With many developing economies facing inflation, high debt, and fiscal instability, the ability to meet high co-investment thresholds (some reaching near 80%) remains the greatest variable in the success of these agreements.
2. The Data Transparency Gap
As noted in the tracker, there is a lack of clarity regarding whether "co-financing" amounts represent new funding or merely the reallocation of existing health budgets. If countries are simply shifting funds from one area to another to meet MOU requirements, the net improvement in health outcomes may be negligible.
3. Geopolitical Alignment
The decision to pursue these agreements via bilateral MOUs rather than multilateral channels (like the Global Fund or Gavi) underscores a desire for more direct U.S. control over foreign policy outcomes. This strategy allows the U.S. to tie health assistance more closely to specific bilateral diplomatic goals.
4. Risk of Service Interruption
Given that the U.S. is withdrawing $8.1 billion in aggregate funding, there is an inherent risk that the transition period will be marked by "service degradation." If the infrastructure for data, lab, and workforce development is not fully operational before the U.S. funding cuts take full effect, the resulting gap in care could have severe consequences for vulnerable populations.
Conclusion
The "America First Global Health Strategy" represents the most significant departure from U.S. global health policy in over two decades. By moving from a donor-grantee model to a co-investment partnership model, the United States is essentially betting that its partner nations are ready to step into the role of primary provider.
While the policy is logically consistent with the goal of fostering global self-reliance, the math of the current agreements suggests a period of significant fiscal tension. Whether these 36 nations will emerge with more resilient systems, or whether they will struggle to bridge the $8.1 billion gap left in the wake of the U.S. withdrawal, will define the success of this strategy. As the tracker continues to be updated with new MOU documents and performance data, the global health community will be watching closely to see if the promise of "durable systems" outweighs the reality of reduced financial support.
For more information, including detailed country-by-country breakdowns, visit the KFF global health tracker database.
About the Author