For decades, the American healthcare landscape has been defined by a stark divide between the public and private sectors. While Medicaid serves as the bedrock of coverage for millions of low-income individuals, the mechanisms governing how providers are paid—and, consequently, whether they choose to accept Medicaid patients—have long remained opaque.
States have historically held substantial flexibility in setting Medicaid payment rates. However, this autonomy has often resulted in a patchwork system where provider participation fluctuates wildly based on the adequacy of reimbursement. As of 2024, research indicated that Medicaid fees for select physician services hovered at approximately 75% of Medicare rates. This disparity creates a significant barrier to entry, as physicians are statistically less likely to accept new patients covered by Medicaid compared to those with private insurance or Medicare.
In a landmark shift, the Centers for Medicare & Medicaid Services (CMS) finalized new transparency provisions in 2024 that represent the most significant effort to date to demystify Medicaid reimbursement. With these rules now taking effect as of July 2026, the era of "black box" pricing in Medicaid is coming to an end.
The Chronology of Reform: A Multi-Year Implementation
The journey toward this transparency milestone began with the realization that policymakers and researchers lacked the fundamental data necessary to improve access to care.
- Pre-2024: States operated with minimal oversight regarding the publication of fee schedules, leading to a fragmented system where comparing cross-state provider rates was nearly impossible.
- 2024: CMS finalized the Ensuring Access to Medicaid Services rule, focusing on fee-for-service (FFS) transparency, alongside a companion rule targeting managed care access and finance.
- July 1, 2026: The core FFS transparency requirements went into effect. States were mandated to publish comprehensive fee schedules online and complete the first round of comparative rate analyses.
- January 1, 2028: This date marks the deadline for the inclusion of new managed care analyses within the formal Network Adequacy and Access Assurances Reports, ensuring that the transparency mandate extends beyond traditional FFS models.
Main Facts: What the New Rules Require
The 2024 rules distinguish between Fee-for-Service (FFS) models—where the state pays the provider directly—and Managed Care (MCO) models, where the state pays a private health plan to manage the provider network. Because 42% of Medicaid spending is attributed to FFS and 53% to managed care (as of FY 2024), the regulations target both sectors to ensure a comprehensive view.
Key Transparency Mandates:
- Comparative Rate Analyses: States must now use 68 specific Evaluation and Management (E/M) billing codes to compare their FFS rates for primary care, obstetrics/gynecology, and mental health services against Medicare benchmarks. These reports must be published biennially.
- Public Fee Schedules: States are now required to maintain a publicly accessible, updated website containing all FFS rates for inpatient, outpatient, and nursing facility services. Updates must be posted within one month of any rate change.
- Home Care Disclosures: To address the growing need for long-term services, states must disclose average hourly rates for personal care, home health aides, and habilitation services.
- Managed Care Reporting: States must now submit annual analyses comparing MCO payment rates to Medicare rates and compare home care rates against state-run FFS benchmarks.
Supporting Data: Understanding the Scope and Limitations
While the new requirements are a step forward, they are not a panacea. Data from the 2023 T-MSIS (Transformed Medicaid Statistical Information System) reveals both the utility and the limitations of these new disclosures.

The "Narrow Window" Problem
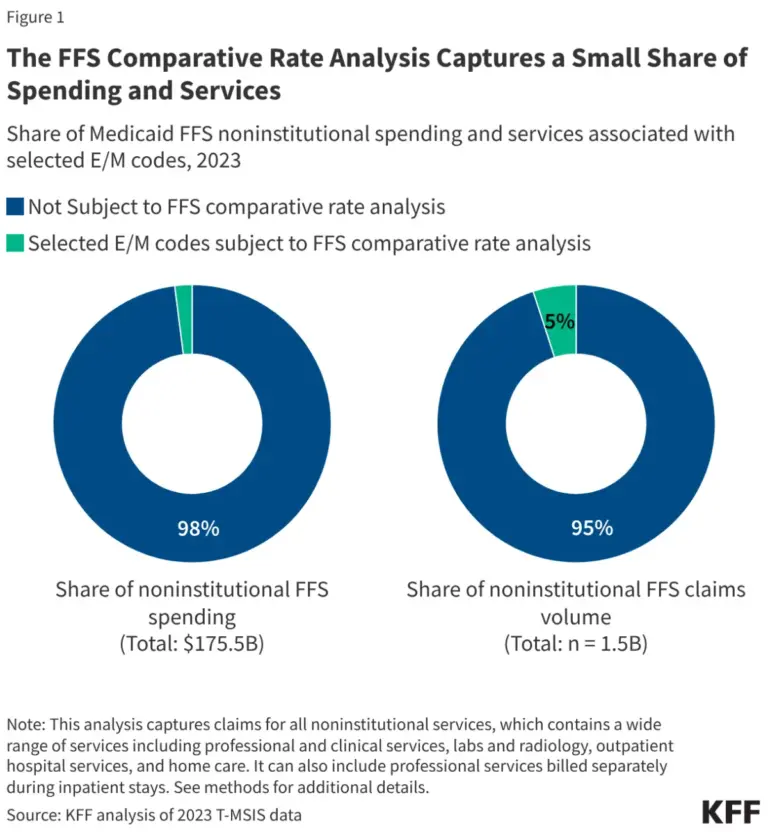
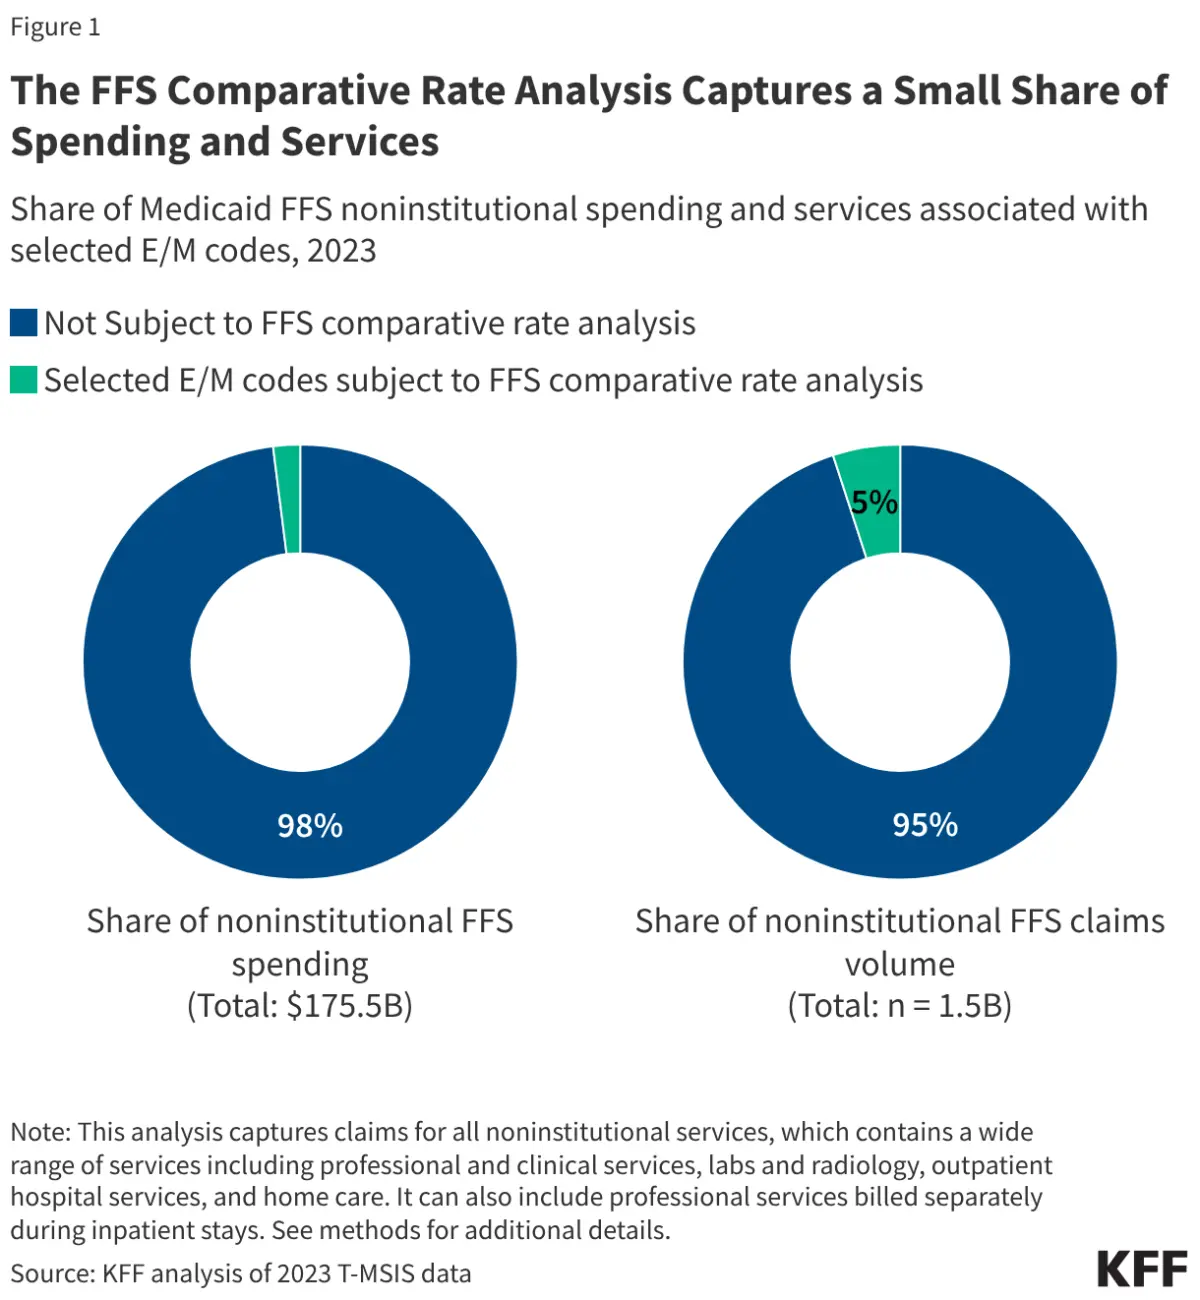
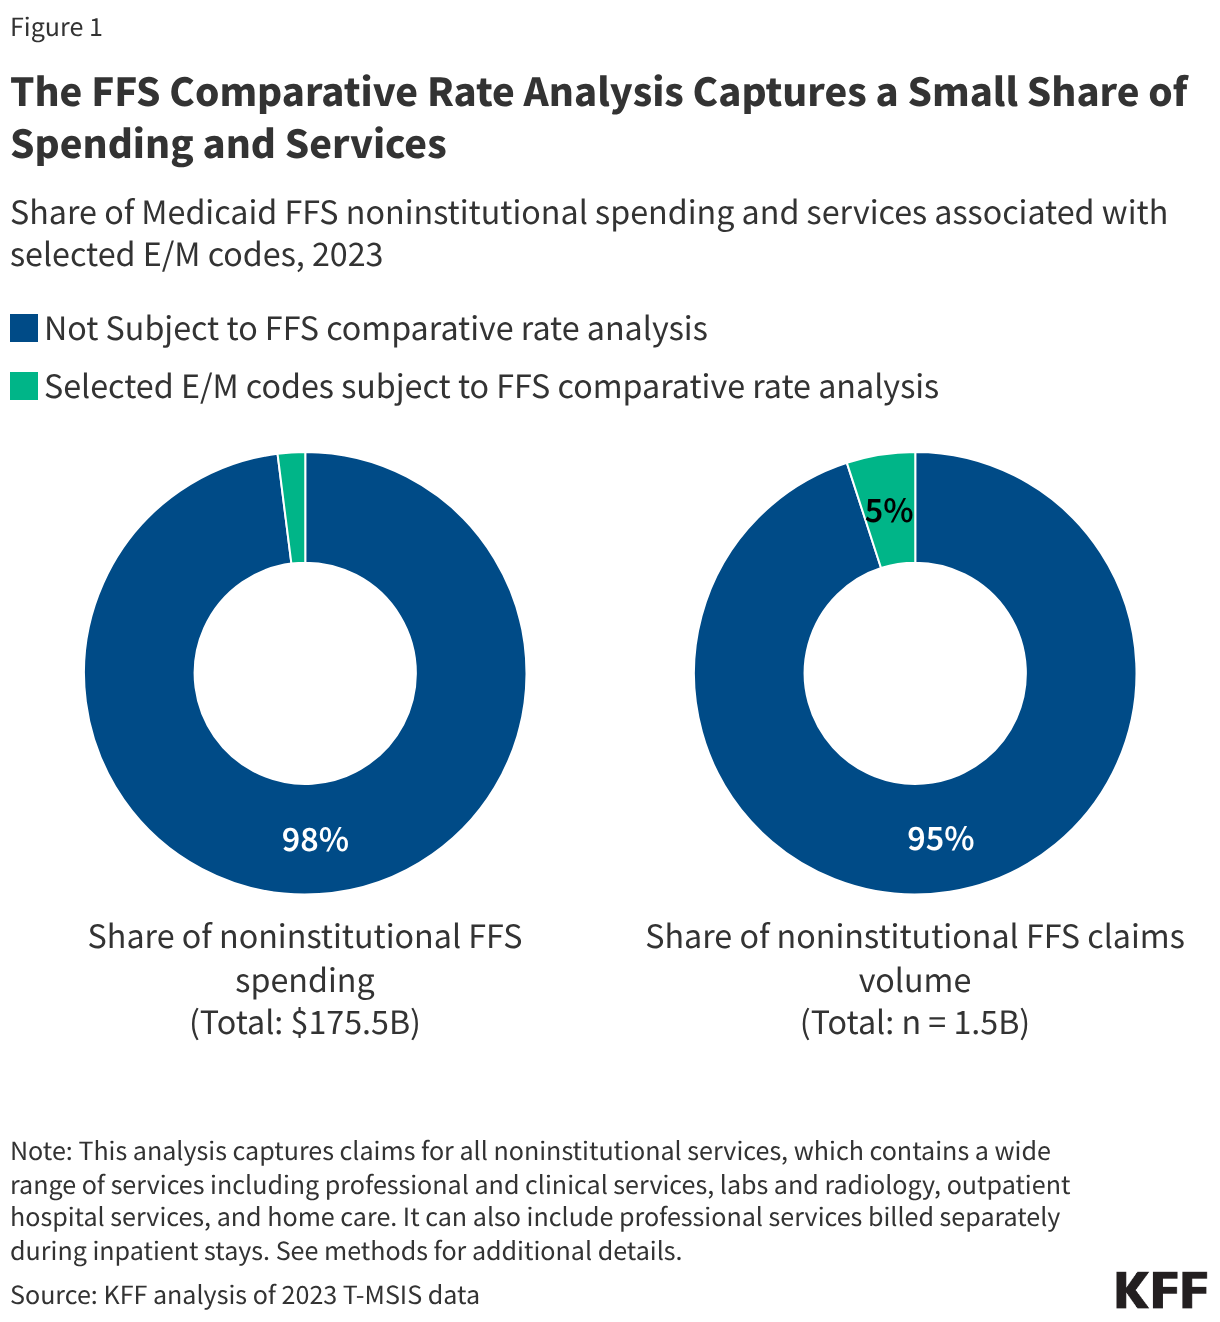
The mandatory comparative rate analysis, which focuses on 68 E/M codes, covers only a fraction of the healthcare spectrum. Analysis indicates that these E/M codes account for just 2% of noninstitutional FFS spending and 5% of noninstitutional claims.
The remaining 95% of claims—which include high-cost services, specialized procedures, and complex diagnostic tests—remain outside the scope of the standardized, Medicare-indexed comparisons. This leaves a significant portion of Medicaid spending less transparent to the public eye.
Who is Impacted?
The demographics of those utilizing these services provide context for the policy. Children, who account for 22% of the overall FFS population, represent 31% of enrollees using the selected E/M services. Furthermore, the rules disproportionately impact patients with chronic conditions. Approximately 66% of individuals utilizing these services have at least one chronic condition, compared to only 35% of the general FFS population. By targeting these services, CMS is focusing on the areas of Medicaid most vital to pediatric health and chronic disease management.
Official Responses and Administrative Challenges
The implementation of these rules has highlighted the technical divide between states. CMS has provided guidance to ensure consistency, but the lack of a standardized format for posting fee schedules remains a significant hurdle.
"We are seeing a massive disparity in how states present their data," noted one healthcare policy expert. "Some states provide sophisticated, searchable databases that allow for real-time comparison. Others simply upload a static PDF or Excel file, forcing researchers to manually parse thousands of lines of data."
States like Rhode Island and Virginia have been lauded for their user-friendly, searchable provider portals. In contrast, states that rely on disparate web pages or non-standardized formats make it difficult for providers and researchers to assess the true value of reimbursement. This fragmentation complicates the primary goal of the rules: to make it easier for stakeholders to evaluate whether payment rates are sufficient to incentivize provider participation.
Implications: A New Era for Provider Access
The ultimate objective of these transparency mandates is to solve the "access crisis." By shining a light on how states compensate providers, CMS hopes to create a more competitive environment where states are incentivized to adjust rates that are significantly below market standards.
The MCO Factor
Perhaps the most critical implication of the new rules is their effect on Managed Care. In many states, FFS rates serve as the "floor" or the benchmark for MCO negotiations. By forcing transparency in FFS, the rules create a ripple effect that will eventually require MCOs to be more transparent about how they, in turn, pay their network providers.
Limitations and Future Outlook
Despite the progress, several challenges remain:
- The Medicare Benchmark: While Medicare is a useful yardstick, it is not always a perfect proxy for Medicaid. For instance, in pediatrics, Medicare coverage is limited, making the Medicaid-to-Medicare comparison less relevant for children’s services.
- Provider Variation: Many non-physician providers, such as licensed clinical social workers or specialized counselors, do not always bill using standard E/M codes, effectively shielding their payment rates from these new reporting requirements.
- Administrative Burden: For states, the cost of compliance is not trivial. Integrating these reporting requirements into existing bureaucratic infrastructure requires significant financial and technical investment.
Conclusion
The 2026 transparency rollout is a watershed moment for the Medicaid program. By moving from a culture of hidden data to one of public disclosure, the federal government is shifting the power dynamic in favor of informed policy-making. While the current scope—covering only a small percentage of total claims—is limited, the framework provides a foundation for future expansion.
As states continue to publish their fee schedules and the first round of comparative analyses becomes public, the focus will shift toward the "so what" factor. Will transparency lead to higher provider participation? Will it force states to raise rates that have languished for years? The answers to these questions will define the next decade of American healthcare equity. For now, the move toward transparency is a vital, albeit incremental, step toward ensuring that Medicaid enrollees receive the same level of care and provider access as any other segment of the American population.
About the Author