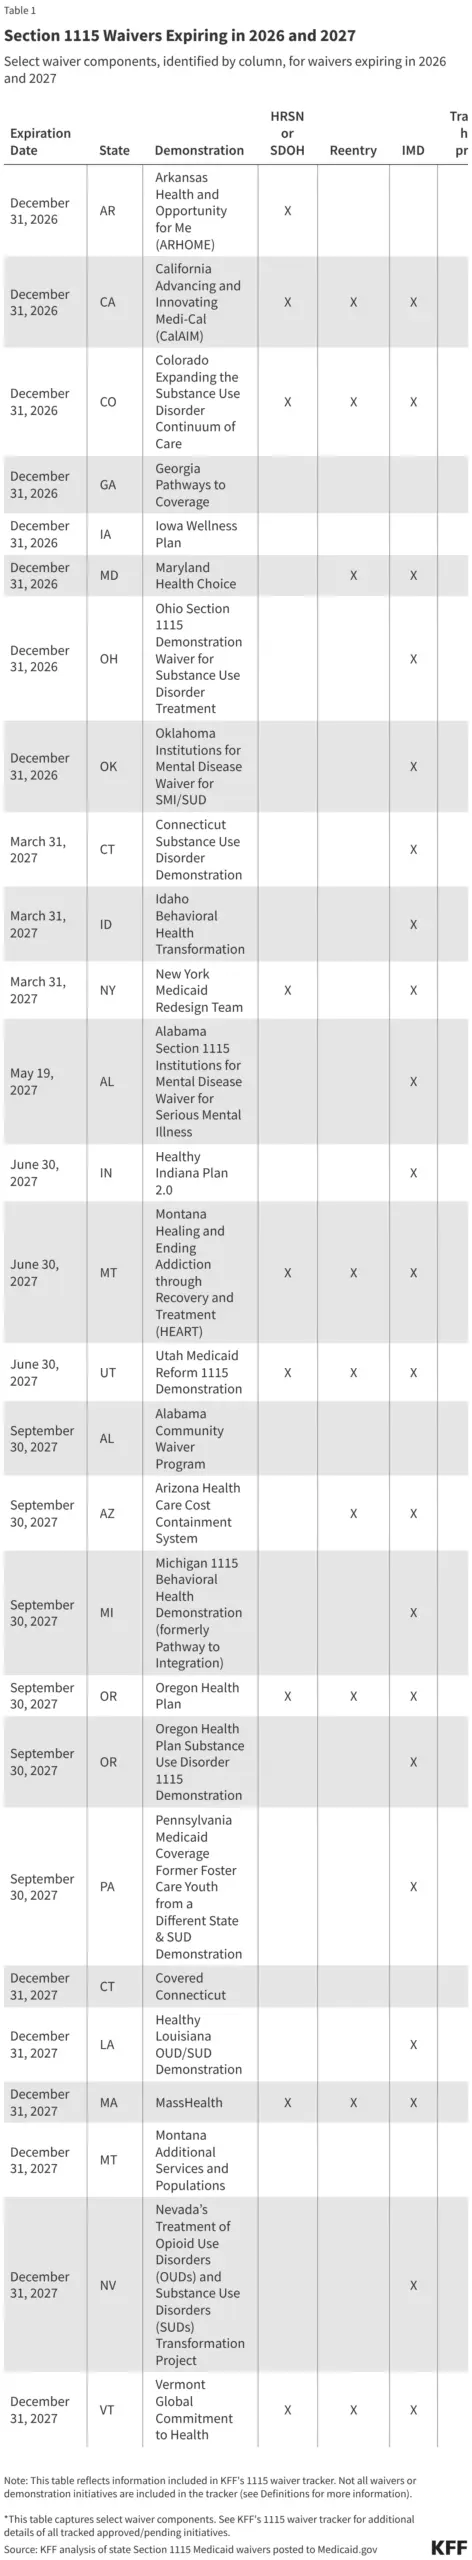
The landscape of American public health policy is undergoing a seismic shift. Section 1115 Medicaid demonstration waivers, long considered the "laboratories of democracy" for state-level healthcare innovation, are facing their most significant regulatory restructuring in decades. Following the enactment of the 2025 reconciliation law and the subsequent guidance issued by the Centers for Medicare and Medicaid Services (CMS) in June 2026, the era of permissive waiver approvals is drawing to a close. As of January 1, 2027, states will operate under a stringent new regime that codifies budget neutrality into federal statute and demands unprecedented actuarial rigor.
For states that have relied on these waivers to expand coverage, address social determinants of health, and innovate delivery systems, the transition represents a precarious balancing act between fiscal conservatism and the need for public health stability.
Main Facts: The Codification of Fiscal Discipline
At its core, a Section 1115 waiver allows states to test new approaches to Medicaid that deviate from standard federal requirements, provided the Secretary of Health and Human Services (HHS) deems the project likely to "promote the objectives of the Medicaid program." Historically, these waivers were governed by a flexible, albeit complex, "budget neutrality" requirement. This doctrine held that federal spending under a waiver should not exceed the costs that would have been incurred had the waiver never been granted.
The 2025 reconciliation law, signed into effect by President Trump on July 4, 2025, elevated this practice from administrative policy to federal statute. The law introduced a mandatory requirement: the CMS Chief Actuary must now formally certify the budget neutrality of any proposed waiver before it can receive federal approval.
This legislative change has fundamentally altered the power dynamics between the federal government and the states. By requiring a more rigorous, actuarially sound justification for every dollar of projected "savings," the new policy significantly narrows the scope for creative financing. Initiatives that were previously approved under "hypothetical" savings models—such as certain Health-Related Social Needs (HRSN) services or expansive workforce initiatives—now face a much higher threshold for approval.
Chronology: A Timeline of Policy Evolution
The transition toward this stricter oversight has been marked by several critical milestones:
- 2018: The first Trump administration introduced initial reforms to budget neutrality, tightening the baseline calculations for "without-waiver" costs.
- 2021–2024: The Biden administration promoted greater flexibility, encouraging states to utilize waivers to address HRSN and continuous eligibility.
- July 4, 2025: President Trump signs the reconciliation law, codifying budget neutrality and mandating Chief Actuary certification.
- 2025: The Government Accountability Office (GAO) publishes a report criticizing the lack of transparency in previous waiver approvals, specifically targeting "hypothetical" expenditures.
- June 2026: CMS releases formal guidance outlining the new approach to budget neutrality, setting a January 1, 2027, effective date.
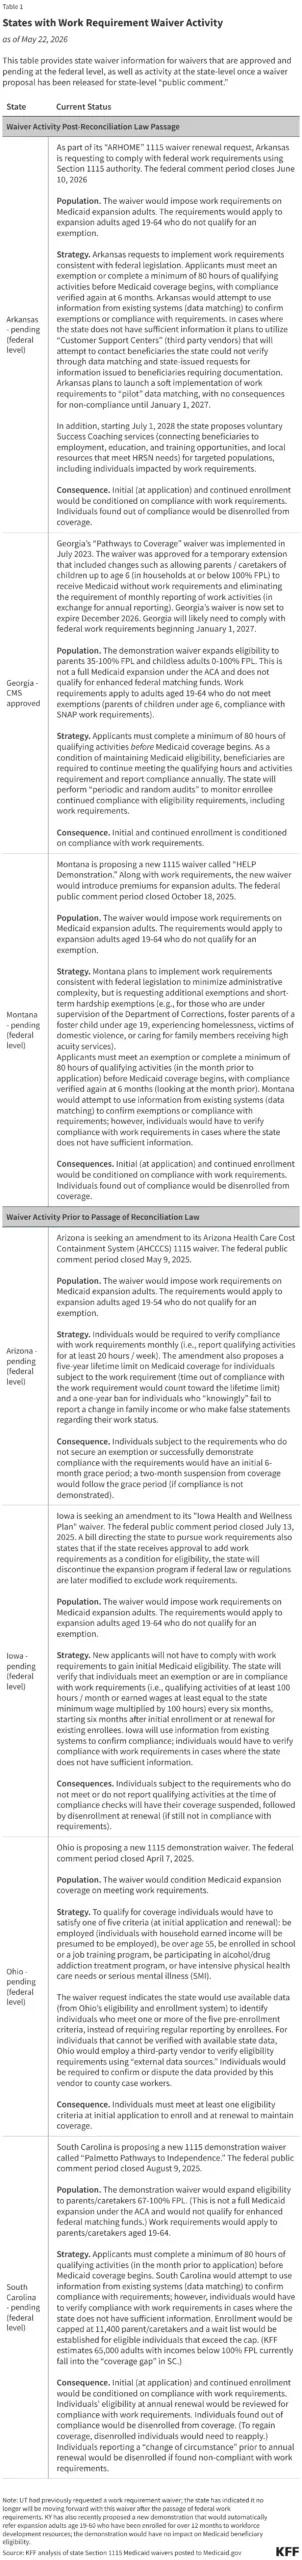
- August 2026: Arkansas announces that its "ARHOME" waiver renewal—a flagship program for Marketplace-based Medicaid expansion—has been denied by CMS under the new criteria.
- September 2026: CMS approves five reentry waivers (D.C., Louisiana, Maine, Minnesota, and Nevada) while simultaneously signaling that infrastructure funding for these programs will no longer be considered "hypothetical."
- January 1, 2027: The new budget neutrality rules officially take effect, regardless of the status of formal rulemaking.
Supporting Data: The Impact of "Budget Neutrality" Calculations
The historical process for assessing budget neutrality involved a complex negotiation between the state, CMS, and the Office of Management and Budget (OMB). States were tasked with establishing a "without-waiver" baseline—a projection of what the state would have spent without the requested flexibilities—and a "with-waiver" projection. The difference between these two figures represented the "savings" that could be reinvested into the demonstration project.
The GAO has consistently raised concerns that these calculations were often inflated, creating "paper savings" that did not necessarily translate to true federal cost-savings. In a 2025 report, the GAO highlighted the lack of longitudinal monitoring of these projects, suggesting that the federal government lacked the tools to verify if these waivers were actually achieving their intended health outcomes while maintaining fiscal discipline.
The new CMS guidance attempts to resolve this by requiring:
- Rigorous Financial Analysis: States must now provide comprehensive economic and statistical modeling at the application stage, rather than following approval.
- Elimination of "Fast-Track" Renewals: The streamlined approval process for straightforward waiver renewals has been rescinded, forcing all states into a more intensive review cycle.
- Inclusion of Administrative Costs: Future calculations must include administrative expenses, which were previously often excluded from the budget neutrality bottom line.
Official Responses and State-Level Implications
The immediate fallout of these changes is best exemplified by the situation in Arkansas. The state’s "ARHOME" program, which enrolled Medicaid expansion adults into private ACA Marketplace plans, was a cornerstone of its healthcare delivery system. Because the program relied on waiver authority that is no longer compatible with the strict budget neutrality requirements, CMS has signaled that it will not approve a renewal.
Arkansas is currently scrambling to negotiate a two-year extension to transition its population to a different delivery model. This scenario serves as a warning to other states currently utilizing 1115 waivers to fund coverage expansions or delivery system reforms: the "flexibility" of the past is being replaced by the "certainty" of current fiscal mandates.
Conversely, the approval of reentry waivers for five states in late 2026 suggests that while the fiscal rules are tightening, the administration is still willing to engage with states on specific, high-priority initiatives—provided they can fit within the new financial guardrails. However, the caveat regarding infrastructure funding is telling: CMS will no longer allow states to categorize infrastructure investments as "hypothetical" expenditures that exist outside the standard budget neutrality calculation. This forces states to find existing, non-waiver funding streams to support the underlying technology and administrative systems required to manage reentry programs.
Implications: The Road Ahead for Medicaid Innovation
The path forward for Medicaid innovation is likely to be characterized by several key trends:
1. Increased Burden of Proof for States
States will face significantly longer lead times for waiver approvals. The necessity of conducting "rigorous analysis" before submission means that states must invest more in actuarial services and data collection. This creates a barrier to entry for smaller, less-resourced states that may lack the internal capacity to meet these high standards.
2. A Pivot Toward Alternative Authorities
CMS has explicitly directed states to look toward alternative authorities, such as the state plan amendment (SPA) process or 1915(c) waivers, for initiatives that do not strictly require the broad flexibilities of an 1115 waiver. While these pathways offer less "innovation" potential, they provide a more stable, statutory foundation that is less susceptible to the shifting winds of administrative budget neutrality policies.
3. The "1115-Only" Challenge
Activities categorized as "1115-only"—such as certain traditional healing practices or innovative delivery models—are now at high risk. Because these initiatives do not have a standard Medicaid equivalent, they must be paid for through generated savings. If a state cannot prove that the waiver will create enough federal savings to offset the cost of these initiatives, they will likely be denied. This effectively puts a "price tag" on innovation that many states will struggle to afford.
4. Continued Monitoring and Rulemaking
Although the new policies are effective as of January 2027, the forthcoming federal rulemaking process remains a critical point of interest. States, advocates, and providers will be watching closely to see how CMS defines "rigorous analysis" and whether there will be any "grandfathering" for existing waivers that are already midway through their five-year cycles.
Conclusion
The 2027 budget neutrality framework is more than just an accounting change; it is a fundamental reassertion of federal control over the Medicaid program. By demanding that states treat every waiver dollar as a precious, finite resource, the government is signaling that the era of unfettered state experimentation is over.
While the new rules may succeed in curbing federal spending and increasing fiscal accountability, they also threaten to stifle the very innovation that Section 1115 waivers were designed to foster. As states navigate this new regulatory terrain, they will need to prioritize data-driven proposals that clearly demonstrate both fiscal sustainability and improved health outcomes. The challenge for the coming years will be to determine whether these strictures will lead to a more efficient Medicaid system, or if they will simply lead to a less responsive one, leaving vulnerable populations to navigate an increasingly rigid safety net.
About the Author