Editorial Note: This comprehensive analysis, originally published on October 9, 2026, has been updated to incorporate the latest CMS landscape data. It provides an in-depth examination of firm-level market entries and exits, the density of plan choices available to the average beneficiary, and the shifting geographic footprint of private Medicare insurers across the United States.
The Medicare Advantage (MA) market, which serves as the primary private-sector alternative to traditional Medicare, is undergoing a period of structural recalibration. For the 2027 plan year, the average Medicare beneficiary has access to 28 Medicare Advantage prescription drug (MA-PD) plans. While this suggests a robust marketplace, a deeper analysis of county-level data reveals a nuanced narrative of retrenchment, consolidation, and strategic pruning by major industry players.
The 2027 landscape is characterized by a significant reduction in the number of firms operating in the space and a contraction in the geographic availability of plans. This analysis, utilizing data from the Centers for Medicare & Medicaid Services (CMS), examines these trends while highlighting the implications for the millions of seniors and individuals with disabilities who rely on these plans for their healthcare coverage.
Main Facts: A Market in Transition
The headline figures for 2027 point toward a cooling of the rapid expansion that characterized the Medicare Advantage sector for the better part of the last decade. While the vast majority of beneficiaries still enjoy a significant array of choices, the "hyper-choice" era is beginning to wane.

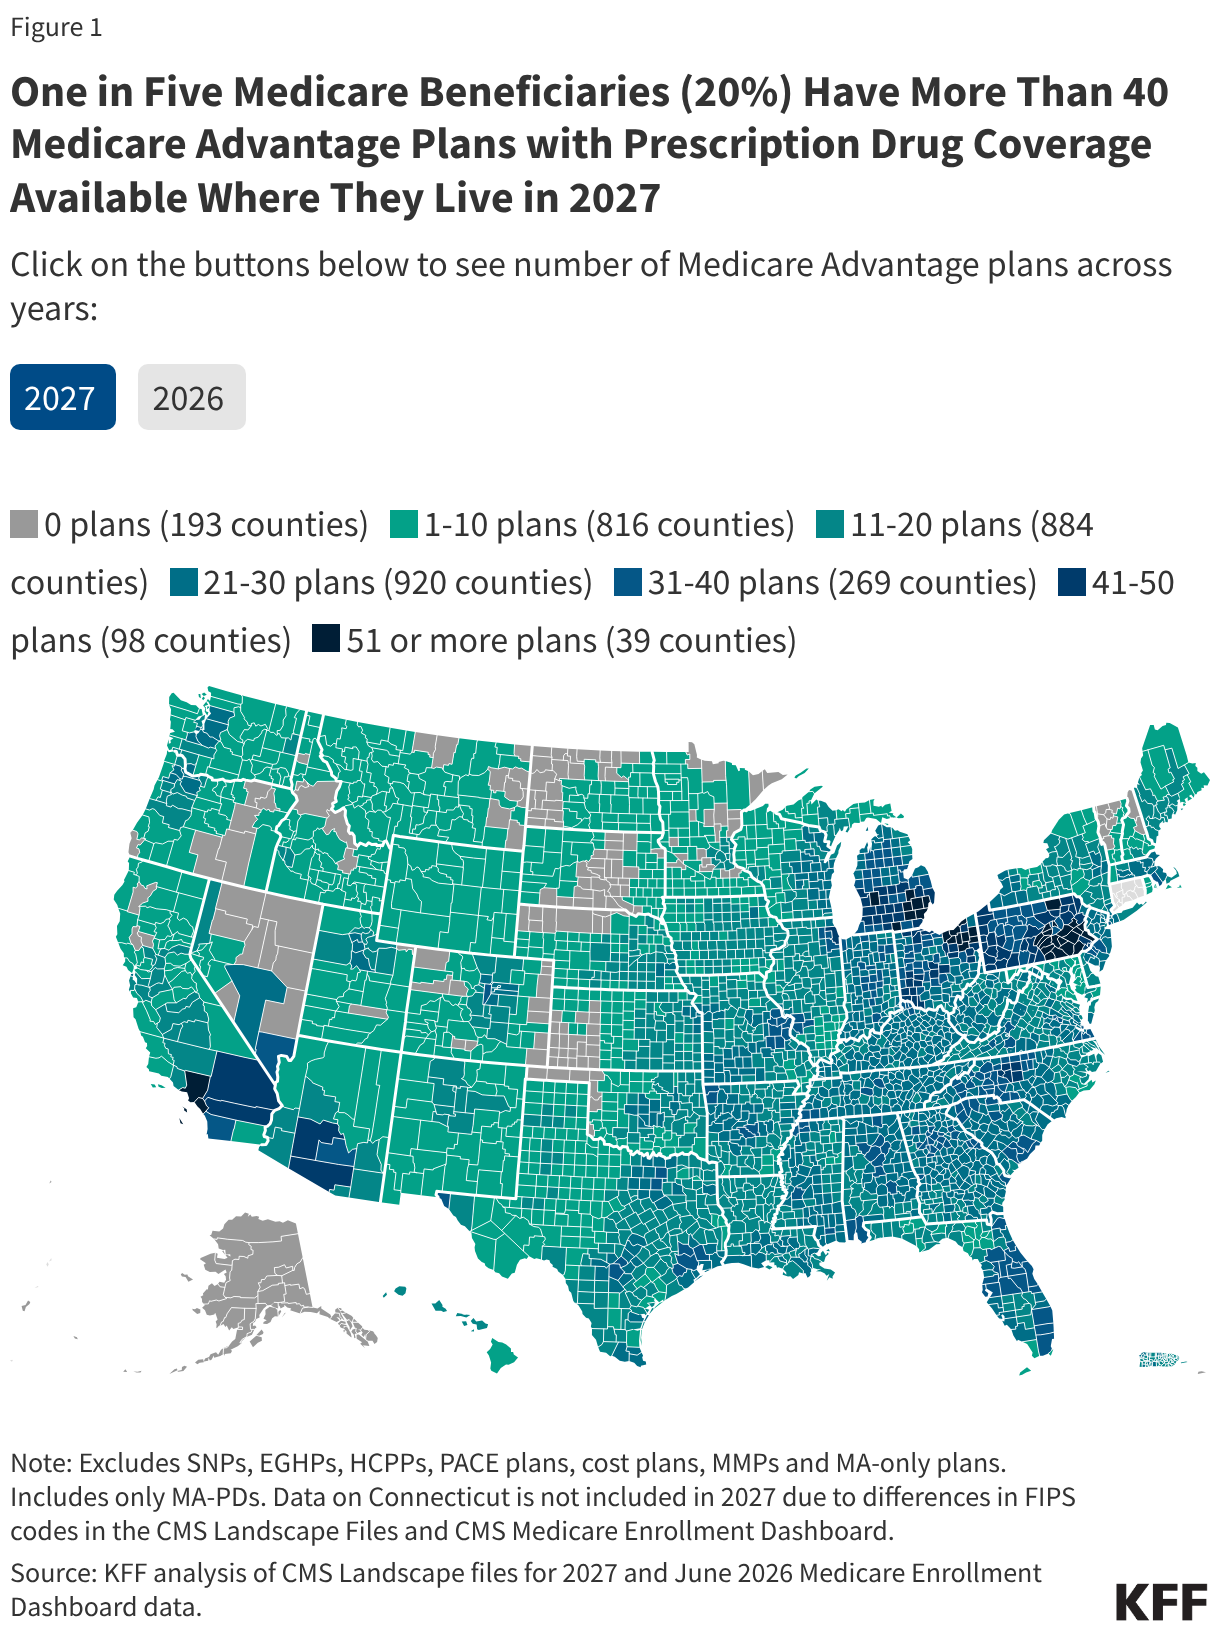
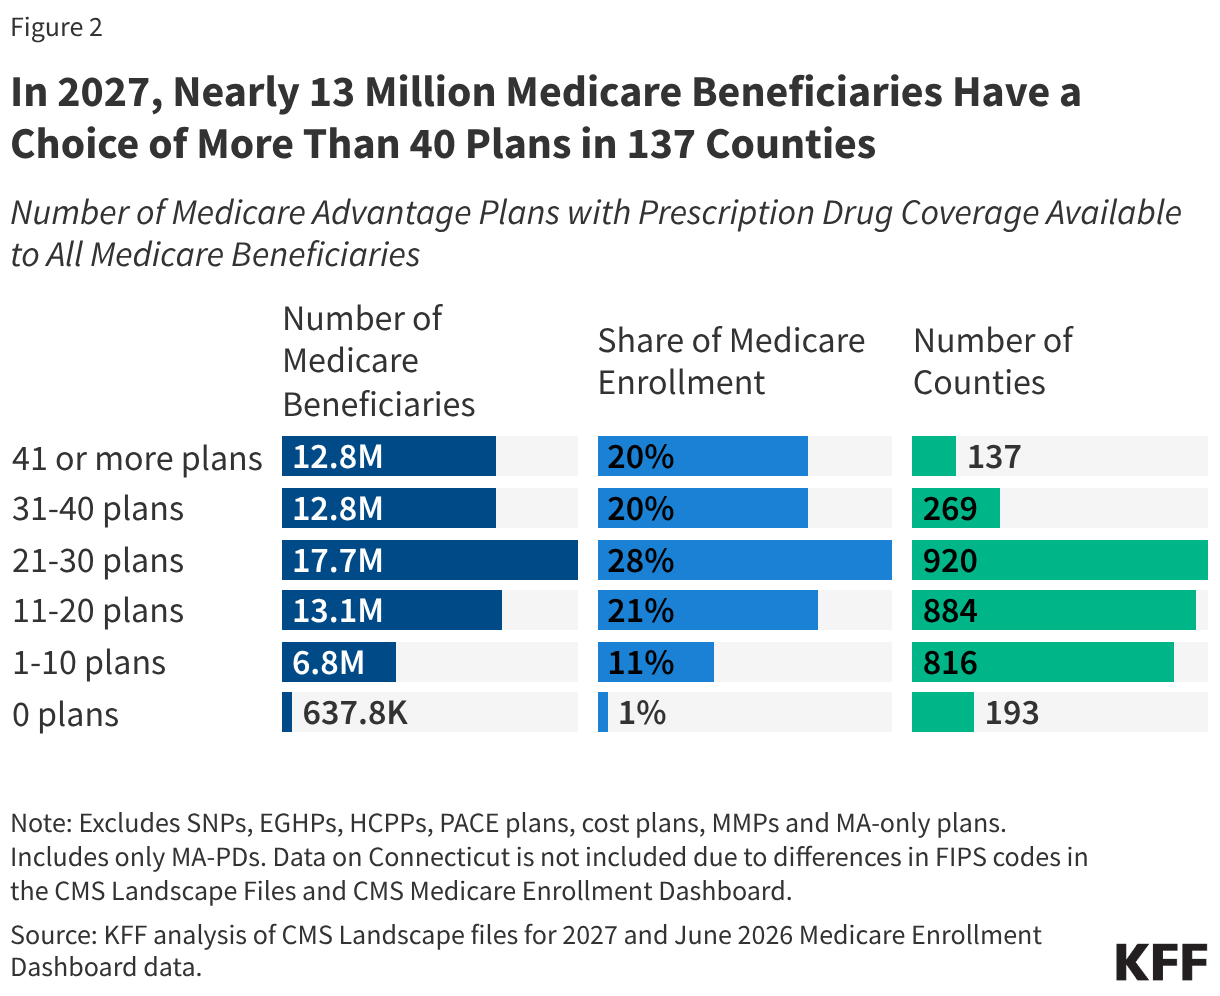
- Choice Concentration: Roughly one in five Medicare beneficiaries (20%) now has access to more than 40 MA-PD options. This represents a notable decline from 2026, when 27% of beneficiaries resided in areas with such a high volume of plans.
- The "Desert" Effect: The number of counties with absolutely no MA-PD options for general enrollment has risen to 193 in 2027, up from 123 in 2026. This trend, while affecting a small percentage of the total beneficiary population (approximately 1%), underscores a growing fragility in rural healthcare access.
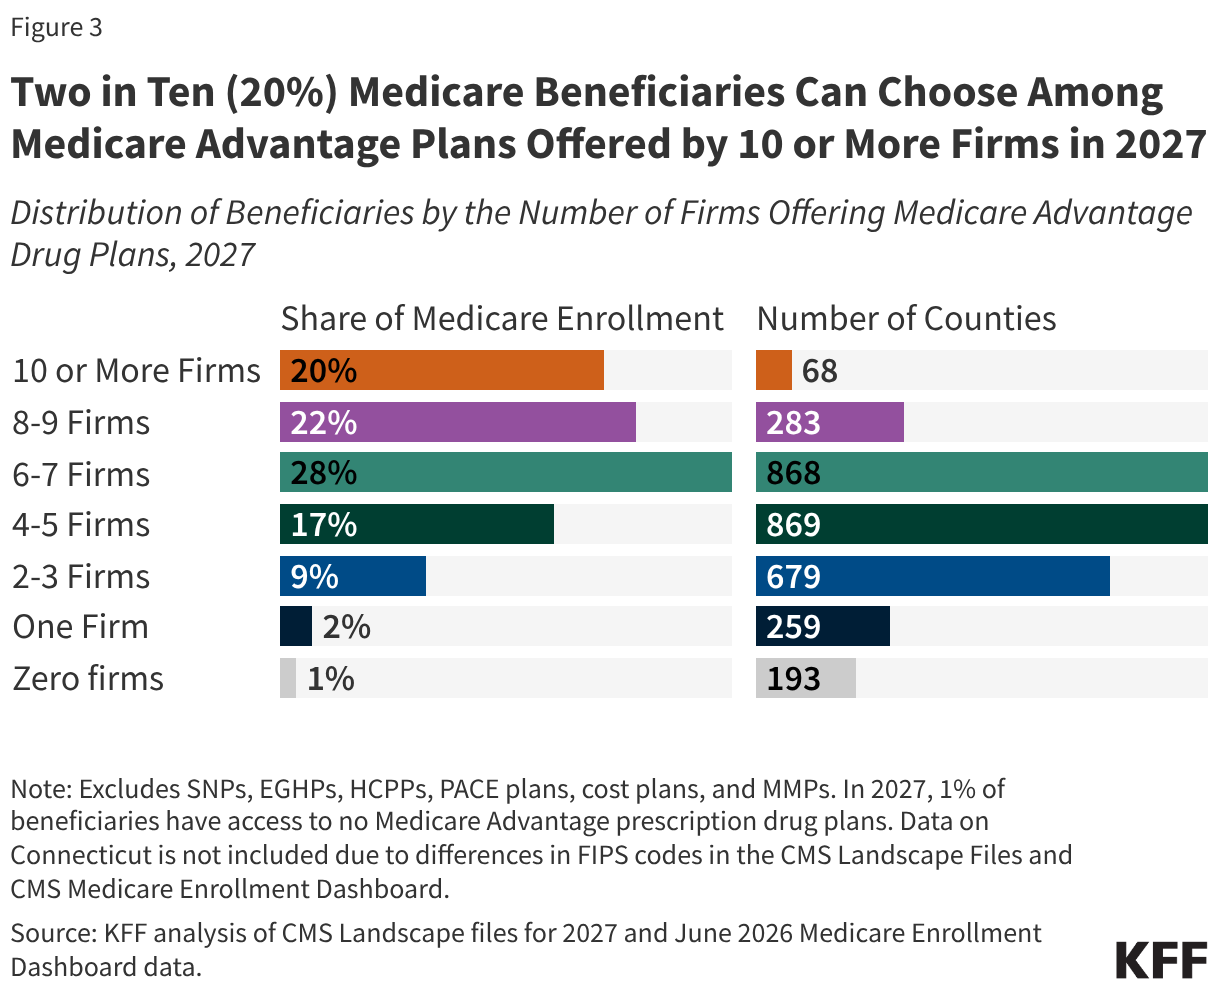
- Firm Contraction: The average beneficiary can now choose from plans offered by seven firms, a decrease of one firm compared to the 2026 plan year.
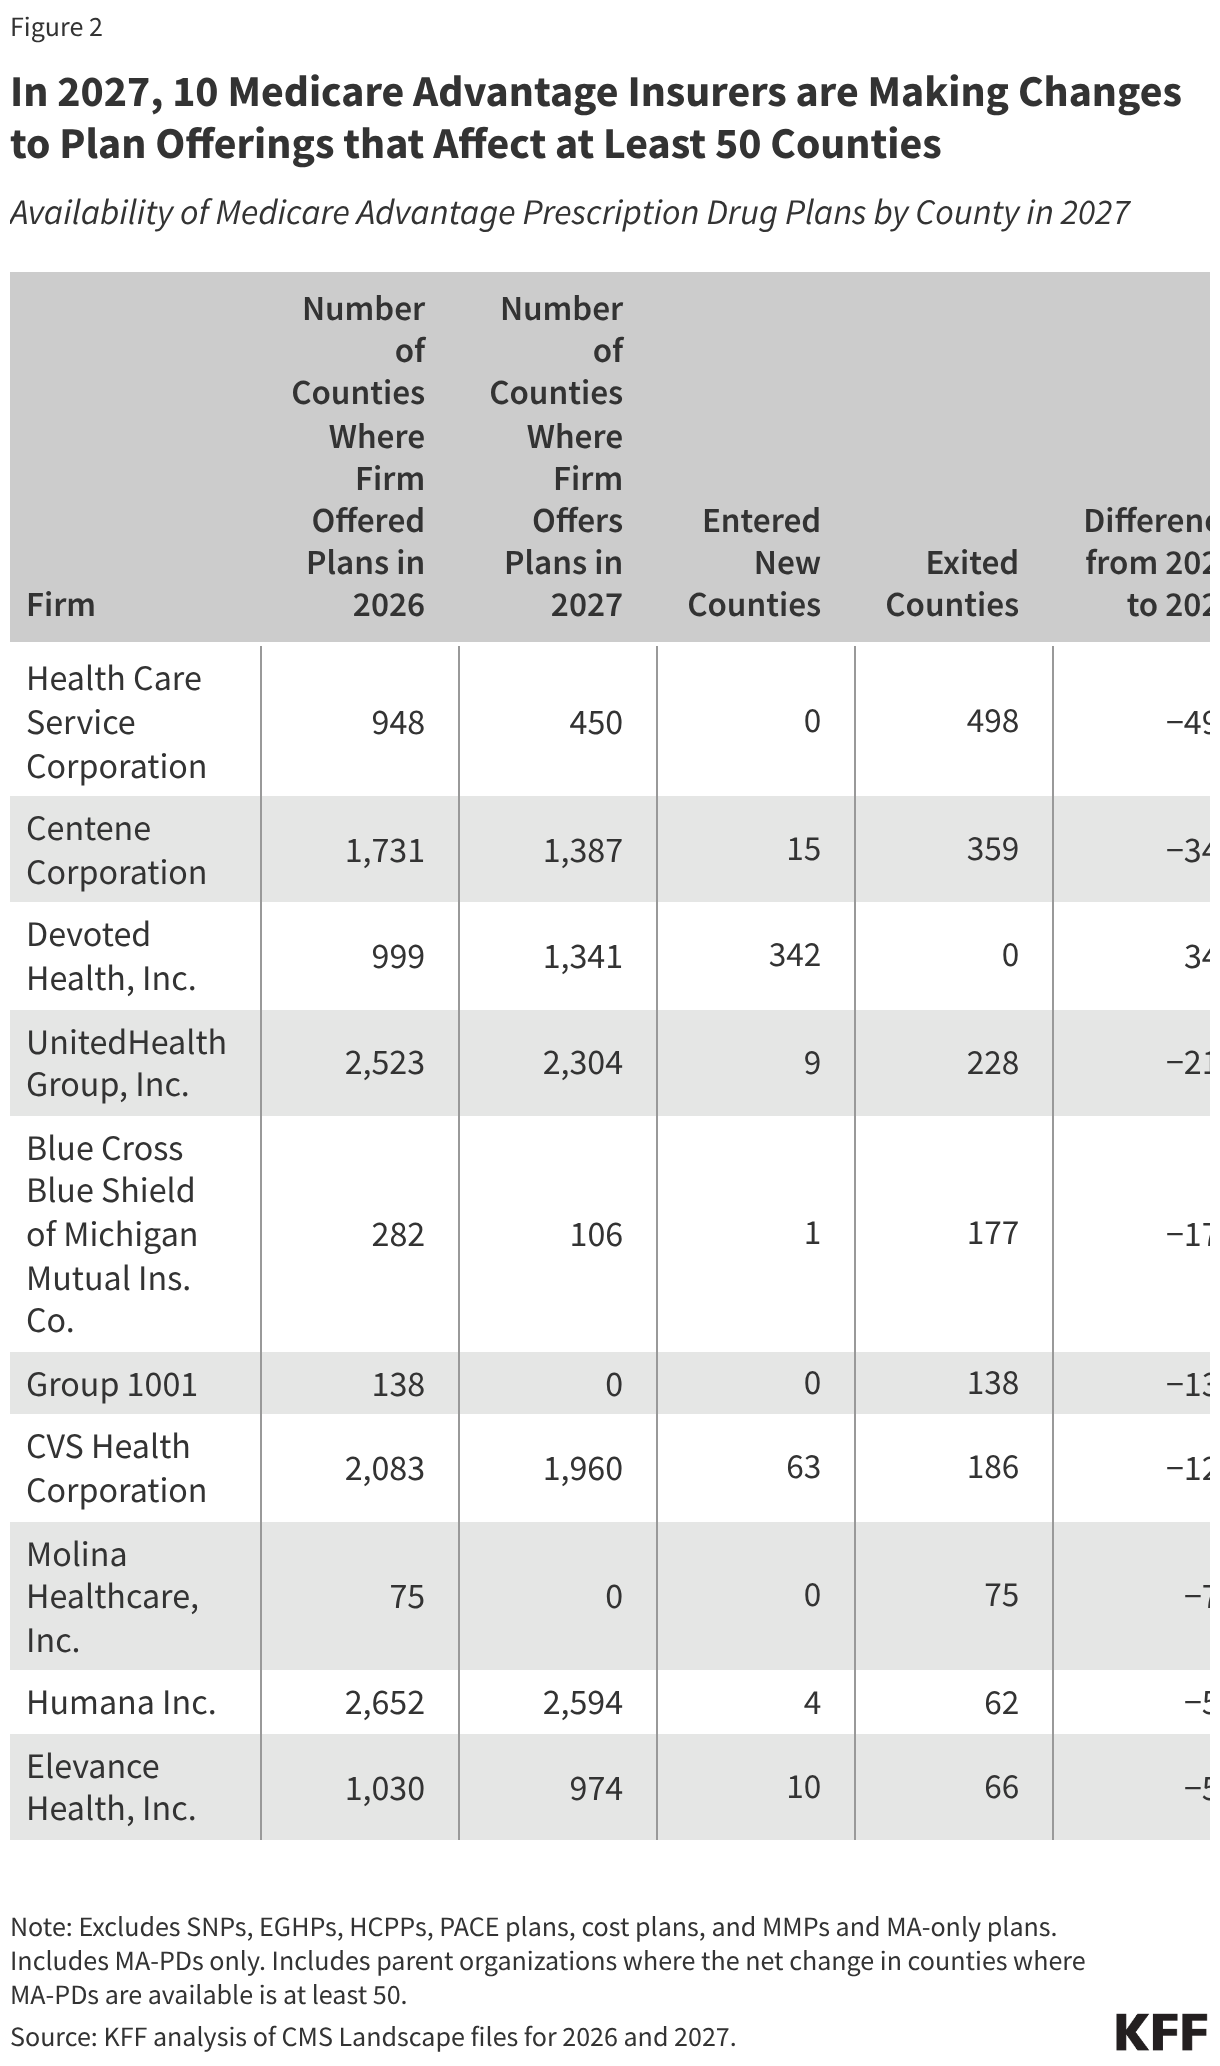
- Strategic Exits: Market leaders—specifically UnitedHealth Group and Humana—are actively exiting more counties than they are entering, signaling a shift toward profitability and risk management over sheer geographic dominance.
Chronology: The Evolution of the 2027 Plan Year
The transition into the 2027 plan year did not occur in a vacuum; it is the result of compounding pressures that have built up since the 2025 and 2026 cycles.
Early 2026: Throughout the first half of the year, industry analysts noted increasing regulatory scrutiny and mounting cost pressures regarding supplemental benefits. Profit margins in the MA sector began to tighten, prompting insurers to signal to investors that they would prioritize "margin over membership" for the upcoming cycle.
Mid-2026 (The Planning Phase): As insurers submitted their 2027 bids to CMS, the trend of consolidation became apparent. Firms began identifying underperforming markets—often rural, low-density counties—for closure. Concurrently, mergers and affiliations continued, with several regional health systems either exiting the market or being absorbed by larger national parent organizations.
October 2026 (The Official Release): With the release of the CMS Landscape files, the full extent of the contraction was revealed. The data confirmed that while some innovators like Devoted Health were aggressively expanding, the collective weight of the industry was leaning heavily toward exit.
November 2026 – January 2027 (Implementation): As beneficiaries navigate the open enrollment period and the start of the new plan year, the impact of these changes becomes a reality. The transition has forced hundreds of thousands of enrollees to evaluate their coverage, as their previous plans have either been discontinued or significantly altered in terms of geographic availability.
Supporting Data: By the Numbers
The quantitative evidence paints a picture of a market that is consolidating its footprint.
Geographic Distribution of Choice
The 13 million people who have access to more than 40 MA-PD plans represent a shrinking cohort. Conversely, the population with 1 to 10 plan options has surged, jumping to nearly 7 million people in 2027 from 4.8 million in 2026. This polarization suggests that while urban centers remain highly competitive, the "middle ground" of competition is thinning.
The Firm-Level Exodus
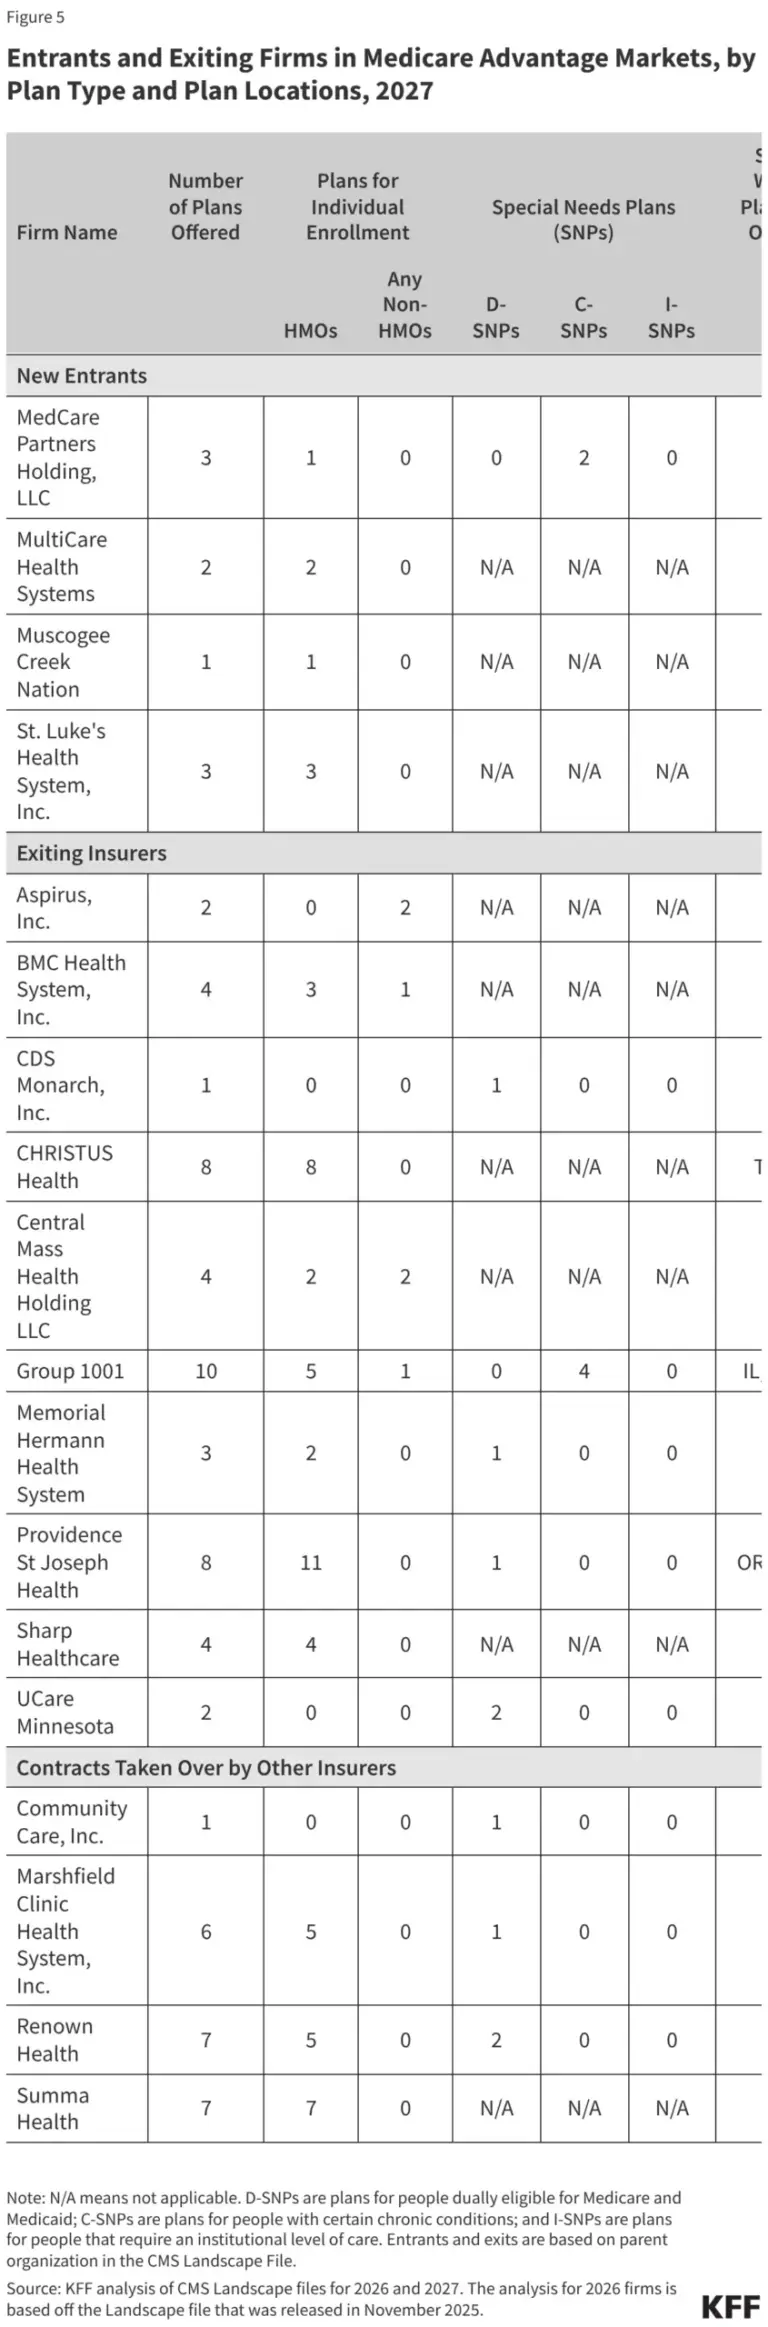
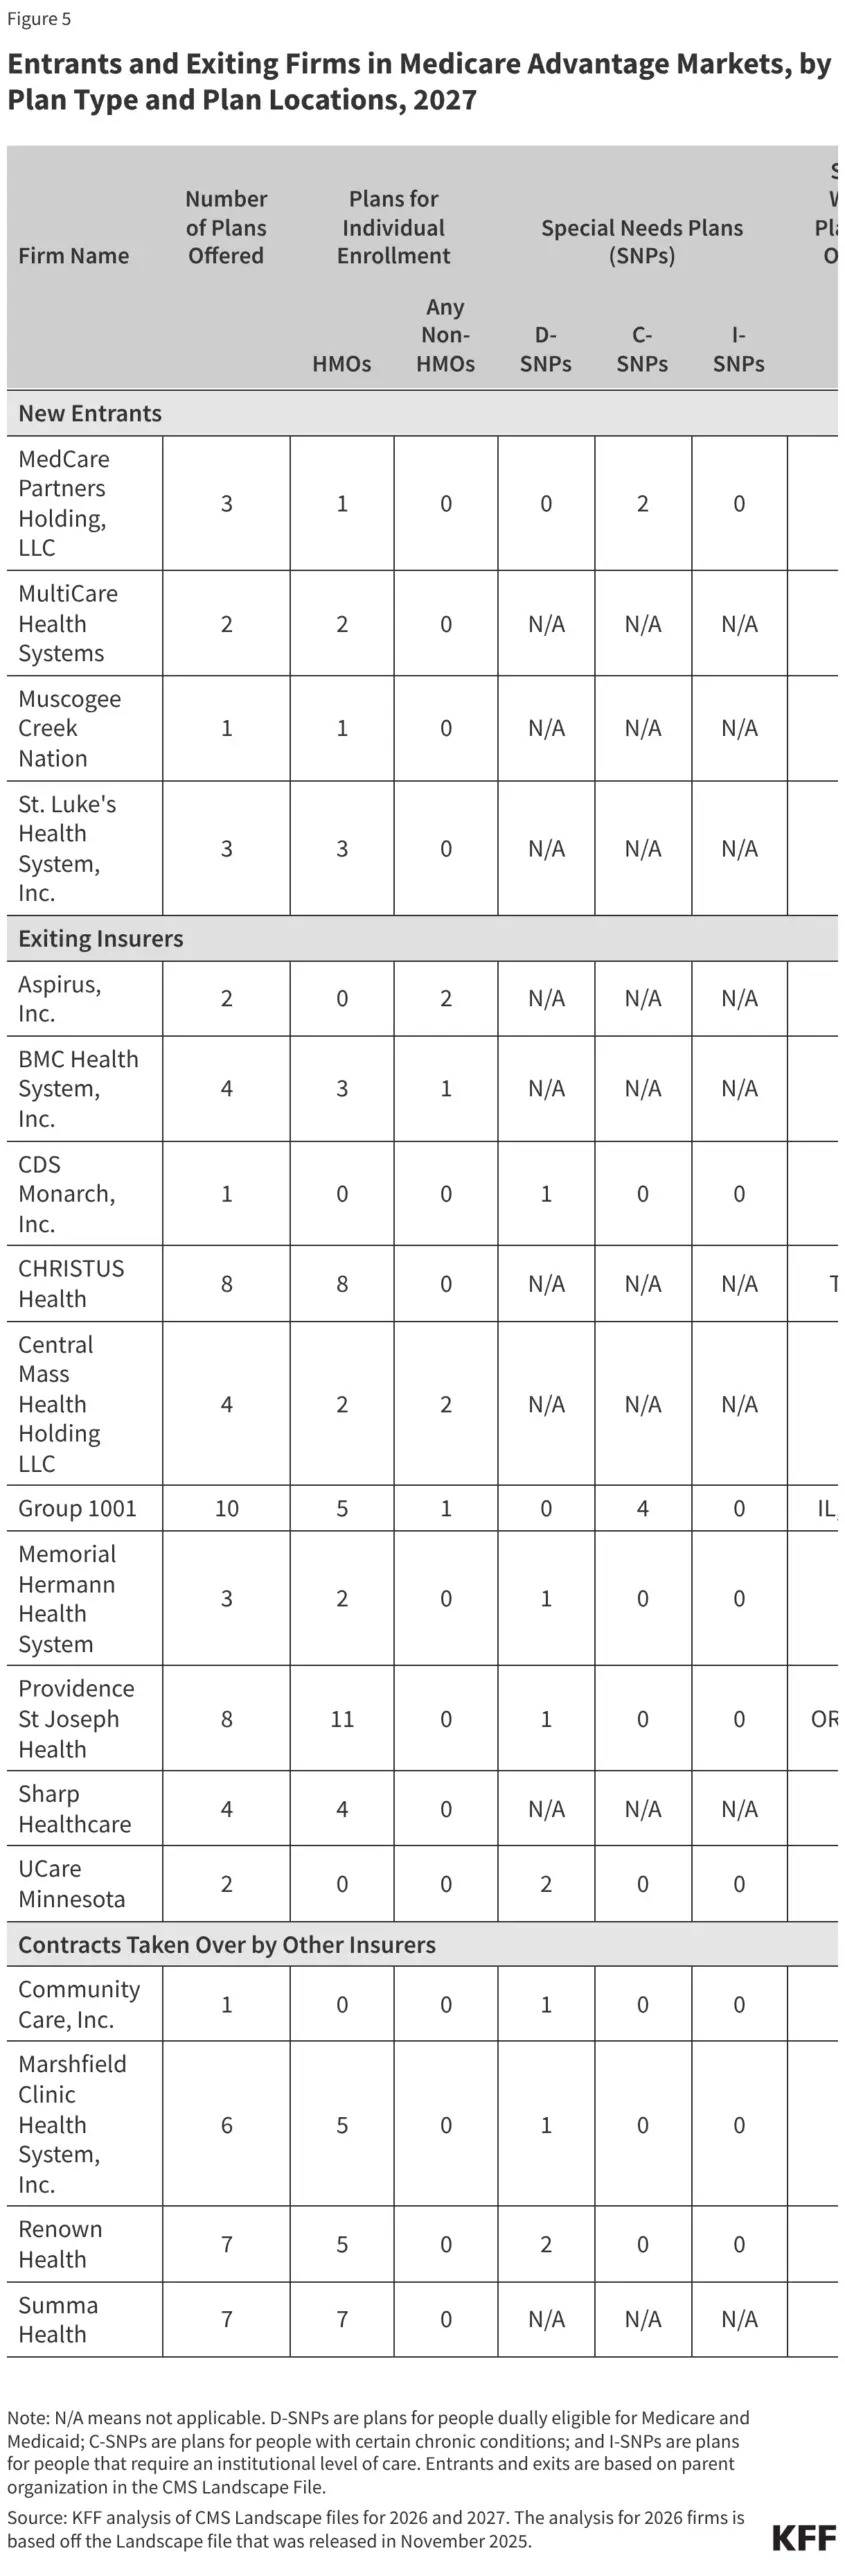
The data on firm participation is perhaps the most telling indicator of market health. In 2027, ten firms that were active in 2026 have exited the market entirely. Another four firms have effectively vanished from the landscape through mergers or acquisitions.
The exit of Health Care Service Corporation (HCSC), which is withdrawing from 498 counties, stands as the most aggressive reduction in footprint for the 2027 cycle. Centene follows with 359 exits. While these firms retreat, Devoted Health’s entry into 342 counties serves as an outlier in an otherwise contractionary environment.
The Rural Divide
The increase in counties with zero MA-PD options—from 123 to 193—is heavily concentrated in states like Alaska, North Dakota, Oklahoma, and New Hampshire. In these regions, the absence of MA-PDs forces beneficiaries to rely on traditional Medicare, potentially leaving them without the integrated drug and supplemental coverage that characterizes the MA model.
Official Responses and Industry Sentiment
The decision-making process behind these exits is multifaceted. In discussions with stakeholders and through public filings, several themes have emerged:
- Regulatory Uncertainty: Several firms, including those that exited the market, have cited the "changing Medicare landscape." This is often shorthand for shifting CMS star-rating methodologies and payment rate adjustments that make it harder to sustain high-benefit, low-premium plans.
- Cost Pressures: The rising cost of medical services, combined with higher utilization rates, has made it difficult for smaller or regional plans to maintain solvency without raising premiums—a strategy that often leads to a loss of market share.
- Strategic Realignment: For larger players like Humana and UnitedHealth Group, the exit from specific counties is a move to optimize their risk pool. By retreating from markets where they lack the scale to be efficient, they can concentrate resources in areas where they can maintain a competitive edge and better control medical loss ratios.
- The "SNP" Pivot: Many firms are not exiting Medicare altogether; they are pivoting to Special Needs Plans (SNPs). This allows them to maintain a presence in the market while focusing on high-acuity, more predictable, and often more profitable patient populations.
Implications for the Future of Medicare
The 2027 Medicare Advantage landscape carries significant implications for policy, the healthcare industry, and, most importantly, the beneficiaries.
For the Beneficiary
The primary risk for the average enrollee is "plan churn." As firms exit counties, beneficiaries are forced to shop for new plans. This creates administrative burden and, more critically, the potential for disruption in continuity of care. If a preferred physician is not in the network of the new plan, or if the new formulary does not cover necessary medications, the impact on health outcomes could be substantial.
For the Policy Landscape
The growing number of counties with limited or no MA-PD access poses a political challenge. The Medicare Advantage program was designed to offer the same level of choice nationwide. The emergence of "plan deserts" may force lawmakers to reconsider the adequacy of reimbursement rates in rural areas. If private competition continues to fail in these regions, there will be renewed pressure on CMS to incentivize participation in underserved markets or risk leaving millions without private options.
For Market Competition
The trend toward consolidation favors the largest insurers. As smaller, regional, or niche firms exit, the market becomes increasingly dominated by a handful of national giants. While these large firms offer scale and stability, a reduction in the number of competitors could eventually lead to higher costs for the government and, ultimately, less innovation in plan design and supplemental benefits.
The Innovation Factor
Despite the contraction, the market is not static. Partnerships with companies like Instacart, Costco, and Walmart show that insurers are still looking for ways to differentiate their products. These co-branded plans, which often focus on the "social determinants of health"—such as nutrition and transportation—suggest that the next phase of the Medicare Advantage market will be defined by integration rather than mere geographic presence.
Conclusion
The 2027 Medicare Advantage landscape is a clear reflection of a market finding a new equilibrium. After years of rapid, perhaps unsustainable, growth, the sector is currently in a phase of strategic consolidation. While beneficiaries in major metropolitan areas will continue to see a plethora of options, those in rural and underserved regions are feeling the brunt of the industry’s shift toward fiscal austerity. As the market moves forward, the success of the Medicare Advantage program will depend on its ability to balance the profitability requirements of private insurers with the mandate to provide universal, high-quality, and reliable healthcare access to all Medicare-eligible Americans.
About the Author