The meteoric rise of GLP-1 receptor agonists—the class of blockbuster drugs including semaglutide (Ozempic/Wegovy) and tirzepatide (Mounjaro/Zepbound)—has transformed the landscape of obesity and diabetes treatment. However, as demand far outpaced supply, a sprawling, largely unregulated “shadow market” of compounded alternatives emerged. By August 2026, the situation has escalated into a public health crisis characterized by over 1,700 adverse event reports, complex legal battles, and a web of interconnected telehealth entities operating under intense scrutiny from the U.S. Food and Drug Administration (FDA).
The Proliferation of a “Copycat” Industry
The market for compounded GLP-1s, once justified by legitimate drug shortages, has ballooned into a multi-billion-dollar enterprise. In April 2026, reports surfaced that the generative-AI-driven firm MEDVi was on track to achieve $1.8 billion in annual sales, despite being the subject of an aggressive FDA crackdown.
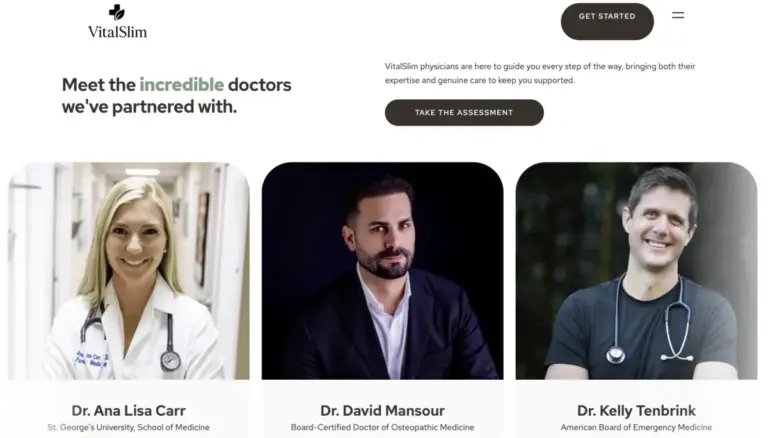
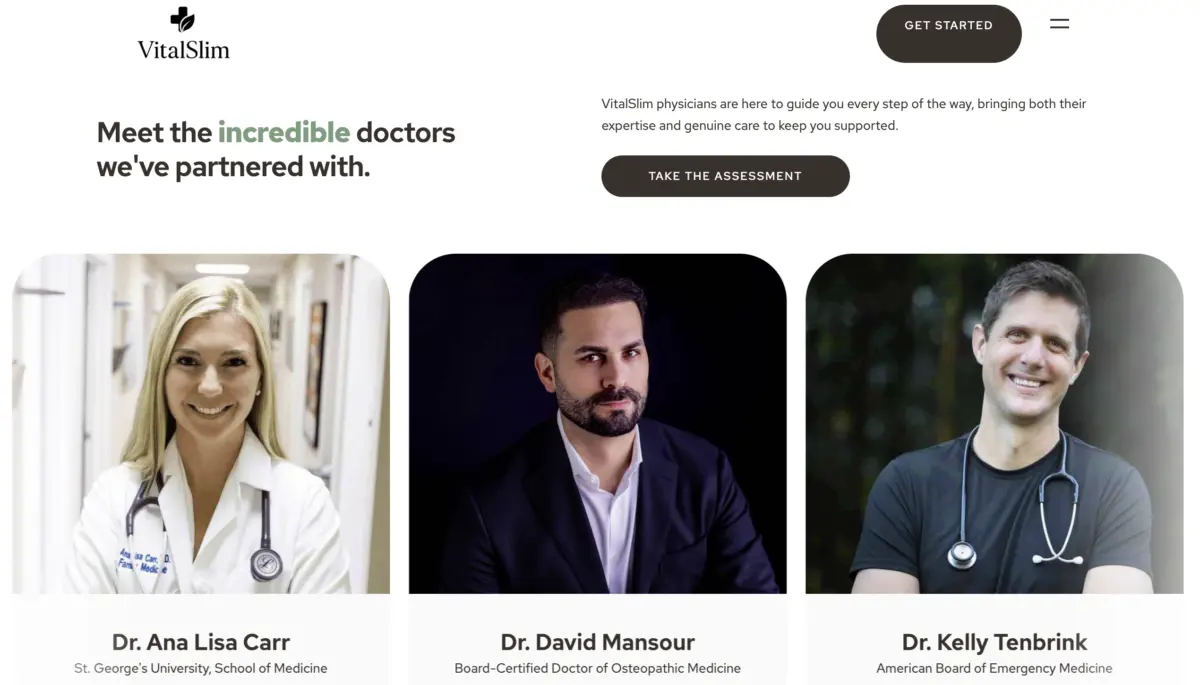
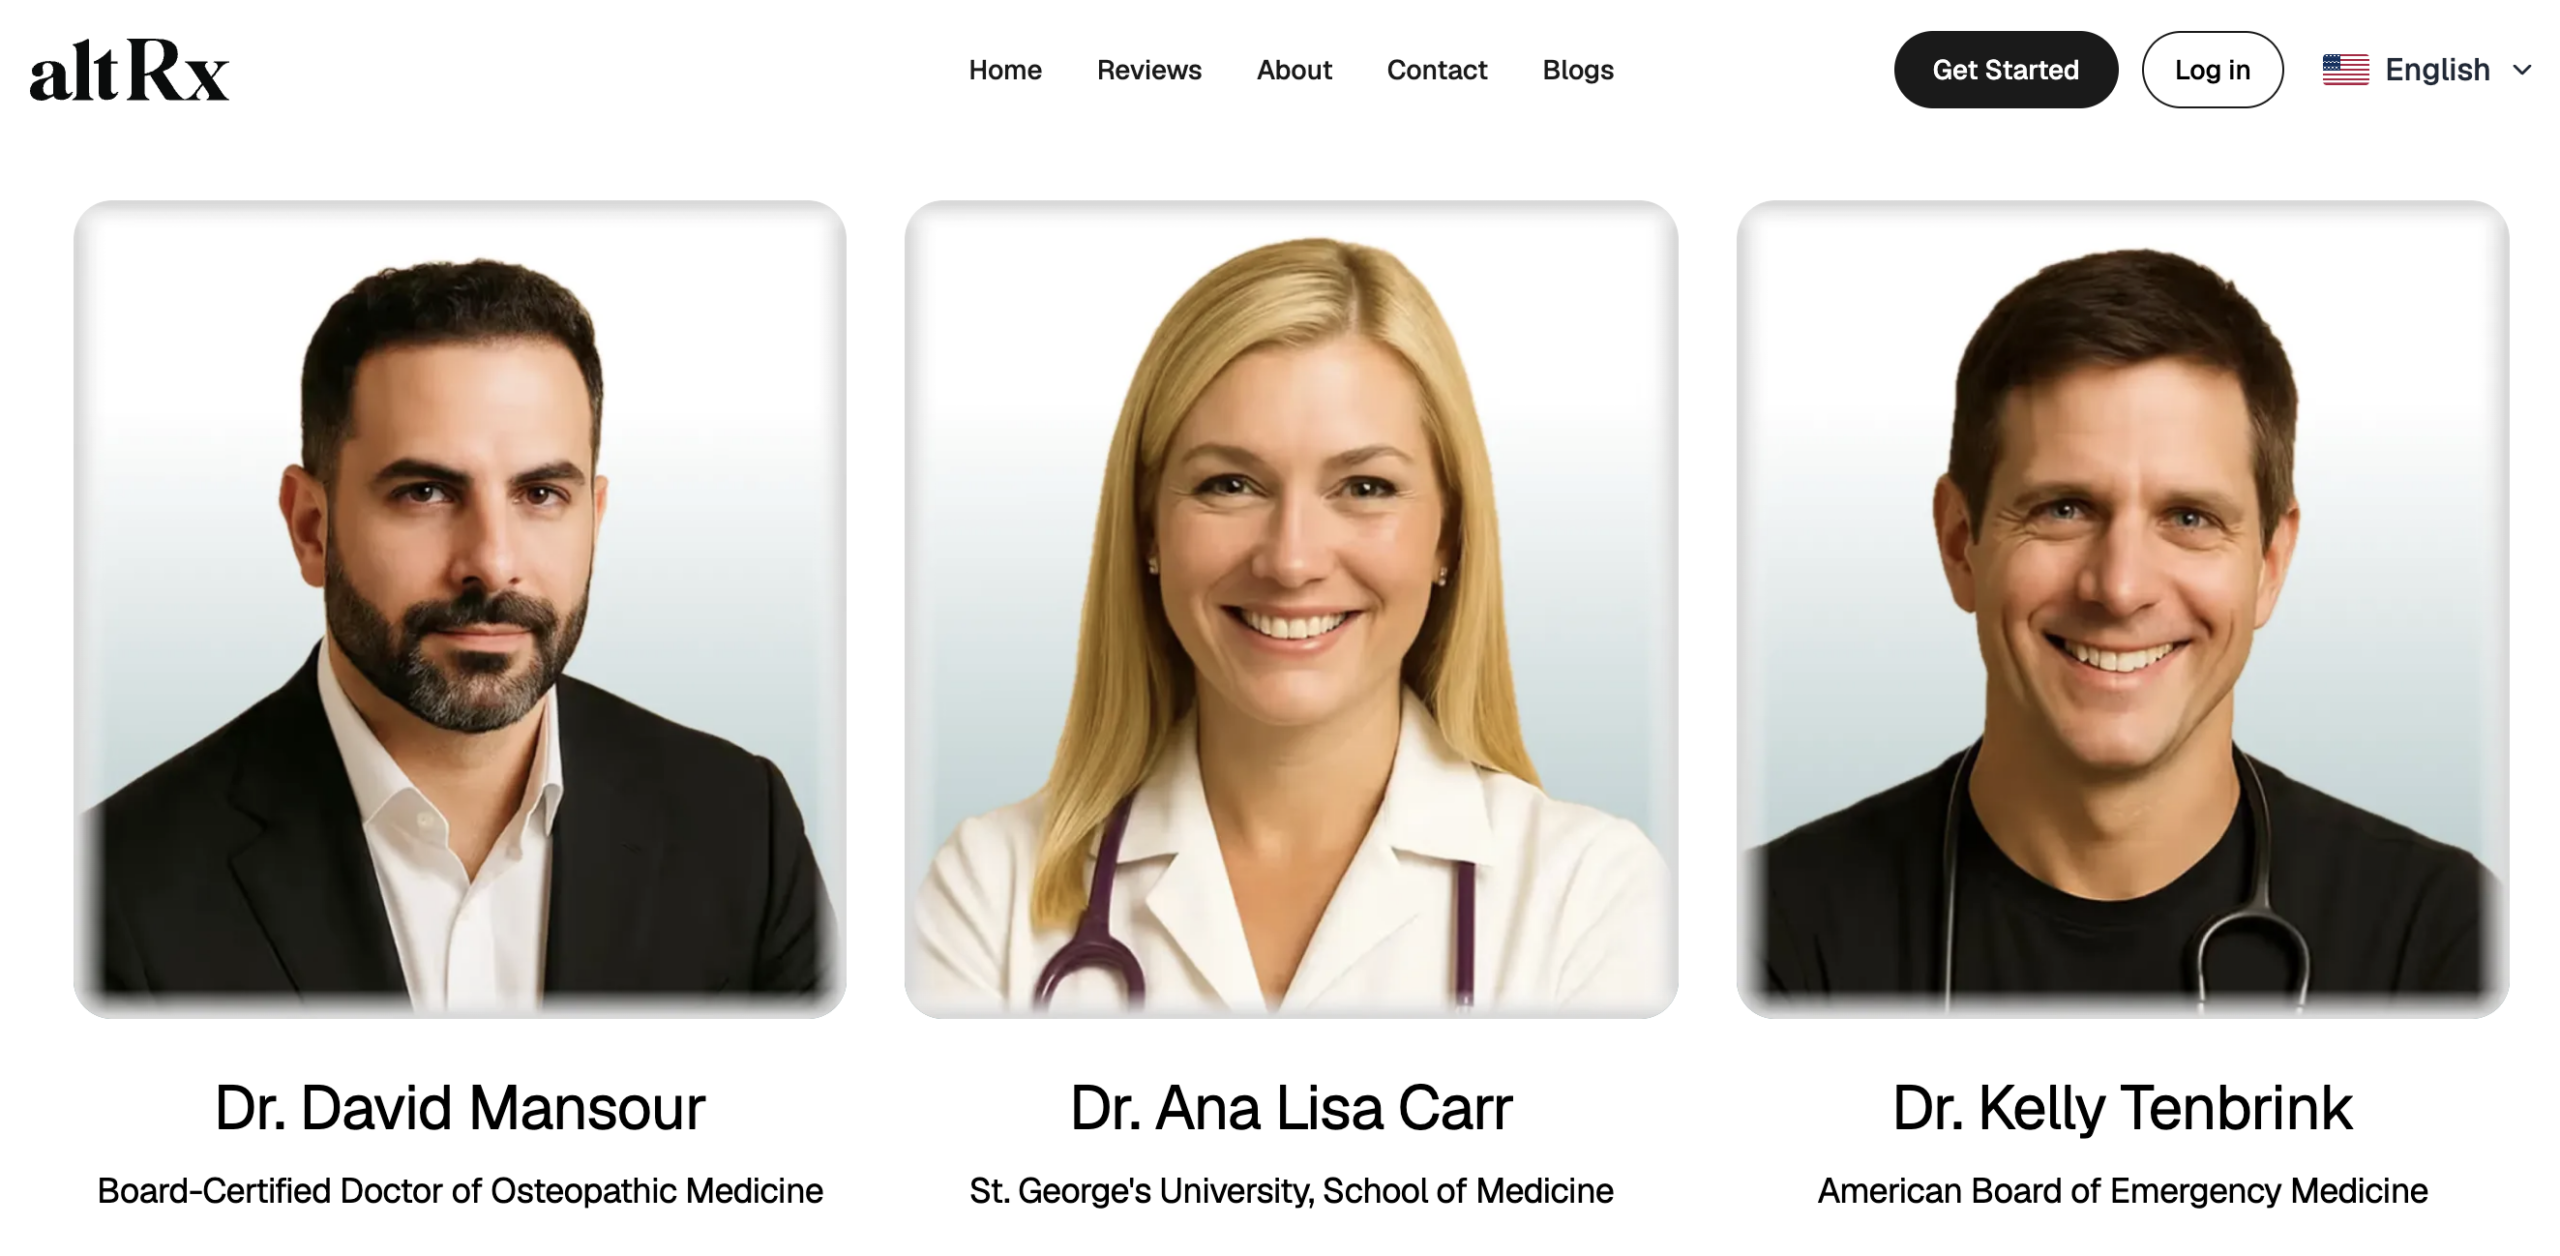
The industry’s playbook has become strikingly uniform: create slick, consumer-facing websites; utilize a revolving door of featured clinicians to build perceived legitimacy; and rely on a centralized infrastructure of pharmacy networks and telehealth provider platforms. Investigative findings reveal that multiple storefronts—such as VitalSlim, MDRxLabs, and AltRx—frequently feature the same roster of physicians, often sharing medical-provider networks like OpenLoop Health and pharmacy partners like Triad Rx. This interconnected ecosystem suggests that the "personalized medicine" promised by these platforms is often a standardized, high-volume manufacturing operation disguised as bespoke clinical care.
A Chronology of Regulatory Friction
The relationship between federal regulators and the compounding industry has been defined by a game of cat-and-mouse.

- 2022–2024: Following the official designation of semaglutide and tirzepatide as "in shortage," the FDA provided a narrow regulatory opening for state-licensed pharmacies to produce compounded versions of these drugs to meet patient needs.
- 2025 (The Year of Enforcement): As manufacturing capacity stabilized, the FDA began pulling the rug from under the industry. In September 2025 alone, the agency issued over 55 warning letters to online sellers. By May 22, 2025, the final "enforcement discretion" window had slammed shut, rendering the continued production of these copies legally tenuous.
- 2026 (Continued Crackdown): The FDA’s stance has hardened. In February 2026, the agency issued a formal warning letter to MEDVi, alleging that the company misled consumers by implying its products were FDA-approved equivalents. Further waves of warnings in March and June 2026 targeted dozens of telehealth entities for misbranding under the Federal Food, Drug, and Cosmetic Act (FDCA).
Mounting Safety Data and Clinical Risks
The allure of rapid weight loss has frequently eclipsed the reality of pharmaceutical safety. As of May 31, 2026, the FDA had logged 990 adverse event reports for compounded semaglutide and over 730 for compounded tirzepatide.
These numbers, however, likely represent a mere fraction of the true toll. Many state-licensed pharmacies are not mandated to report adverse events to federal authorities. Supplementing these figures, data from America’s Poison Centers highlights a staggering 1,500% increase in GLP-1 agonist exposure cases between 2019 and 2025.
The clinical dangers are compounded by delivery failures. Unlike the pre-filled, measured pens provided by original manufacturers, compounded products often arrive in vials requiring the patient to draw their own dosage. This has led to a spike in 10-fold dosing errors—cases where patients, confused by complex syringe measurement units, have accidentally administered lethal or sub-therapeutic doses. Furthermore, allegations of fraudulent labeling—where the pharmacy listed on the vial does not exist or was not the actual manufacturer—have introduced a new layer of uncertainty for the millions of Americans utilizing these services.
Official Responses and Industry Pushback
The industry’s response to these regulatory hurdles has been largely adversarial. The Outsourcing Facilities Association, representing many of the larger compounding entities, filed a lawsuit in late 2024 challenging the FDA’s decision to remove these drugs from the shortage list, arguing the agency acted prematurely.
On the legislative front, the bipartisan SAFE Drugs Act of 2025 represents the most significant attempt to curb the compounding boom. The bill seeks to limit compounding to no more than 20 units per month for drugs that are "essentially a copy" of an FDA-approved product. This proposal has sparked intense lobbying, with the Alliance for Pharmacy Compounding and the National Community Pharmacists Association arguing that such restrictions would unfairly stifle patient access to affordable care.
Meanwhile, the pharmaceutical giants—Novo Nordisk and Eli Lilly—have taken the fight to the courtroom. Novo Nordisk has initiated over 130 lawsuits across 40 states, successfully securing 44 permanent injunctions against companies accused of selling knock-off semaglutide. Lilly’s strategy has mirrored this, targeting not only the pharmacies but the telehealth "gatekeepers" that facilitate the sales.
The Implications of a "Shadow" Medical Model
The current state of the GLP-1 market raises profound questions about the future of digital health and patient safety.
1. The Erosion of Informed Consent
Many patients are drawn to these sites by aggressive marketing and promises of "weight loss solutions" that mirror the convenience of established pharma. However, as noted in reports regarding companies like FitRx and Zealthy, this convenience often masks predatory financial practices. Customers have reported insurmountable challenges in canceling recurring subscriptions, unauthorized charges, and a general lack of oversight regarding the medical necessity of their prescriptions.
2. The Legal Vulnerability of Telehealth
The ongoing civil RICO complaint against OpenLoop Health and Triad Rx marks a turning point in how these networks are viewed. By alleging that these companies provided the "black-box" infrastructure for storefronts to sell unproven drugs—such as oral tirzepatide, a formulation not marketed or validated by the original manufacturer—the litigation suggests that the telehealth platforms are not merely passive service providers, but active participants in an illicit supply chain.
3. Public Health at the Crossroads
The long-term impact on the public remains the most pressing concern. With as many as 1.5 million Americans potentially using compounded products, the medical community is bracing for the fallout. The combination of potentially impure, mislabeled, or incorrectly dosed medication, paired with a lack of consistent medical supervision, creates a perfect storm for chronic health complications.
Conclusion: A Regulatory Reckoning
The "Gold Rush" of compounded GLP-1s is reaching its inevitable breaking point. The FDA’s persistent enforcement, the wave of private litigation, and the potential passage of the SAFE Drugs Act signal that the era of unfettered access to "copycat" metabolic drugs is closing.
For the millions of patients currently navigating this system, the message from regulators is increasingly clear: the convenience of a telehealth prescription cannot replace the safety profile of an FDA-approved, rigorously tested pharmaceutical product. As the industry attempts to pivot, the focus must shift from rapid expansion and revenue maximization to the foundational pillars of healthcare—safety, transparency, and accountability. Whether the current network of telehealth and compounding providers can survive this transition, or whether they will be dismantled by the legal and regulatory forces now arrayed against them, remains the defining question of the next chapter in obesity medicine.
About the Author