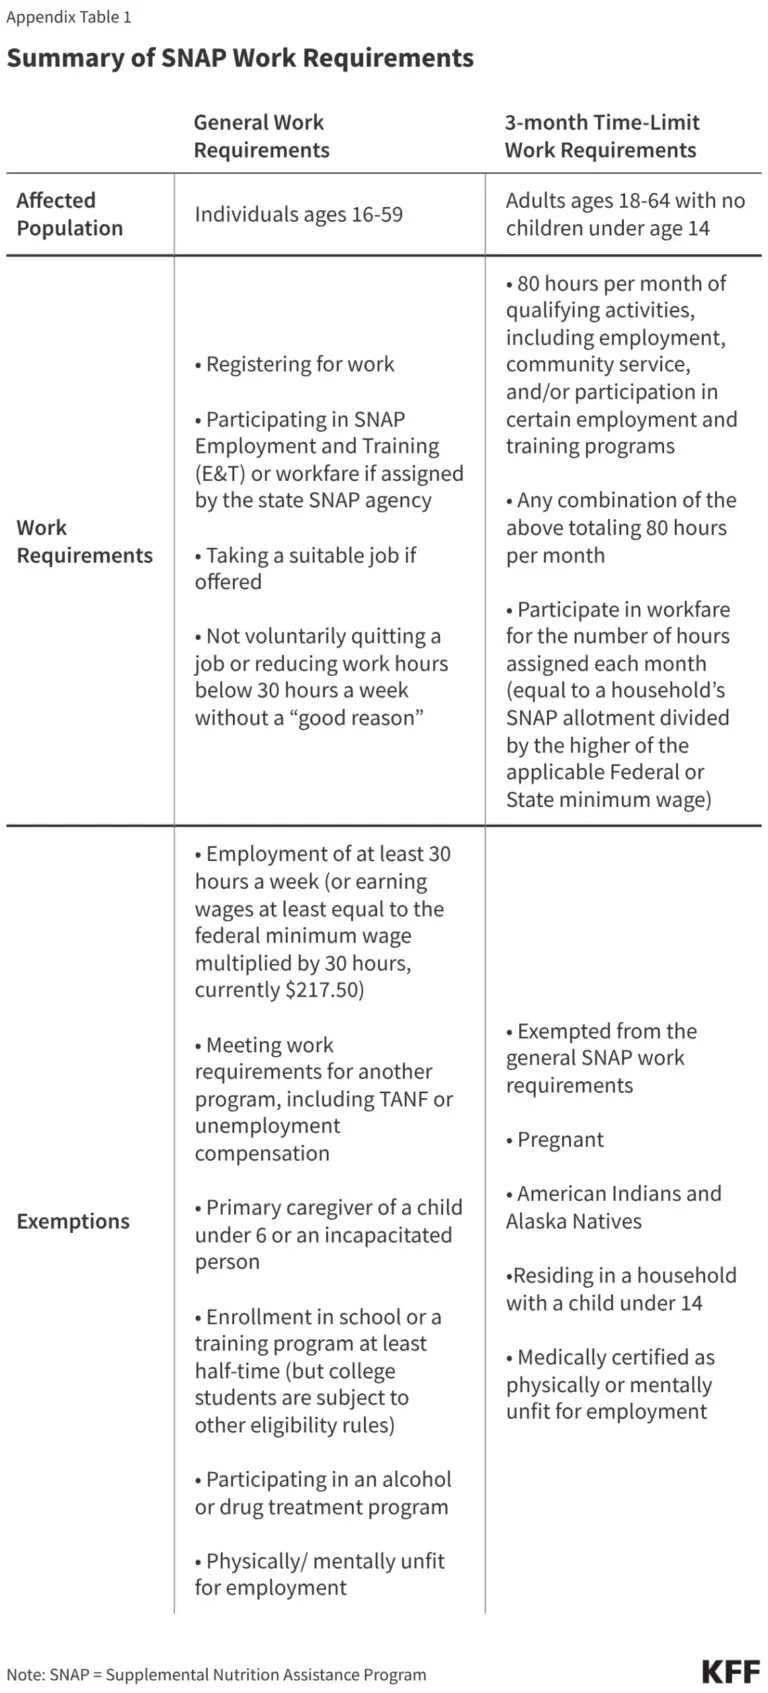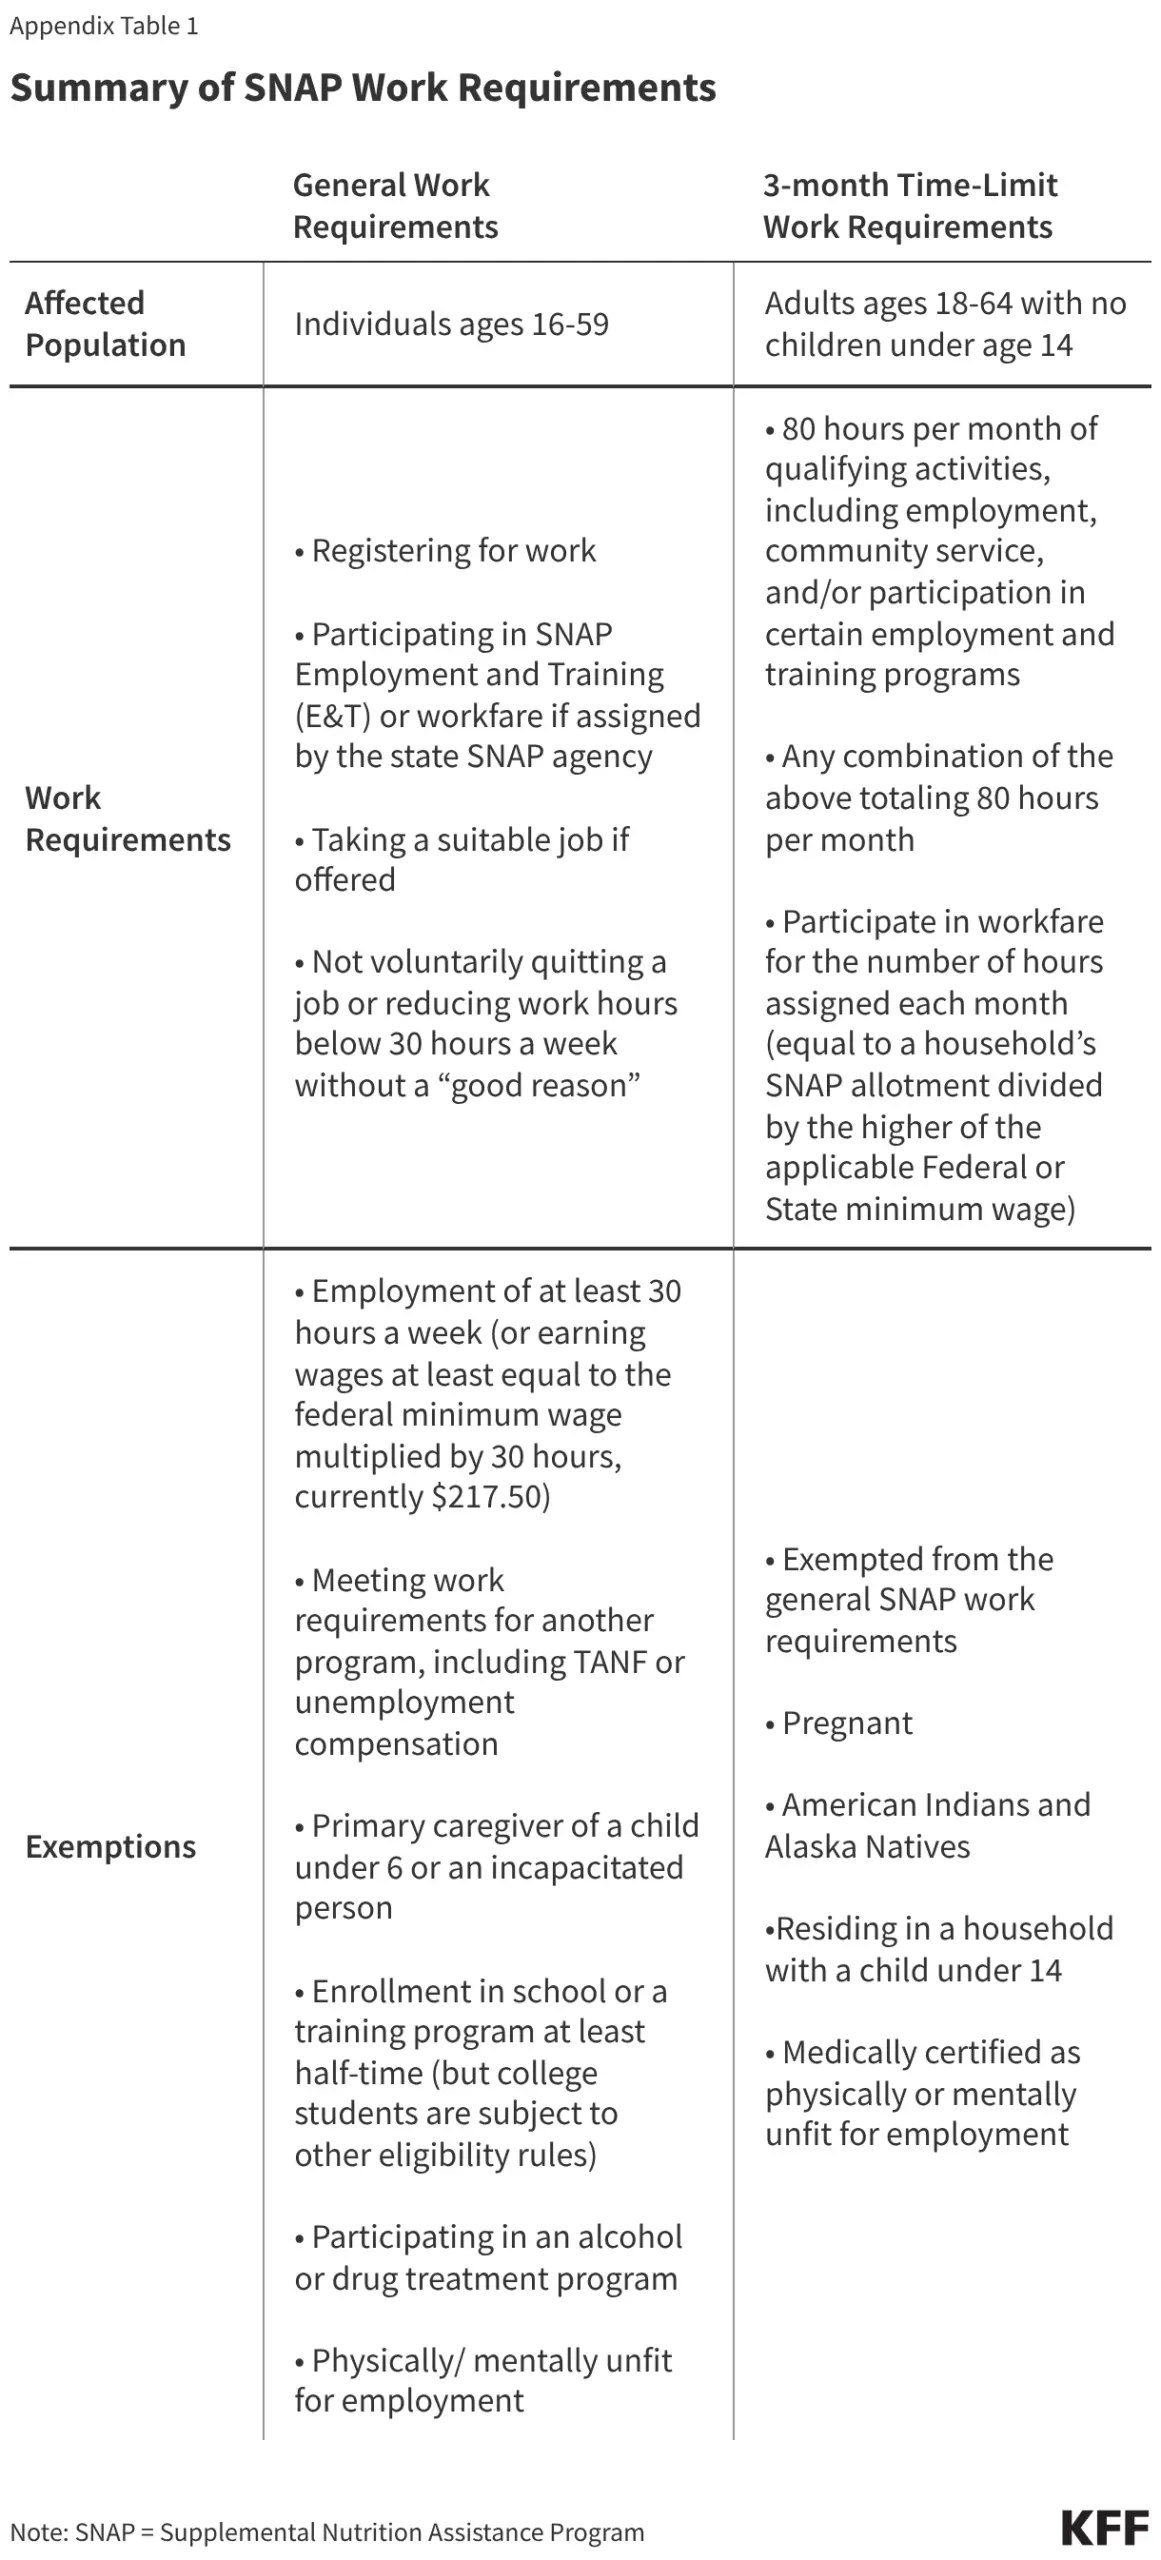
As the United States approaches a significant transformation in federal social safety net policy, the intersection of food security and healthcare access has become a focal point of administrative debate. Starting January 1, 2027—or sooner, at the discretion of individual states—44 states will be mandated to implement work requirements as a condition for Medicaid eligibility for adults within the Affordable Care Act (ACA) expansion group and certain waiver programs. This shift mirrors long-standing policies within the Supplemental Nutrition Assistance Program (SNAP), setting the stage for a complex, dual-layered administrative challenge.
As states scramble to build the infrastructure required to verify "medical frailty" and "fitness for work," the lessons learned from the SNAP program—often characterized by inconsistent definitions and heavy administrative burdens—are being scrutinized. With billions of federal dollars and millions of low-income lives at stake, the pressure to balance program integrity against the necessity of ensuring access for the vulnerable has never been higher.
Main Facts: The New Landscape of Federal Aid
The core of the upcoming policy change is the expansion of work requirements from the nutrition sector into the healthcare sector. While SNAP has historically conditioned benefits on work for able-bodied adults, the new mandate applies this philosophy to Medicaid, specifically targeting the expansion population.
Central to these regulations is the "medical frailty" exemption. Lawmakers have recognized that forcing individuals with significant health impairments into the workforce is both impractical and potentially harmful. However, defining "medically frail" is a complex task. To qualify, an individual must have a documented qualifying condition and prove that the condition directly impairs their ability to meet employment mandates.
CMS has introduced a tiered framework to assist states, but the flexibility remains high. States are not strictly bound to federal verification methods, leading to a patchwork of potential policies. This uncertainty is exacerbated by the fact that SNAP and Medicaid—while both federal programs—operate under vastly different regulatory and data-sharing architectures.
Chronology of Implementation and Policy Evolution
The transition toward these unified work mandates is not sudden; it is the culmination of years of legislative maneuvering.
- Pre-2027: SNAP continues its long-standing model of state-defined fitness, where eligibility workers conduct interviews and exercise discretion in granting exemptions for physical or mental limitations.
- June 2026: CMS releases an interim final rule providing guidance on the community engagement requirements for Medicaid. This document introduces the tiered verification approach for medical frailty.
- January 1, 2027: The federal deadline for the 44 affected states to link Medicaid eligibility to work requirements.
- October 2027: A critical shift in SNAP fiscal accountability begins, where states become liable for a portion of benefit costs if their Payment Error Rate (PER) exceeds 6%.
- January 1, 2028: The window for Medicaid self-attestation of medical frailty closes. After this date, states are strictly limited in their ability to accept client statements as sufficient proof of exemption, forcing a reliance on automated data or formal provider documentation.
Supporting Data: The SNAP Precedent and Administrative Variation
The historical performance of SNAP provides a cautionary tale regarding the dangers of administrative discretion. Federal regulations currently allow states to define "physical or mental unfitness" for employment with minimal national standardization.
The Role of the Eligibility Worker
In the current SNAP model, the in-person or phone interview is the primary gatekeeper. Eligibility workers—who often lack medical training—frequently rely on visual observations or subjective assessments to determine if a recipient is "obviously unfit" for work. Evaluations have shown that this creates significant inconsistency: one worker might grant an exemption for a client using an oxygen tank, while another might demand formal medical documentation for the same individual.
The Documentation Burden
When unfitness is not "obvious," states require medical provider statements. However, the lack of standardized forms or guidance for medical professionals leads to a wide spectrum of responses. Some states require comprehensive clinical reports, while others accept a simple check-box form. This creates an "administrative tax" on both the healthcare system and the applicant. Providers, often overwhelmed by the paperwork, may provide inconsistent evaluations, leading to unequal access to benefits based solely on the applicant’s state of residence.
Financial Penalties and "Defensive" Administration
The introduction of the Payment Error Rate (PER) penalties in SNAP has already begun to change state behavior. In Arizona, for instance, the threat of fiscal penalties has led the state to abandon client self-attestation in favor of rigorous, mandatory documentation. This "defensive administration" protects the state budget but often results in the unintended denial of benefits to eligible individuals who cannot navigate the complex documentation requirements.

Official Responses and CMS Guidance
The Centers for Medicare & Medicaid Services (CMS) has acknowledged the difficulty of this transition. The agency’s "tiered medical frailty framework" is designed to reduce the burden on individuals by utilizing existing data:
- Tier 1: Automated verification using existing claims and encounter data from the previous 12 months.
- Tier 2: A combination of claims data and supplemental state-level information.
- Tier 3: An individualized, manual process requiring external documentation for new enrollees or those with insufficient medical history in the system.
Despite this framework, CMS has faced criticism from advocacy groups who argue that the tiered system still places an undue burden on new applicants—the very group least likely to have a robust 12-month claims history. Furthermore, CMS has signaled that states found to be "too lenient" in granting medical frailty exemptions during federal audits could face financial clawbacks. This creates a powerful incentive for states to adopt highly restrictive, rather than inclusive, interpretations of medical frailty.
Implications: The High Stakes for Vulnerable Populations
The implications of this policy shift are profound, affecting everything from state budget management to individual health outcomes.
The Risk of "Churn"
The most immediate risk is the phenomenon of "churn"—individuals cycling on and off Medicaid due to administrative errors or the inability to provide timely documentation. When individuals lose coverage because they could not navigate the verification process, they often lose access to the very medical care that manages their chronic conditions, ironically leading to worse health outcomes and higher long-term costs for the healthcare system.
Data Interoperability Challenges
While Medicaid has access to claims data that SNAP lacks, the quality of that data is highly dependent on provider coding practices. If doctors fail to use the specific codes that match the state’s exemption criteria, patients will be forced into the manual, Tier 3 verification process, regardless of their actual health status. This highlights the gap between administrative data and clinical reality.
A New Era of State-Level Disparity
By 2028, the landscape of social safety net access will be more fragmented than ever. A resident in a state that utilizes robust data-sharing between SNAP and Medicaid may find it easy to maintain coverage, while a resident in a state with rigid documentation requirements and high error-rate anxiety may find themselves repeatedly cut off from essential services.
Fiscal vs. Human Cost
The ultimate irony of these policies is the conflict between the goals of program integrity and social support. While the government aims to reduce "waste" and "error," the mechanisms used to achieve this—increasing the complexity of application and renewal processes—inevitably create barriers for those who need the services most.
As states prepare for the January 2027 rollout, the success of these programs will depend on whether policymakers can shift from a mindset of "policing eligibility" to one of "facilitating access." Without clear, uniform national standards for medical frailty and a commitment to protecting the most vulnerable from administrative churn, the implementation of these work requirements threatens to exacerbate the very poverty and ill-health they were intended to address.
For the millions of Americans relying on Medicaid and SNAP, the coming years will not just be about navigating a new bureaucratic process; they will be about the fundamental stability of their access to food and medical care in an increasingly restrictive federal environment.
About the Author