As the U.S. healthcare landscape prepares for the 2027 plan year, a significant portion of the immigrant population faces a daunting new reality. The 2025 reconciliation law has introduced stringent eligibility requirements for federally funded health programs, fundamentally altering the path to coverage for millions of lawfully present immigrants. These legislative changes represent one of the most substantial retrenchments of the Affordable Care Act (ACA) since its inception, effectively decoupling "lawful presence" from "subsidy eligibility."
Main Facts: The New "Eligible Noncitizen" Framework
Starting January 1, 2027, the 2025 reconciliation law restricts access to premium tax credits (PTCs) and cost-sharing reductions (CSRs)—the financial cornerstones that make Marketplace insurance affordable—to a narrower subset of individuals. Under the new guidelines, only those classified as "eligible noncitizens" will retain access to federal subsidies.
This category is strictly defined to include:
- Lawful Permanent Residents (LPRs): Commonly referred to as "green card" holders.
- Cuban and Haitian Entrants: Individuals granted specific humanitarian status.
- COFA Residents: People residing in the U.S. under the Compacts of Free Association.
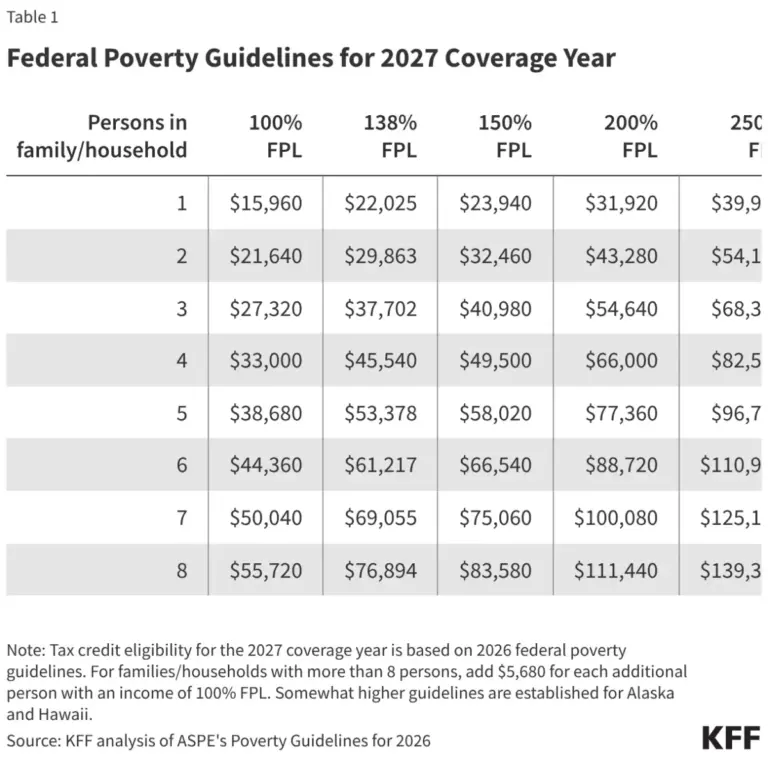
Crucially, this policy excludes a vast array of other lawfully present immigrants, including refugees and asylees who have not yet secured a green card, as well as those residing in the country on various work visas. While these individuals may technically remain "lawfully present" under broader immigration law, they are no longer recognized as "eligible noncitizens" for the purposes of federal health subsidies. Furthermore, the law has already phased out subsidy access for any lawfully present immigrant earning less than 100% of the Federal Poverty Level (FPL) who does not qualify for Medicaid, a change that took effect in early 2026.
Chronology of Implementation
The transition to this new regime is being executed in stages, creating a compressed timeline for both federal agencies and enrollees:
- January 1, 2026: The first phase of the law took effect, barring lawfully present immigrants earning below 100% of the FPL from accessing subsidized Marketplace plans.
- November 1, 2026: The start of the Open Enrollment Period for the 2027 plan year. This serves as the primary window for the Federally Facilitated Exchange (FFE) to conduct mass eligibility redeterminations.
- January 1, 2027: The formal implementation date for the new "eligible noncitizen" restrictions. On this day, subsidies for those failing to meet the new criteria will be officially terminated, and individuals determined to be ineligible for coverage will lose their plans.
- 2028 Tax Year: A secondary shift will occur where the Exchange must verify all eligibility data—including income, family size, and immigration status—before any PTCs can be issued, replacing the current "pay first, verify later" system.
Supporting Data: The Scope of Impact
The financial and human impact of these provisions is substantial. The Congressional Budget Office (CBO) has projected that these measures will reduce federal spending by approximately $91.4 billion over the next decade. However, this fiscal savings comes at a significant cost to public health: the CBO estimates that an additional one million individuals will become uninsured by 2035 as a direct result of the 2027 restrictions.
The 2026 eligibility changes, which targeted low-income immigrants, are expected to add another 200,000 individuals to the ranks of the uninsured, contributing an additional $27.3 billion in reduced federal spending. When combined, these figures suggest that the 2025 law will effectively reverse years of progress in reducing the uninsured rate among immigrant communities, particularly in states with high concentrations of work-visa holders and asylees.
Official Responses and Administrative Procedures
The Centers for Medicare and Medicaid Services (CMS) has been tasked with the monumental burden of operationalizing these changes. For the 29 states relying on the FFE, CMS has updated its platform to reflect the new criteria, utilizing the Department of Homeland Security’s Systematic Alien Verification for Entitlements (SAVE) system to conduct automated data matching.
The Verification Challenge
A primary point of contention is the reliance on the SAVE system. Advocates and CMS itself have noted that SAVE provides only "point in time" verification. It often fails to capture recent adjustments in immigration status—such as a refugee who has recently received a green card but whose file has not been updated in the federal database.

If the system cannot automatically verify an enrollee’s status, that individual is granted a 95-day "reasonable opportunity period" to submit physical documentation. Failure to resolve these discrepancies by the deadline will result in the immediate cessation of subsidies. Even more concerning is the fate of those who are auto-enrolled into unsubsidized plans; they will be responsible for the full, market-rate premium. If they fail to make these payments, they risk losing coverage entirely and may be held liable for any medical costs incurred during the grace period.
State-Based Exchange (SBE) Variability
While states operating their own exchanges must also comply with the federal law, they maintain local autonomy regarding outreach and verification. This has created a patchwork system where, in some states, outreach is robust, while in others, the administrative burden of verifying noncitizen status is straining resources, particularly as states concurrently manage new requirements for Medicaid and ACA expansion populations.
Implications: A Looming Public Health Crisis
The ramifications of this policy extend far beyond the administrative offices of the Marketplace. Experts are warning of a "chilling effect" that could ripple through immigrant communities.
Financial Hardship and the Loss of Safety Nets
For many, the loss of subsidies renders insurance mathematically impossible to afford. As ACA Marketplace premiums rise—driven by the expiration of enhanced tax credits—the "unsubsidized" option is effectively a non-option for working-class families. This leaves families with the choice of either paying ruinous premiums or dropping coverage entirely, which carries long-term risks, including the potential for significant debt if a medical emergency occurs.
Confusion and Fear
The landscape is further complicated by the intersection of these health policies with broader federal immigration enforcement. Even those who remain eligible for subsidies may choose to disenroll out of fear that their data could be used for immigration enforcement, or due to general confusion regarding the "public charge" rule. The cumulative effect of these pressures is a profound sense of instability for mixed-status families, who must now weigh the necessity of health insurance against the perceived risks of engaging with government systems.
The "Last Resort" Burden
As federal pathways close, the burden of care will inevitably shift to community health centers and state-funded programs. However, these systems are already operating at capacity. While states like New Mexico have moved to fill the gaps with state-funded subsidies, most states lack the fiscal surplus to do so. The trend, in fact, has been the opposite: several states have recently scaled back their own immigrant-coverage initiatives due to the same budget pressures that motivated the federal law.
The Future of "Mixed-Status" Household Planning
Looking toward 2028, the requirement for pre-enrollment verification of all data points marks a fundamental change in the ACA experience. For households with mixed immigration status, this will create a logistical nightmare. Parents may be forced to decide whether to secure coverage for their U.S. citizen children while leaving themselves vulnerable, or to navigate a system that effectively penalizes them for their documentation status.
Conclusion
The 2025 reconciliation law marks a decisive pivot in American social policy. By prioritizing federal savings over broad-based health coverage, the legislation has created a new, complex tier of insurance eligibility that will undoubtedly lead to a significant increase in the uninsured population. As the November 2026 enrollment period approaches, the success or failure of this transition will depend heavily on whether states and the federal government can mitigate the administrative hurdles and clear up the widespread confusion threatening the health and financial security of millions.
About the Author