As the Medicare open enrollment period for 2027 officially commences, millions of American seniors and individuals with disabilities face a significantly more complex and costly landscape for prescription drug coverage. New data from the Centers for Medicare & Medicaid Services (CMS) reveals that beneficiaries must be more diligent than ever in reviewing their options, as the era of "automatic" plan stability has been replaced by a market defined by sharper premium hikes and shifting cost-sharing structures.
For the average Medicare beneficiary, the landscape includes a choice between 28 different Medicare Advantage prescription drug plans (MA-PDs) and 9 stand-alone prescription drug plans (PDPs). While the sheer volume of choices might seem beneficial, the financial disparity between these options has reached a critical juncture.
Main Facts: The Premium Surge
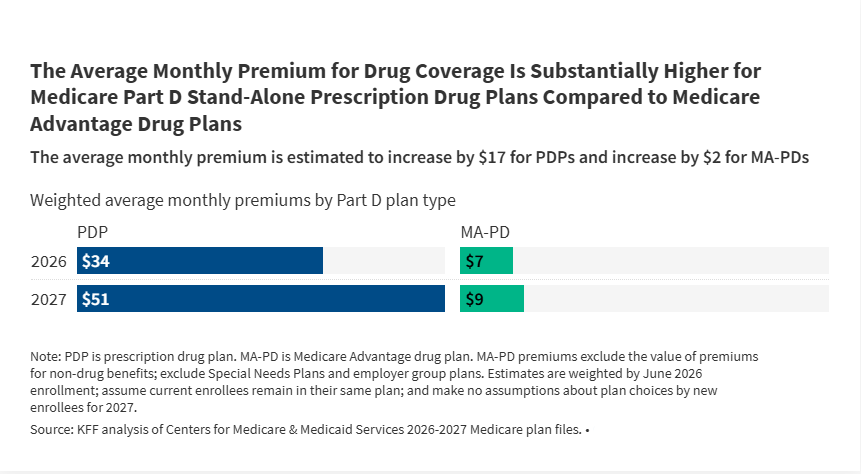
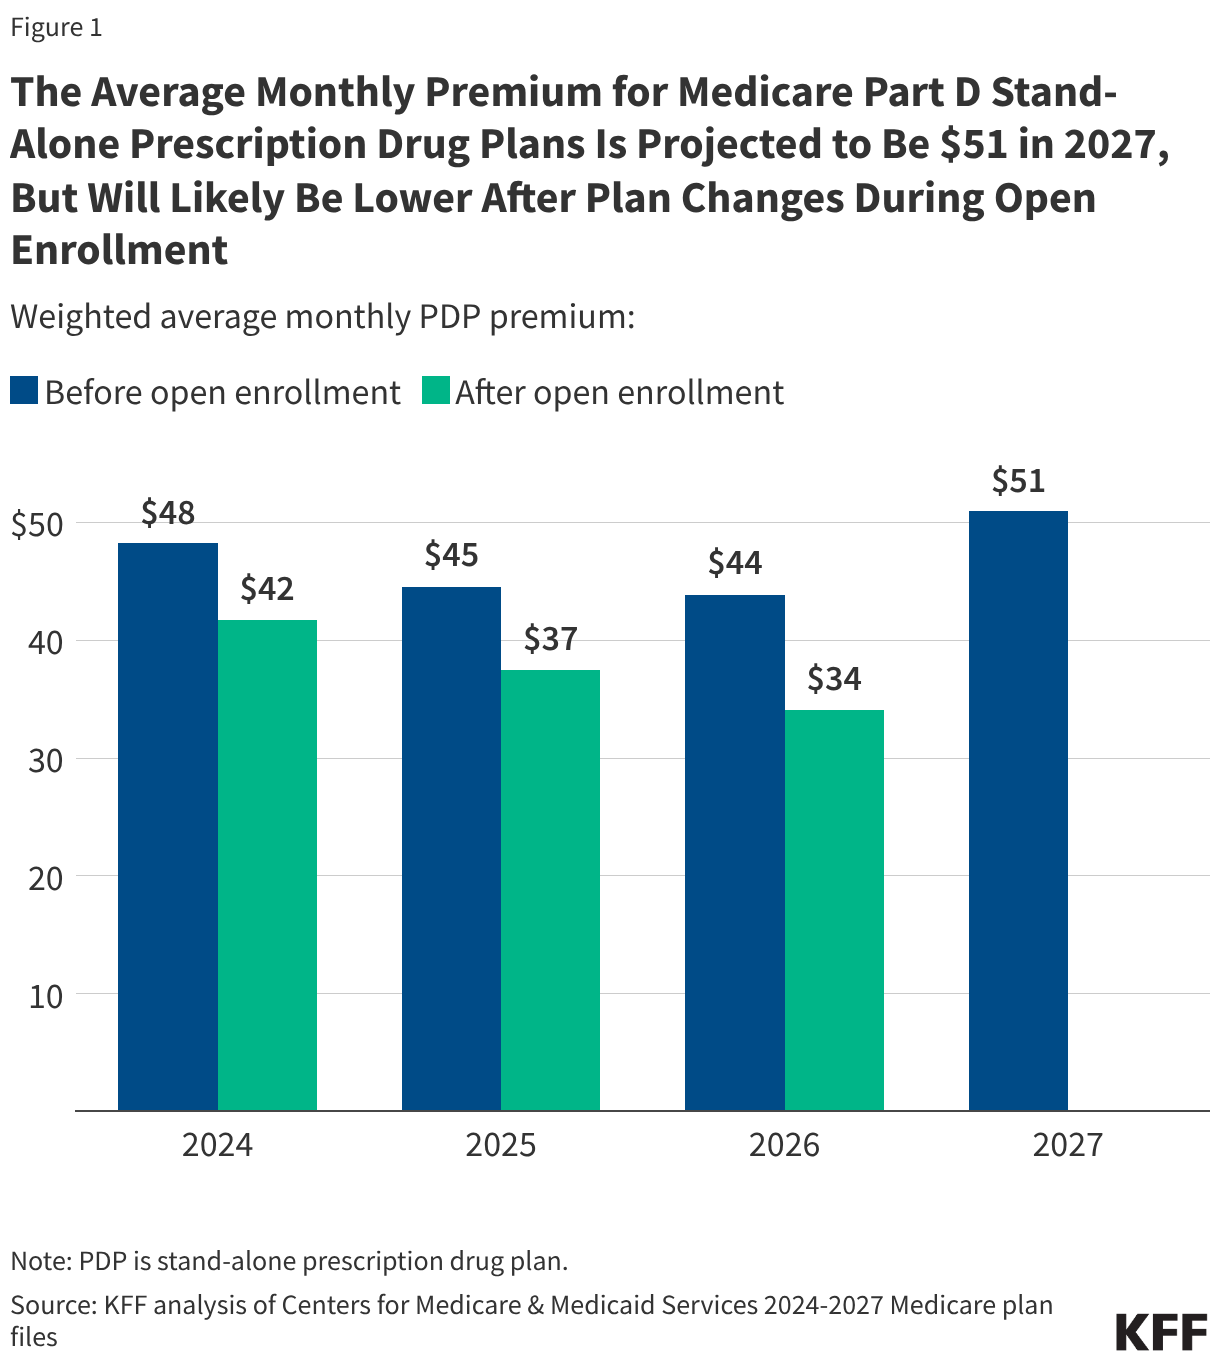
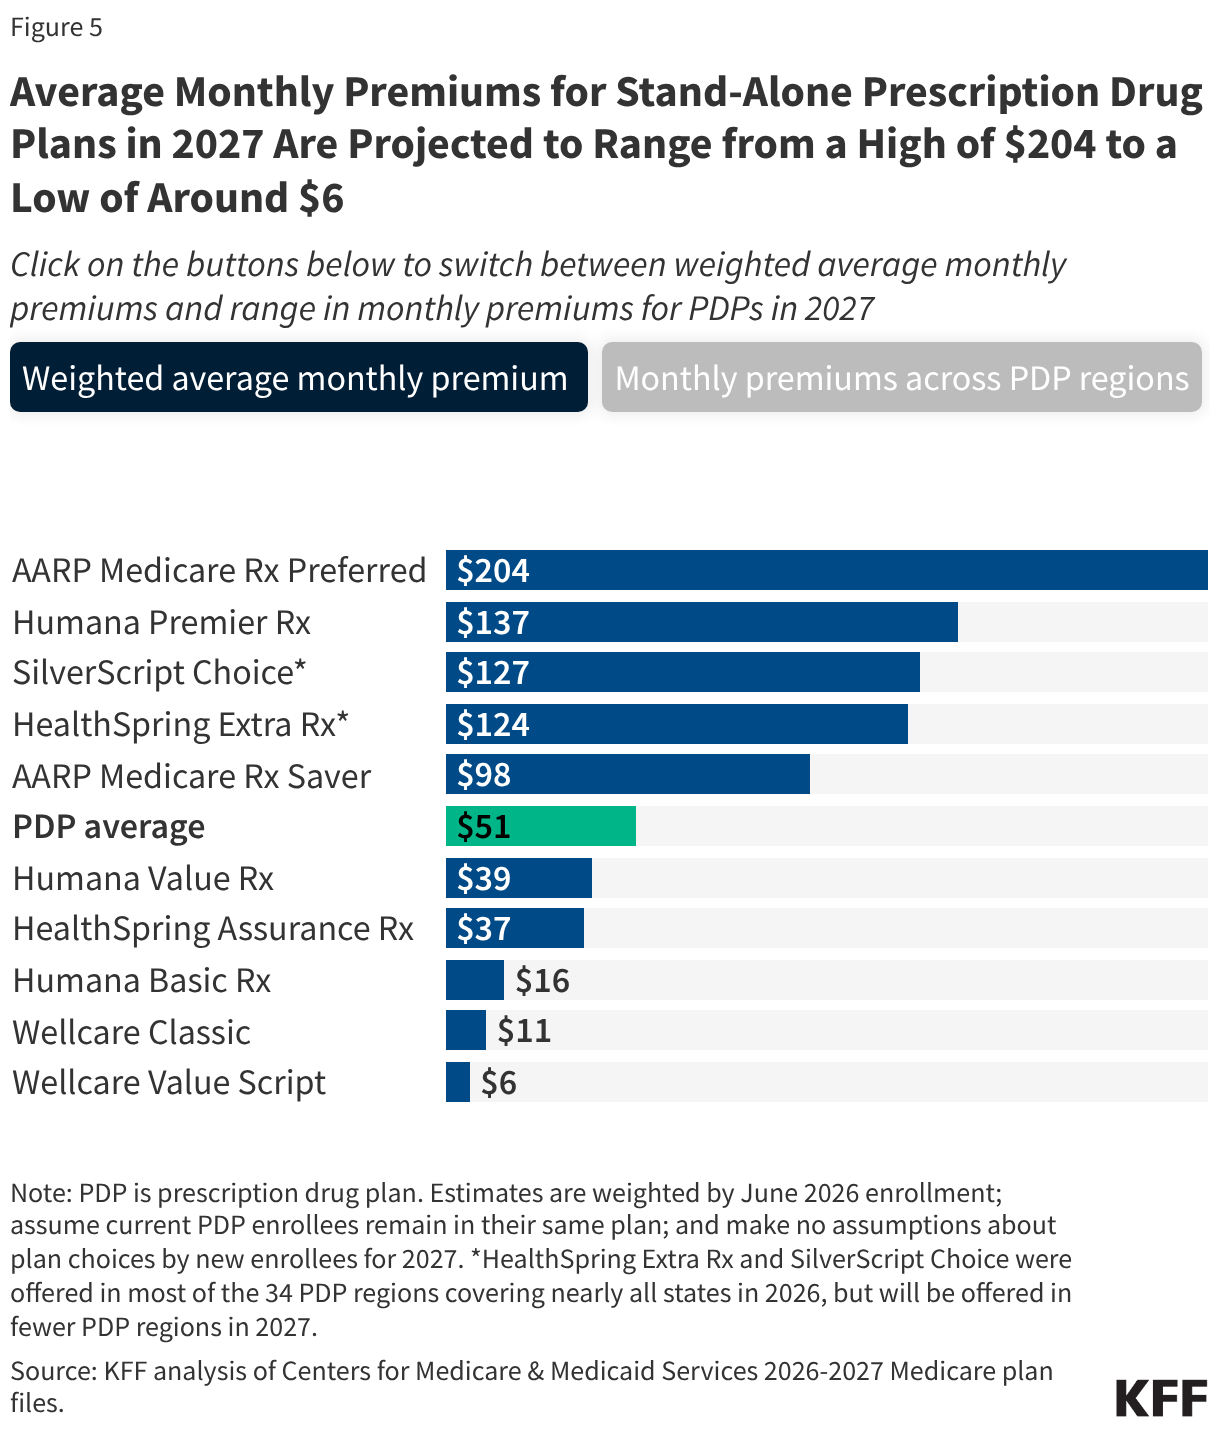
The most striking development for 2027 is the projected increase in premiums for stand-alone prescription drug plans (PDPs). If enrollees simply renew their current coverage without taking action, the average monthly premium is projected to jump from $34 in 2026 to $51 in 2027—a 50% increase.
While CMS has issued a more modest projection of a $36 average premium, this figure appears to account for an assumption that beneficiaries will proactively switch to lower-cost plans. However, for the millions of seniors who do not actively compare their options, the reality of the market reflects the higher $51 figure. This volatility is driven largely by the expiration of the Part D Premium Stabilization Demonstration, a federal initiative that previously capped premium increases and provided subsidies to plan sponsors. With that program now sunsetting, the "safety net" for premiums has vanished.
A Chronology of Changing Costs
To understand the current climate, one must look at the recent trajectory of Medicare Part D. In 2025, the market began showing signs of stress, with average premiums hovering around $37. By 2026, despite initial fears of steep increases, the market stabilized partially due to the aforementioned demonstration project, keeping the weighted average premium at $34.
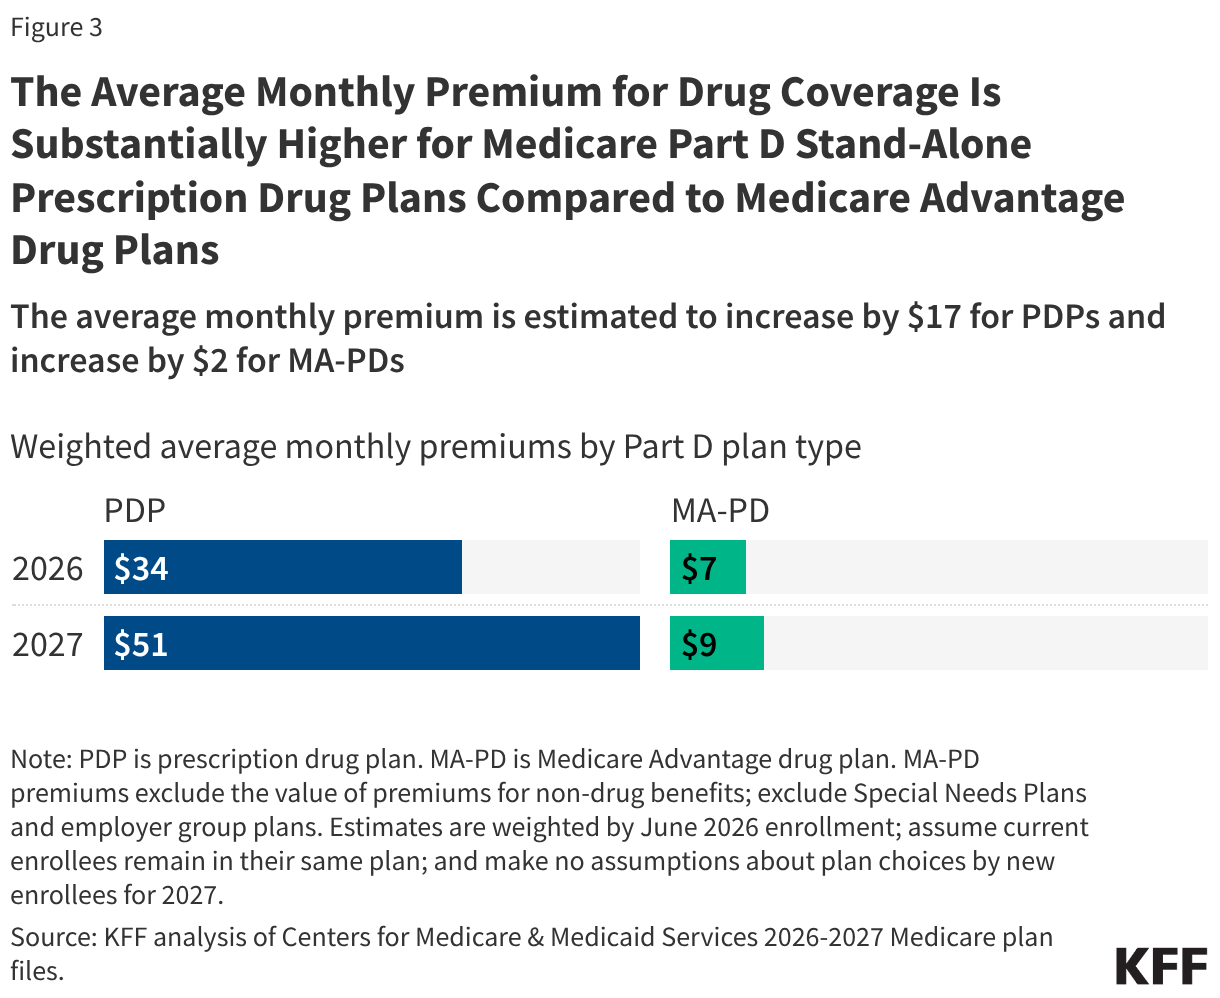
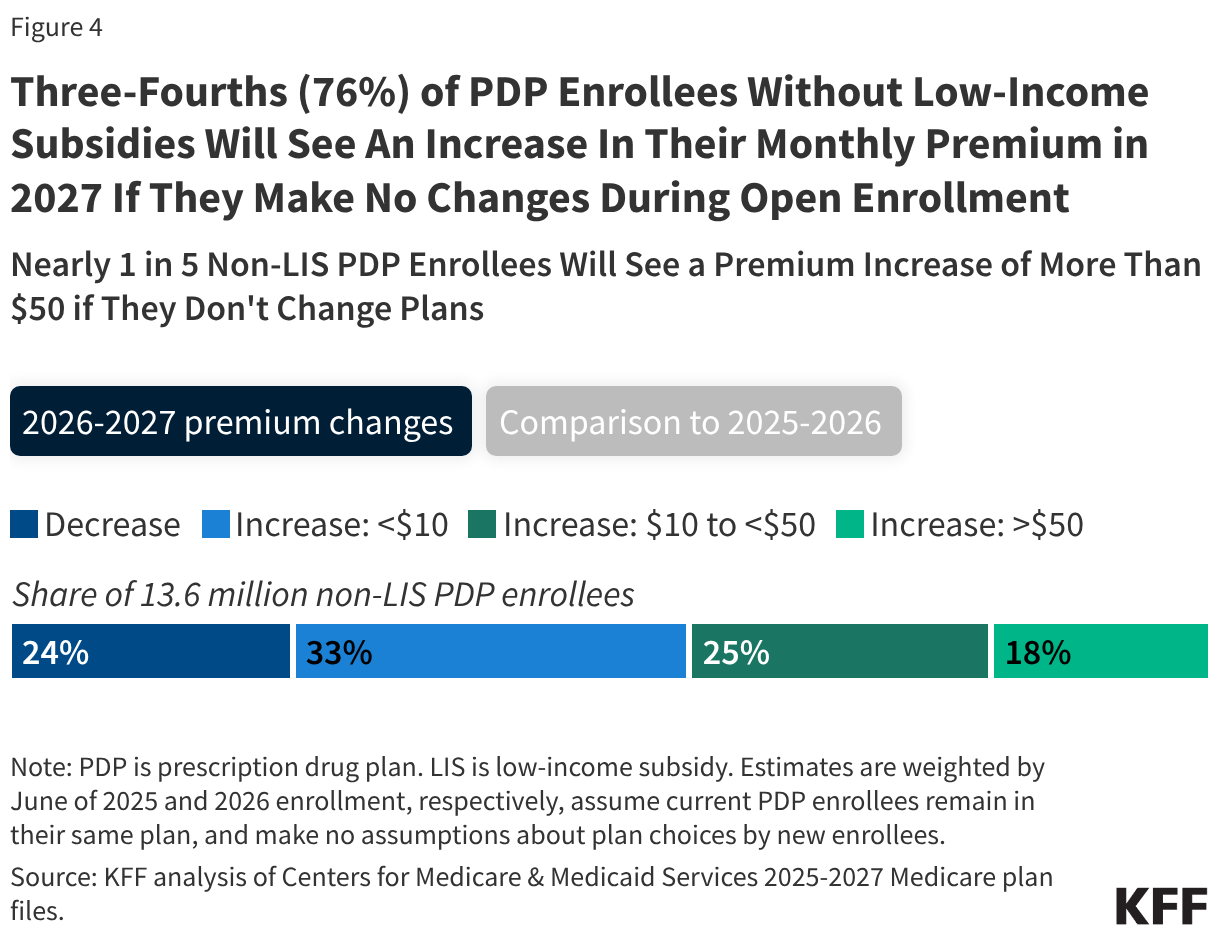
However, the 2027 transition marks a structural break. The discontinuation of federal subsidies means that plan sponsors are no longer shielded from the rising costs of drug coverage. Consequently, the "no-premium" PDP options that many beneficiaries relied upon in 2026 have effectively disappeared from the market. For those who stayed in their plans during the 2025-2026 window, the transition to 2027 represents a "sticker shock" moment, as 76% of non-Low-Income Subsidy (LIS) enrollees will face a higher premium if they remain in their current plan.
Supporting Data: The Great Divide
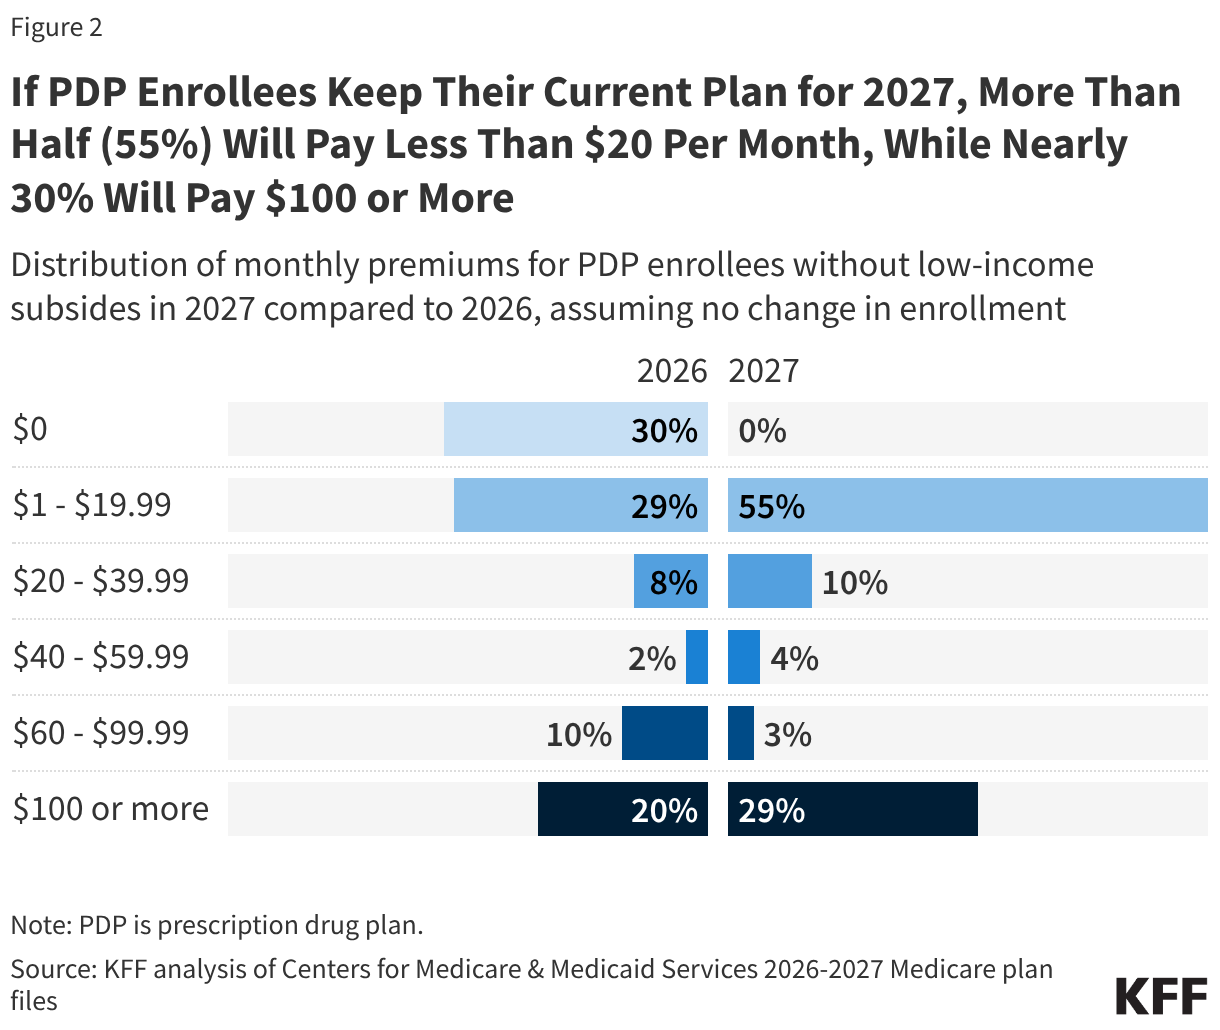
The divergence between stand-alone PDPs and Medicare Advantage prescription drug plans (MA-PDs) has never been more pronounced.
- Premium Disparity: While PDP enrollees are looking at an average of $51 per month, MA-PD enrollees face an average of just $9 per month.
- The "Rebate" Factor: This massive gap is not accidental. MA-PD sponsors are permitted to use federal "rebate dollars"—payments derived from Medicare’s overall funding for private plans—to subsidize or eliminate drug premiums. There is no equivalent mechanism for stand-alone PDPs. Consequently, while 8 in 10 MA-PD enrollees enjoy a $0 premium for their drug coverage, the stand-alone PDP market has become a high-cost environment for those without government subsidies.
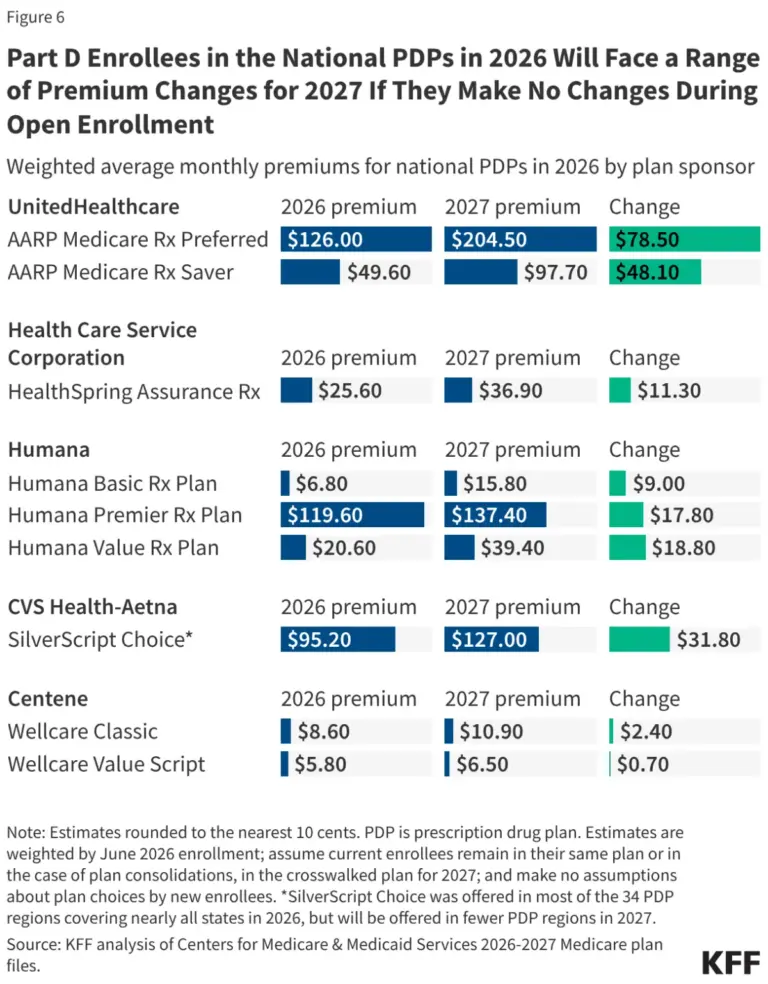
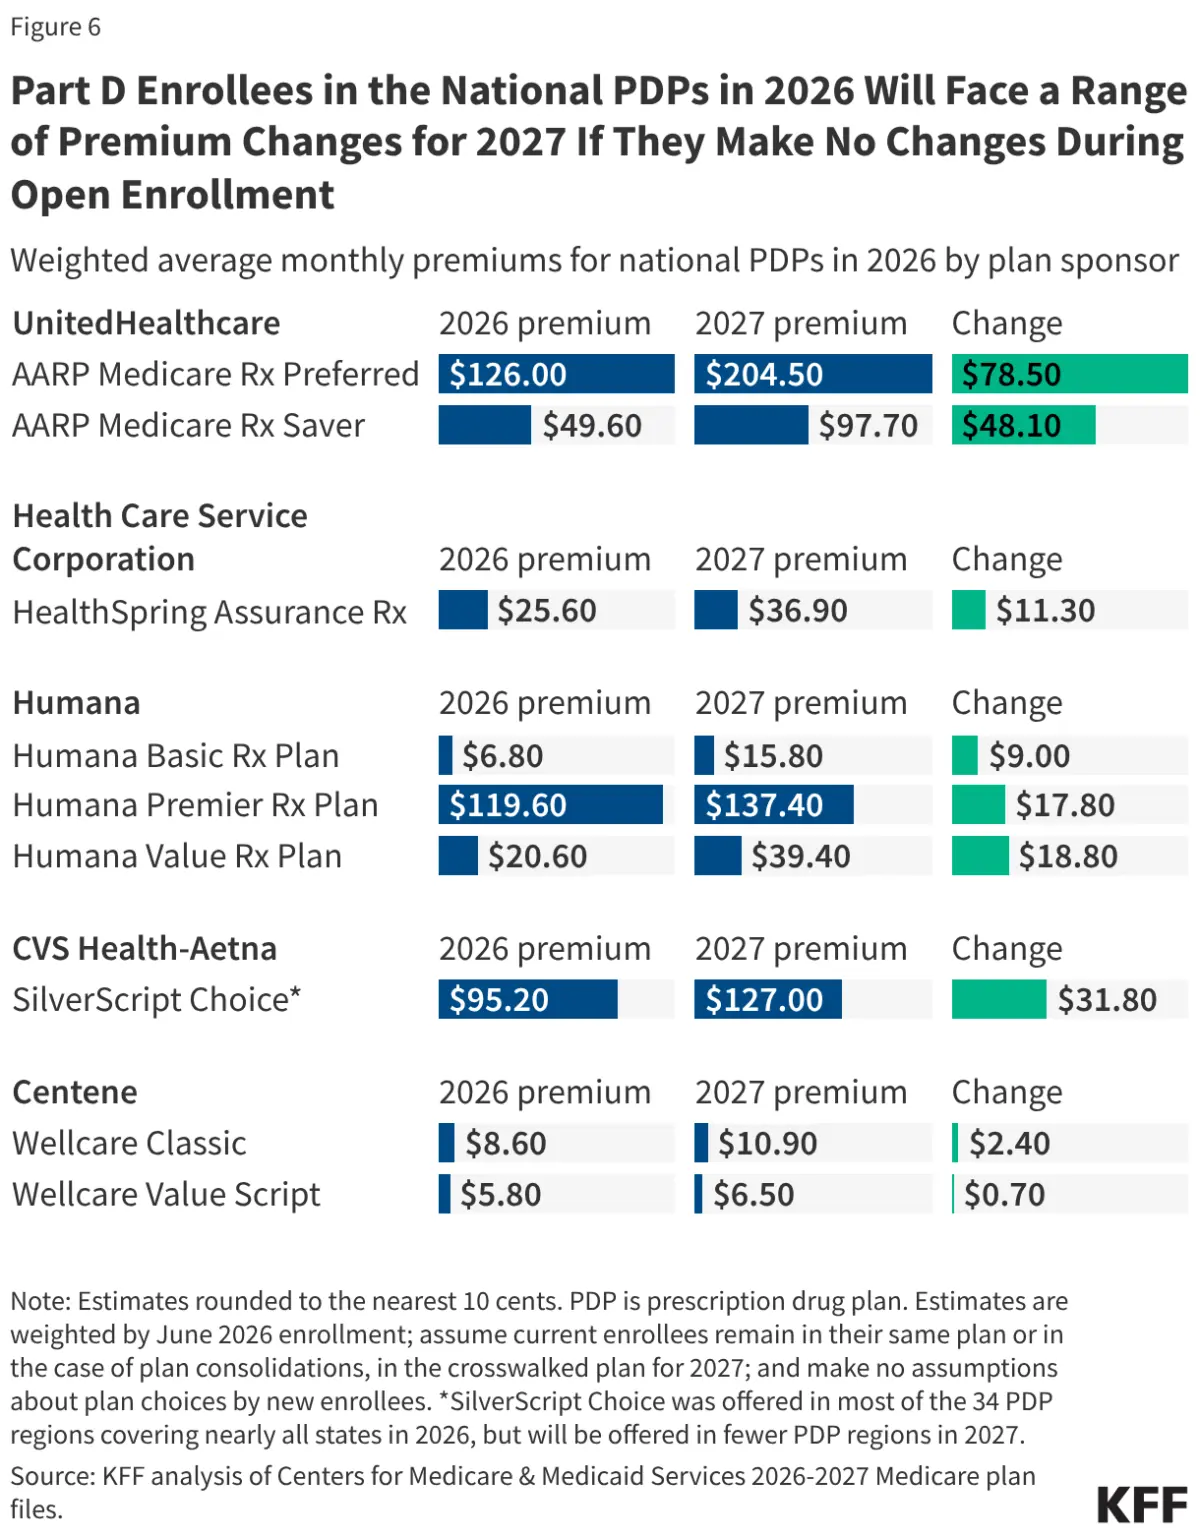
- Regional Variability: Premiums for the 8 national PDPs vary wildly. For instance, the AARP Medicare Rx Preferred plan averages $204 per month, yet that price can swing by over $100 depending on the region. This geography-based pricing makes it nearly impossible for a beneficiary to rely on national averages when making personal financial decisions.
Deductibles and Cost-Sharing: The New Norm
Beyond the monthly premium, the "out-of-pocket" threshold is rising. In 2027, almost every stand-alone PDP enrollee (99.8%) will be in a plan that requires a deductible for drug coverage. Even within Medicare Advantage plans, 85% of enrollees are now subject to a deductible.
The shift toward coinsurance is perhaps the most significant change in how beneficiaries pay for their medicine. Unlike a fixed copayment (e.g., $10 for a pill), coinsurance requires the patient to pay a percentage of the drug’s cost. Because drug prices can fluctuate, this exposes seniors to unpredictable costs.
In 2027, the standard formulary design—consisting of preferred generics, generics, preferred brands, non-preferred drugs, and specialty drugs—increasingly forces patients into coinsurance tiers for everything except basic generics. For non-preferred drugs, patients should expect to pay between 30% and 50% of the cost. When these percentages are applied to high-cost specialty medications, the financial burden can become unsustainable for those on fixed incomes.
Official Responses and Regulatory Context
The Centers for Medicare & Medicaid Services (CMS) maintains that the market remains competitive. However, the decision to discontinue the Part D Premium Stabilization Demonstration has left policy analysts and patient advocacy groups concerned.
Industry analysts suggest that the disappearance of zero-premium plans is a direct consequence of the loss of federal support. When the government stopped capping premium hikes at $50, the result was immediate: 2.4 million enrollees now face an increase of more than $50 per month. CMS officials note that their role is to facilitate a marketplace, and they emphasize that the "annual notice of change" documents mailed to every beneficiary are the primary tool for mitigating these costs. They urge, and in many cases demand, that beneficiaries treat open enrollment as a mandatory annual audit of their personal finances rather than a passive renewal process.
Implications: Why "Doing Nothing" Is Risky
The data paints a clear picture: for 2027, inertia is the most expensive strategy a Medicare beneficiary can adopt.
- The End of Passive Enrollment: In previous years, staying in a current plan might have resulted in a modest, manageable price increase. In 2027, the cost of staying in an old plan could mean an increase of hundreds of dollars annually.
- The "Plan Shopping" Necessity: Because premiums for the same national plan can vary by over $100 across different regions, beneficiaries must use the Medicare Plan Finder tool to input their specific list of medications. A plan that is affordable in one zip code may be prohibitively expensive in another.
- Financial Planning for Coinsurance: Because most plans have shifted toward coinsurance for brand-name and specialty drugs, beneficiaries must plan for "variable" costs. A fixed monthly budget is no longer sufficient if a surprise spike in a drug’s retail price results in a higher coinsurance payment at the pharmacy counter.
- The LIS Safety Net: For those with limited income and assets, the Low-Income Subsidy (LIS) remains a critical, life-saving program. However, as premiums rise across the board, the importance of qualifying for and maintaining this status is more vital than ever.
As we move through this open enrollment season, the 2027 Part D landscape serves as a stark reminder of the complexities of the U.S. healthcare system. For the millions of Americans relying on these plans, the message is singular: verify, compare, and act. The financial penalty for complacency in 2027 is simply too high to ignore.
About the Author