Introduction: The Evolving Landscape of Public Health Coverage
As of mid-2026, the American public health insurance landscape—specifically the Medicaid and Children’s Health Insurance Program (CHIP)—is navigating a period of significant structural and legislative transition. Following the conclusion of the pandemic-era "continuous enrollment" period, the federal government and individual states have shifted their focus toward long-term stabilization, even as new legislative mandates loom on the horizon.
This report synthesizes the most recent enrollment data provided by the Centers for Medicare & Medicaid Services (CMS) and evaluates the implications of the 2025 reconciliation law. With new work and reporting requirements set to take effect in early 2027, the coming months represent a critical window for understanding the baseline from which future changes will be measured.
Main Facts: The Current State of Medicaid and CHIP
The current enrollment picture is characterized by complex, multi-layered trends that distinguish between Medicaid-only and CHIP-only populations, as well as the unique needs of children versus adults.
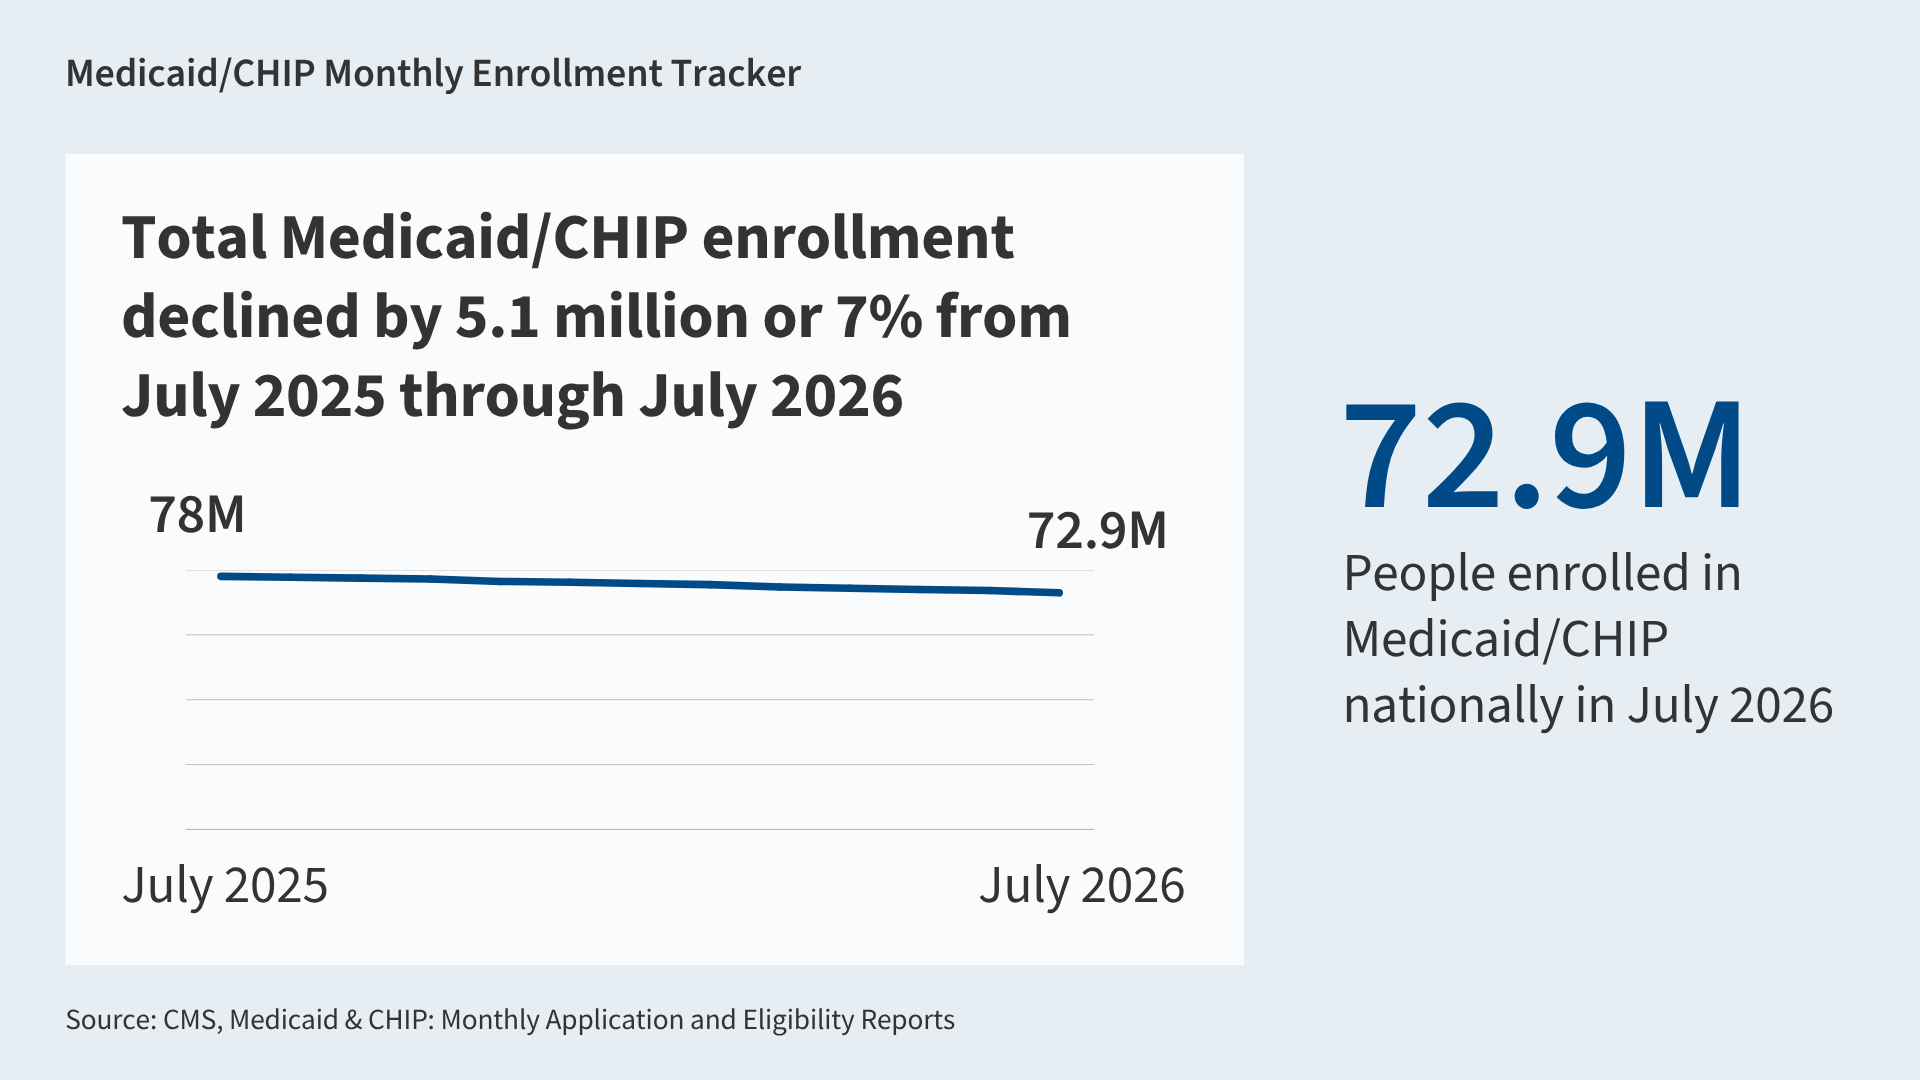
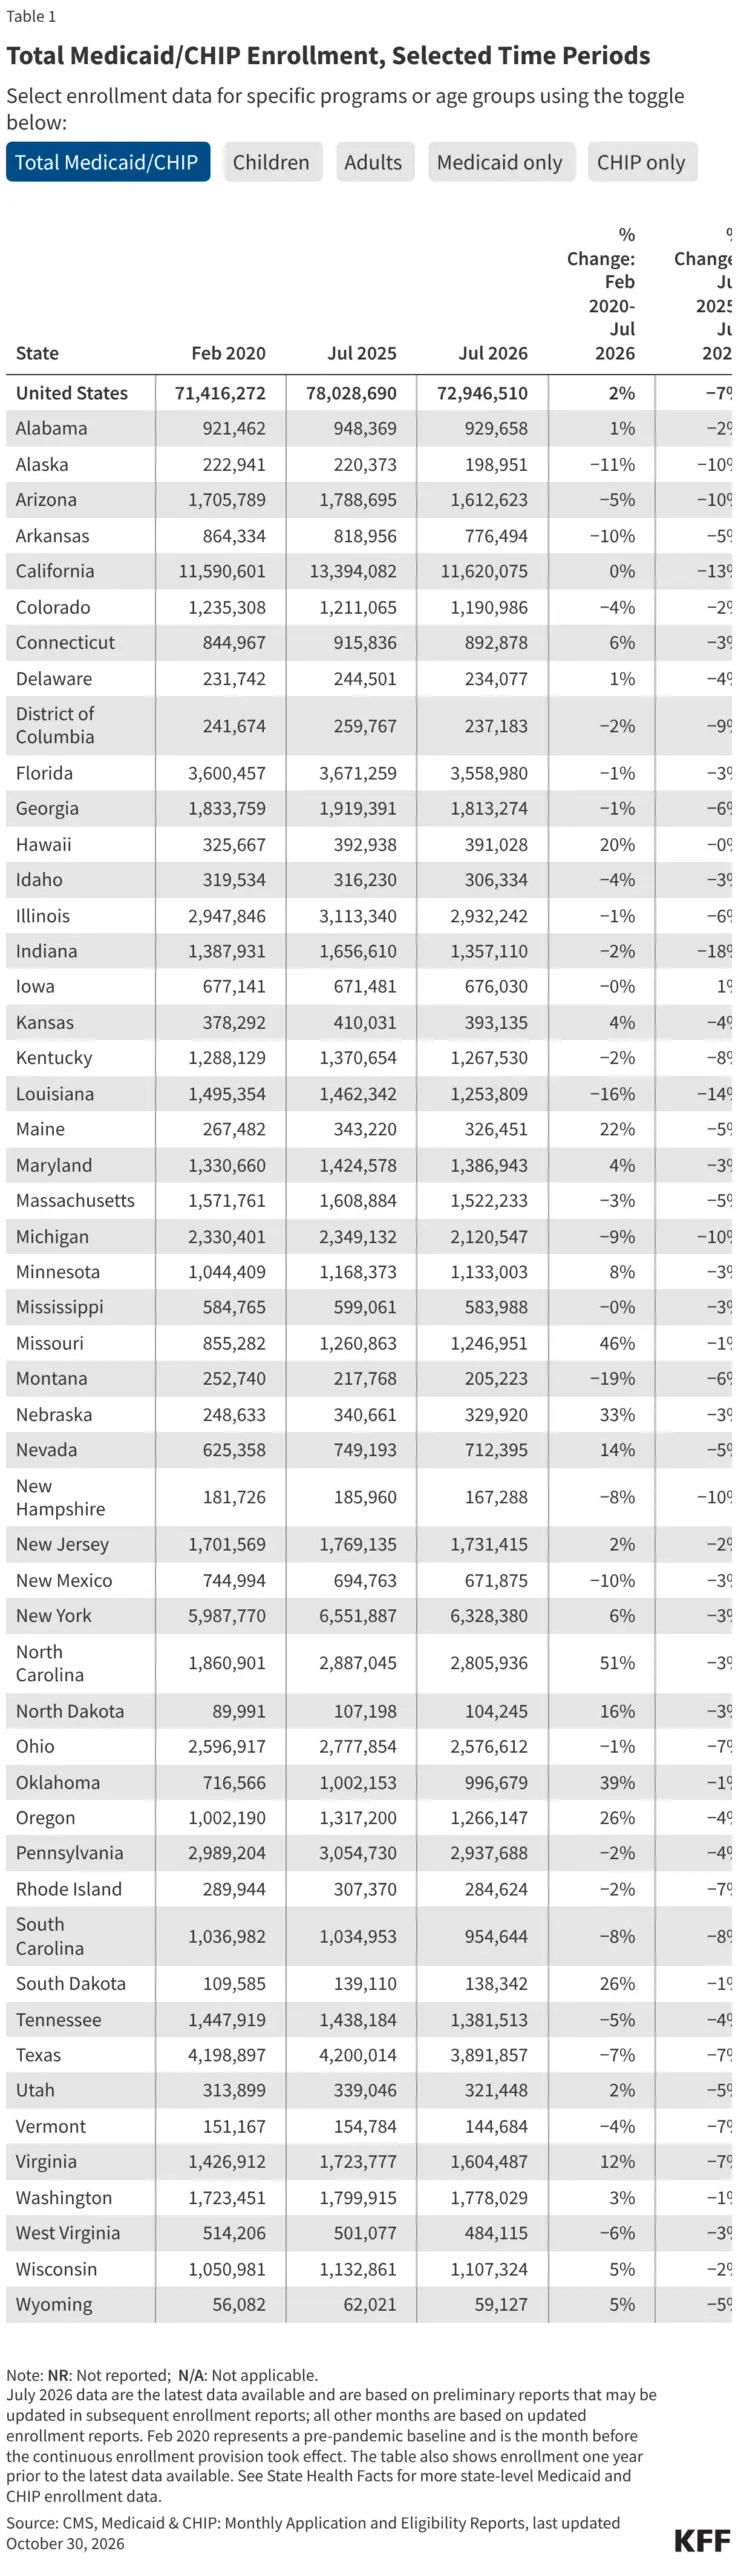
- Data Scope: The enrollment data tracked here stems from the CMS Performance Indicator Project. It is essential to note that these figures capture "full-benefit" enrollees. Consequently, individuals receiving only limited-benefit coverage—such as those enrolled solely for family planning services—are excluded. This means that while these data points are the gold standard for tracking enrollment trends, they represent a conservative estimate of the total population currently relying on Medicaid and CHIP.
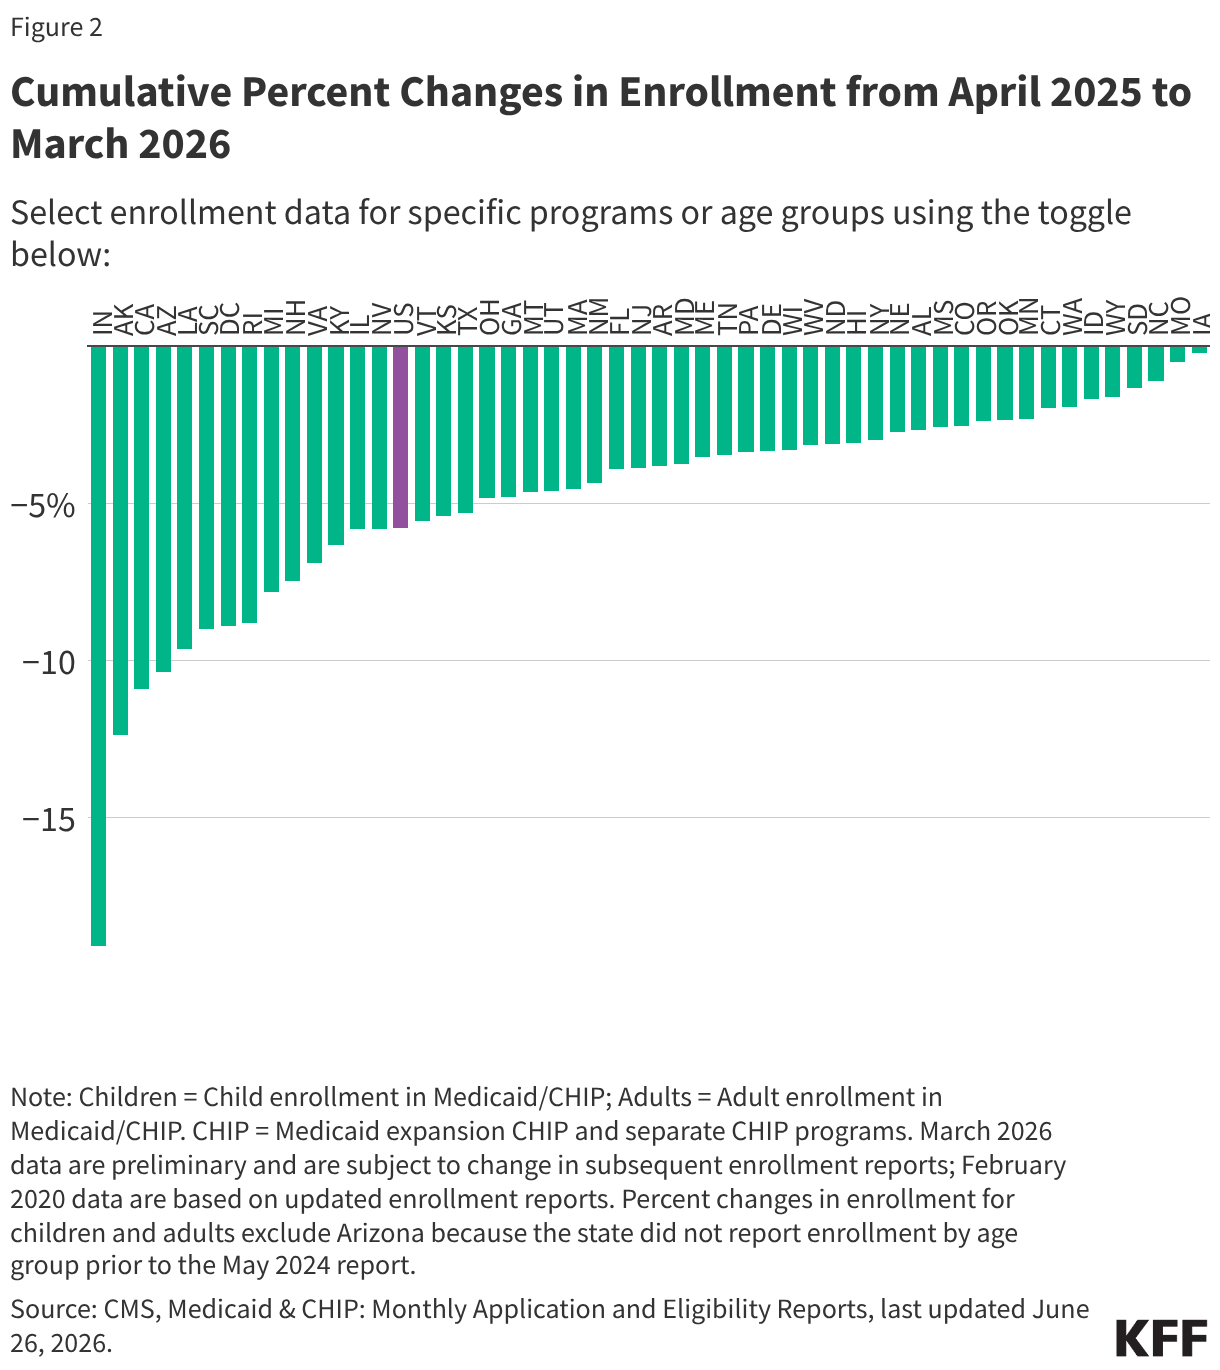
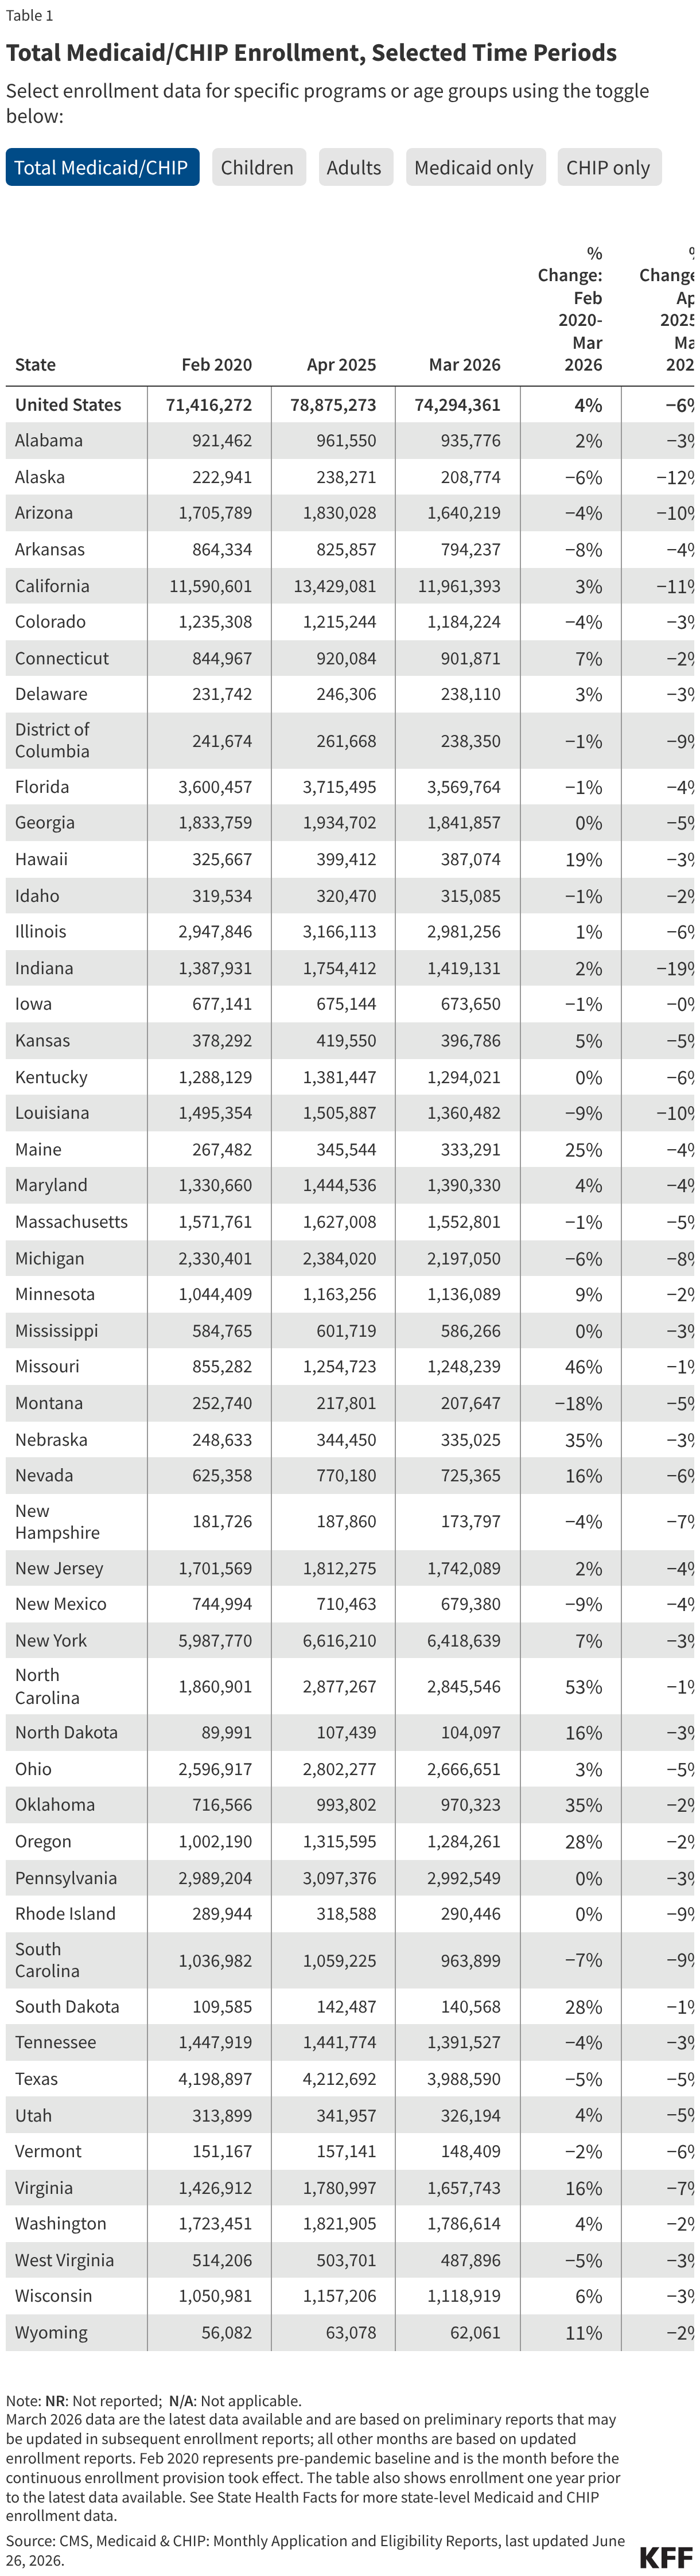
- The 2026 Snapshot: As of July 2026, the data indicates a plateauing effect in some sectors, contrasted by continued volatility in others. Because these data points are preliminary, they are subject to refinement as states submit final monthly reports, but the current trajectory suggests a system that has largely absorbed the initial shocks of the post-unwinding period.
- Exclusionary Factors: It is important to acknowledge that these reports cannot be used to monitor enrollment shifts by specific eligibility pathways, such as the Medicaid expansion group. For those interested in the granular effects of expansion policies, specialized tracking resources remain the primary source of truth.
Chronology: From Pandemic Baseline to 2026 Stability
The trajectory of Medicaid enrollment over the last six years has been unprecedented in American administrative history.
The Pre-Pandemic Baseline (February 2020)
Before the onset of COVID-19, Medicaid and CHIP enrollment served as a stable safety net. February 2020 serves as our critical baseline—the last month before the "continuous enrollment" provision took effect. This provision prohibited states from disenrolling individuals, leading to an historic surge in enrollment that acted as a buffer during the economic instability of the pandemic.
The Unwinding Period (2023–2024)
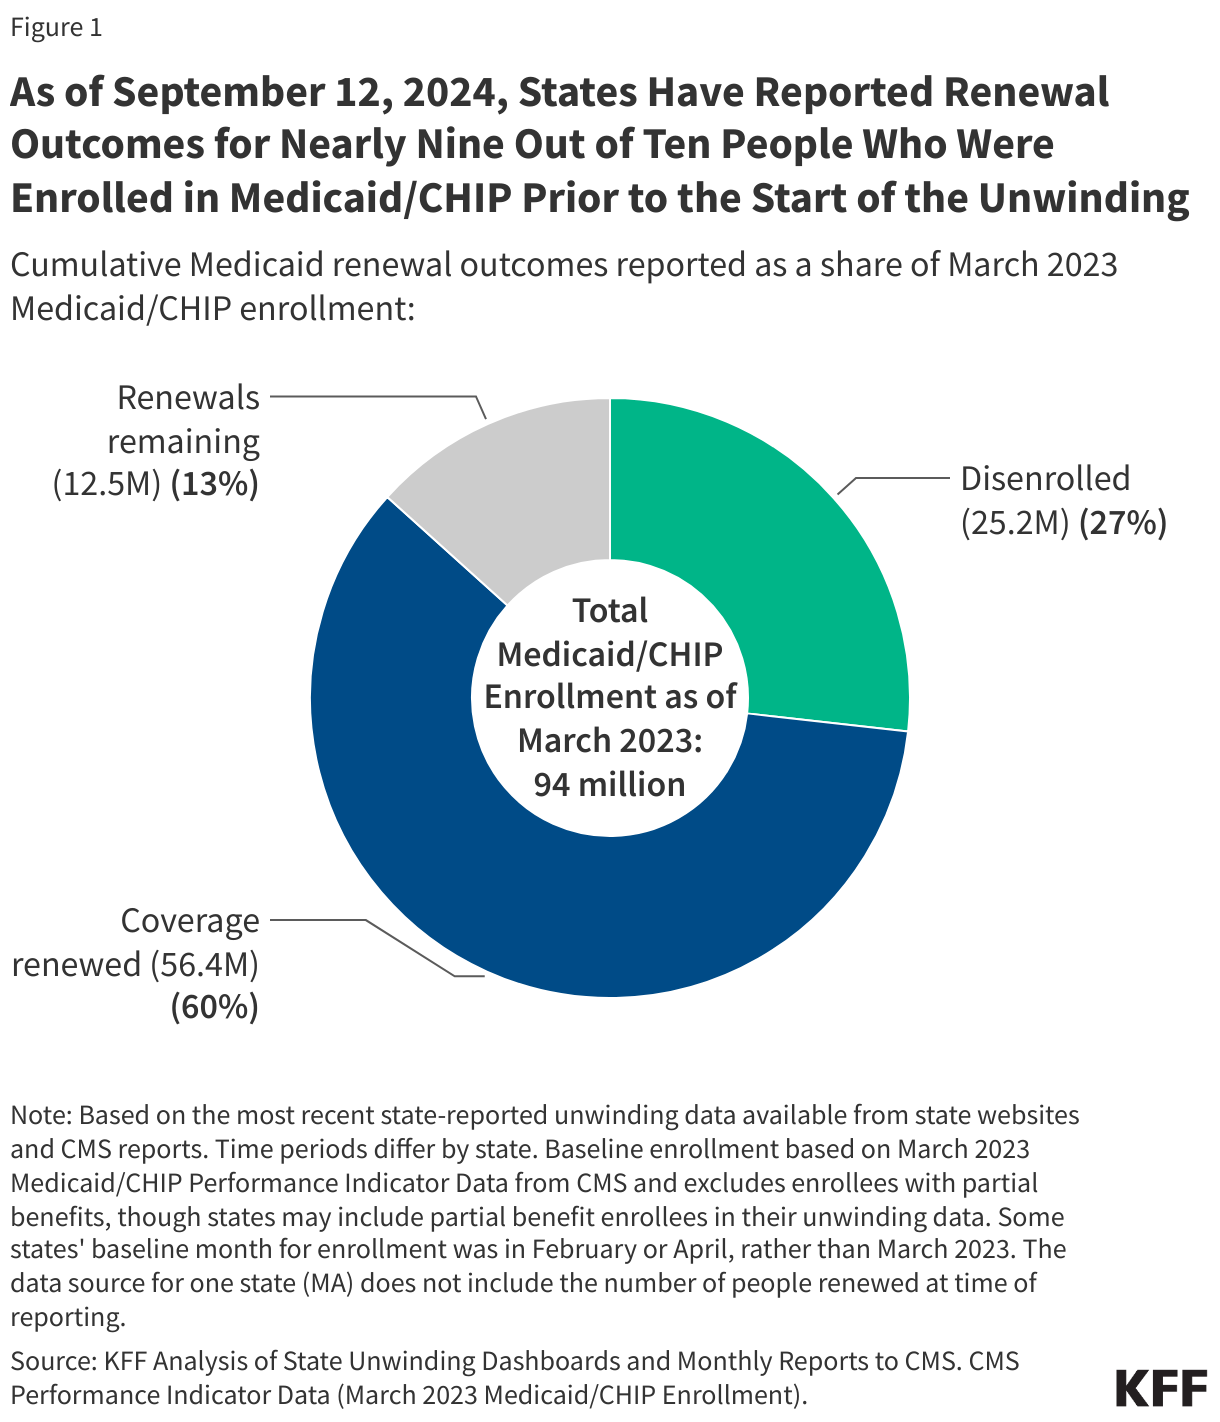
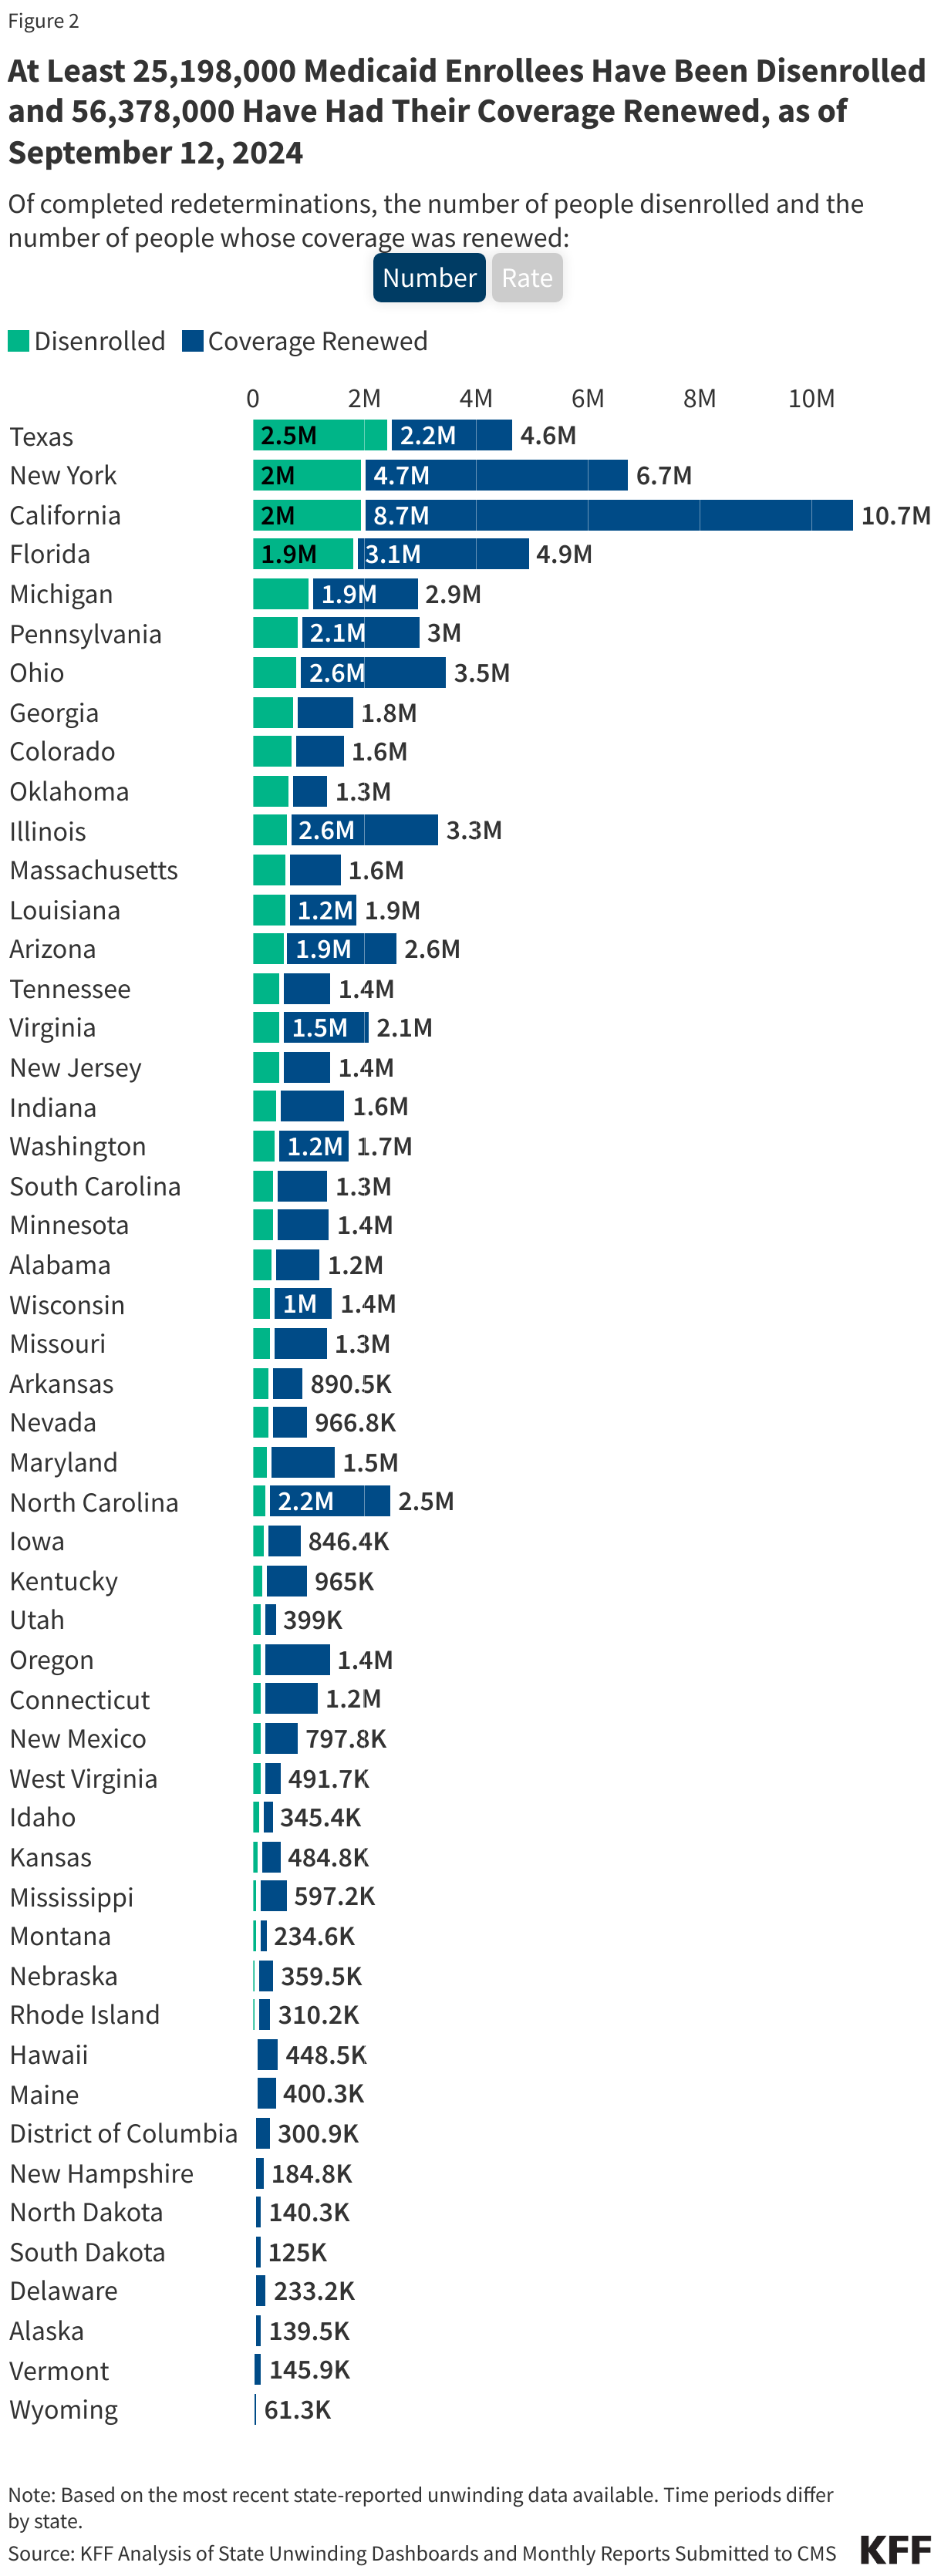
Following the expiration of the continuous enrollment provision, the "unwinding" phase began. States were tasked with a massive administrative undertaking: redetermining the eligibility of millions of enrollees. This period, which spanned most of 2023 and the first half of 2024, resulted in significant disenrollments. By September 2024, data confirmed that nearly nine out of ten individuals who were enrolled prior to the unwinding had their status processed.
The 2025 Reconciliation Law and the Path to 2027
The 2025 reconciliation law introduced a new chapter for the program. The law mandates that adults in the expansion group, as well as those in specific 1115 waiver programs, must adhere to new work and reporting requirements starting January 2027. This legislative shift is expected to decrease enrollment over the next decade relative to the trajectory established under previous law.
Supporting Data: Analysis of Renewal Outcomes
The data collected during the unwinding process provides a stark look at the administrative hurdles faced by enrollees.
The "Procedural" Disenrollment Problem
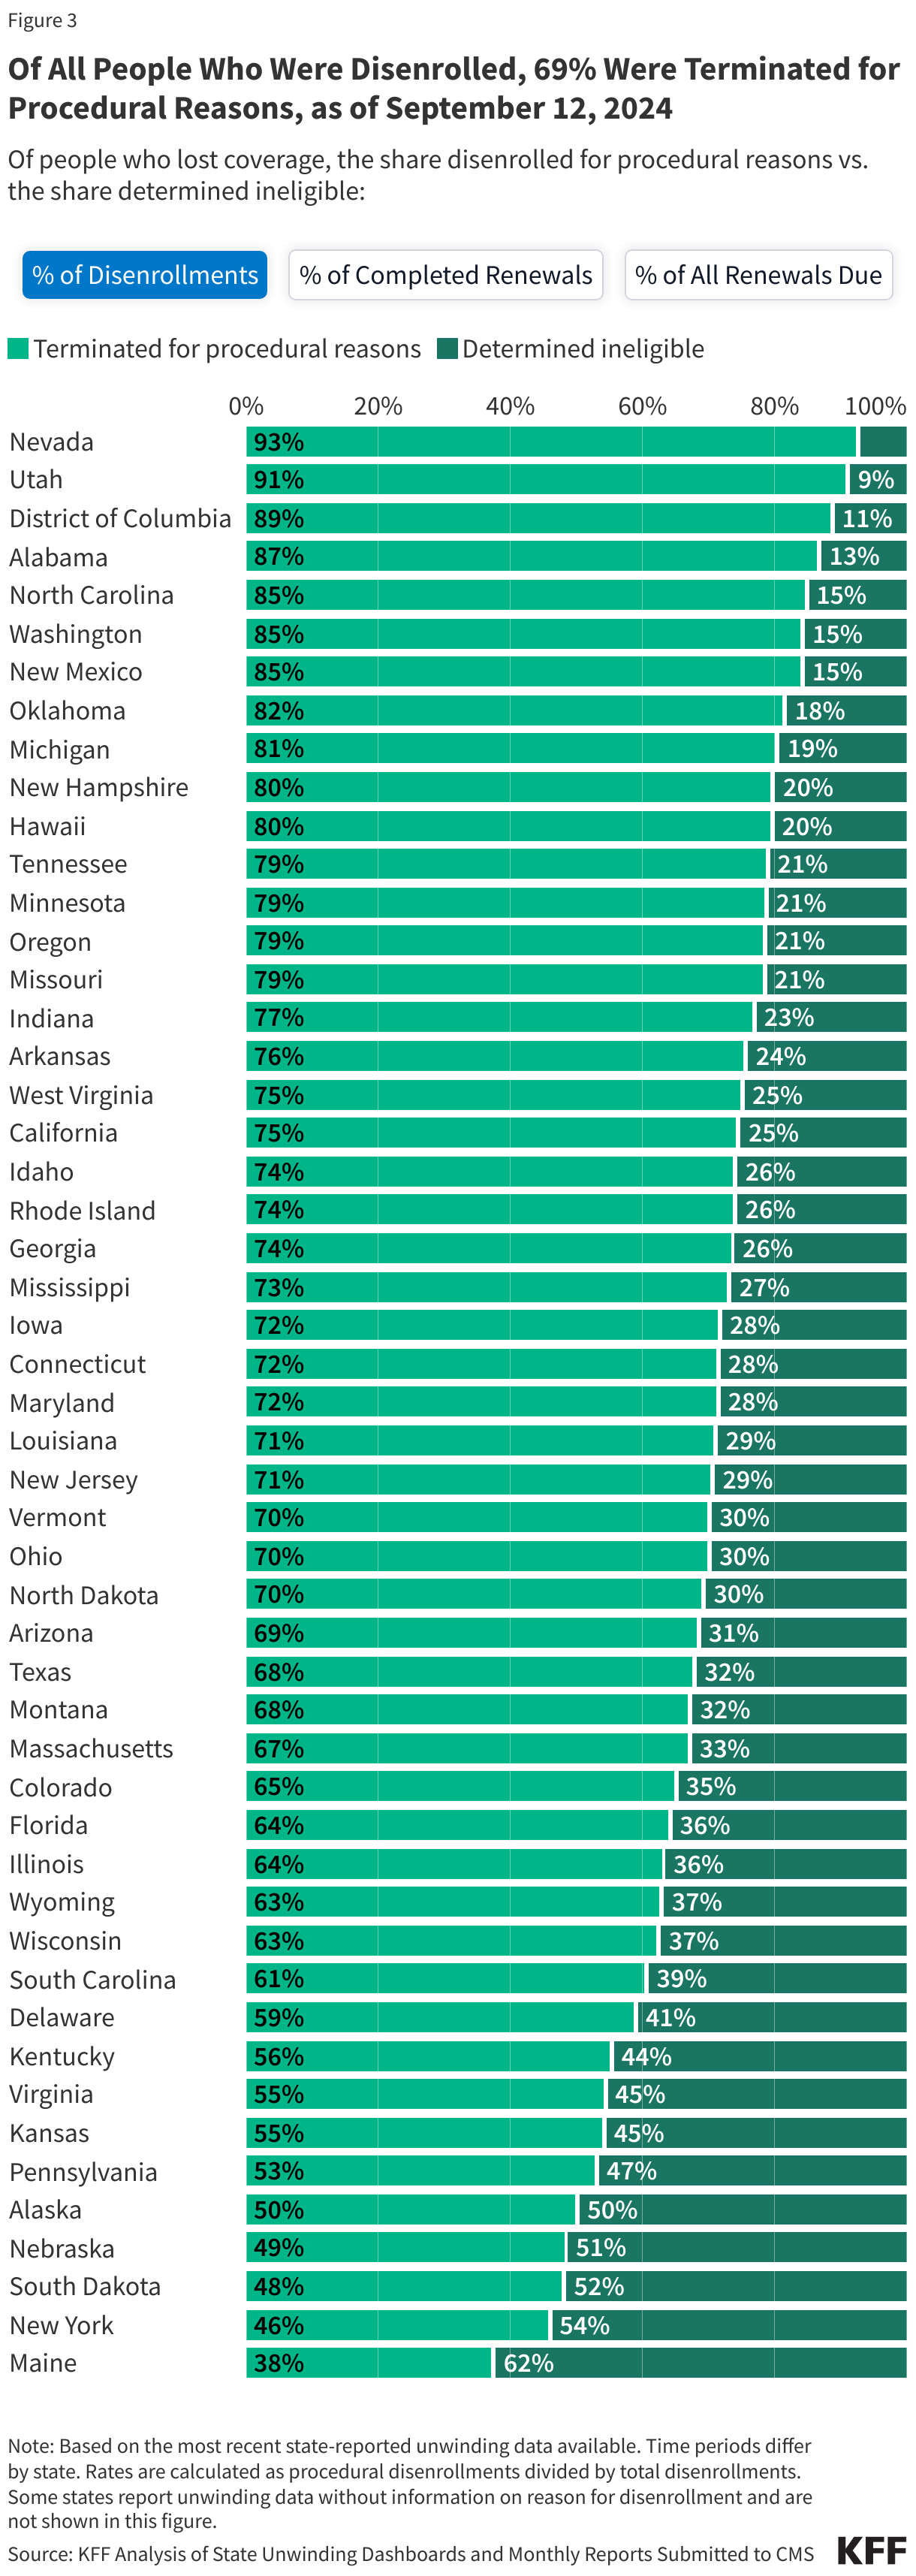
Perhaps the most alarming statistic to emerge from the unwinding period was the prevalence of "procedural disenrollments." As of September 12, 2024, approximately 69% of those who lost coverage were terminated for procedural reasons—meaning they were disenrolled not because they were found ineligible, but because they failed to navigate the paperwork requirements successfully.
Renewal Efficiency: The Ex Parte Process
Conversely, the data highlights the importance of the ex parte renewal process—a system where states use existing data to automatically renew coverage. As of September 2024, roughly 61% of individuals who retained their Medicaid coverage did so through these automated processes. This demonstrates that when states have the data infrastructure to conduct seamless renewals, the burden on the enrollee is significantly reduced.
Geographic Variation
There exists a massive disparity in how different states handled the redetermination process. Disenrollment rates for completed redeterminations varied wildly, from as high as 57% in some jurisdictions to as low as 12% in states like North Carolina. These variations often reflect differences in state-level administrative capacity, outreach efforts, and the stringency of documentation requirements.
Official Responses and Policy Implementation
Federal authorities at CMS have continuously updated their guidance to encourage states to adopt "mitigation strategies" to prevent eligible individuals from losing coverage. These strategies have included:
- Extended Outreach: Using community partners to reach vulnerable populations.
- System Modifications: Updating eligibility systems to better capture ex parte data.
- Delayed Renewals: In cases of system failures, some states have been granted flexibility to adjust their renewal timelines.
However, the transition into the 2027 work requirement era is expected to challenge these administrative systems further. The federal government has indicated that it will be monitoring state compliance with the 2025 law closely, particularly regarding how states communicate these new requirements to the expansion population.
Implications: The Future of Medicaid
The implications of these trends are far-reaching for healthcare providers, policymakers, and, most importantly, the millions of Americans who rely on these programs.
Impact on Healthcare Providers
For hospitals and clinics, the fluctuation in Medicaid enrollment—particularly the high rate of procedural disenrollments—creates financial uncertainty. Uncompensated care costs are often tied to the number of uninsured or underinsured patients entering emergency rooms. A reduction in Medicaid coverage, even for those who remain technically eligible, places an increased burden on the healthcare safety net.
The 2027 Horizon
As we look toward January 2027, the primary concern for advocates is the "churn" that new work requirements might induce. If the experience of the unwinding period is any indication, administrative barriers—even if unintended—can lead to large-scale coverage loss. Ensuring that the transition to the new requirements is managed with transparency and accessibility will be the defining challenge for state Medicaid directors in the coming year.
Data Transparency and Monitoring
The reliance on tools like the KFF Medicaid Enrollment Tracker and CMS monthly reports has never been more vital. These tools provide the transparency necessary to hold systems accountable. Moving forward, the focus will likely shift from the "unwinding" data to the "work requirement implementation" data, as the research community prepares to track the potential long-term contraction of the program.
Conclusion
The data provided by CMS and analyzed in this report paints a picture of a system in flux. While the massive redetermination event of the unwinding period has concluded, the structural changes brought about by the 2025 reconciliation law suggest that Medicaid enrollment will remain a focal point of legislative and public health debate for the next decade.
For stakeholders, the key takeaway is clear: administrative processes are as important as eligibility criteria. Whether it is through the success of ex parte renewals or the challenges of procedural disenrollment, the way in which policy is executed at the state level determines who retains access to care and who falls through the cracks. As we approach 2027, the intersection of data-driven policy and administrative implementation will determine the stability of the American safety net for years to come.
For questions regarding this analysis, please reach out to the relevant policy research divisions or consult the official CMS monthly enrollment reports updated periodically.
About the Author