Introduction: A Decade of Policy Divergence
More than a decade after the Affordable Care Act (ACA) was signed into law, the landscape of American public health coverage remains defined by a stark, state-by-state divide. At the heart of this divide is the Medicaid expansion—a transformative policy tool designed to extend health insurance to nearly all adults with incomes up to 138% of the Federal Poverty Level (FPL). As of 2025, that threshold translates to an annual income of $21,597 for an individual.
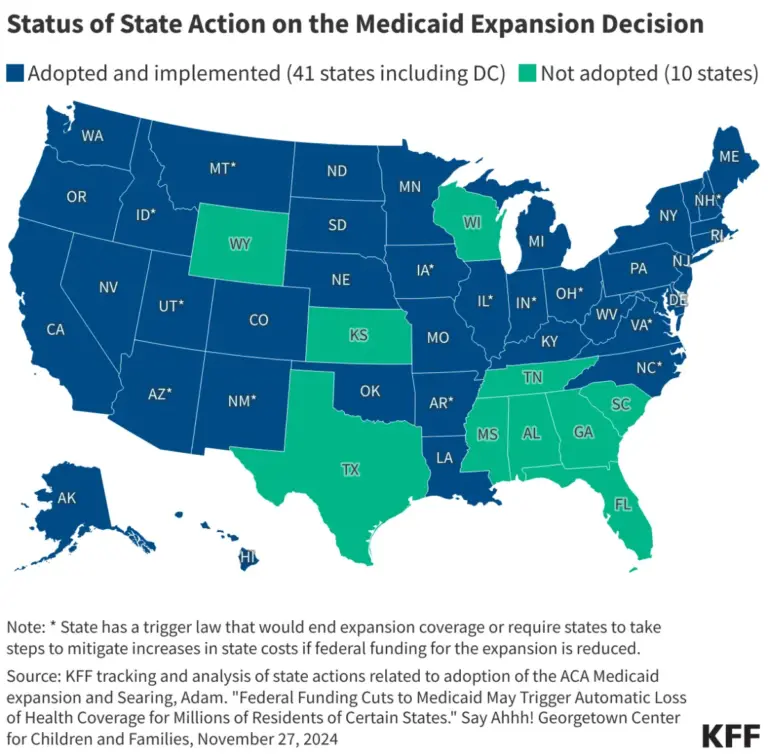
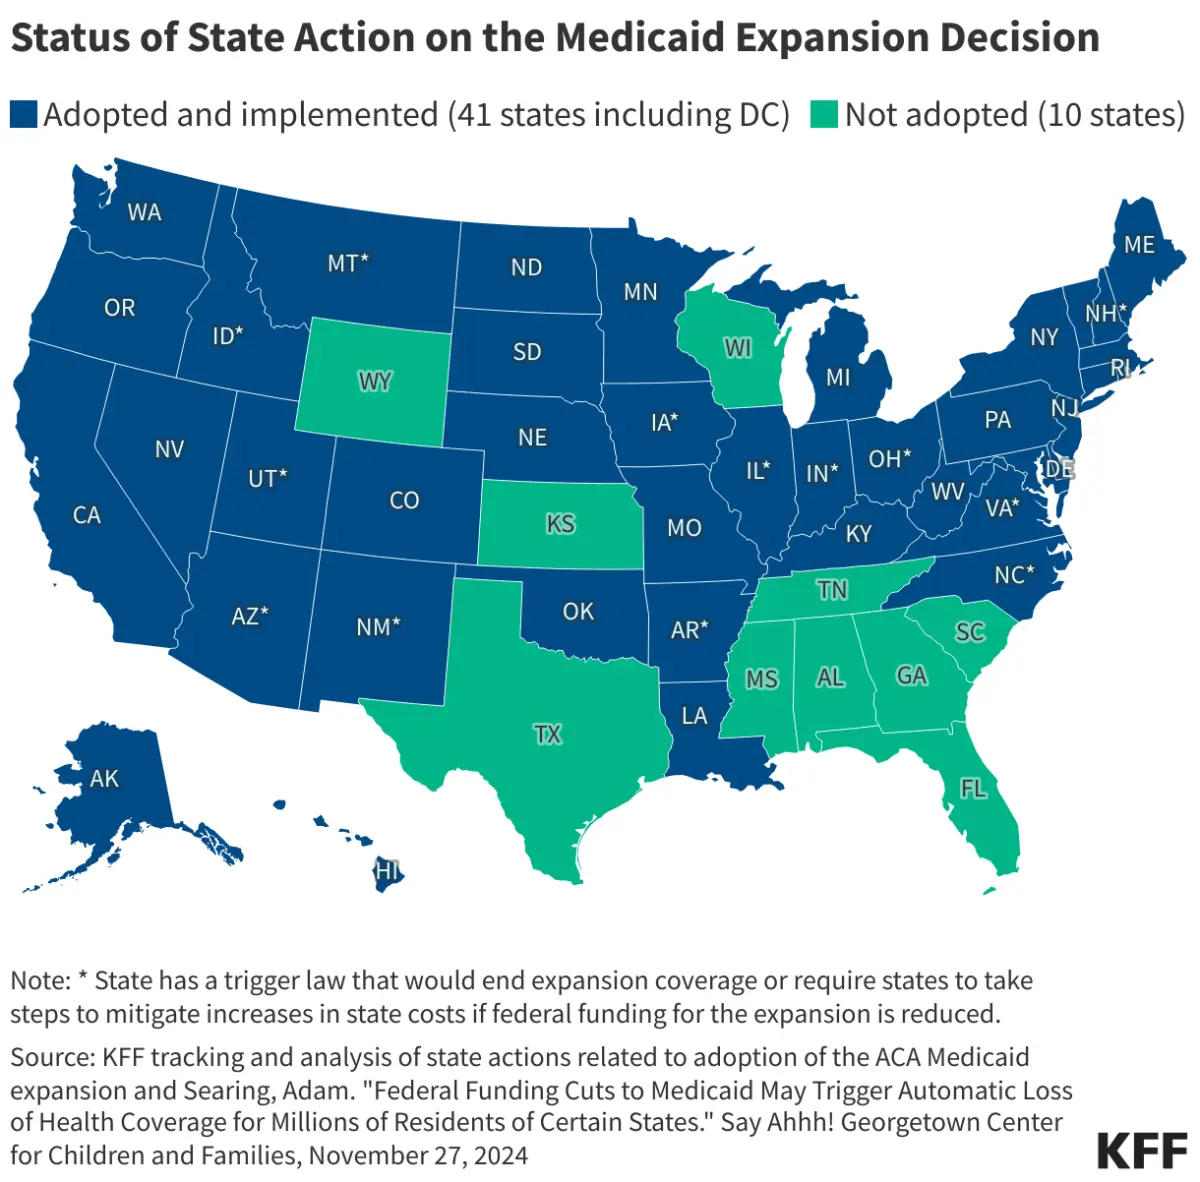
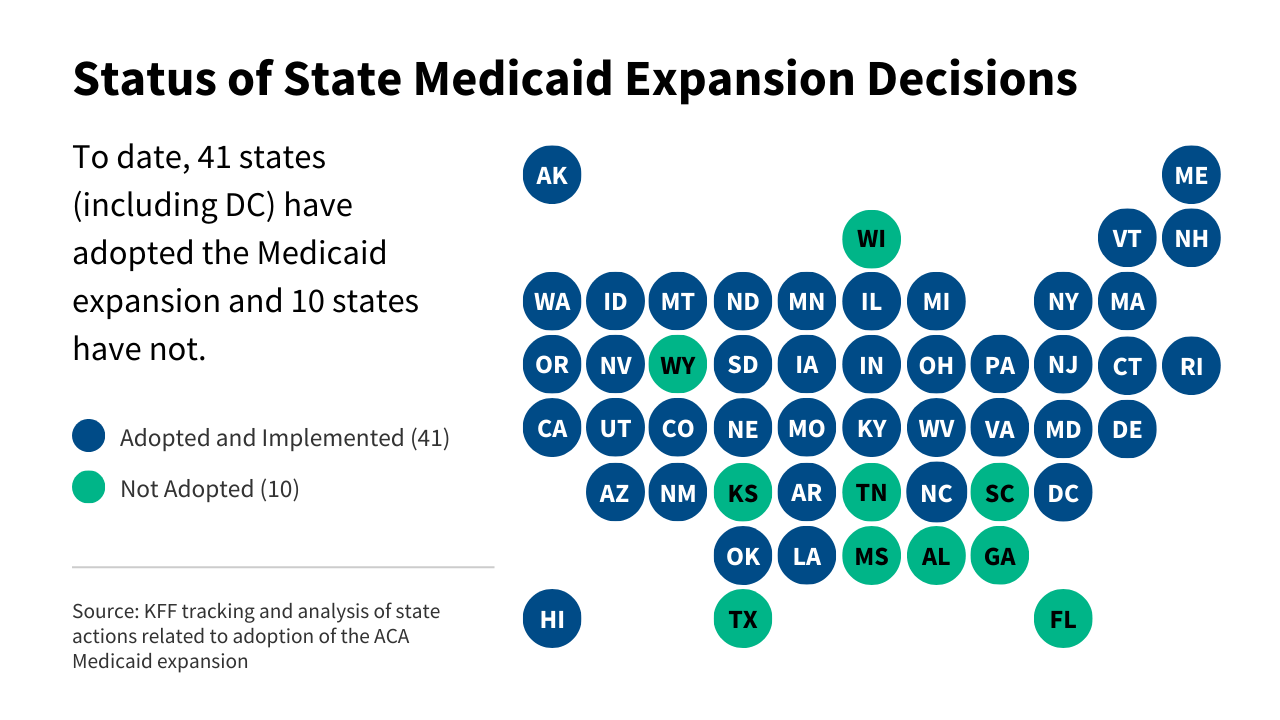
While the federal government offers an enhanced Federal Medical Assistance Percentage (FMAP) to incentivize states to broaden their eligibility criteria, the decision to participate remains a sovereign state choice. Today, the nation is split: 41 jurisdictions, including the District of Columbia, have embraced the expansion, while 10 states continue to resist, leaving a significant "coverage gap" for thousands of low-income citizens. This report examines the current status, historical trajectory, and complex political implications of one of the most consequential health policy debates in modern American history.
Main Facts: Defining the Expansion
The Medicaid expansion represents the single largest expansion of health coverage in the U.S. since the inception of Medicare and Medicaid in 1965. By shifting the eligibility focus from categorical requirements (such as being a parent, disabled, or elderly) to a simple income-based standard, the ACA aimed to eliminate the "coverage gap"—a situation where individuals earn too much to qualify for traditional Medicaid but too little to afford private insurance premiums or marketplace plans.
The Financial Incentive Structure
The federal government sweetened the deal for states by covering 90% or more of the costs for the expansion population. This enhanced FMAP was designed to ensure that state budgets would not be disproportionately burdened by the influx of newly insured residents. Despite this, opponents have frequently cited long-term fiscal sustainability and ideological concerns regarding government-led healthcare as the primary drivers for opting out.
The Current Map
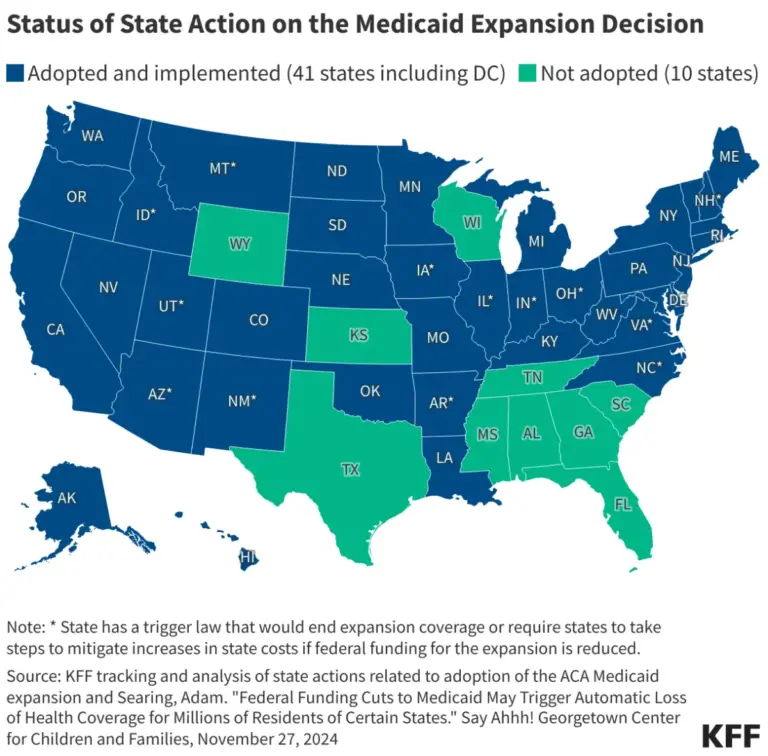
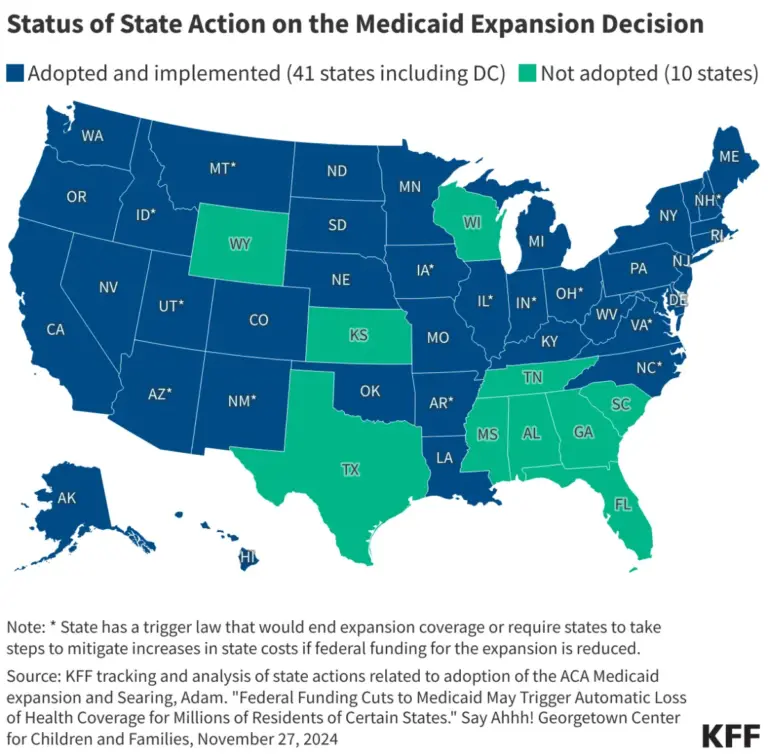
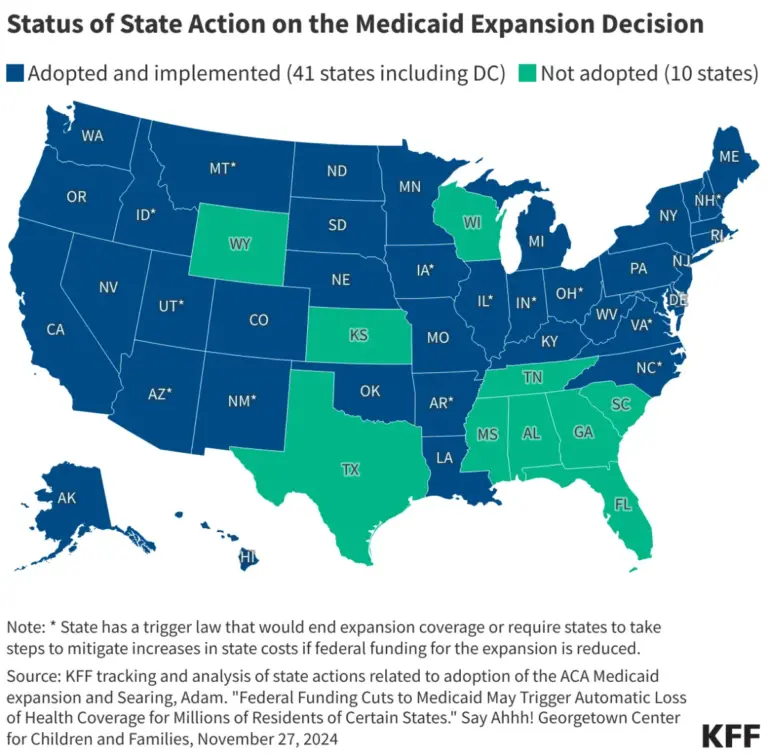
According to the latest tracking data from KFF, 41 states have moved to adopt the expansion. The remaining 10 states remain holdouts, though the pressure to expand continues to fluctuate based on legislative cycles, gubernatorial priorities, and grassroots advocacy.
Chronology: The Path to the Present
The history of Medicaid expansion is not a linear march toward universal adoption; it is a series of fits, starts, and landmark legal challenges.
2010–2012: The Foundation and the First Hurdle
The ACA was enacted in 2010, and Medicaid expansion was initially written as a mandatory requirement for all states. However, the 2012 Supreme Court ruling in National Federation of Independent Business v. Sebelius fundamentally changed the trajectory. The Court ruled that the federal government could not force states to expand Medicaid under threat of losing all existing Medicaid funding. This effectively made the expansion optional, turning the program into a "patchwork" system overnight.
2013–2018: The Initial Wave and The Rise of "Red State" Expansion
Following the Court’s ruling, a group of early-adopter states moved quickly to expand coverage. By the mid-2010s, a new trend emerged: Republican-led states began to find ways to expand, often using "Section 1115 waivers" to implement conservative-leaning policies—such as work requirements or premiums—as a condition of expansion. This period saw states like Indiana and Arkansas join the fold, signaling that the debate was no longer strictly partisan.
2019–2024: Ballot Initiatives and Renewed Pressure
As legislative stalemates persisted in many states, advocates turned to the ballot box. Voter-led initiatives in states like Idaho, Utah, and Nebraska forced the issue, demonstrating significant public support for expansion that often bypassed traditional legislative resistance. By 2024, the conversation shifted toward long-term stability and the potential risks posed by "trigger laws"—statutes in some states that would automatically terminate the Medicaid expansion if federal funding levels were ever reduced.
Supporting Data: The Impact of Coverage
The data suggests that Medicaid expansion is not merely a bureaucratic change but a transformative force in economic and physical health.
Health Outcomes and Financial Security
Studies consistently show that states that expanded Medicaid see improved health outcomes, including better management of chronic conditions like diabetes and hypertension, higher rates of cancer screenings, and reduced maternal mortality rates. Beyond clinical outcomes, the economic stability of households increases; the expansion reduces the incidence of medical debt and the likelihood of personal bankruptcy.
The "Trigger" Law Complication
A critical, often overlooked aspect of current state activity involves "trigger laws." These are legislative mechanisms designed to protect state budgets by automatically scaling back or eliminating the expansion if the federal government reduces its share of funding.
- South Dakota and West Virginia: These states have engaged in ongoing discussions regarding the implementation of such triggers.
- Virginia: A notable legislative attempt to refine the state’s trigger law was debated recently, highlighting a growing nervousness among state lawmakers regarding their long-term reliance on federal subsidies.
- Illinois and North Carolina: Both states have seen proposals aimed at moderating or removing existing trigger laws, suggesting a desire for more predictable, long-term health policy.
Official Responses and Political Maneuvering
The debate surrounding Medicaid expansion is rarely settled. It remains a fixture in statehouses across the remaining 10 non-expansion states.
Executive vs. Legislative Action
In many states, the governor acts as the primary engine for or against expansion. Recent years have seen governors propose expansion in their annual budgets, only to face resistance from conservative legislative chambers. Conversely, in states where the executive is opposed, legislative committees have occasionally attempted to introduce bills that would trigger a voter referendum or a special study commission.
The Role of Section 1115 Waivers
The federal government has allowed states to use Section 1115 waivers to experiment with their Medicaid programs. While these waivers were initially used to allow for "non-traditional" expansions, the current federal administration has signaled a pivot toward emphasizing coverage continuity and access, frequently rejecting proposals that include strict work requirements that could jeopardize the coverage of the most vulnerable.
Implications: The Future of the "Coverage Gap"
The failure to adopt Medicaid expansion in 10 states leaves millions of individuals in a state of limbo. These individuals—often the "working poor"—are frequently employed in service, agricultural, or gig-economy jobs that do not provide employer-sponsored health insurance.
The Economic Argument
The economic implications for non-expansion states are significant. Hospitals in these states, particularly in rural areas, face higher rates of uncompensated care. When patients lack insurance, they often delay care until it becomes an emergency, forcing hospitals to absorb the costs. This financial strain has led to the closure of several rural hospitals, further diminishing the quality of life in these communities.
The Moral and Political Imperative
As the 2025 landscape settles, the pressure for expansion is likely to increase. Advocates argue that the "patchwork" system is inherently unequal, creating a society where access to life-saving care is determined by a zip code. On the other side, fiscal conservatives maintain that the expansion is an unsustainable burden on taxpayers and that private market alternatives are more efficient.
Looking Ahead
The path forward for the 10 holdout states will likely be defined by a mix of grassroots pressure, hospital advocacy, and the evolving fiscal realities of the federal government. If Congress were to ever revisit the FMAP structure, states with trigger laws would find themselves in the most precarious position.
Ultimately, the Medicaid expansion debate has evolved from a simple question of "yes or no" into a complex, ongoing negotiation over the state’s role in public health. As data continues to show the tangible benefits of expansion, the political cost of remaining a "non-expansion" state is likely to grow, potentially forcing a tipping point in the years to come.
Conclusion
The ACA’s Medicaid expansion remains one of the most significant policy experiments in U.S. history. While 41 states have secured the benefits of a healthier, more financially stable population, the 10 states that remain outside the program continue to face the challenges of uncompensated care, higher mortality rates, and persistent health inequities. As the debate continues, the focus will likely remain on the tension between ideological opposition and the practical, data-backed benefits of broad, state-supported health coverage. Whether through ballot initiatives or shifting legislative tides, the map of the United States is far from fixed, and the next decade of Medicaid policy promises to be as dynamic as the last.
For more information on state-specific legislative activity, including tracking of bill status and executive actions, readers are encouraged to visit the KFF State Health Facts portal or consult the latest policy briefs from the Georgetown Center for Children and Families.
About the Author