More than a decade after the Affordable Care Act (ACA) was signed into law, the landscape of American public health coverage remains defined by a stark, state-by-state divide. At the heart of this divide is the Medicaid expansion—a policy designed to extend health insurance to nearly all adults with incomes up to 138% of the Federal Poverty Level (FPL). As of 2025, that threshold translates to an annual income of $21,597 for an individual. While the federal government provides an enhanced federal matching rate (FMAP) to incentivize states to participate, the decision to opt in remains a sovereign state-level choice, leading to a patchwork of coverage that continues to shift as political winds change.
The Current State of Play: A Nation Divided
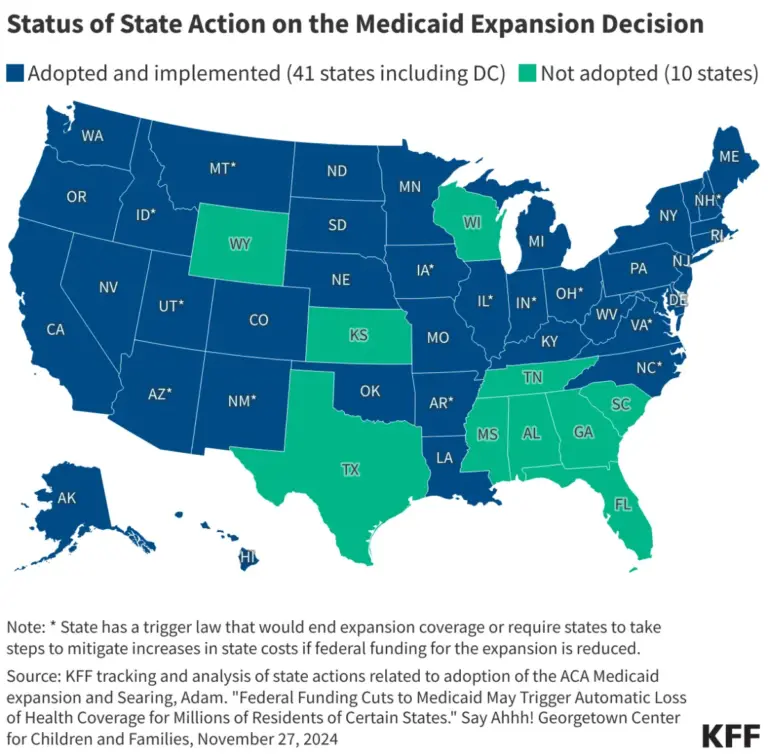
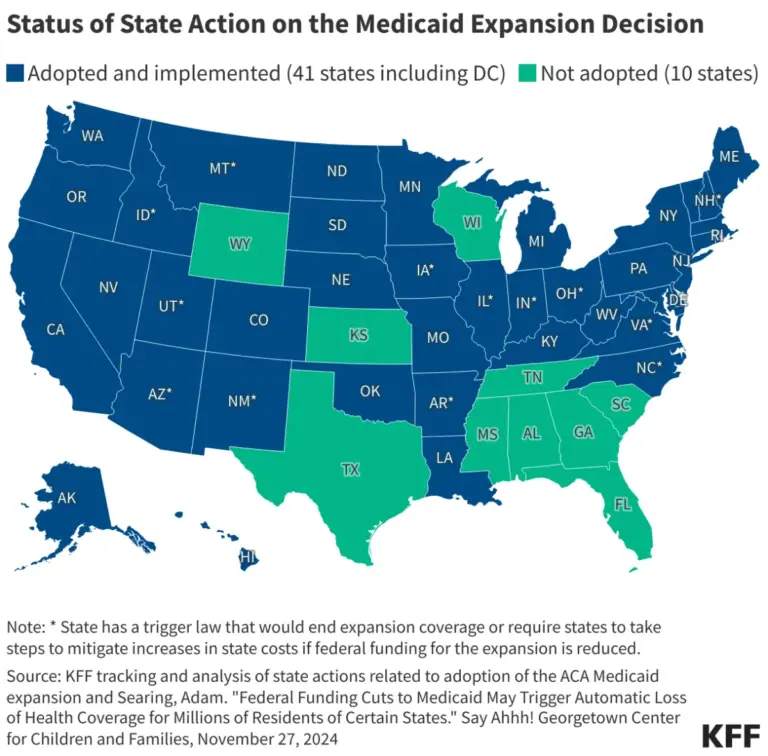
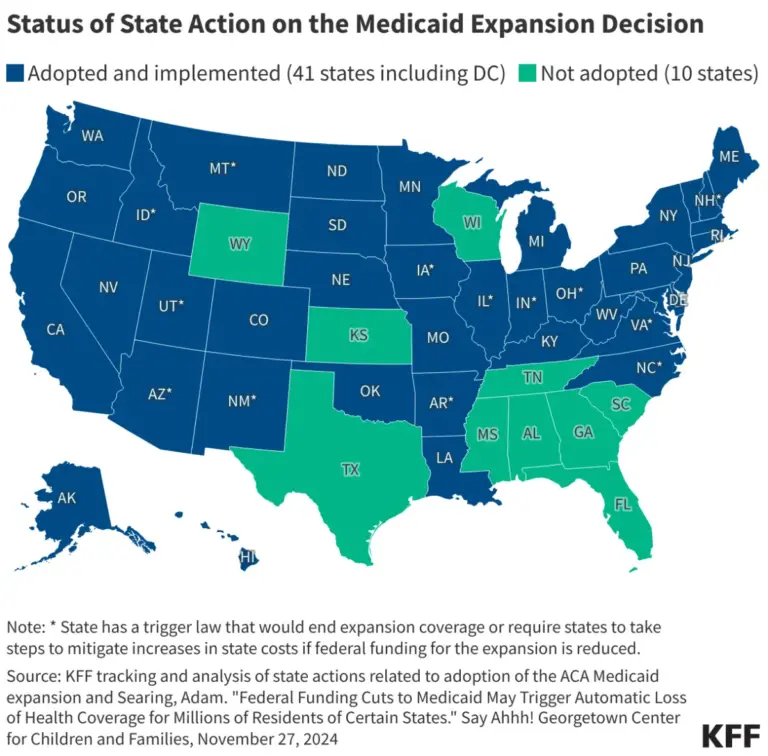
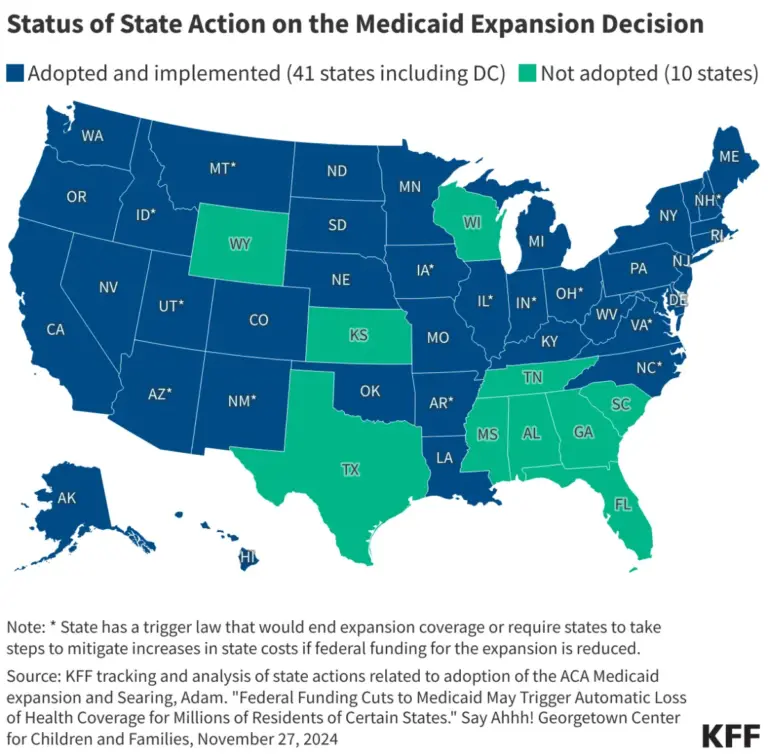
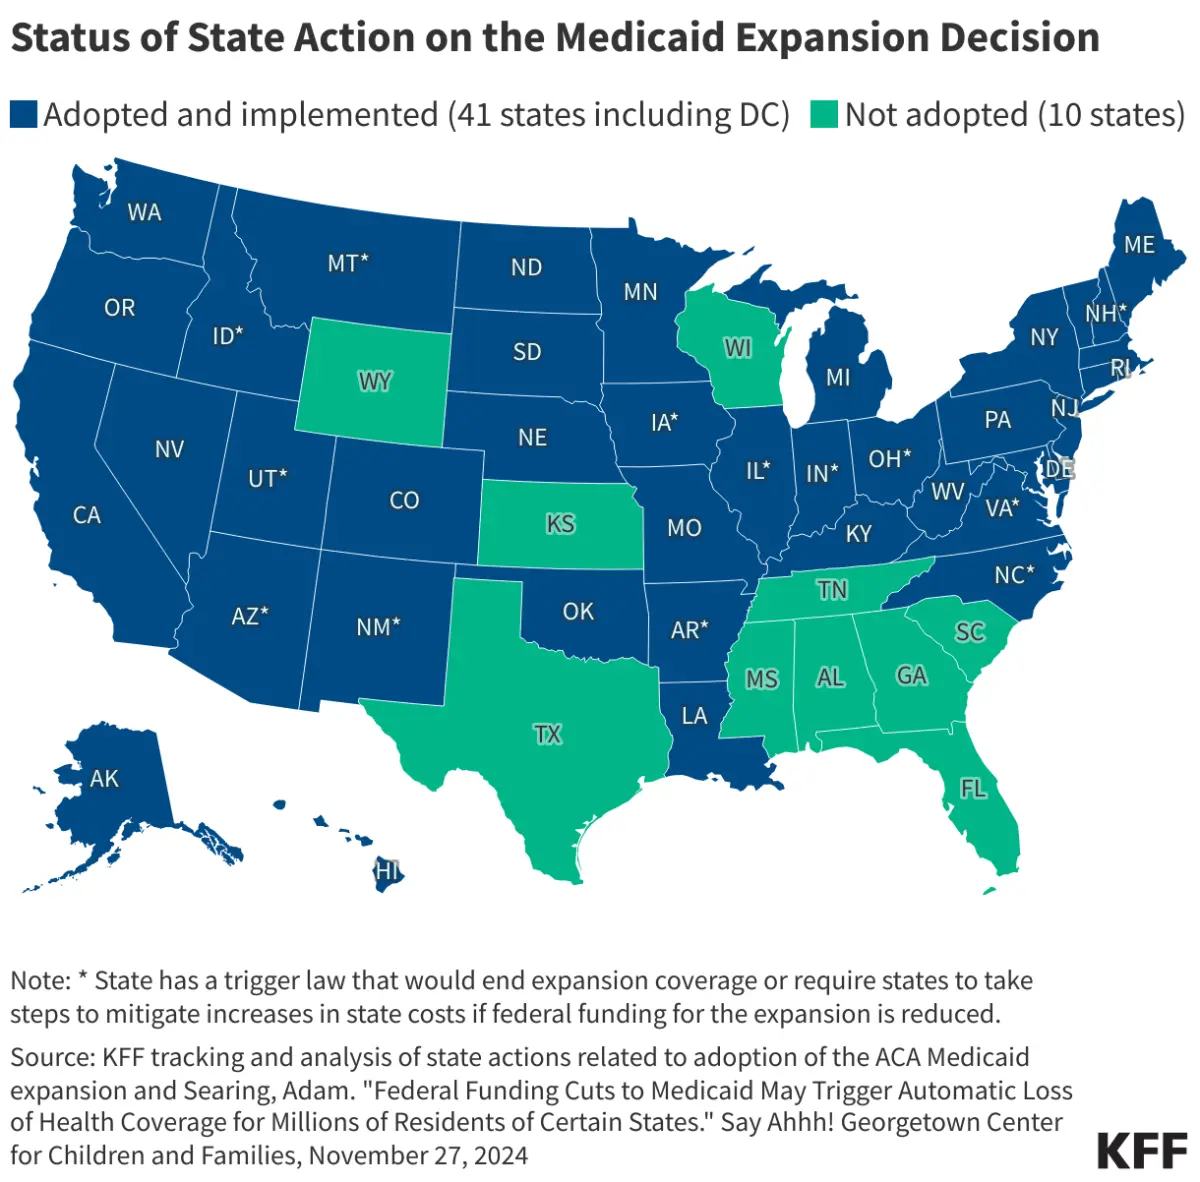
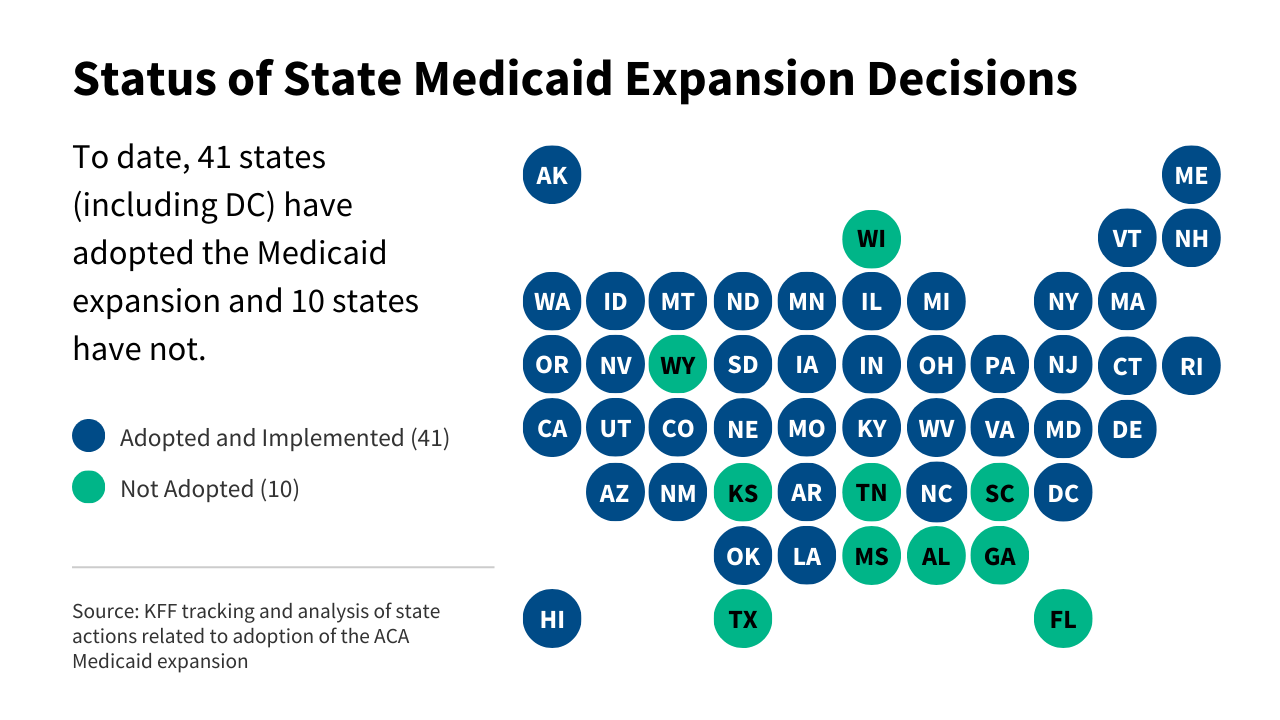
As of late 2024 and heading into 2025, the national map of Medicaid expansion presents a clear, if fragmented, picture. According to the latest tracking data from KFF, 41 states—including the District of Columbia—have formally adopted the Medicaid expansion. Conversely, 10 states remain as non-expansion jurisdictions, leaving a significant gap in coverage for low-income residents who earn too much to qualify for traditional Medicaid but too little to afford private insurance on the ACA marketplace.
This divide is not static. State legislatures, executive offices, and, in some cases, voter-led ballot initiatives continue to engage in a high-stakes tug-of-war over the program. For the 41 states that have embraced expansion, the focus has shifted from initial adoption to the complexities of program management, including the use of Section 1115 waivers to impose work requirements or other limitations on the expansion population. For the 10 holdout states, the debate persists through legislative bills, gubernatorial budget proposals, and grassroots organizing.
A Chronological Evolution of Expansion
The trajectory of Medicaid expansion has been marked by three distinct phases: the immediate post-ACA implementation, the era of state-by-state resistance, and the current period of consolidation and "trigger" policy uncertainty.
2010–2014: The Foundation
When the ACA was passed in 2010, the expansion was intended to be mandatory for all states. However, the 2012 Supreme Court ruling in NFIB v. Sebelius fundamentally altered the law, effectively making the expansion voluntary for states. This ruling created an immediate bifurcation in the healthcare market, as some states moved quickly to secure federal funding while others resisted on ideological or fiscal grounds.
2015–2020: The Wave of Ballot Initiatives
As legislative paths in conservative-leaning states proved difficult, advocacy groups shifted their focus to the ballot box. Starting with Maine in 2017, voters in several states—including Idaho, Nebraska, Utah, and Oklahoma—bypassed recalcitrant legislatures to approve expansion through direct democracy. This period highlighted a growing public consensus that prioritized health access over partisan opposition.
2021–Present: The "Trigger" Era
The current era is characterized by legislative caution. Many states have implemented "trigger" laws—statutes that make their expansion contingent upon the continued receipt of the enhanced federal matching rate. This creates a volatile environment where any potential federal budget cut could lead to the automatic termination of coverage for millions of residents.
Supporting Data: The Economic and Clinical Impact
The expansion is not merely a social policy; it is a massive fiscal instrument. The enhanced FMAP—which covers 90% of the costs for the expansion population—has served as a primary driver for state participation. For states, this federal investment has historically offset the costs of uncompensated care at hospitals, improved the solvency of rural health systems, and served as a powerful economic stimulus for the healthcare sector.
However, the data also reveals the vulnerability of this model. The Georgetown Center for Children and Families has recently warned that federal funding cuts to Medicaid could trigger an "automatic loss of health coverage" for millions. This risk is amplified by the existence of state-level trigger laws. For example, in states like South Dakota and West Virginia, policymakers have been debating the architecture of these triggers to protect against future federal volatility. In other states, such as Virginia, attempts to modify or remove these automatic termination clauses have met with legislative resistance, signaling that the future of the program remains tied to the stability of federal-state fiscal relations.
Official Responses and Political Maneuvering
The debate over expansion is as much about political identity as it is about health policy. Proponents of expansion emphasize the moral imperative of closing the "coverage gap," arguing that access to preventive care reduces long-term costs and improves population health metrics. Opponents, meanwhile, frequently cite concerns over long-term fiscal sustainability, the expansion of government dependency, and the potential for federal overreach.
Legislative and Executive Actions
The tracking of state-level activity reveals that the "non-expansion" states are rarely quiet. In these states, we see a recurring cycle of:
- Legislative Bills: Pro-expansion lawmakers frequently introduce bills that are stifled in committee or defeated on the floor.
- Gubernatorial Proposals: Some governors have proposed "limited coverage expansions." While these proposals often seek to bypass the full requirements of the ACA to avoid federal oversight or ideological traps, they often fail to qualify for the enhanced federal matching funds, limiting their scope and impact.
- Voter-Led Initiatives: These remain the most potent tool for bypass, though they are subject to strict legal and procedural hurdles that vary by state.
The Implications: Why It Matters
The implications of the Medicaid expansion divide are profound, affecting everything from economic mobility to mortality rates.
Health Equity and Clinical Outcomes
The primary implication is the persistence of the coverage gap. Individuals living in the 10 non-expansion states are disproportionately represented among the uninsured. This population faces significant barriers to accessing basic healthcare, leading to delayed diagnoses for chronic conditions like diabetes, hypertension, and cancer. The inability to access primary care forces many to rely on emergency rooms, which are the most expensive and least efficient venues for routine medical care.
Rural Health and Hospital Solvency
Many of the states that have resisted expansion are home to a high density of rural hospitals. The financial viability of these institutions is often tied to the volume of Medicaid-insured patients. In states that have not expanded, these hospitals have faced a "perfect storm" of high uncompensated care costs and declining patient volumes, leading to an alarming number of rural hospital closures. Expansion, by providing a steady stream of revenue, serves as a vital lifeline for these community anchors.
Economic Impact
Beyond the clinical, the economic argument for expansion has gained traction. Federal funds flowing into a state’s healthcare system act as a multiplier, creating jobs in the medical sector and keeping residents healthy enough to participate in the workforce. When a state declines to expand, it effectively leaves billions of dollars of federal tax revenue on the table—money that is paid by residents of those states but redirected to other, more compliant states.
Conclusion: The Road Ahead
The next phase of the Medicaid expansion story will likely be defined by federal budget negotiations and state-level fiscal anxiety. As the U.S. faces mounting pressures on the national debt, the stability of the enhanced FMAP will become a central point of contention. If the federal government moves to reduce these matching rates, the "trigger" laws currently on the books in several states will be tested for the first time.
The 10 holdout states face a narrowing window of opportunity to capitalize on the federal support currently available. Meanwhile, the 41 expansion states face the ongoing challenge of maintaining their programs in an environment of political polarization.
The Medicaid expansion is, at its core, a testament to the complexity of American federalism. It is a system that allows for localized policy innovation but also creates profound inequities based on geography. As the nation moves deeper into the 2020s, the debate over who deserves access to healthcare—and who should pay for it—will continue to be the primary litmus test for the effectiveness of the American social contract. Whether through future legislative shifts, court rulings, or a new wave of ballot initiatives, the status of Medicaid remains the most dynamic and consequential element of the nation’s healthcare landscape.
For policymakers, the challenge remains clear: finding a path toward universal coverage that respects the constraints of fiscal policy while fulfilling the fundamental promise of the Affordable Care Act. The data confirms that while progress has been immense, the work of ensuring health equity across the United States is far from complete.
About the Author