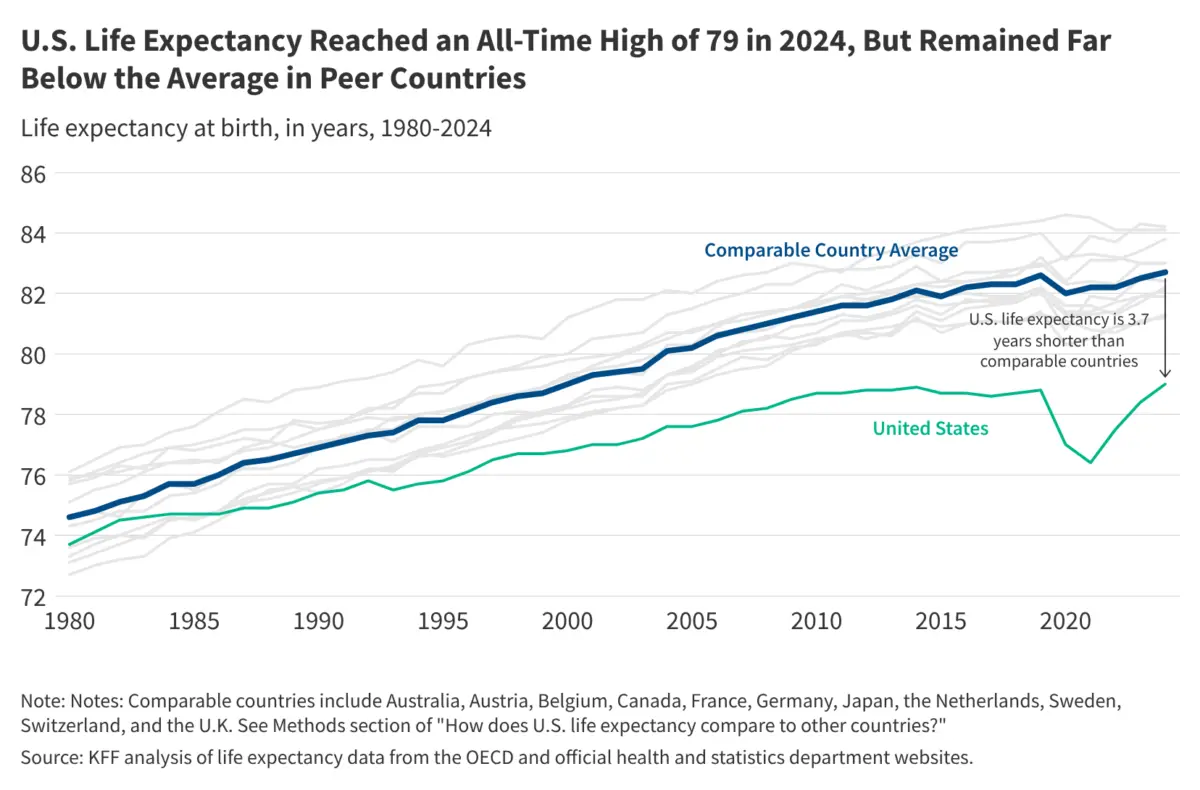
The United States healthcare system stands as a monumental paradox in the global landscape. While the nation pours unprecedented financial resources into medical innovation, pharmaceutical development, and state-of-the-art facilities, it simultaneously lags behind its economic peers in nearly every fundamental metric of population health. A comprehensive new data analysis from the Peterson-KFF Health System Tracker reveals a stark reality: despite spending nearly twice as much per capita on healthcare than any other wealthy nation, Americans face lower life expectancy and poorer long-term health outcomes.
This report examines the deep-seated discrepancies between U.S. investment and health performance, exploring why the wealthiest nation on earth struggles to translate its massive financial outlays into a healthy citizenry.
Main Facts: The Great Disconnect
The Peterson-KFF Health System Tracker’s latest chart collection provides a sobering comparison between the U.S. and other high-income, developed nations. The data underscores a consistent theme: the U.S. healthcare system is high-cost but low-value when measured against population-wide health indicators.
The primary takeaways are as follows:
- The Spending Gap: Per-capita healthcare spending in the U.S. is double that of comparable peer nations. This includes spending on hospital services, pharmaceuticals, administrative overhead, and specialized care.
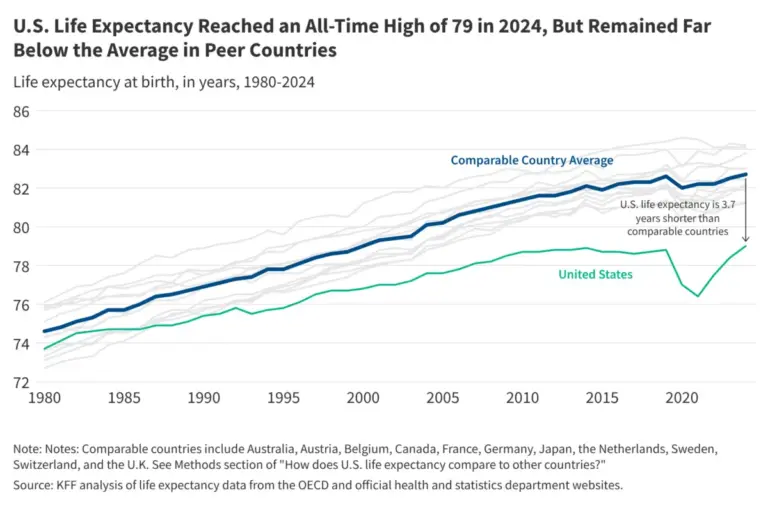
- Life Expectancy Deficit: Despite this investment, the average life expectancy for an American is lower than the average of its peer group, which includes nations like Canada, the United Kingdom, Germany, and Japan.
- Outcome Disparities: The U.S. performs significantly worse in long-term health metrics, such as the management of chronic conditions and maternal mortality rates.
- Capacity Issues: The U.S. suffers from a relative shortage of general practitioners, suggesting that the system is skewed toward reactive, high-cost specialty care rather than proactive, preventative primary care.
Chronology: A Decades-Long Divergence
The current state of U.S. healthcare is not the result of a single policy failure but rather the culmination of decades of structural divergence.
1970s–1980s: The Rise of the Fee-for-Service Model
During the late 20th century, the U.S. moved toward a decentralized, market-driven healthcare model. While other nations—particularly in Europe—began strengthening universal, tax-funded, or social-insurance systems, the U.S. doubled down on employer-sponsored private insurance. This era saw the rapid inflation of medical costs as the "fee-for-service" model incentivized the volume of services over the quality of outcomes.
1990s–2000s: The Technology Boom and Cost Escalation
As medical technology advanced, the U.S. became the world leader in diagnostic equipment and complex surgical interventions. While these advancements saved countless lives, they also contributed to the "medical arms race," where hospitals competed for patients by acquiring expensive technology, driving costs upward without necessarily improving broader public health indicators.
2010–Present: The ACA Era and Persistent Gaps
The passage of the Affordable Care Act (ACA) in 2010 aimed to expand access and bend the cost curve. While the ACA successfully reduced the number of uninsured Americans, it did not address the fundamental structural issues driving systemic high costs and lower-than-average outcomes. The gap between U.S. health metrics and those of peer nations has remained stubbornly wide, with life expectancy in the U.S. actually declining in the years surrounding the COVID-19 pandemic.
Supporting Data: Where the U.S. Falters and Where It Excels
To understand the complexity of the U.S. healthcare system, one must look beyond the macro-level failures and examine specific performance benchmarks.
Chronic Disease and Long-Term Outcomes
The U.S. faces a crisis in managing long-term health. Data shows that the U.S. has higher rates of hospital admissions for preventable chronic conditions, such as congestive heart failure and uncontrolled diabetes, compared to peer nations. This suggests a failure in the primary care infrastructure—the "gatekeeper" model that keeps patients healthy and out of the hospital is largely absent or inaccessible for many Americans.
Maternal and Obstetric Safety
Perhaps most alarming is the data regarding maternal mortality. The U.S. maternal mortality rate is significantly higher than that of other wealthy nations. Furthermore, metrics regarding obstetric trauma—injuries sustained during childbirth—show that U.S. hospitals lag behind international standards, indicating a gap in institutional patient safety protocols.
The Nuance of Success: Acute Treatment
It would be inaccurate to label the entire system a failure. The U.S. healthcare system performs exceptionally well in specific high-acuity scenarios. For instance, the mortality rate within 30 days of an acute hospital treatment (such as a heart attack or stroke) is often lower in the U.S. than in peer nations. Similarly, in certain post-operative safety measures, U.S. hospitals have implemented sophisticated protocols that reduce complications.
In short: If you are already acutely ill and have access to a top-tier U.S. facility, you are likely to receive some of the best care in the world. However, if you are seeking to avoid becoming acutely ill, the U.S. system is statistically inferior to its international peers.
Official Responses and Expert Perspectives
The release of the Peterson-KFF data has reignited debates among policymakers, economists, and healthcare providers.
The Economist Viewpoint
Health economists frequently point to the administrative complexity of the U.S. system. Unlike single-payer or highly regulated multi-payer systems in Europe, the U.S. system features thousands of different insurance plans, each with unique billing, coding, and coverage requirements. This "administrative burden" accounts for a significant portion of the extra spending that does not reach the patient.
The Provider Perspective
Medical associations, such as the American Medical Association (AMA), often highlight the burden of "defensive medicine." Because of the high risk of medical malpractice litigation in the U.S., physicians often order redundant tests and procedures to protect themselves, which contributes to the cost of care without improving health outcomes.
Policy Advocacy
Public health advocates argue that the focus must shift from "sick care" to "health care." They contend that until the U.S. addresses social determinants of health—such as nutrition, housing, and socioeconomic inequality—no amount of medical technology can close the gap in life expectancy.
Implications: The Future of the American System
The data presented by the KFF Health System Tracker carries profound implications for the future of American society and the economy.
1. Economic Sustainability
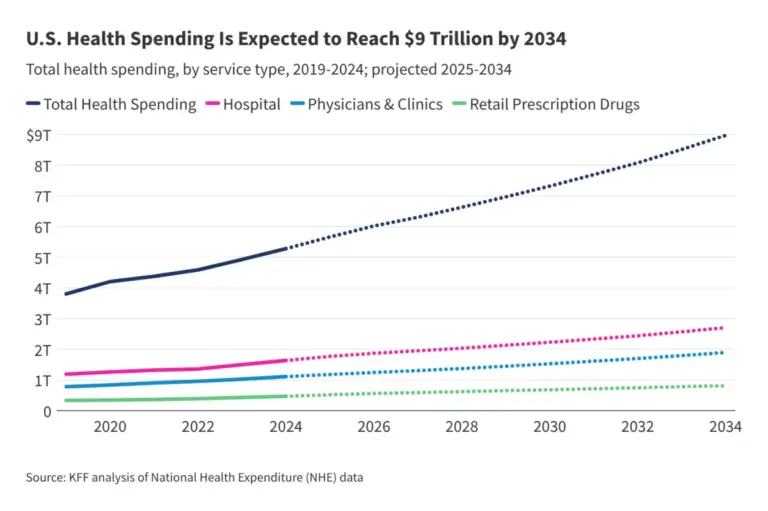
Healthcare spending currently consumes a massive share of the U.S. GDP. As the population ages, this spending is projected to grow, potentially crowding out other critical investments in education, infrastructure, and climate resilience. The current trajectory is arguably fiscally unsustainable.
2. The Health Equity Gap
The disparity in outcomes is not distributed equally. The U.S. system often exacerbates existing socioeconomic divides. Those with high-quality, employer-sponsored insurance may experience the "best" of the system, while those in rural areas or lower income brackets face the brunt of the system’s failures.
3. A Call for Structural Reform
The evidence suggests that minor tweaks will not suffice. Policymakers are increasingly looking toward:
- Value-Based Care: Transitioning from paying for the volume of tests to paying for health outcomes.
- Primary Care Expansion: Investing in the workforce and infrastructure to ensure every American has a medical home.
- Administrative Simplification: Streamlining the billing and insurance apparatus to reduce overhead costs.
Conclusion
The United States healthcare system is a masterpiece of technological capability that is failing to perform its most fundamental duty: keeping its people healthy. By continuing to spend significantly more than its peers while achieving lower life expectancy, the U.S. has created a system that is as inefficient as it is expensive. The Peterson-KFF data serves as a mirror, reflecting the urgent need for a shift in priorities—moving away from the worship of high-cost intervention and toward the realization of holistic, accessible, and preventative population health.
As the nation moves forward, the challenge will be to preserve the undeniable brilliance of American medical innovation while building the social and structural foundation required to make that care effective, equitable, and sustainable for all. The data is clear: the current path is unsustainable. The question remains whether the political and systemic will exists to fundamentally alter the course of American medicine.
About the Author