More than a decade after the landmark passage of the Affordable Care Act (ACA), the landscape of American healthcare remains deeply bifurcated. At the heart of this divide lies the Medicaid expansion, a policy initiative designed to extend coverage to nearly all adults with incomes up to 138% of the Federal Poverty Level—a threshold that, for an individual in 2025, translates to $21,597 annually. While the expansion has fundamentally reshaped the safety net for millions of low-income Americans, the decision to participate remains a state-level choice, leading to a fragmented system where access to care often depends on a resident’s zip code.
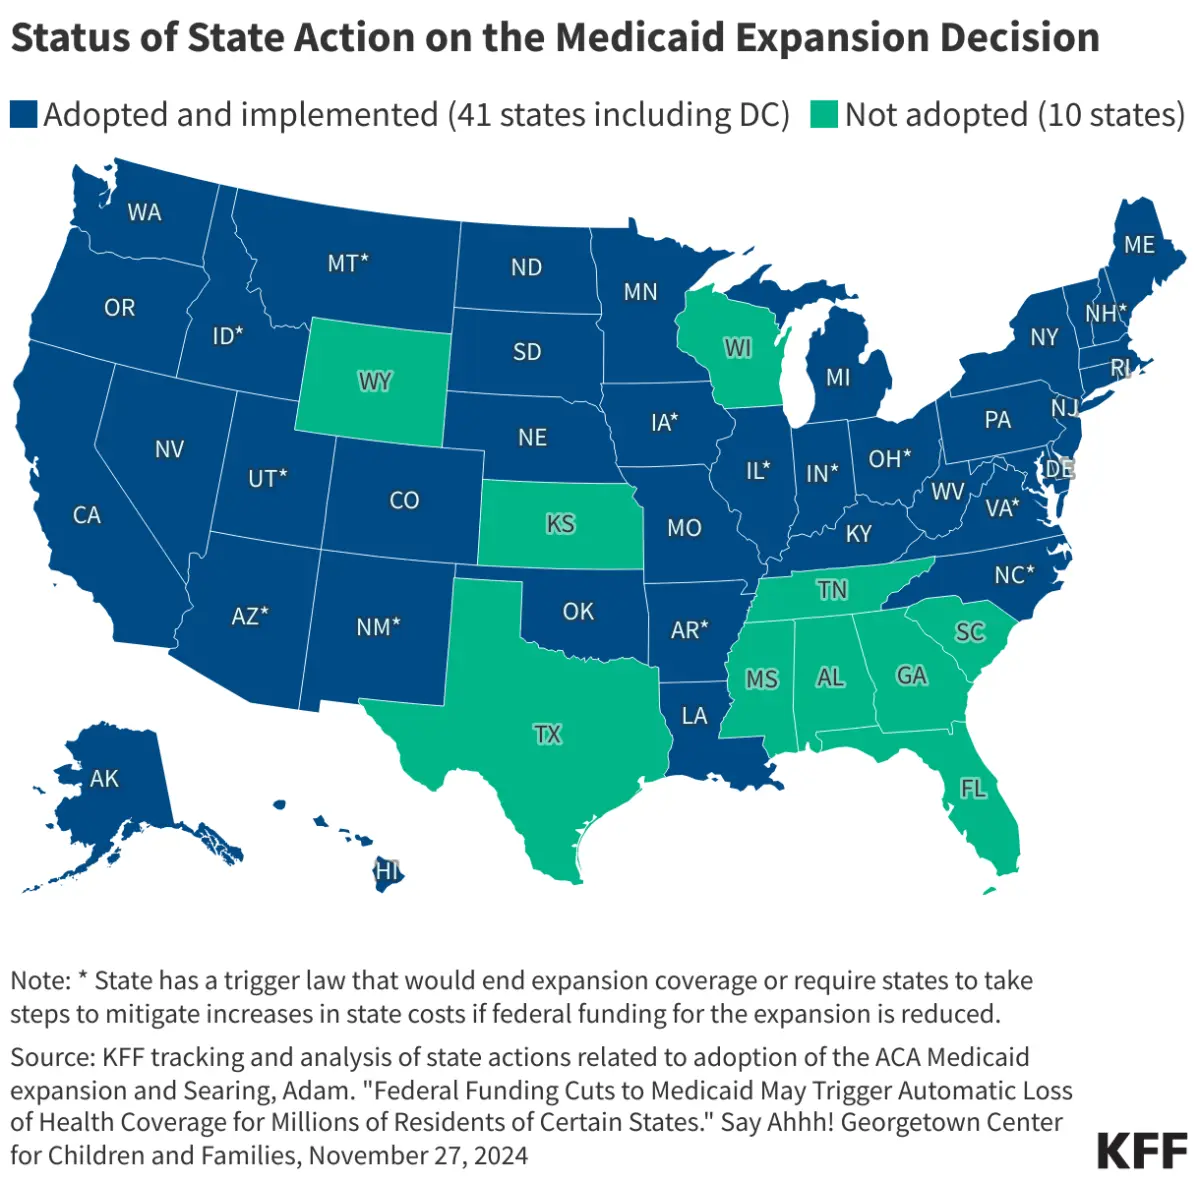
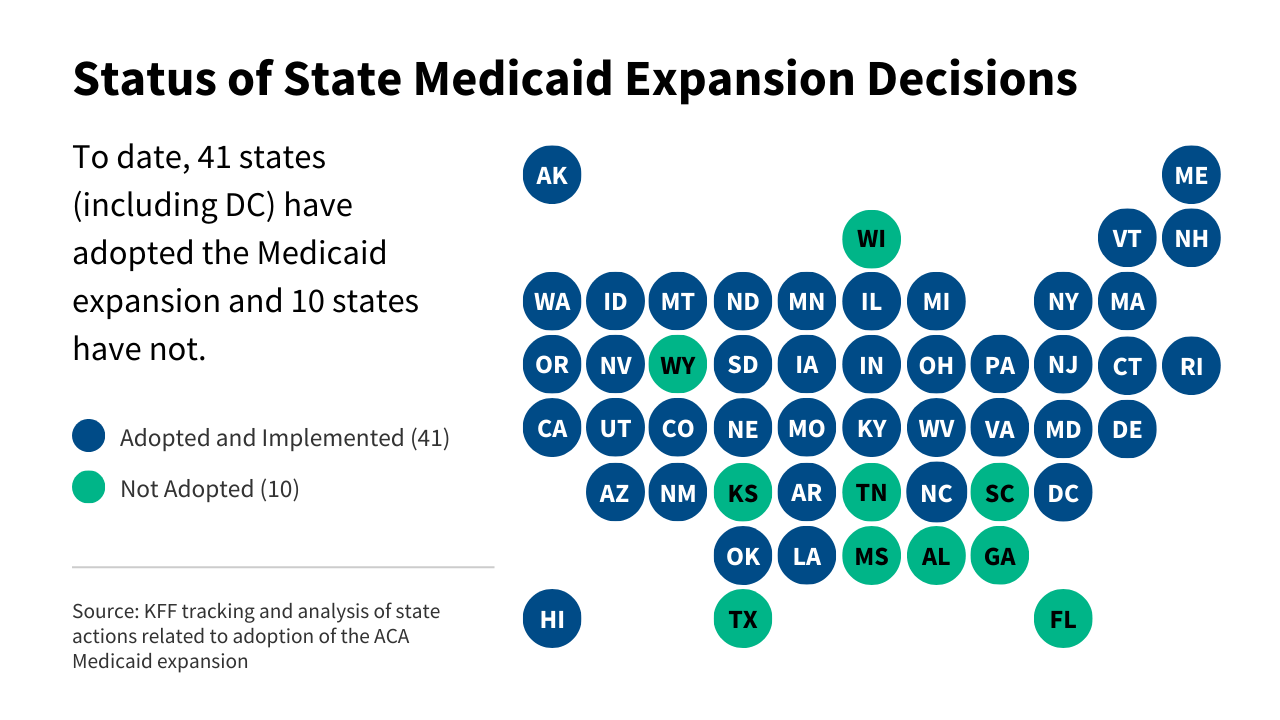
As of late 2024, the national tally reflects a significant, though incomplete, adoption of the policy: 41 states, including the District of Columbia, have embraced the expansion, while 10 states continue to hold out. This report examines the current status, historical context, and the ongoing policy debates surrounding the Medicaid expansion.
The Core Mechanism: Bridging the Coverage Gap
The ACA’s Medicaid expansion was crafted as a primary vehicle for poverty reduction and public health improvement. By offering states an enhanced federal matching rate (FMAP)—significantly higher than the traditional Medicaid match—the federal government incentivized states to broaden eligibility. The objective was to capture the "coverage gap" population: individuals who earn too much to qualify for traditional Medicaid but too little to afford private insurance through the ACA Marketplace.
For many states, the fiscal incentive was a powerful driver. The federal government covers the vast majority of the costs for the expansion population, shielding states from the full financial burden of providing comprehensive healthcare to their most vulnerable citizens. However, the political friction surrounding the expansion has often outweighed the fiscal benefits, leading to years of legislative deadlock in the remaining non-expansion states.
A Chronology of Expansion: From 2010 to 2025
The trajectory of Medicaid expansion has been anything but linear. Following the Supreme Court’s 2012 decision in NFIB v. Sebelius, which rendered the expansion optional rather than mandatory, the rollout transformed into a state-by-state political campaign.
- 2010–2013: Initial Adoption and Resistance: Immediately following the ACA’s passage, a cohort of states moved quickly to expand, viewing it as a moral and economic imperative. Conversely, a vocal group of conservative-led states rejected the expansion, citing concerns over long-term federal fiscal sustainability and the philosophical objection to expanding a government-run entitlement program.
- 2014–2018: The "Blue Wave" and Ballot Initiatives: As the benefits of expansion became visible in participating states—including lower uncompensated care costs for hospitals and improved health outcomes—public pressure mounted. During this period, several states, including Maine and Idaho, successfully bypassed legislative stalemates through voter-led ballot initiatives, signaling a growing public consensus for universal coverage.
- 2019–2023: The Southern Expansion Trend: The political calculus began to shift in the South. States like Louisiana, Arkansas, and eventually North Carolina, moved to expand, often framing the decision as a means to stabilize rural hospitals and stimulate local economies.
- 2024–2025: Current Status and Emerging Threats: Today, the focus has shifted from initial adoption to the defense of existing programs. In states that have already expanded, debates are now centered on "work requirements" and the potential implementation of Section 1115 waivers that could limit or place new conditions on the expansion population.
Supporting Data: The Geography of Access
KFF’s latest tracking data highlights the stark reality of the current divide. The map of the United States remains split, with the majority of non-expansion states concentrated in the South and parts of the Midwest.
Key Metrics and Trends
| Feature | Status |
|---|---|
| Expansion States (incl. DC) | 41 |
| Non-Expansion States | 10 |
| 2025 FPL Threshold (Individual) | $21,597 |
| Primary Legislative Activity | Budget amendments, "trigger" law revisions |
The data provided by organizations like KFF and the Georgetown Center for Children and Families suggests that the stability of these programs is being tested by "trigger laws." Some states have codified laws that tie the existence of their Medicaid expansion directly to the share of federal funding they receive. If federal contributions were to be reduced, these trigger laws could force an automatic, mass termination of coverage, leaving millions of vulnerable residents at risk of immediate health insurance loss.
Official Responses and Political Maneuvering
The discourse surrounding the expansion is characterized by a high degree of volatility. In non-expansion states, debate remains active, with governors and state legislatures frequently locked in negotiations.
Legislative vs. Executive Action
Current activity in non-expansion states is diverse. Some legislatures are debating bills that would initiate a study or partial expansion, while others are focusing on "limited coverage" models. It is important to note that many of these limited models do not meet the federal definition of a full ACA expansion and, consequently, do not qualify for the enhanced federal matching funds.
In expansion states, the conversation has moved toward administrative regulation. Legislators are increasingly exploring Section 1115 waivers—a mechanism that allows states to test new approaches to Medicaid. While the federal government has historically been skeptical of work requirements, the shifting political winds mean that states are constantly testing the boundaries of what is permissible under federal law.
The Trigger Law Debate
A critical area of concern involves the aforementioned "trigger" laws. For example, in Virginia, recent legislative sessions saw debates over whether to remove automatic termination clauses that threaten the expansion if federal funding levels fluctuate. Similar discussions have occurred in Illinois and North Carolina, where policymakers are grappling with the legal architecture of their programs to ensure they can withstand potential shifts in federal policy.
The Implications: Why It Matters
The failure to achieve nationwide expansion has profound implications for the American healthcare system, touching on economic, public health, and social equity dimensions.
Economic Consequences
For states that have resisted expansion, the economic fallout is twofold. First, the lack of coverage leads to higher rates of uncompensated care at hospitals, particularly in rural areas. When patients cannot pay for emergency services, the cost is often absorbed by the facility or passed on to private insurance premiums. Second, these states are effectively sending their tax dollars to Washington without receiving the full benefit of the federal investment, creating a "wealth transfer" that leaves their own healthcare infrastructure underfunded.
Public Health Disparities
The health implications are perhaps the most dire. Without access to preventative care, low-income individuals often delay seeking treatment until a condition becomes critical. This results in higher rates of untreated chronic illnesses such as diabetes, hypertension, and cancer. Furthermore, the absence of Medicaid expansion has been linked to higher maternal mortality rates and worsening outcomes in the fight against the opioid epidemic.
The Future of the Safety Net
As we look toward the remainder of the decade, the Medicaid expansion will likely remain a flashpoint in American politics. The push for "Universal Coverage" is frequently contrasted with the push for "Fiscal Conservatism." The tension between these two ideologies will dictate whether the remaining 10 states eventually join the fold or whether we see an erosion of the progress made in the 41 states that currently participate.
Conclusion: A System in Transition
The Medicaid expansion under the Affordable Care Act remains one of the most significant public policy experiments in American history. It has proven that federal-state partnerships can effectively expand access to care, yet it has also exposed the fragility of a system that relies on state-by-state political consensus.
For the millions of Americans living in the 10 states without expansion, the promise of the ACA remains largely unfulfilled. As policymakers continue to monitor federal funding, legislative trigger laws, and the evolving needs of the uninsured, the path forward will require a delicate balance between fiscal responsibility and the fundamental goal of ensuring that healthcare is accessible to all, regardless of economic standing. The data is clear: the expansion has saved lives and stabilized health systems, but until the divide is closed, the American healthcare landscape will continue to function as a tale of two nations.
About the Author