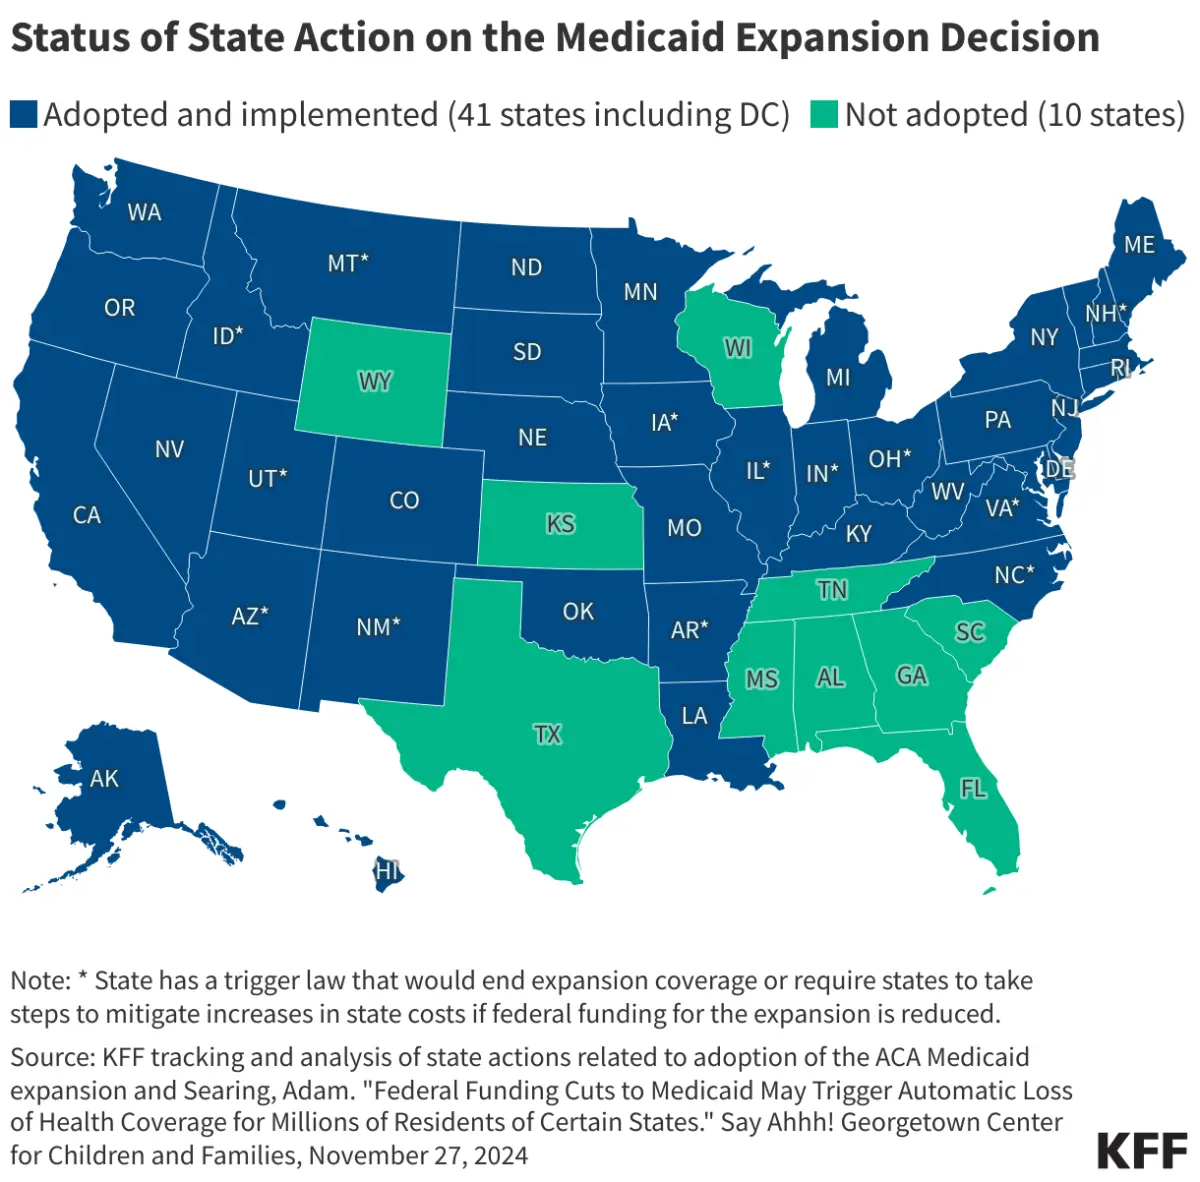
More than a decade after the Affordable Care Act (ACA) was signed into law, the landscape of American public health coverage remains defined by a stark geographical and political dichotomy. At the heart of this divide is the Medicaid expansion—a cornerstone of the ACA designed to extend health security to millions of low-income adults. As of 2025, while the majority of the United States has embraced this federal-state partnership, a significant minority of states continue to hold out, creating a patchwork of coverage that has profound implications for health equity, state budgets, and the political future of the American safety net.
The Core Mechanism: Bridging the Coverage Gap
The ACA’s Medicaid expansion was envisioned as a national solution to the "coverage gap"—the population of adults who earned too much to qualify for traditional Medicaid but too little to afford private insurance premiums. Under the expansion, states are empowered to cover nearly all adults with household incomes up to 138% of the Federal Poverty Level. For the 2025 calendar year, this threshold translates to an annual income of $21,597 for an individual.
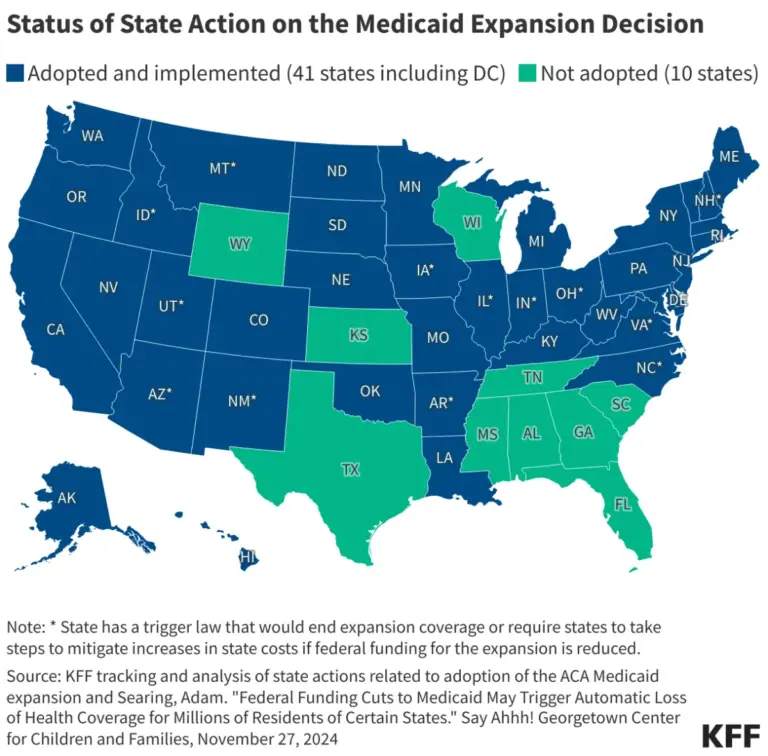
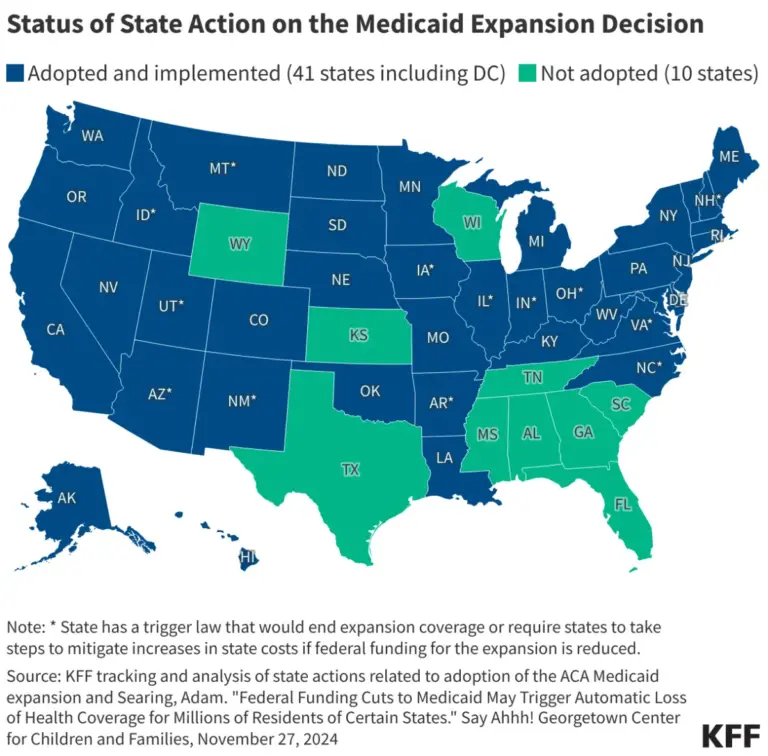
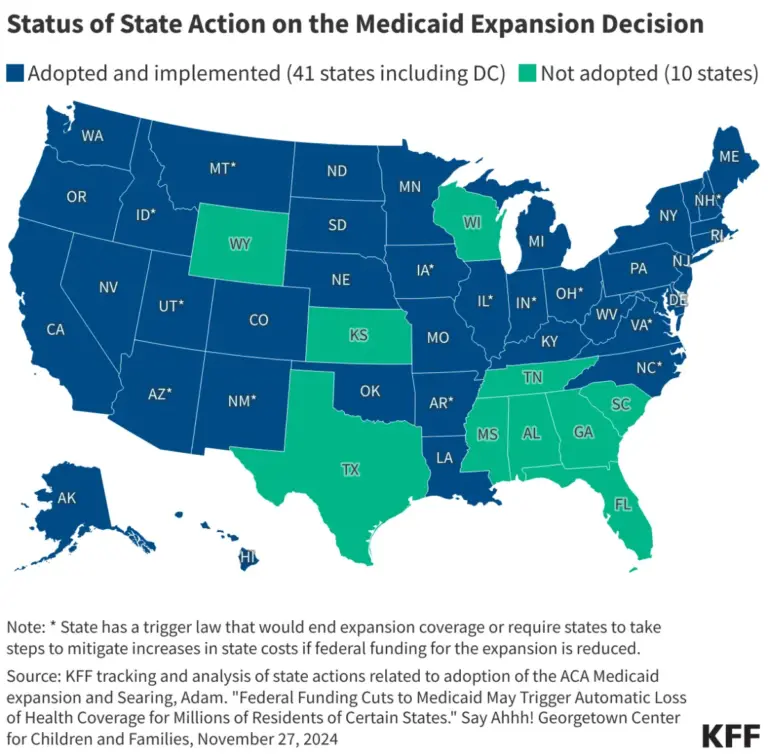
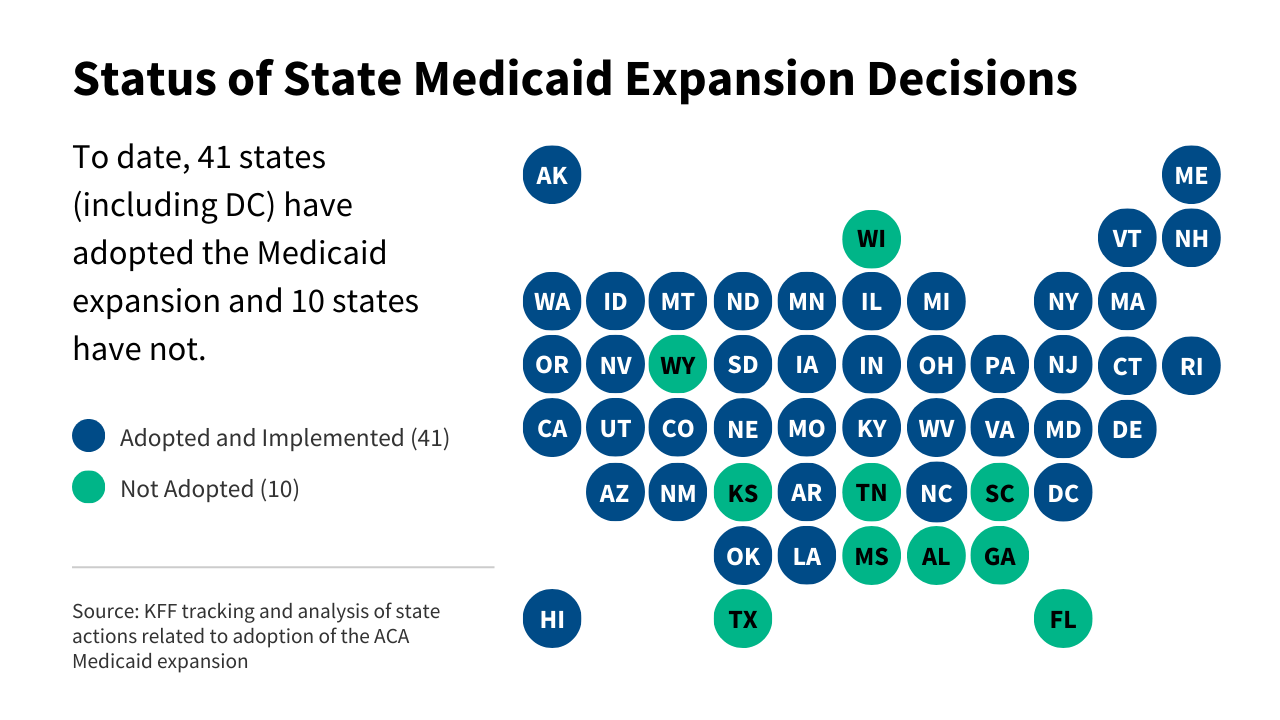
To incentivize participation, the federal government provides an enhanced Federal Medical Assistance Percentage (FMAP). This means the federal government covers a significantly larger share of the costs for the expansion population than it does for the traditional Medicaid population. Despite this fiscal enticement, the decision to expand remains a state-level prerogative. According to the latest tracking data from KFF, 41 states (including the District of Columbia) have formally adopted the expansion, while 10 states remain as non-expansion jurisdictions.
Chronology of a Policy Transformation
The journey of the Medicaid expansion has been marked by litigation, legislative battles, and shifts in public opinion.
2010–2012: The Mandate and the Court Challenge
When the ACA was passed in 2010, the expansion was intended to be mandatory for all states. However, the 2012 Supreme Court ruling in National Federation of Independent Business v. Sebelius fundamentally altered the trajectory of the law. The Court ruled that the federal government could not withhold existing Medicaid funding from states that refused to expand. This effectively turned a federal mandate into a voluntary option, setting the stage for the current state-by-state landscape.
2013–2018: The Initial Wave of Adoption
In the years immediately following the Supreme Court decision, a wave of states—led largely by Democratic governors or those with moderate Republican leadership—opted into the program. The economic arguments began to take hold: state hospitals were struggling with the burden of uncompensated care, and the infusion of federal dollars was seen as a vital economic stimulus for rural and urban healthcare systems alike.
2019–2025: Ballot Initiatives and Political Realignment
As the traditional legislative process stalled in many conservative-leaning states, the focus shifted to the ballot box. Voters in states like Idaho, Nebraska, and Utah bypassed reluctant legislatures by passing voter-led initiatives to expand Medicaid. This period also saw significant activity regarding "trigger laws"—statutes that link the existence of the state’s Medicaid expansion to the level of federal funding provided. Recent years have seen debates in states like South Dakota and West Virginia regarding these triggers, as lawmakers worry about the long-term sustainability of the program should federal funding levels shift.
Supporting Data: A Landscape in Flux
The current data reveals a country where access to life-saving care often depends on a zip code. The expansion states have seen significant reductions in their uninsured rates, leading to improved outcomes for chronic disease management, mental health, and substance use disorders.
The Fiscal and Legislative Tracker
For the non-expansion states, the "tracker" of current activity is a barometer of political intent. Legislative actions—such as the passage of bills through committees—and executive actions, such as gubernatorial budget proposals, provide a real-time look at how these states are navigating the pressure to expand.
In contrast, many expansion states are now in a "maintenance" phase, focusing on Section 1115 waivers. These waivers allow states to modify their programs, sometimes introducing new requirements for the expansion population. While these waivers provide flexibility, they also spark debate over whether they create barriers to coverage that contradict the original intent of the ACA.
Trigger Laws: The Safety Net’s Achilles’ Heel
A critical, often overlooked aspect of the current landscape is the rise of "trigger laws." These laws act as a legislative failsafe, providing for the automatic termination of the expansion program if the federal government reduces its share of the funding. The Georgetown Center for Children and Families has highlighted that such triggers could lead to an abrupt loss of coverage for millions of residents, creating a high-stakes environment for state budget planners. In states like Virginia, debates have centered on whether to remove these automatic termination clauses to provide more stability for the healthcare system.
Official Responses and Perspectives
The debate over Medicaid expansion is rarely just about health care; it is a debate about the role of government.
Proponents of Expansion argue that the policy is a moral imperative. By ensuring that low-income workers have access to primary care, states reduce the reliance on emergency rooms, which are the most expensive form of care. Public health officials frequently cite the "economic multiplier effect," noting that federal Medicaid dollars support jobs in the healthcare sector and bolster the financial viability of rural hospitals.
Critics and Opponents often cite concerns over long-term fiscal sustainability. Even with the enhanced federal matching rate, states are responsible for a portion of the costs. Opponents argue that if the federal government were to lower the FMAP, states would be left with a permanent, expensive entitlement program that could crowd out other budget priorities like education or infrastructure. Additionally, some conservative lawmakers argue that Medicaid expansion encourages dependency on government programs rather than private market participation.
Implications for the Future
As we look toward the remainder of the 2020s, the implications of this policy divide are profound.
Health Equity and Disparities
The most immediate implication is the persistent inequality in health outcomes. Residents in non-expansion states are statistically less likely to have a "medical home," more likely to delay care due to cost, and more likely to suffer from untreated chronic conditions. This creates a two-tiered system of health in America.
The Resilience of the Safety Net
The stability of the American healthcare safety net is currently tethered to the federal budget. Should the political climate in Washington shift, the reliance of 41 states on the federal government for a large portion of their Medicaid budgets creates a point of vulnerability. The ongoing discussions around "trigger laws" are a symptom of a deeper anxiety: the fear that the federal-state partnership is not as permanent as it once seemed.
The Role of Advocacy
The future of the remaining 10 non-expansion states will likely be determined by grassroots advocacy. As seen in the recent history of ballot initiatives, the public increasingly views health insurance as a necessity rather than a luxury. Whether through voter initiatives or shifting political coalitions, the pressure on these final holdout states is unlikely to dissipate.
Conclusion
The Medicaid expansion under the Affordable Care Act remains one of the most significant domestic policy achievements of the 21st century. It has successfully moved millions of Americans from the margins of the healthcare system into the mainstream. However, the fact that the expansion remains incomplete after more than a decade of implementation highlights the persistent friction in the American federalist system.
For the 41 states that have embraced expansion, the focus has shifted to sustainability, quality improvement, and the management of waiver programs. For the 10 states that have not, the debate continues, fueled by the competing priorities of fiscal caution and the undeniable health needs of their citizens. As the healthcare landscape continues to evolve, the Medicaid expansion will remain a primary battleground for the vision of what a modern, equitable American society should provide for its most vulnerable members.
The data is clear: the expansion has changed the life expectancy, financial security, and health outcomes of a nation. Whether the remaining gaps will eventually be closed remains one of the most important unresolved questions in American public policy.
About the Author