The pharmaceutical industry stands at a critical juncture. As clinical trial protocols grow increasingly complex—ballooning to an average of nearly 6 million data points per phase 3 study—the traditional, human-centric model of clinical monitoring is buckling under the weight of manual data wrangling. In response, a new study from the Tufts Center for the Study of Drug Development (CSDD) and clinical trial platform provider Medable has provided the industry’s most rigorous look yet at how “agentic” AI can transform this operational bottleneck into a significant financial engine.
The analysis, which focuses on oncology trials, reveals that Medable’s Clinical Monitoring Agent could generate an 82x return on investment (ROI) for phase 3 trials and a 64x ROI for phase 2. In terms of expected net present value (eNPV), these figures translate into a staggering $21 million in added financial value for phase 3 studies and $7.5 million for phase 2.
Main Facts: A Paradigm Shift in Clinical Oversight
The collaboration between Tufts CSDD and Medable marks a departure from speculative AI hype. By applying financial modeling to operational metrics, the researchers sought to move the conversation from “AI efficiency” to “bottom-line impact.”
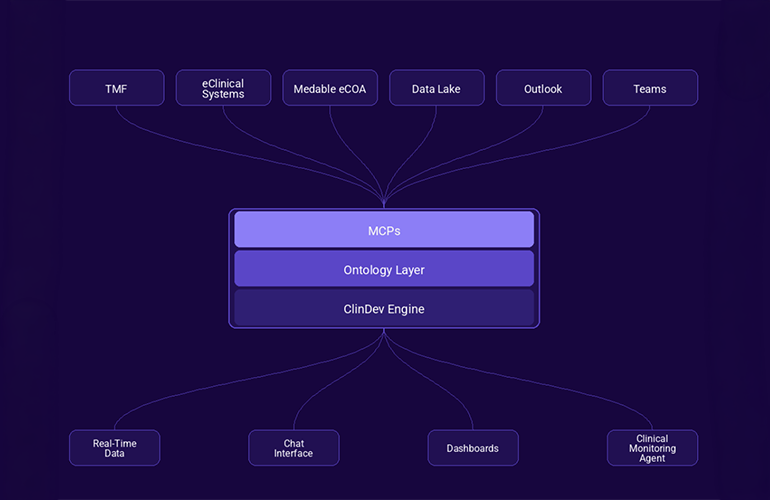
The Clinical Monitoring Agent functions as a digital layer integrated into a sponsor’s existing clinical ecosystem. It pulls data from disparate sources—including Electronic Data Capture (EDC) systems, Clinical Trial Management Systems (CTMS), and safety databases—to identify trends, flagging potential protocol deviations, adverse event reporting gaps, and enrollment lags long before a human analyst might notice them.
The core findings of the study suggest that for sponsors with large oncology portfolios, the cumulative impact is massive. For a pharmaceutical company managing 20 active indications, the incremental eNPV is projected at up to $226 million. For larger portfolios with 50 indications, that figure jumps to an estimated $565 million, assuming the value proposition holds across each study.
The Chronology of the AI Integration
The journey toward this level of automation has been a multi-year evolution within the clinical space:
- 2024–2025 (The Pilot Phase): Pharmaceutical companies began experimenting with AI/ML to handle specific, siloed tasks. During this period, the industry struggled to quantify the actual value, often viewing AI as an experimental cost center rather than a strategic asset.
- Late 2025 (The Productivity Realization): IBM and other industry analysts reported that software developers were seeing significant time savings—averaging one to two hours per day—thanks to agentic workflows. This prompted clinical leaders to ask: If AI can write code, why can’t it monitor clinical trial data?
- 2025 (The 18% Benchmark): A previous Tufts CSDD study of 36 industry-reported AI/ML use cases confirmed that AI-enabled solutions were delivering an average 18% reduction in cycle time, particularly in patient monitoring and enrollment assessment.
- August 2026 (The Validation): The current Tufts-Medable study marks the transition from "pilot" to "proven investment," providing the first clear financial framework for justifying the cost of agentic AI deployments in clinical trials.
Supporting Data: Wrangling the Complexity
The necessity for AI in modern trials is driven by an explosion in data density. A recent Tufts CSDD/TransCelerate analysis of 105 protocols across 15 major sponsors found that the average phase 3 protocol now contains 5.9 million data points, a nearly six-fold increase from the 929,000 data points recorded in 2012.
The Failure Rate Context
This data surge is occurring against a backdrop of persistently high failure rates. According to data published in the Journal of Medicinal Chemistry, the cumulative failure rate for small-molecule cancer drugs has remained stagnant at approximately 95% from phase 1 through phase 3 for three decades. While success rates in phase 3 oncology have improved slightly—a 2026 analysis of 824 trials showed a 43.4% success rate—the margin for error remains razor-thin.
The Medable agents are designed to mitigate this risk by acting as an early-warning system. By identifying sites that are falling behind or detecting adverse event trends before they become safety signals, the agents allow for mid-study adjustments that were previously impossible to execute in real-time.
Official Responses: Moving Beyond the "Black Box"
The collaboration was designed to answer the question: "What is the actual value proposition?"

"We’ve known for some time that companies have been piloting AI enablement tools, but what they’ve often been lacking is any kind of quantification of the actual ROI," said Ken Getz, executive director of the Tufts CSDD. "We were really interested in doing a study where we could put some hard numbers around a specific AI enablement solution."
Dr. Pamela Tenaerts, Chief Medical Officer at Medable, emphasized that the agent’s true power lies in its ability to synthesize context across systems. "The agent has the ability to see things slightly earlier than a human would," Dr. Tenaerts noted. "It can see across the sites a clinical research associate (CRA) manages, whether that’s a recurring issue or not. It allows the human to focus on higher-priority decisions—like whether to amend a protocol or shift strategy—while the agent handles the mundane data wrangling."
However, industry experts are careful to manage expectations regarding autonomy. Venu Mallarapu, chief transformation and AI officer at eClinical Solutions, noted that while the industry is moving toward more sophisticated agents, we remain in an "assistive" era. "There’s nobody that is running fully autonomous agents that not only process the data but also make decisions without human involvement," Mallarapu observed.
Implications: The Future of the Clinical Operating Model
The implications of the Tufts-Medable study are far-reaching, suggesting that the "human-in-the-loop" model will be the standard for the foreseeable future, even as the "loop" becomes increasingly automated.
1. The "Recommend-and-Review" Workflow
Medable’s approach is a prime example of the current industry standard. The agent performs tasks such as drafting queries for missing data and filing them in the Trial Master File (TMF), but the final decision remains with the human. The agent does not "suspend" the CRA’s judgment; it enhances it.

2. The Bottleneck Migration
Dr. Tenaerts raised a critical point regarding the future of site operations: "If we are getting really efficient at sending out emails to sites, we sure hope that the sites will get some help, because if you dump all that stuff on them, that’s still a bottleneck, right?" As AI increases the velocity of clinical monitoring, the pressure shifts to the clinical sites themselves, which may require their own AI-enabled tools to manage the increased volume of communication and data queries.
3. Configurability as a Competitive Advantage
One of the most important takeaways from the study is that "off-the-shelf" AI is not a reality for clinical trials. Because every sponsor has different systems and protocols, Medable’s agents require approximately 20% customization to fit the specific nuances of a trial. This suggests that the value of an AI agent is not just in the algorithm, but in the breadth of its integrations (Medable currently connects with 40+ systems, including Oracle, Veeva, and Databricks).
4. Expansion Beyond Oncology
While the current ROI data is specific to oncology, the logical next step is the horizontal scaling of these agents into other therapeutic areas. As Dr. Tenaerts noted, the mechanisms of data monitoring are universal. If the ROI model holds for oncology—a high-complexity, high-risk environment—it is highly probable that the financial benefits will be even more pronounced in less complex trials, potentially lowering the barrier to entry for smaller biotech firms and orphan drug developers.
Conclusion: The ROI of Clarity
The Tufts CSDD and Medable analysis provides a roadmap for the pharmaceutical industry. By moving away from the "black box" mystery of AI and into the realm of concrete financial modeling, they have provided a blueprint for how to scale innovation. The future of clinical research will not be defined by whether we use AI, but by how effectively we integrate it into the human-centric decision-making processes that define the success or failure of life-saving therapies.
As the industry continues to battle a 95% failure rate in drug development, the ability to turn millions of data points into actionable, real-time insights is no longer just an efficiency play—it is a competitive necessity. With an 82x ROI on the table, the question for many executives is no longer "Why should we invest?" but rather, "How quickly can we deploy?"
About the Author