Introduction: A Policy Milestone
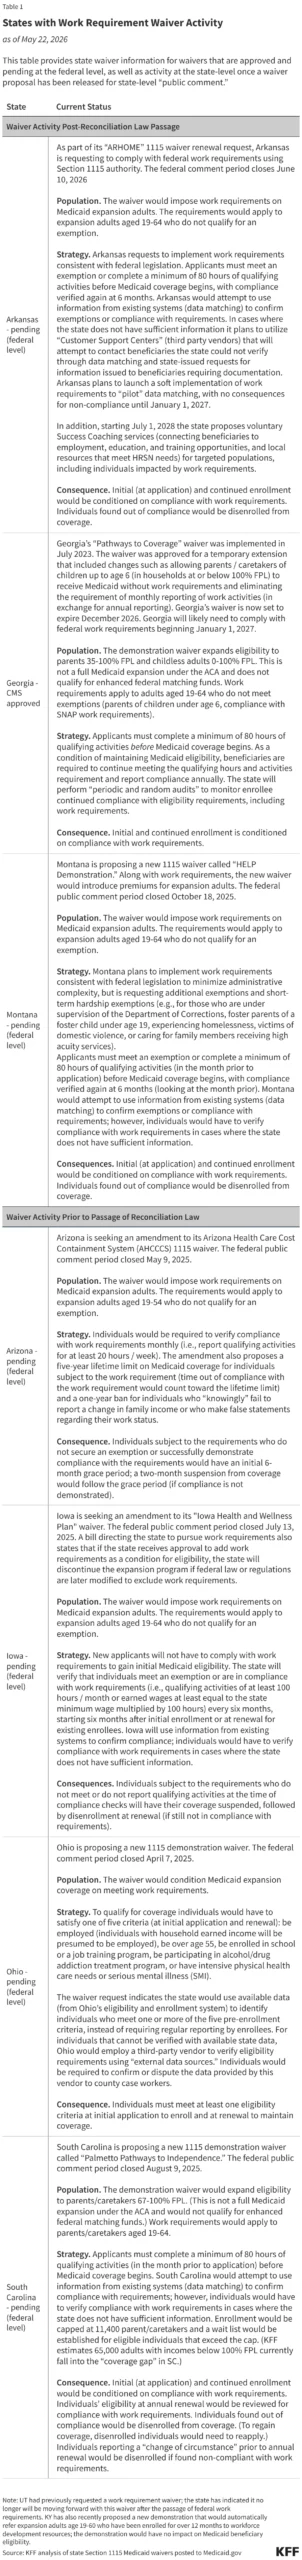
On May 1, 2026, Nebraska etched its name into the history of American social policy by becoming the first state in the nation to enforce mandatory work requirements for Medicaid eligibility. This shift, authorized under the federal 2025 reconciliation law, mandates that states tie Medicaid benefits for adults in the Affordable Care Act (ACA) expansion group—along with specific waiver program enrollees—to documented workforce participation or valid exemptions.
While federal law sets a nationwide implementation deadline of January 1, 2027, Nebraska opted for an accelerated timeline. This decision has positioned the state as a "policy laboratory," providing the first tangible, real-world data on how these requirements impact low-income populations. As the national discourse intensifies ahead of the 2026 midterm elections, Nebraska’s experience offers a complex look at the intersection of government assistance, administrative burden, and the labor market.
Chronology: From Legislation to Enforcement
The path to Nebraska’s current policy environment began with the 2025 federal reconciliation bill, a legislative package that fundamentally altered the administration of state-level Medicaid programs.
- May 1, 2026: Nebraska officially commences the enforcement of work requirements for new Medicaid applicants, preempting the national deadline.
- July 2026: The state begins applying these requirements to existing Medicaid enrollees undergoing their annual coverage renewal process.
- September 17, 2026: The Nebraska Medicaid Advisory Committee (MAC) holds a pivotal meeting to review the first four months of implementation data. This meeting served as the primary window into the program’s initial success and friction points.
- January 1, 2027: The federal deadline for all states to implement work requirements, following the path blazed by Nebraska.
- January 1, 2028: A critical threshold for states. After this date, the federal government will strictly limit the use of self-attestation, requiring more rigorous, paper-trail-heavy documentation for eligibility verification.
The Mechanics of Verification: A Two-Tiered System
Nebraska’s strategy for verifying compliance relies on a hybrid approach intended to minimize administrative bottlenecks while ensuring policy adherence.
Data Matching and Self-Declaration
The state’s Department of Health and Human Services (DHHS) first attempts to verify employment status through automated data matching with state wage databases. If a match is found, the individual is sent an approval notice, effectively removing the need for further action.
When the state lacks sufficient data, the burden shifts to the applicant. In these instances, the state issues a formal notice of information request, accompanied by a declaration form. Applicants have a 30-day window to return this form, attesting that they are either engaged in qualifying activities—such as full-time employment, vocational training, or community service—or that they meet specific exclusion criteria.
Hardship Exceptions
Recognizing that life circumstances can fluctuate, Nebraska has implemented a series of short-term hardship exceptions. These are designed to protect individuals facing:
- Regional Economic Volatility: Residing in counties with high unemployment rates.
- Crisis Events: Displacement or economic instability caused by natural disasters.
- Medical Necessity: Inpatient hospitalizations or stays in long-term nursing facilities.
- Caregiving and Medical Travel: Mandatory travel outside one’s community to secure essential healthcare for oneself or a dependent.
Supporting Data: Assessing the Impact
The September 2026 MAC report provides the first comprehensive look at the program’s impact. The data suggests that while the vast majority of enrollees remain unaffected or are in compliance, a notable segment of the population has lost access to coverage.
Application Outcomes
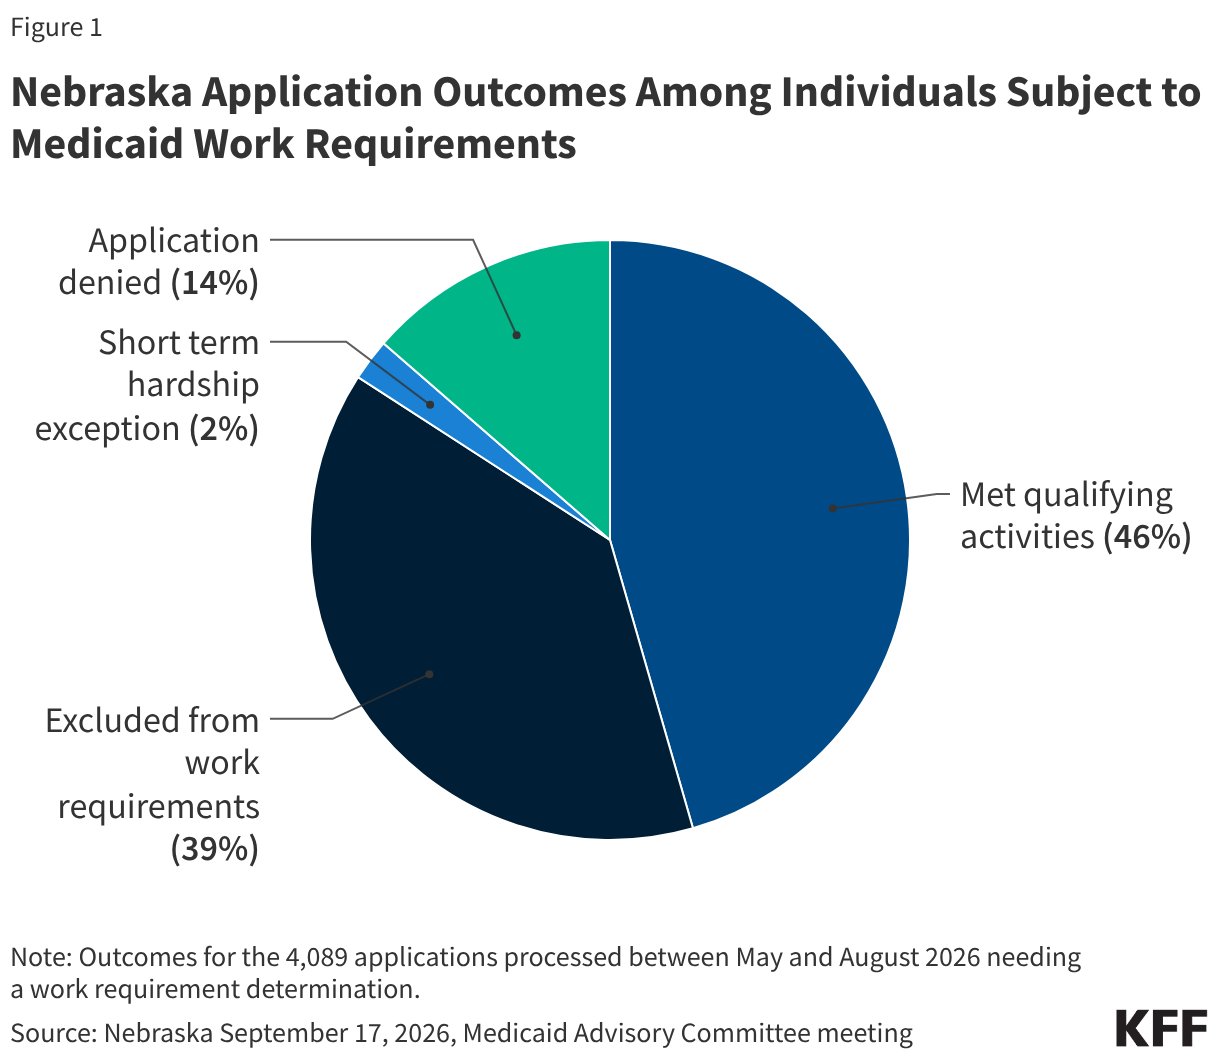
Between May and August 2026, the state processed 9,614 applications. After filtering out applications submitted prior to the policy start date and those denied for traditional reasons (such as income levels exceeding eligibility thresholds), 4,089 applications were evaluated under the new work requirements.
- 86% Success Rate: The overwhelming majority of applicants either met the work requirements, qualified for an exclusion, or were granted a hardship exception.
- 14% Denial Rate: This group, totaling roughly 572 individuals, saw their applications denied specifically due to the new requirements.
Renewal Outcomes
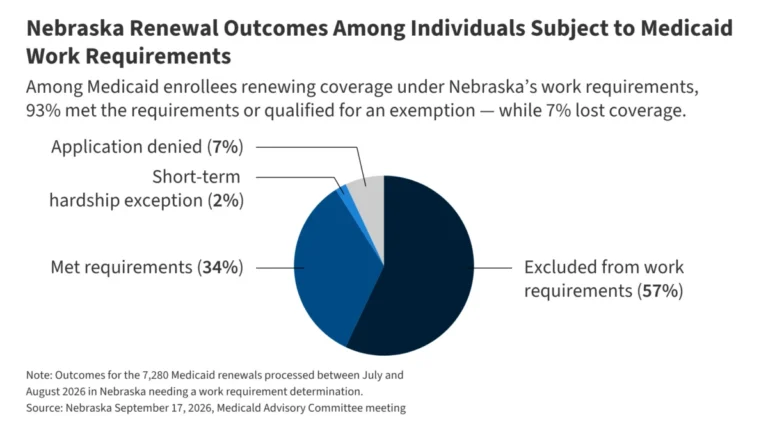
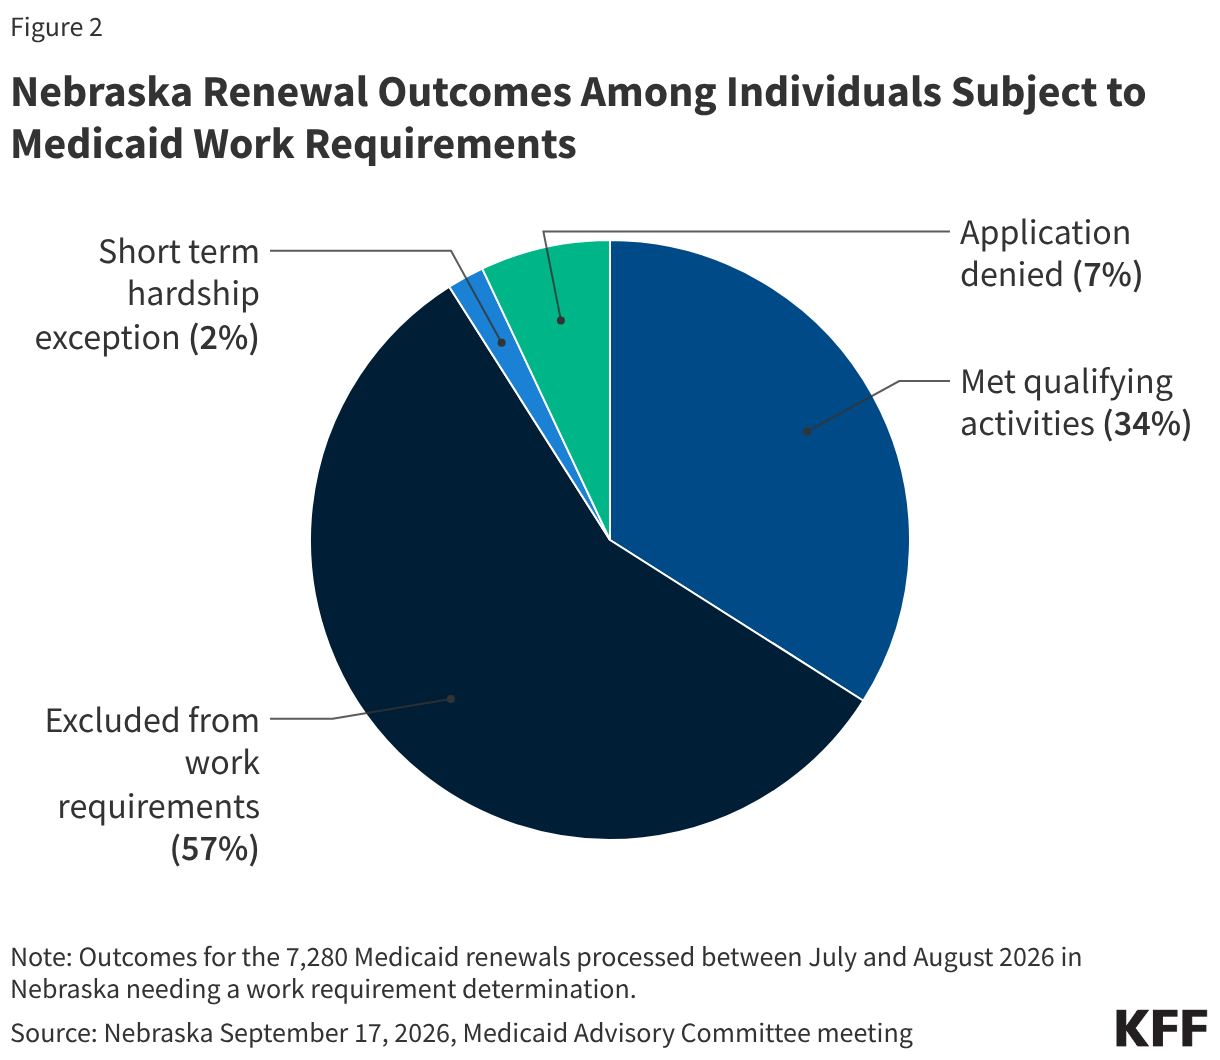
The data for existing enrollees is similarly stark. Between July and mid-August 2026, the state processed 7,280 renewals subject to the mandate.
- 93% Retention Rate: The vast majority of enrollees successfully navigated the new verification process.
- 7% Disenrollment Rate: Despite the high retention, 7% of enrollees—over 500 individuals—lost their coverage.
KFF analysts suggest these figures should be viewed with caution. It remains unclear whether the individuals who were disenrolled were truly ineligible, or if they simply failed to respond to administrative notices due to confusion or barriers in the verification process.
Official Responses and Administrative Friction
The implementation of these requirements has not been without its challenges. The Centers for Medicare & Medicaid Services (CMS) has already signaled that Nebraska’s current reliance on self-attestation is a "first-year luxury."
The CMS Warning
In recent communications, CMS has urged the state to tighten its medical frailty verification process. The federal government expressed concern that the current, more permissive approach might be misclassifying individuals who do not truly meet the criteria for "medically frail" status. By mandating stricter oversight, CMS is effectively signaling that future disenrollment rates in Nebraska—and other states—may increase as the administrative "safety net" of self-attestation is dismantled.
The "Administrative Burden" Critique
Public policy experts, including researchers from the Kaiser Family Foundation (KFF), argue that the primary risk of these programs is not the work requirement itself, but the "administrative churn." For gig workers, seasonal laborers, or those holding multiple part-time jobs, documenting fluctuating hours is notoriously difficult. If the state’s portal or paper-based systems are not user-friendly, the "loss of coverage" may be a result of technical failure rather than a lack of employment.
Implications: The Road Ahead
As Nebraska moves into the second year of its program, the focus will shift from initial implementation to long-term sustainability.
The 2028 Threshold
The most significant hurdle on the horizon is the transition away from self-declaration. Starting in 2028, the ability to simply "check a box" to claim an exclusion will be largely eliminated. This will require the state to manage a massive influx of physical documentation—pay stubs, physician letters, and training certificates. The potential for a sharp increase in disenrollment during this transition is high, as the administrative burden on the state and the applicant will reach its peak.
Election Year Dynamics
The timing of this policy, occurring in the heat of the 2026 midterm election cycle, has turned Nebraska into a political flashpoint. Supporters of the policy argue that it promotes personal responsibility and ensures that the Medicaid program remains focused on the most vulnerable. Critics, conversely, point to the 7–14% disenrollment rates as evidence that the policy acts as a barrier to healthcare for working-class citizens who may be struggling to navigate a complex bureaucracy.
Looking for Patterns
Moving forward, researchers are looking for more granular data. Questions remain:
- Re-application Rates: Do individuals who lose coverage eventually return to the rolls, or are they permanently disenrolled?
- Barrier Identification: Are there specific cohorts—such as those with disabilities not yet classified as "medically frail"—who are disproportionately losing coverage?
- Labor Market Effects: Does the policy actually increase workforce participation, or does it merely shift the demographic composition of the Medicaid-insured population?
Conclusion
Nebraska’s experiment is a bellwether for the future of the American safety net. The state has proven that it is possible to implement these requirements, but the human and administrative costs of doing so remain subject to intense debate. As the rest of the country prepares to follow suit by 2027, the lessons learned from the "Nebraska Model"—both its successes in retention and its challenges in verification—will be vital for policymakers across the political spectrum. For now, the data suggests that while the system is functioning for most, the margin of error for the remaining percentage of the population is razor-thin.
About the Author