Executive Summary: The Flexibility Paradigm
Medicaid Section 1115 demonstration waivers have long served as the primary laboratory for American health policy. By allowing states to bypass specific federal statutory requirements, these waivers grant governors and state legislatures the flexibility to experiment with innovative delivery systems, eligibility criteria, and benefit structures—provided these changes align with the "objectives of the Medicaid program."
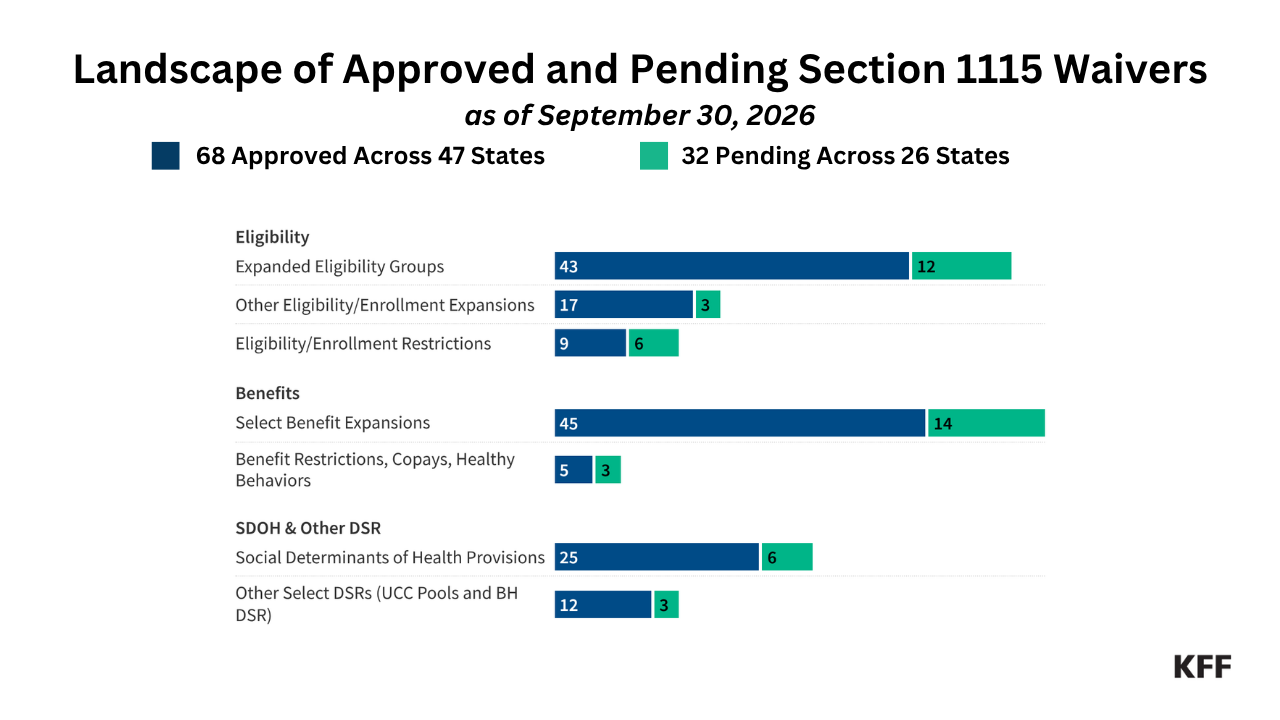
However, as of late 2026, the landscape of these waivers is undergoing a profound transformation. The transition between the Biden and Trump administrations has shifted the federal government’s priorities, moving away from broad social support frameworks toward a more restrictive, market-oriented approach. With nearly every state managing at least one active 1115 waiver, the stakes for millions of low-income Americans are significant. This report tracks the critical changes in eligibility, benefits, and delivery system reforms as federal guidance shifts and new legislative requirements take hold.
The Core Mechanics of 1115 Waivers
Section 1115 waivers function as the ultimate "regulatory bypass" for state health programs. While Medicaid is a joint federal-state partnership governed by federal law, the Secretary of the Department of Health and Human Services (HHS) holds the authority to approve "demonstrations" that test new approaches.
Historically, these waivers have been used to expand coverage to vulnerable populations or to integrate non-medical services into health care. Yet, they are inherently political tools. As administration priorities cycle between Democratic and Republican leadership, the criteria for what constitutes a "program objective" often flip, leading to a patchwork of approvals and rescissions that challenge state administrators and enrollees alike.
Chronology of Policy Shifts: 2023–2026
The current policy environment is defined by three distinct phases of administrative action:
- 2023–2024 (The Expansion Era): The Biden administration aggressively utilized 1115 authority to promote Health-Related Social Needs (HRSN) initiatives, focusing on housing, nutrition, and community reentry for the incarcerated. This period also saw the authorization of multi-year continuous eligibility for children to combat "churn."
- Early 2025 (The Retrenchment): Following the inauguration of the second Trump administration, the federal government began a systematic withdrawal from the previous administration’s progressive frameworks. In March 2025, the new leadership rescinded the HRSN guidance, signaling that future applications would face significantly higher hurdles for approval.
- Late 2025–2026 (The Statutory Tightening): The implementation of the 2025 tax and spending law fundamentally altered the playing field. By mandating work requirements for ACA expansion adults and setting strict timelines for retroactive eligibility, the federal government effectively curtailed the scope of discretionary 1115 authority.
Eligibility and Enrollment: The Push for Work Requirements
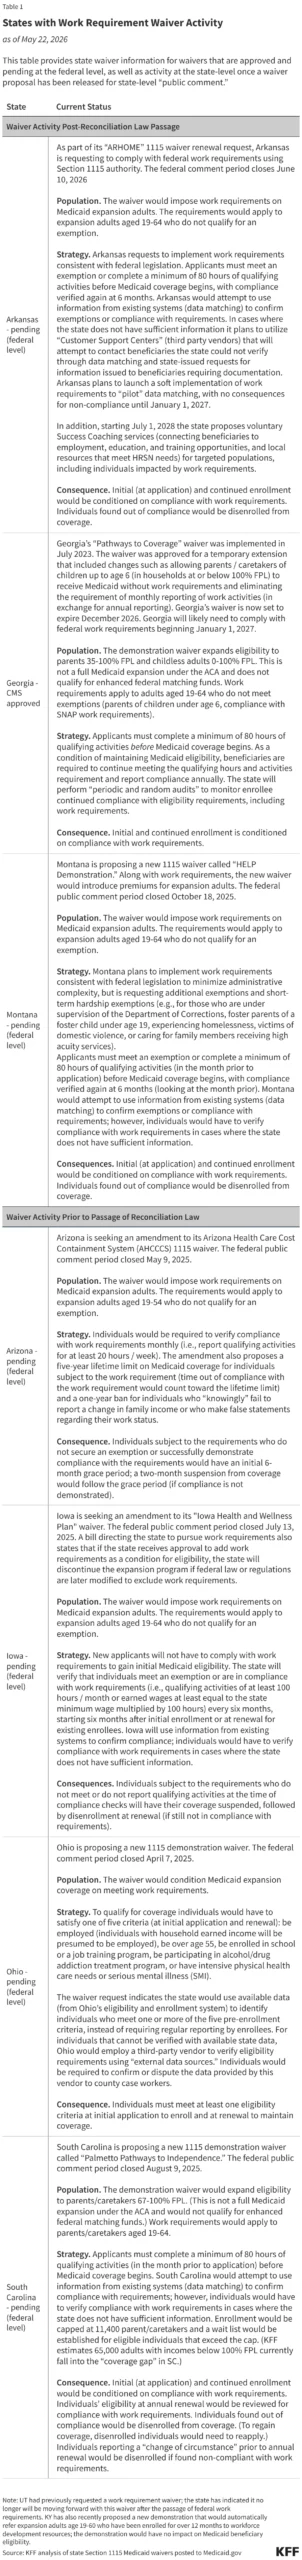
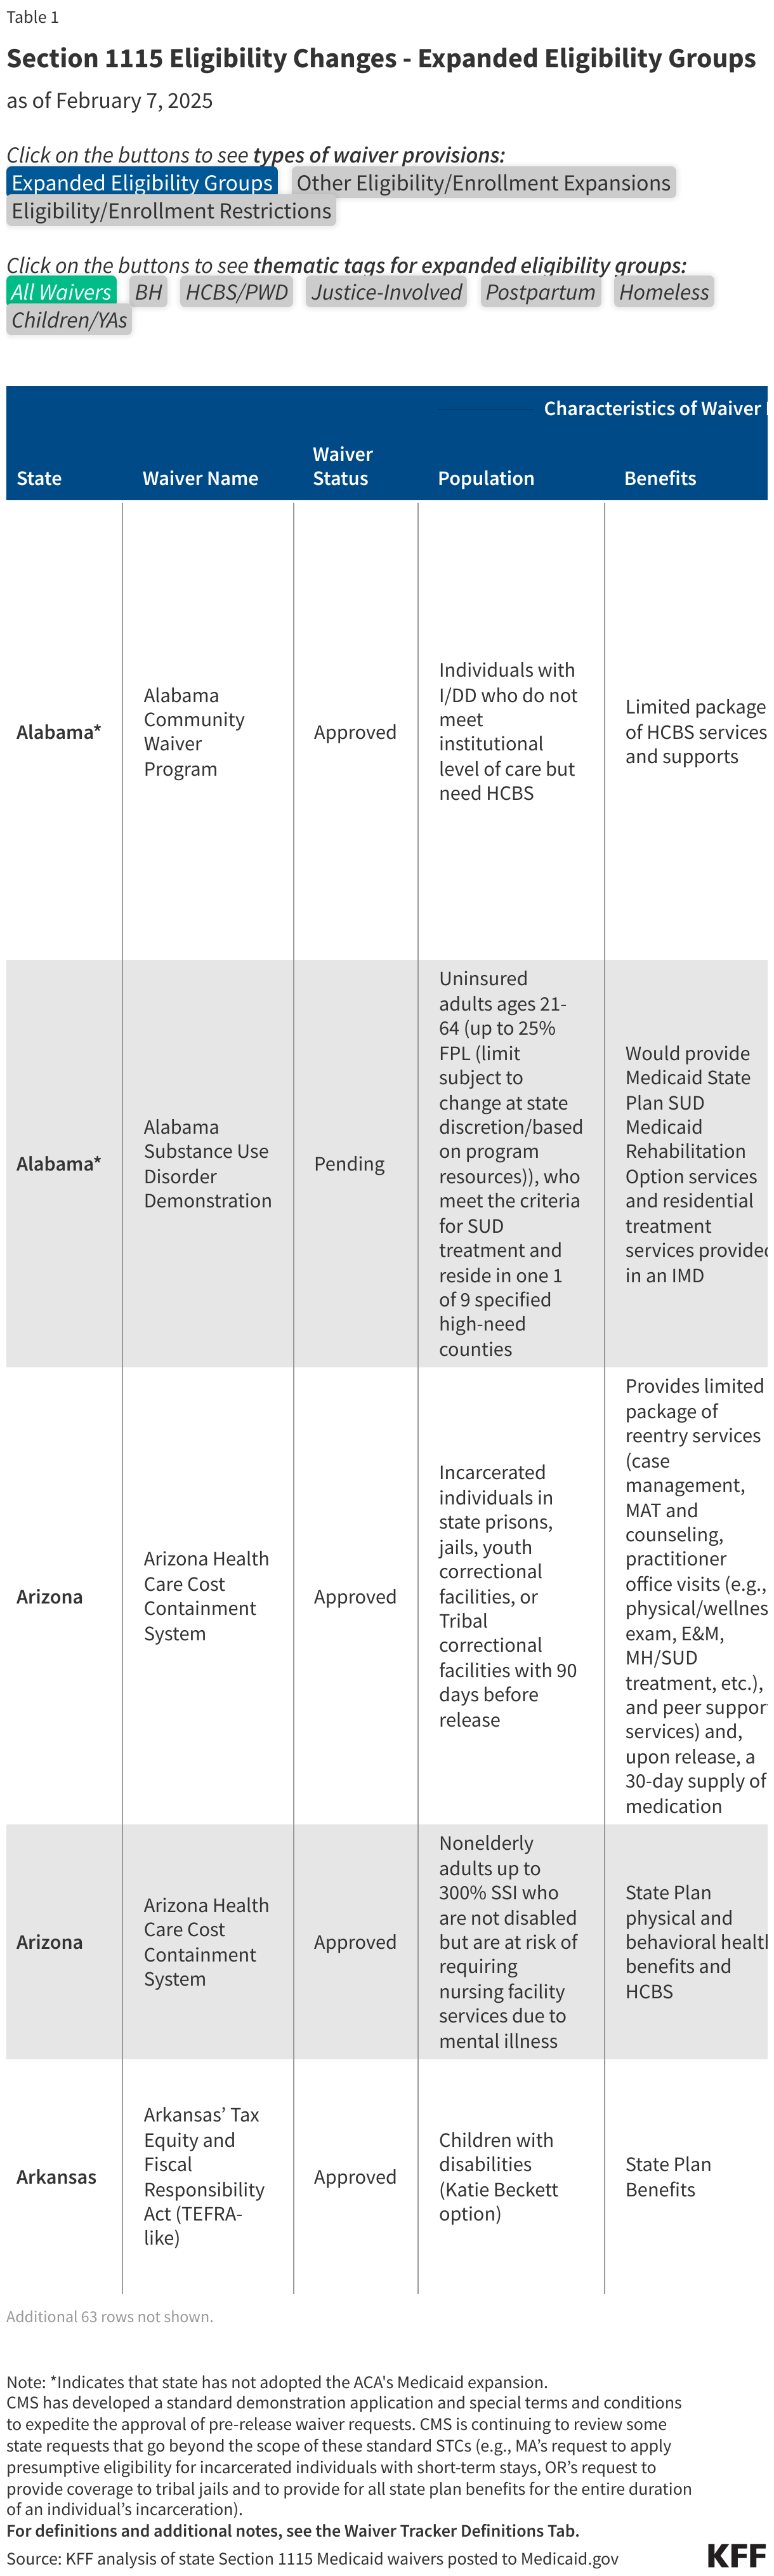
Perhaps the most contentious aspect of the current waiver landscape is the intersection of 1115 authority and federal work requirements. The 2025 reconciliation law mandates that, starting January 1, 2027, states must condition Medicaid eligibility for ACA expansion adults on work or community engagement.
The Shift to State Plan Amendments (SPAs)
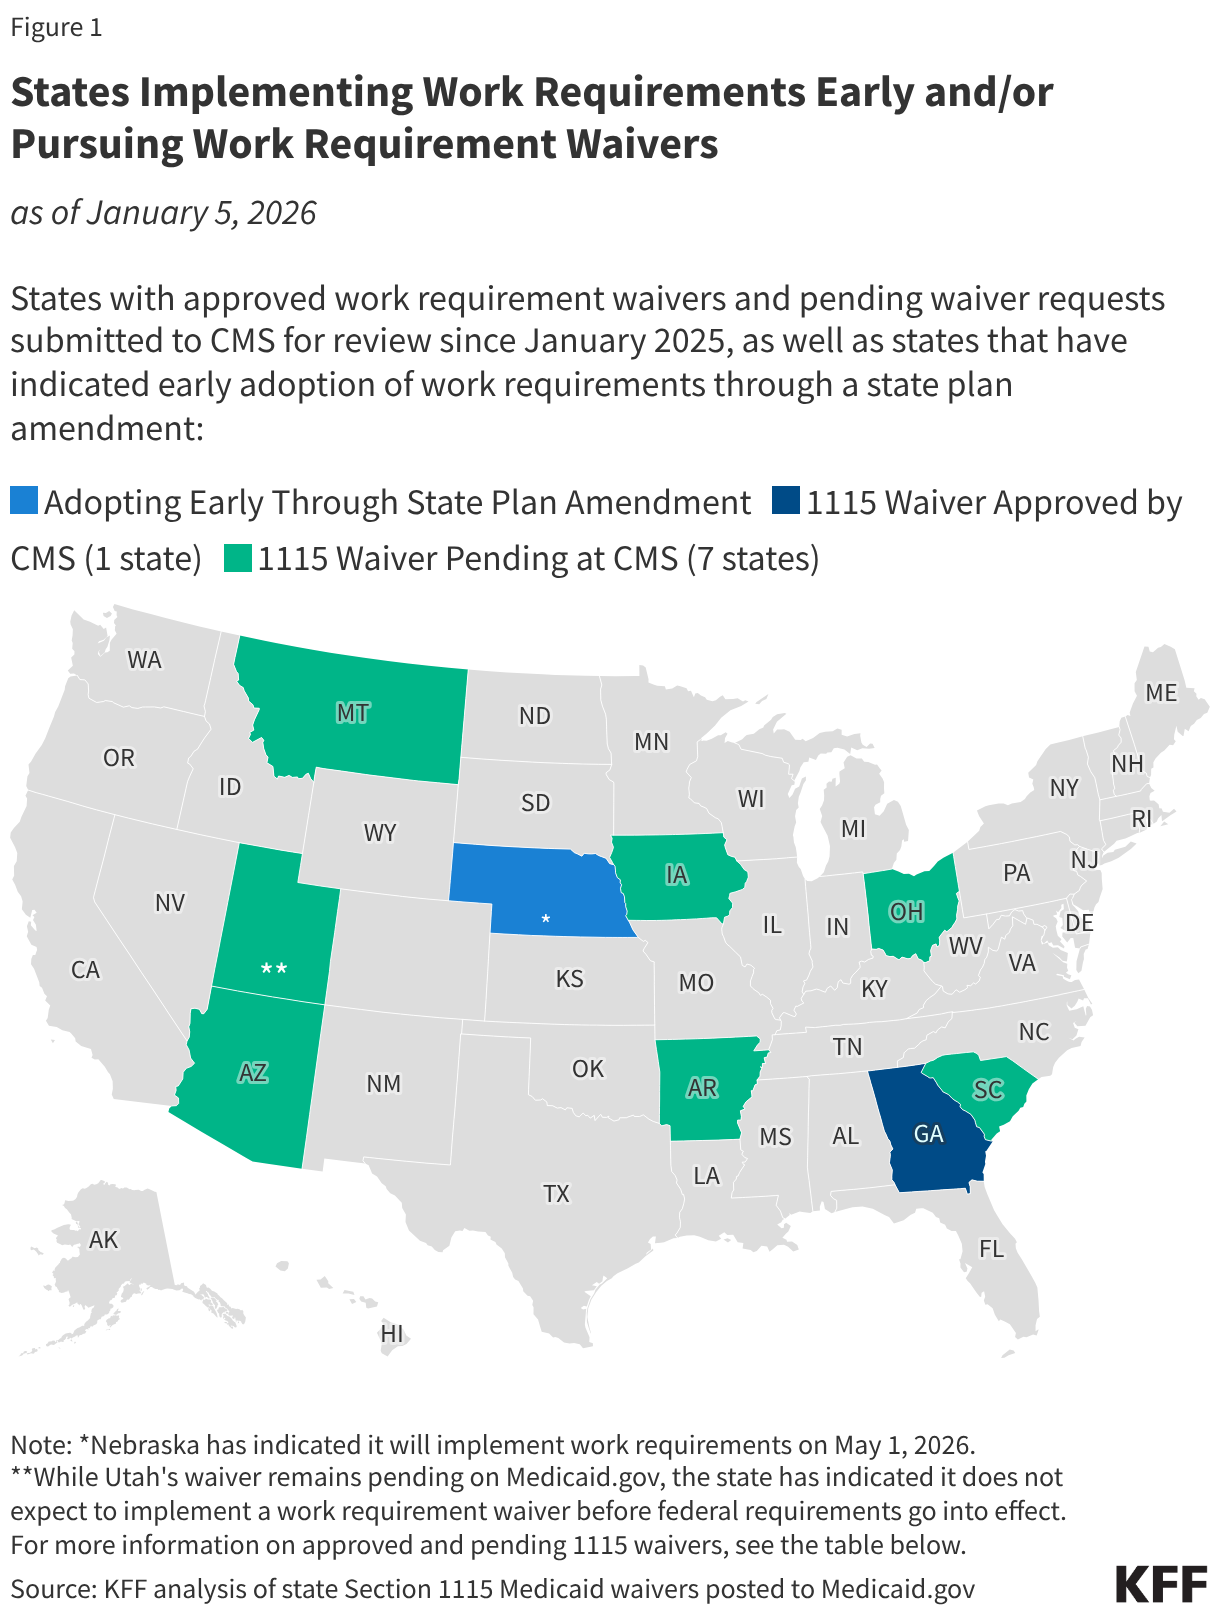
While states previously looked to 1115 waivers to implement these requirements, the new federal law has moved the goalposts. Nebraska, Montana, and Iowa have already moved to enforce these rules early via State Plan Amendments (SPAs). This maneuver bypasses the long-term, demonstration-based approval process of 1115 waivers in favor of permanent statutory adoption.
The Georgia Exception and Litigation
Georgia remains the primary outlier. Following prolonged litigation during the Biden years, the state successfully maintained a work requirement waiver. However, its authority is ticking clock: the waiver is set to expire on December 31, 2026, forcing the state to realign with the new federal mandates by the start of 2027.
Retroactive Eligibility and Premiums
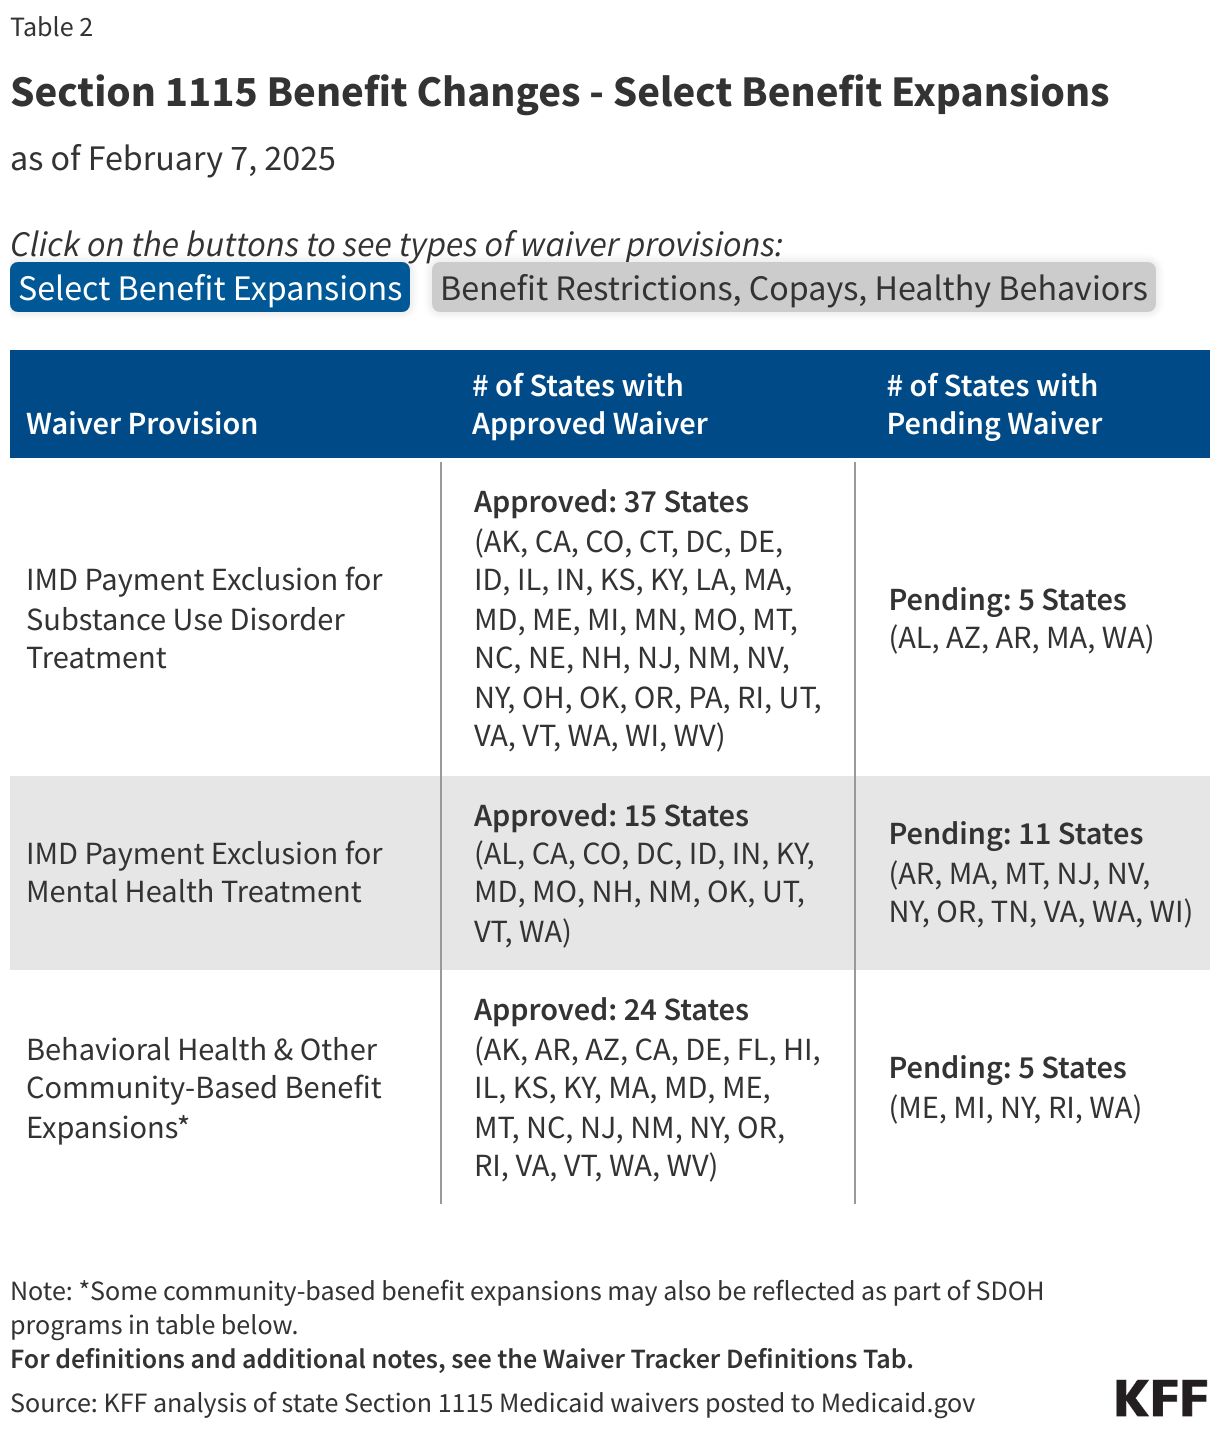
The 2025 law also tightens the rules on retroactive coverage—previously a three-month window—restricting it to one month for expansion enrollees and two months for traditional enrollees starting in 2027. Furthermore, by 2028, states will be prohibited from charging premiums to ACA expansion adults, a move that effectively nullifies many previous "conservative" waiver models (such as those in Michigan or Arkansas) that relied on cost-sharing to promote "personal responsibility."
Benefit Changes and Social Determinants of Health (SDOH)
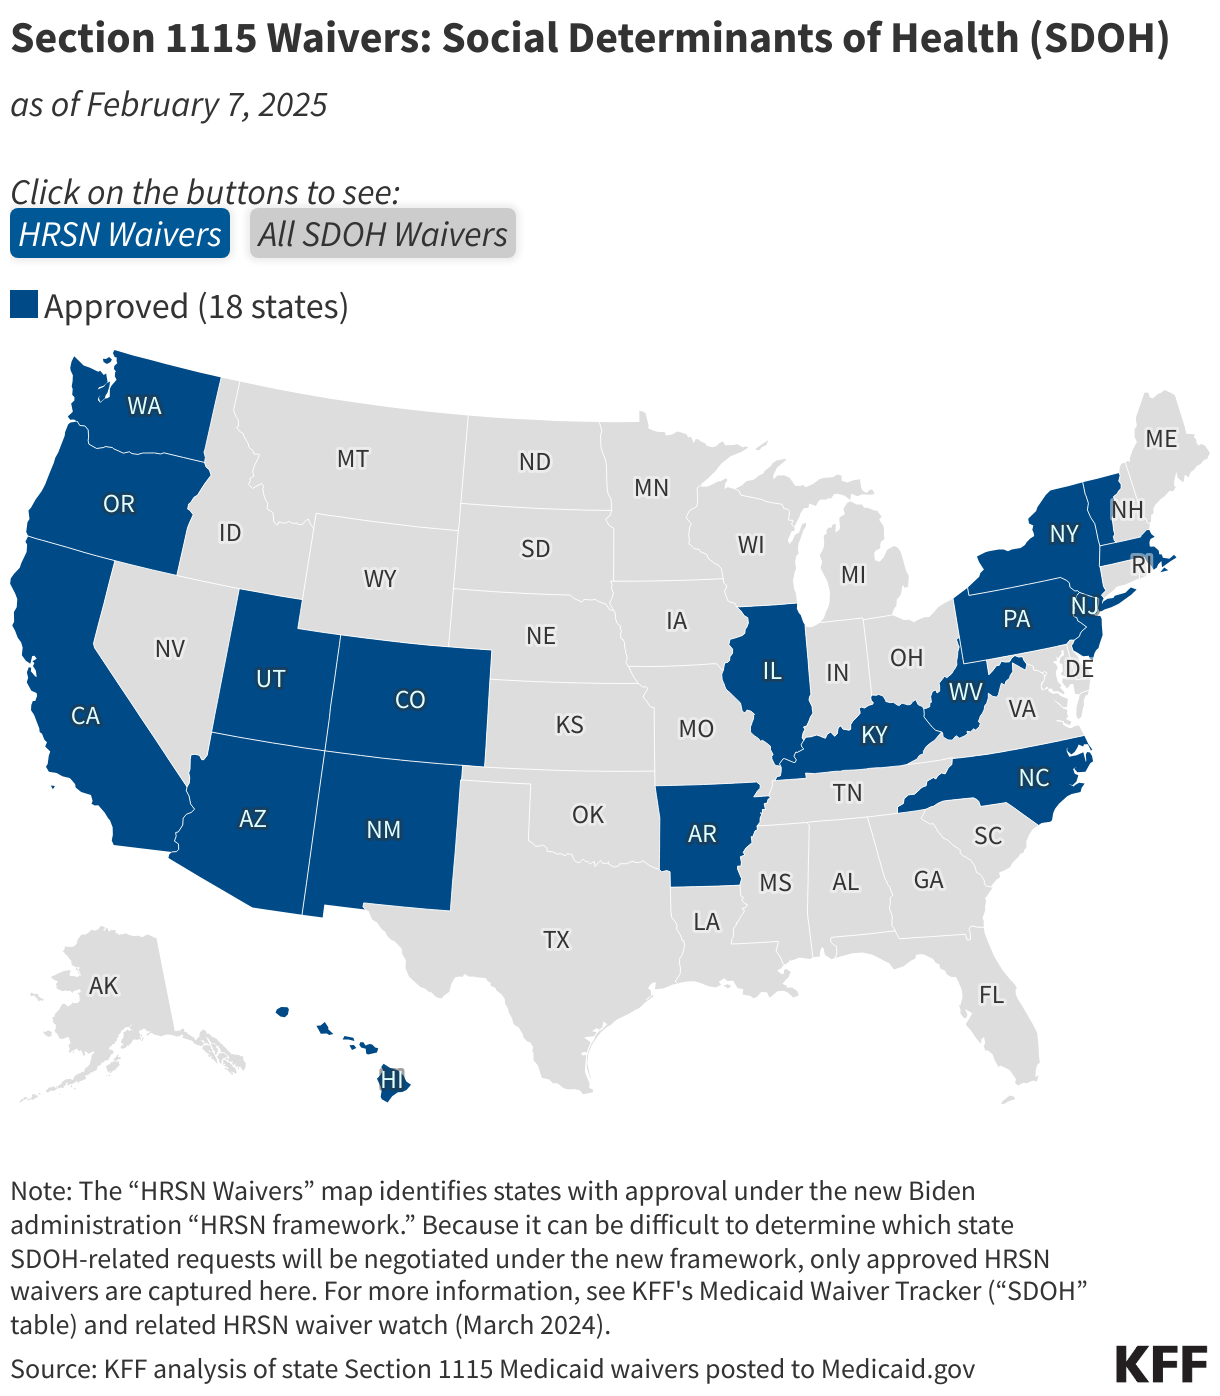
Before the policy shift of 2025, several states gained approval to address the "whole-person" health needs of their enrollees. These HRSN waivers allowed states to pay for services like rent assistance, medically tailored meals, and air conditioners for asthmatic patients.

The "Case-by-Case" Reality
Under the current administration, the formal framework for HRSN has been dismantled. While existing approvals remain in effect—avoiding a sudden collapse of services—the path forward for new states is narrow. CMS has indicated that it will evaluate HRSN requests on a "case-by-case" basis, effectively ending the era of broad, standardized approval for non-medical benefits.
The End of DSHP and Workforce Supports
In April 2025, the federal government moved to phase out funding for "Designated State Health Programs" (DSHP), which many states used to draw down federal matching funds for state-only health initiatives. Similarly, initiatives designed to bolster the Medicaid workforce in behavioral health and primary care are being systematically phased out, shifting the burden of workforce stabilization back to the states.
Multi-Year Continuous Eligibility: A Fading Innovation
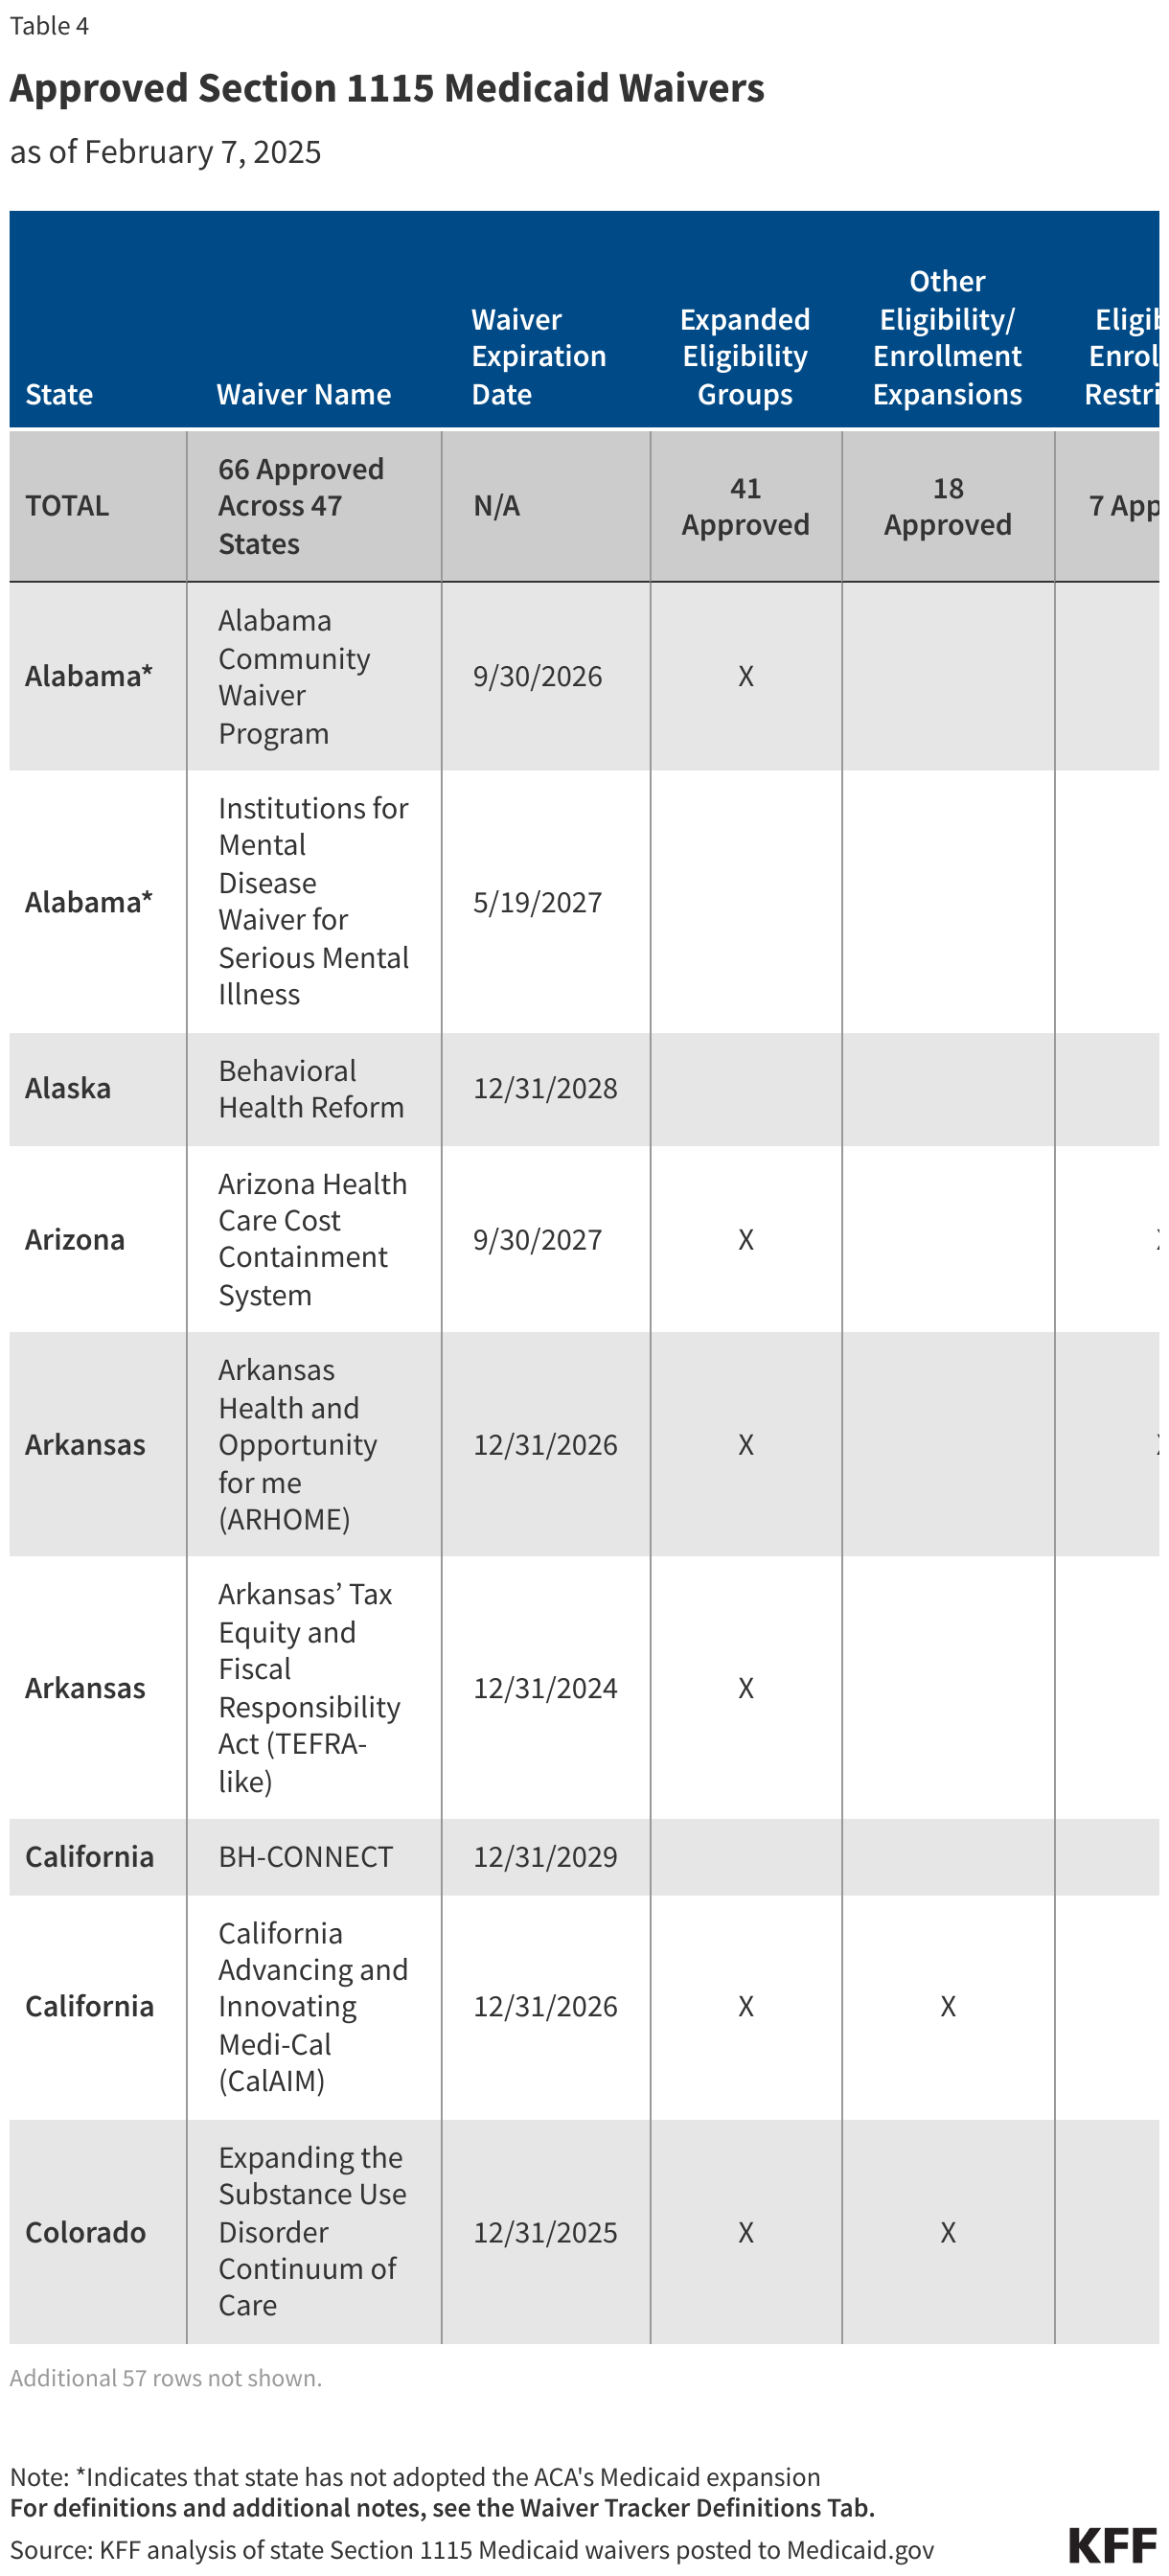
One of the most widely lauded reforms of the early 2020s was the implementation of multi-year continuous eligibility for children. By ensuring that a child’s coverage would not be interrupted by minor fluctuations in family income, states successfully reduced the "churn" that leaves millions of children temporarily uninsured.
However, in July 2025, the administration issued guidance stating that it would no longer approve new or extended continuous eligibility waivers. This decision marks a significant philosophical departure, prioritizing the periodic verification of eligibility over the goal of administrative simplicity and continuous health coverage for minors.
Official Responses and Stakeholder Perspectives
The reaction from state health departments has been mixed. Proponents of the Trump administration’s policies argue that these changes restore fiscal discipline and prevent the "mission creep" of Medicaid into social services that are better handled by other agencies.
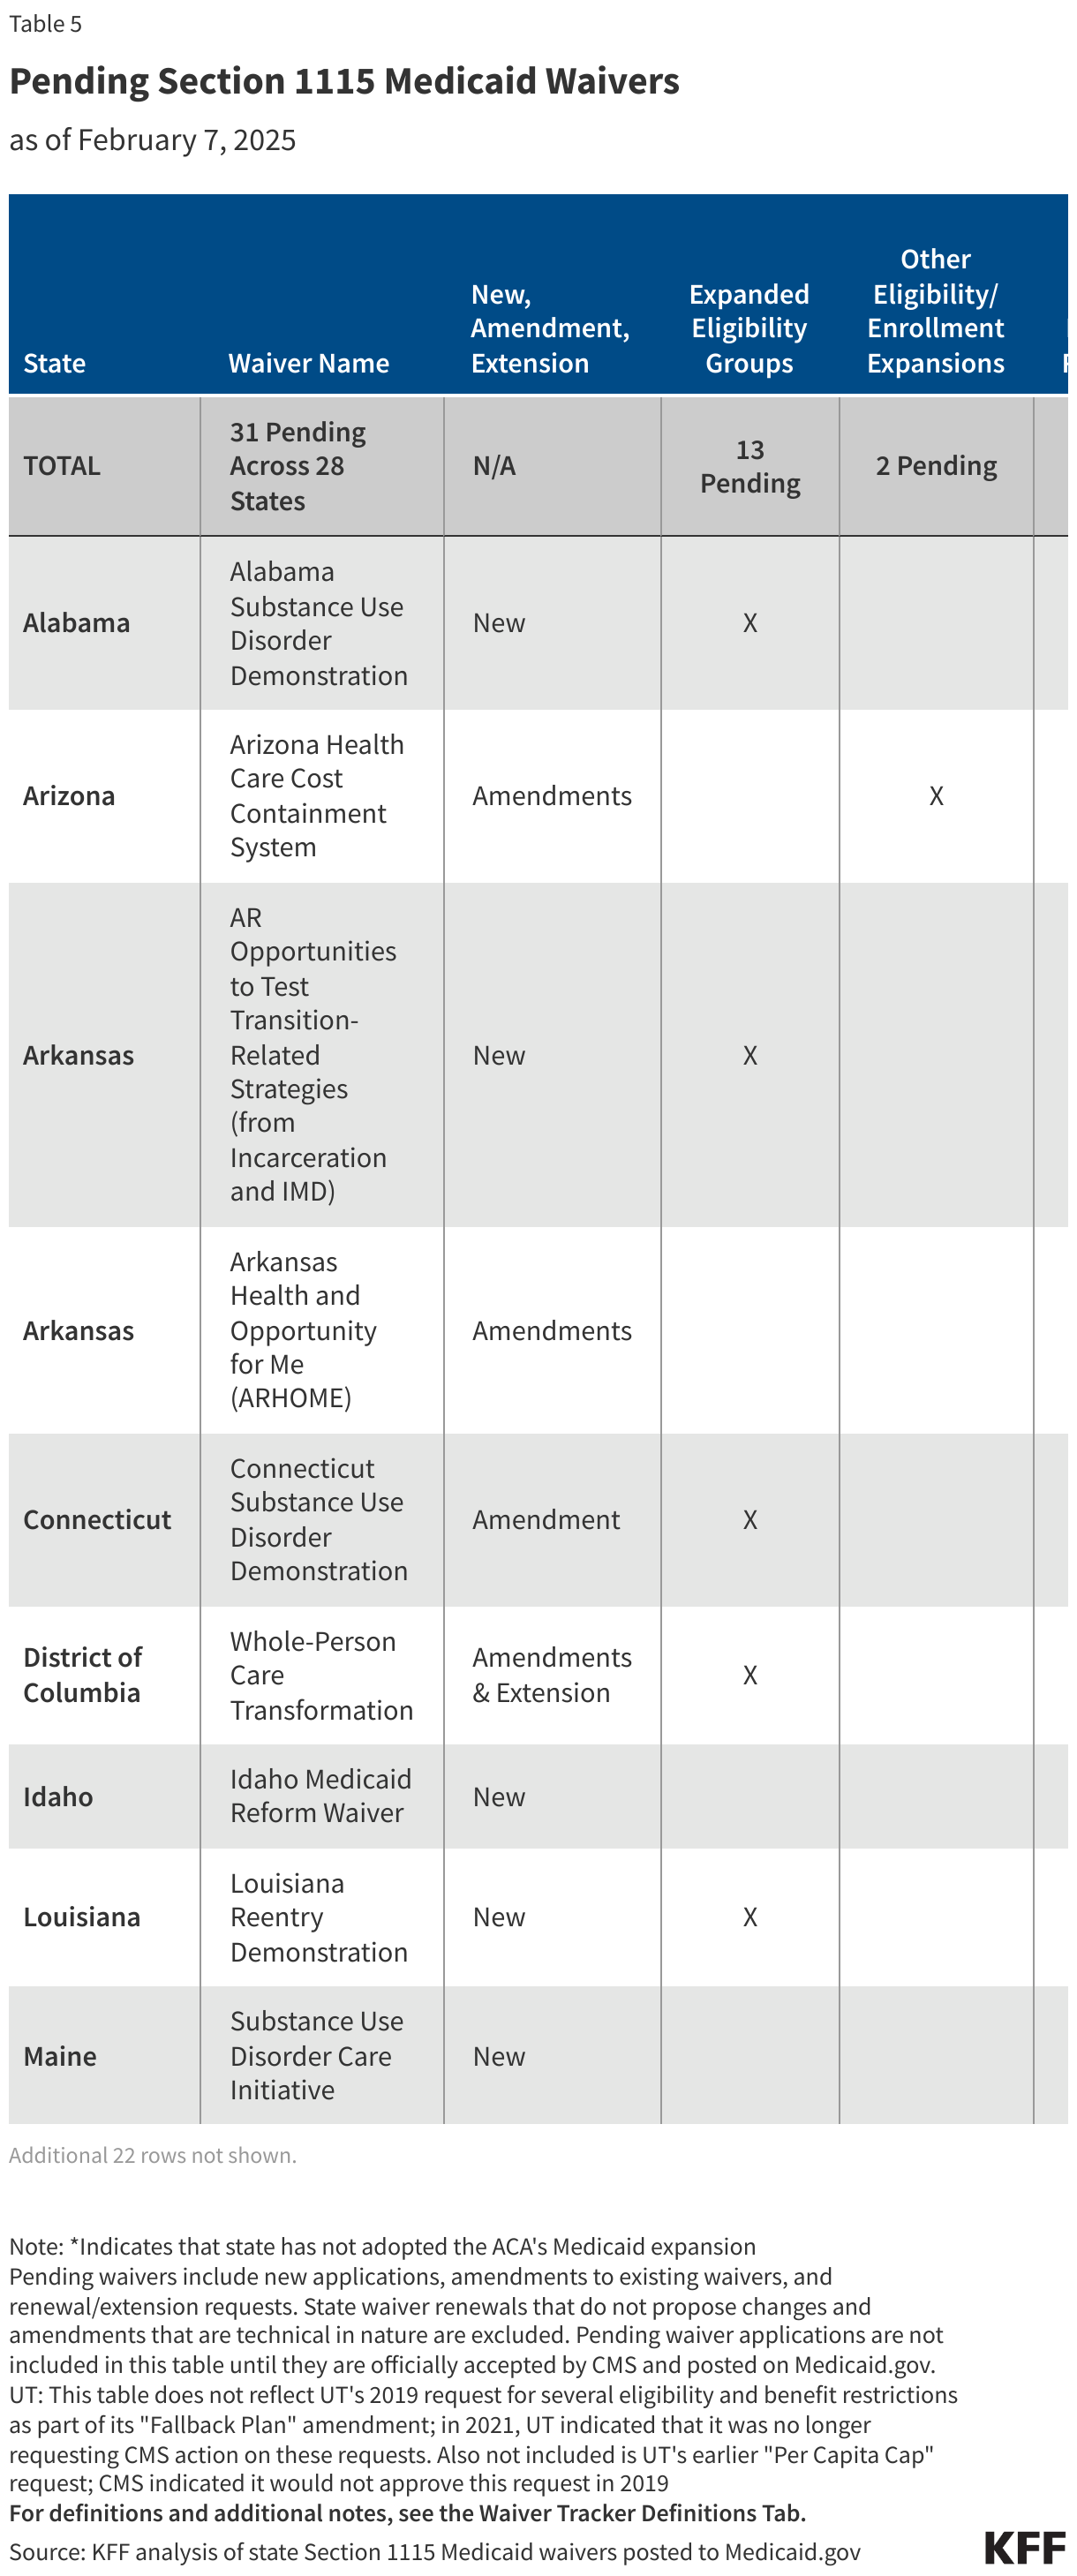
Conversely, health policy analysts at organizations like KFF have raised alarms regarding the potential for increased disenrollment and reduced access to care. The legal community is also closely watching the situation; as seen in the recent U.S. District Court decision in Indiana—where a judge vacated the "Healthy Indiana Plan 2.0" premium and eligibility restrictions—the courts continue to play a decisive role in defining the limits of executive authority over the Medicaid program.
Broader Implications: A Fragmented Future
The current state of Section 1115 waivers suggests a future defined by fragmentation. We are moving away from a national standard of care toward a state-specific model where access to preventative services, social supports, and even basic eligibility is heavily dependent on state-level political alignment.
1. Fiscal Implications
States that relied on DSHP funding or innovative waivers to subsidize their budgets are now facing a "fiscal cliff." As federal support for delivery system reforms wanes, state legislatures must either find new revenue streams or scale back programs that were once supported by the federal government.

2. The Patient Experience
For the average enrollee, the complexity of these waivers is becoming increasingly difficult to navigate. With shifting rules on work requirements, premium payments, and retroactive coverage, the administrative burden on families is likely to grow. The risk is that as these programs become more complex, the most vulnerable populations—those with the least access to information—will be the most likely to lose coverage due to administrative hurdles rather than changes in their financial status.
3. The Future of Medicaid
The 1115 waiver, originally intended to be a tool for innovation, has become a reflection of the deep ideological divide in American governance. The current trend toward restricting the scope of the program suggests that the next few years will see a retreat from the "holistic" view of health that dominated the early 2020s.
As we approach 2027, the focus will shift from what a state can do to improve health outcomes to how a state can comply with the rigorous, mandatory requirements set forth by federal law. The "demonstration" aspect of 1115 waivers is being subordinated to the "regulatory" aspect, likely leading to a more uniform, yet significantly more restricted, national Medicaid landscape.
For stakeholders, the directive is clear: the era of federal encouragement for expansive social-health integration is over. The focus must now pivot to sustaining existing successes within a landscape that is increasingly skeptical of non-traditional Medicaid expenditure.
About the Author