In a move that has fundamentally altered the landscape of American public health policy, the 2025 reconciliation law—famously dubbed by President Trump as the “One Big Beautiful Bill”—has set into motion the most significant transformation of the Medicaid program since its inception. Signed into law on July 4, 2025, the legislation mandates that 44 states, including the District of Columbia, implement strict work requirements for specific cohorts of Medicaid enrollees.
This policy pivot marks a sharp departure from the previous decade of expansion and creates a complex administrative timeline for states, providers, and millions of enrollees. As January 1, 2027, approaches, the healthcare sector finds itself in a race against time to overhaul operational infrastructure, navigate new federal guidance, and prepare for a seismic shift in coverage eligibility.
The Chronology of Change: From Legislative Signing to Implementation
The timeline for this mandate is aggressive, leaving states with a narrow window to reconcile their existing programs with the new federal mandates.
- July 4, 2025: President Trump signs the reconciliation law, officially codifying work requirements into the Medicaid framework.
- June 2026: The Centers for Medicare and Medicaid Services (CMS) releases the definitive list of impacted states and Section 1115 waiver programs.
- Late 2026: States are expected to finalize operational policy, complete system upgrades, and launch mandatory outreach programs for enrollees.
- January 1, 2027: The federal deadline for full implementation of work requirements across the 44 affected jurisdictions.
This timeline has been a point of contention among state administrators. While the legislative intent is to incentivize workforce participation, state health departments argue that the complexity of tracking employment data, verifying hours, and managing exemptions requires a multi-year lead time that the current schedule does not fully accommodate.
Supporting Data: Understanding the Scope of the Mandate
The 2025 law specifically targets the Affordable Care Act (ACA) Medicaid expansion population—adults with incomes up to 138% of the Federal Poverty Level (FPL)—and select enrollees within Section 1115 waiver programs.
The Expansion Landscape
Currently, 41 states and the District of Columbia have expanded Medicaid under the ACA. This group covers millions of low-income adults, with an individual income threshold of $21,597 for the 2025 fiscal year. Under the new law, this entire demographic is subject to the work requirement mandate unless they qualify for specific federal exemptions.
The 1115 Waiver Impact
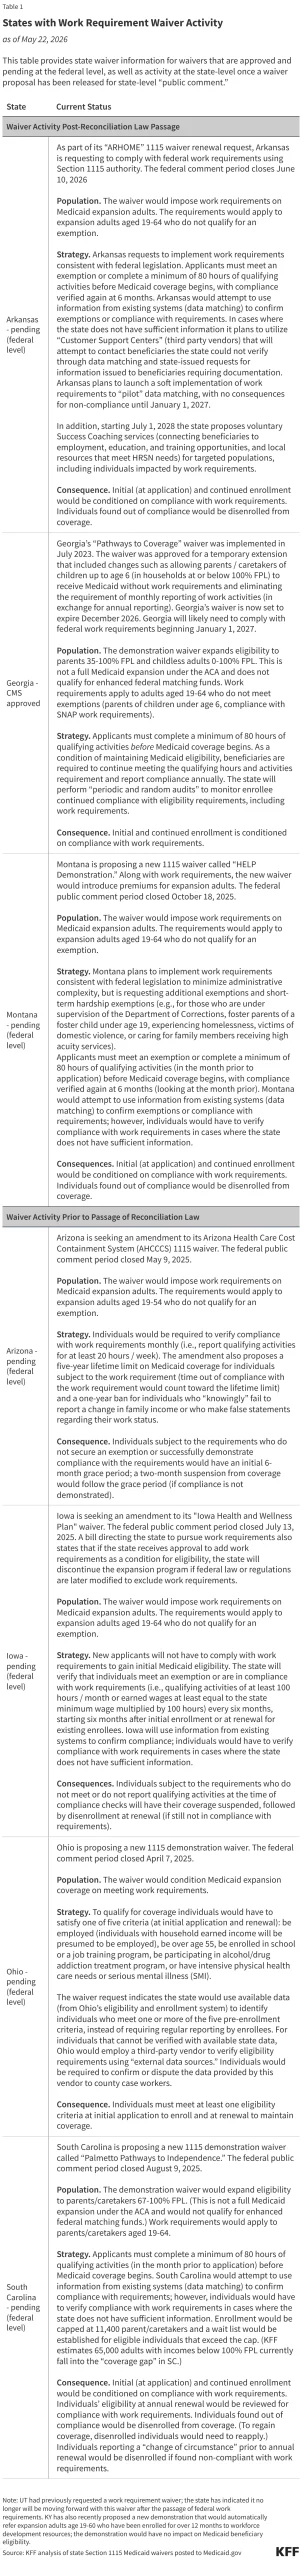
Beyond the ACA expansion groups, the legislation casts a wider net by including specific enrollees in 1115 waiver programs. According to the June 2026 CMS report, these requirements extend to:
- Non-Expansion States: Georgia, Tennessee, and Wisconsin.
- Expansion States: Hawaii, Massachusetts, New York, Oregon, and Utah.
The inclusion of both expansion and non-expansion states in this list highlights the federal government’s intent to apply a uniform standard of workforce engagement across the national Medicaid program, regardless of a state’s specific approach to the ACA expansion.
Operational and Administrative Implications
For state governments, the mandate is not merely a policy change; it is an administrative overhaul. To comply with the law, states must address four critical pillars of operation:
1. System Upgrades and Infrastructure
State Medicaid Management Information Systems (MMIS) were largely designed to process eligibility based on income and household size, not continuous employment verification. Upgrading these systems to handle real-time employment data feeds from state labor departments or self-reporting portals is a monumental task.
2. Outreach and Education
A significant challenge lies in the "churn" associated with Medicaid enrollment. Many enrollees experience fluctuating income or employment status. States are tasked with creating robust education strategies to ensure that enrollees understand how to document their work hours, report exemptions (such as disability, caregiving, or student status), and avoid unnecessary loss of coverage.
3. Staffing and Training
The administrative burden of processing exemptions and handling appeals will require a significant increase in headcount. Caseworkers must be trained to navigate the nuances of the new rules to prevent wrongful disenrollments—a recurring legal pitfall in previous iterations of state-level work requirement experiments.
4. Policy Decisions
States retain some discretion in how they define "work," the number of hours required per week, and the verification methods used. These decisions are currently being debated in state houses across the country, as governors weigh the political pressure to implement the law against the economic reality of their state’s labor market.
Official Responses and Political Debate
The response to the 2025 reconciliation law has been deeply polarized. Proponents of the legislation, including members of the Trump administration, argue that Medicaid was always intended as a temporary safety net, not a permanent entitlement for able-bodied adults. "Work provides dignity, stability, and a path toward self-sufficiency," a White House spokesperson noted shortly after the signing. "By incentivizing employment, we are strengthening both the individual and the economy."
Conversely, healthcare advocacy groups and civil rights organizations have expressed grave concerns. Many argue that the requirements will disproportionately impact marginalized populations, those with undiagnosed health conditions, and rural residents in areas with limited job opportunities.
"The administrative hurdles created by this law are designed to act as a barrier, not a bridge," said a representative from a leading national health policy think tank. "We are likely to see a significant drop in enrollment, not because people have found jobs, but because they have been caught in a bureaucratic trap of reporting requirements."
The Path Forward: Monitoring Implementation
As the country moves toward the January 2027 deadline, the role of CMS will be pivotal. The agency is expected to issue a series of guidance documents to assist states in navigating the transition. These documents will likely focus on:
- Standardized Exemption Criteria: Establishing a federal baseline for what constitutes a "good cause" exemption to prevent extreme variance between states.
- Reporting Mechanisms: Utilizing digital platforms to minimize the burden on the enrollee and the state.
- Monitoring and Evaluation: Tracking the impact of these requirements on health outcomes and employment rates to provide an evidence-based review of the policy’s success.
Tracking the Data
This publication will remain a dedicated resource for stakeholders. We will continue to track state-by-state policy developments, updates from the Centers for Medicare and Medicaid Services, and real-time data regarding the implementation of the law.
The 2025 reconciliation law represents a fundamental shift in the social contract between the federal government and the public. Whether this policy results in the intended surge in workforce participation or a contraction in essential healthcare access remains the most critical question facing the U.S. healthcare system. As implementation begins in earnest, the focus must remain on the balance between administrative accountability and the mission-critical objective of providing care to the nation’s most vulnerable.
Disclaimer: This article is intended for informational purposes and reflects the current status of the 2025 reconciliation law as of the latest federal disclosures. Further updates will be provided as CMS releases additional guidance.
About the Author