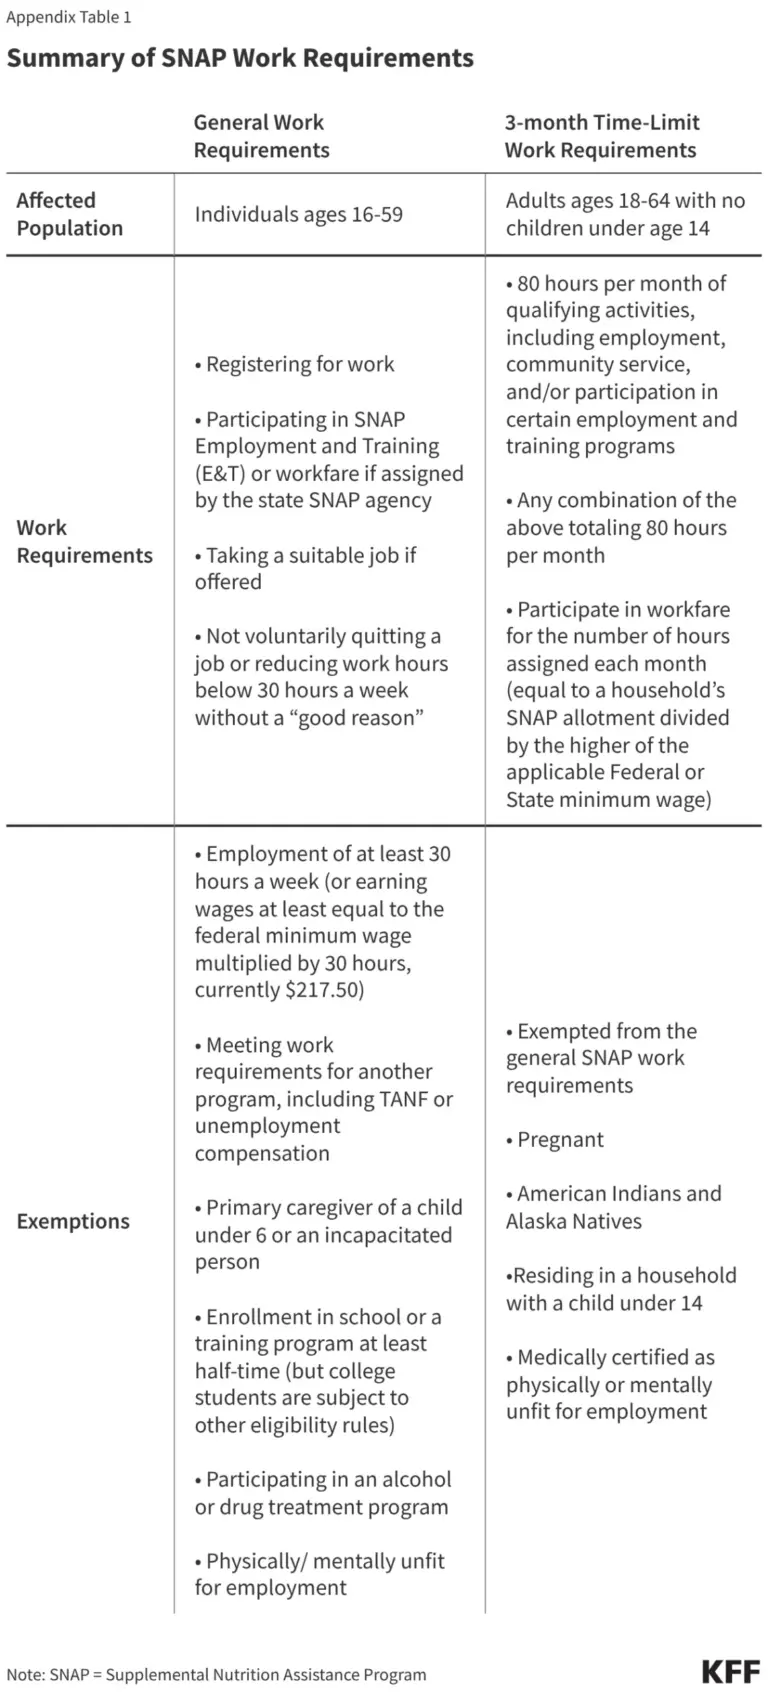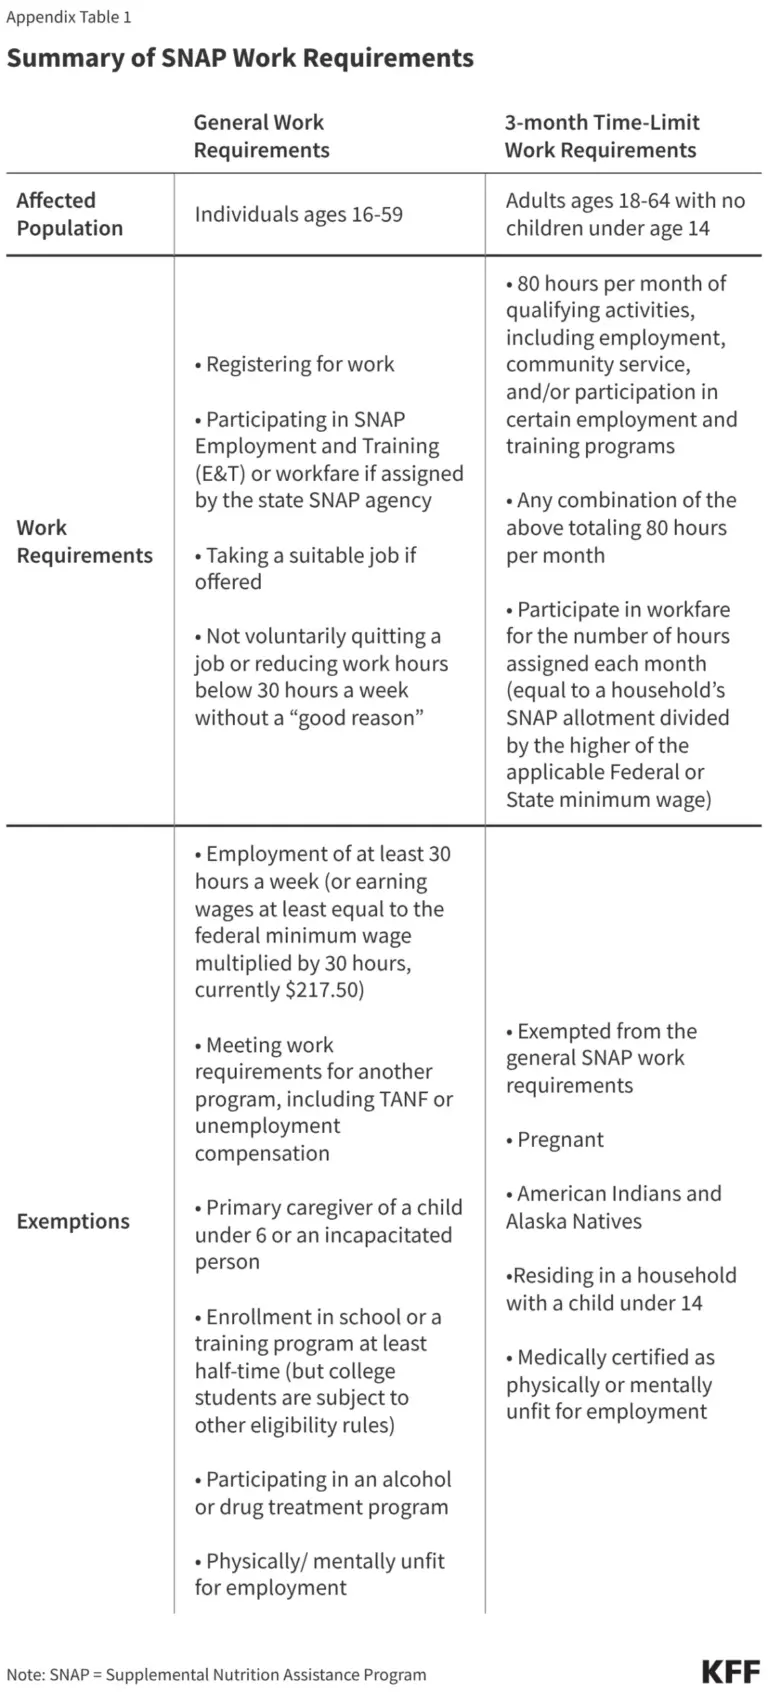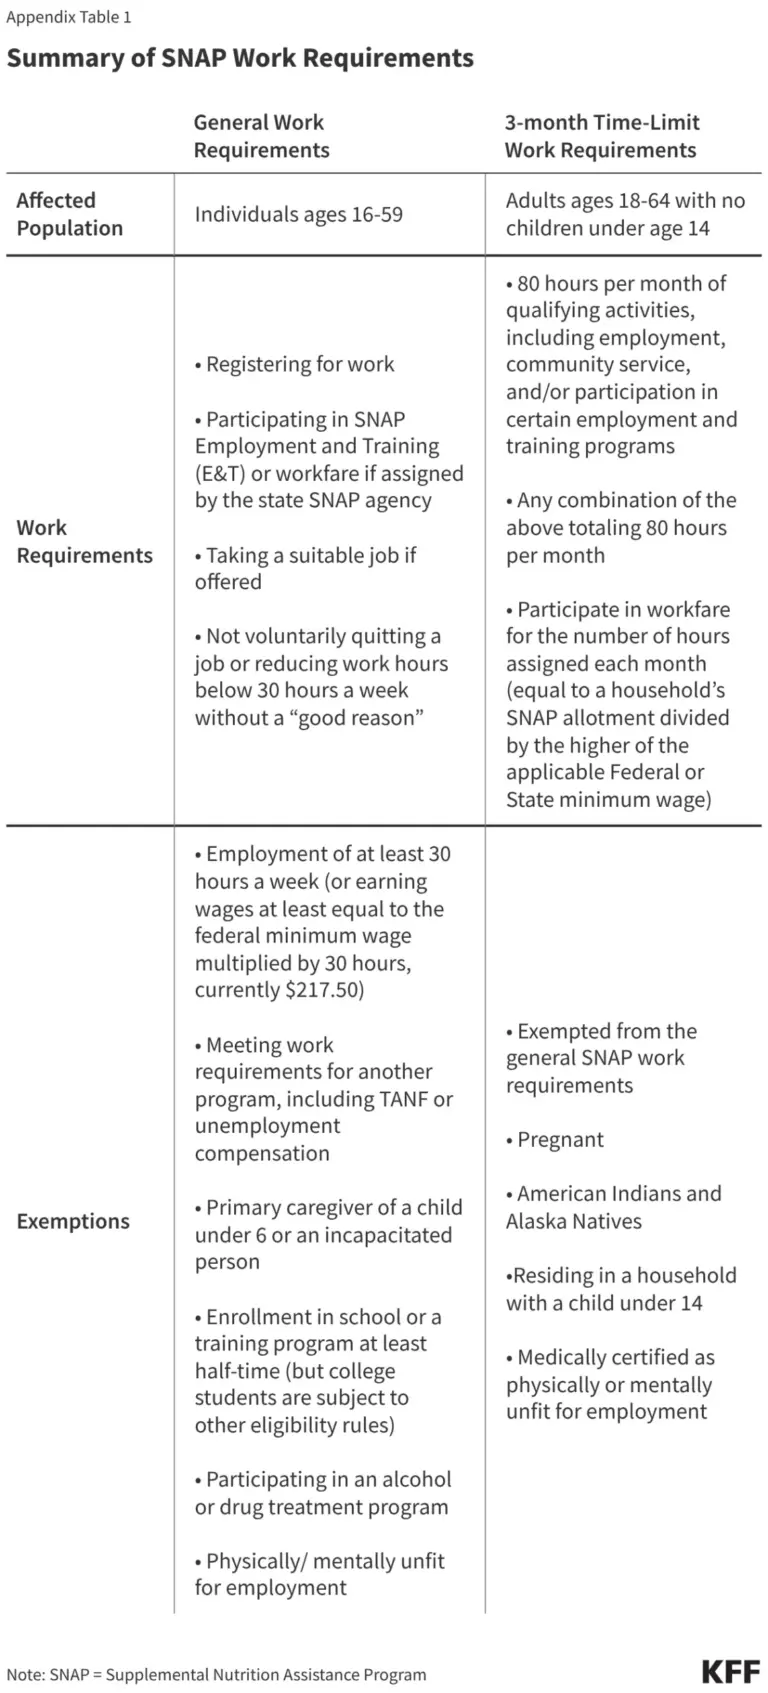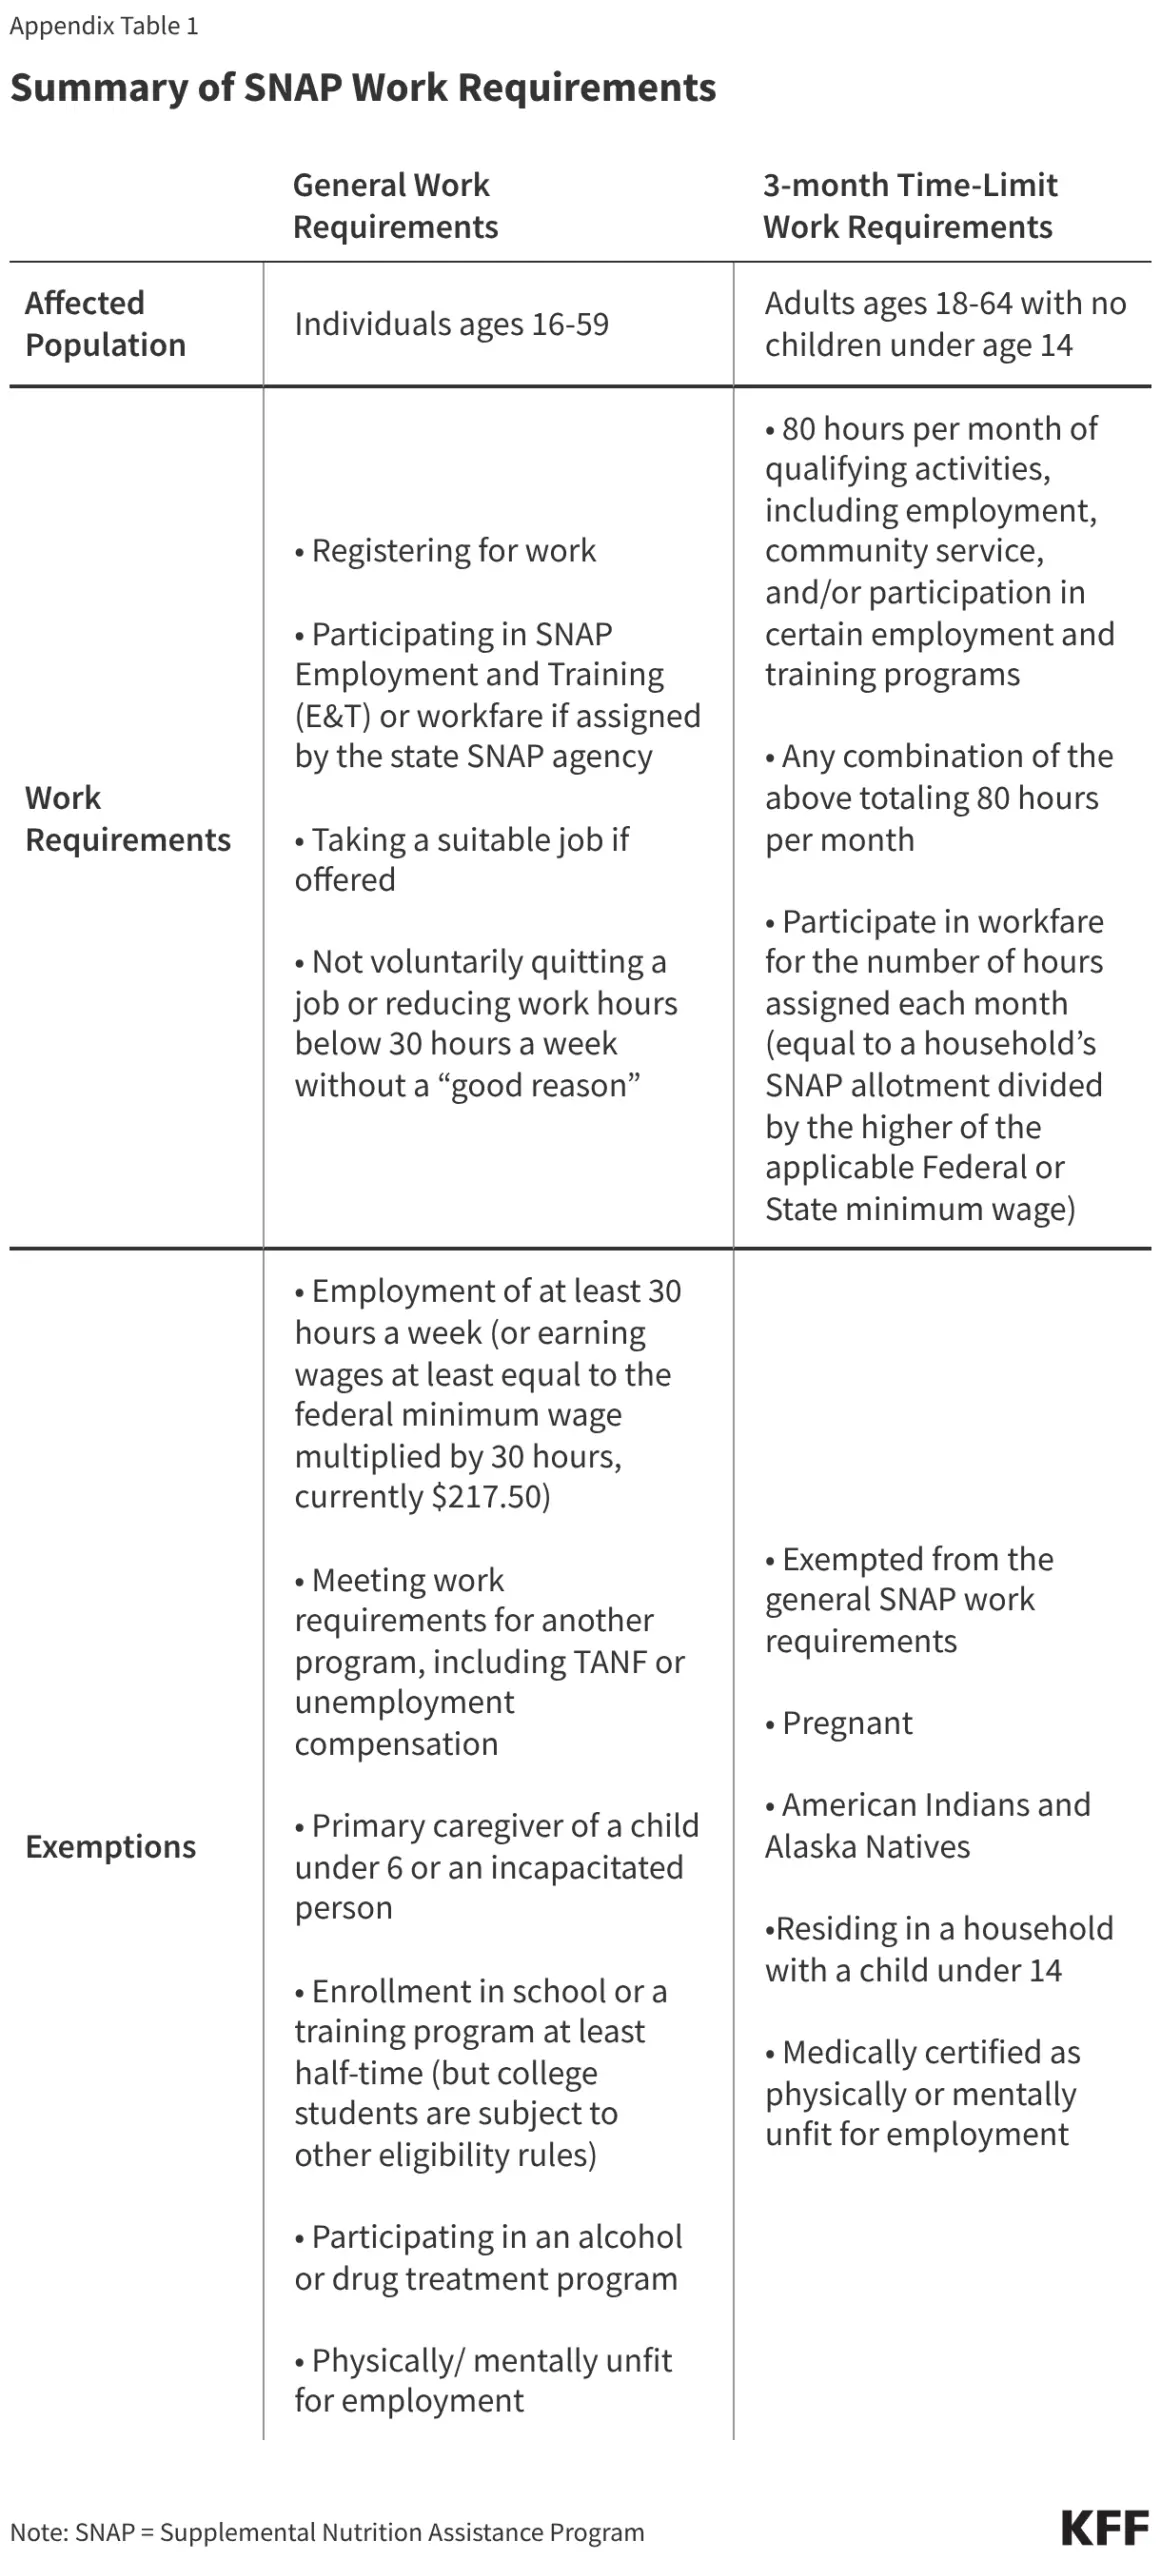
As the United States approaches a significant transformation in its social safety net, the intersection of food assistance and healthcare coverage is under intense scrutiny. By January 1, 2027, 44 states will be mandated to implement work requirements for Medicaid enrollees within the Affordable Care Act (ACA) expansion group—a policy shift that mirrors long-standing practices in the Supplemental Nutrition Assistance Program (SNAP).
This transition marks a pivotal moment in federal policy, forcing state agencies to grapple with complex administrative hurdles: how to accurately and equitably verify the "medically frail" status of individuals to ensure those unable to work are not unfairly stripped of vital benefits.
The Intersection of SNAP and Medicaid Policy
For decades, SNAP has served as the primary federal bulwark against food insecurity, predicated on the condition that able-bodied adults meet specific work requirements. Starting in 2027, the federal government will extend a similar framework to Medicaid. While the policy aims to increase labor force participation, it introduces the critical administrative challenge of identifying and exempting individuals who are "medically frail."
To be exempt from Medicaid work requirements under the new law, an individual must possess a qualifying medical condition and provide evidence that this condition impairs their ability to meet those requirements. The Centers for Medicare & Medicaid Services (CMS) has provided a framework for verification, yet the lack of a standardized federal mandate leaves the actual implementation process largely to state discretion, creating a patchwork of potential outcomes for millions of Americans.
A Chronology of Implementation
The timeline for these changes is aggressive, forcing states into a race against the clock to update their eligibility infrastructure:
- Pre-2027: States continue to manage SNAP work requirements with significant local autonomy, using a mix of eligibility worker interviews and intermittent provider documentation.
- January 1, 2027: The federal mandate for Medicaid work requirements takes effect in 44 states. States begin the transition to automated verification systems for medical frailty.
- October 2027: New federal rules regarding SNAP payment error rates (PER) take effect, increasing the financial liability for states that fail to meet strict administrative accuracy standards.
- January 1, 2028: The grace period for self-attestation in Medicaid expires. Moving forward, states may only accept self-reported medical frailty status once per enrollment period, necessitating more rigorous (and often burdensome) documentation for subsequent renewals.
How States Have Historically Managed SNAP Exemptions
To understand the challenges ahead for Medicaid, one must look at the historical precedent of SNAP. Federal regulations grant states broad flexibility in defining "physically or mentally unfit for employment." This lack of a rigid, uniform definition has led to significant variance in how states protect vulnerable populations.
The Role of Eligibility Workers
Historically, the SNAP application process has relied heavily on the professional judgment of eligibility workers. Through in-person or phone interviews, these workers screen for exemptions. In many jurisdictions, visual observations—such as noting the presence of medical equipment—have served as a legitimate basis for granting an exemption. While this human-centric approach can be more responsive to individual circumstances, it is also inherently subjective.
The Documentation Dilemma
When an exemption is not "obvious," states turn to medical professionals. However, the documentation required by these providers is inconsistent. Some states require standardized forms that demand specific clinical diagnoses, while others accept informal letters or simple phone calls. This inconsistency often places an undue burden on medical providers, who may lack the guidance necessary to assess "fitness for work" from an administrative, rather than clinical, perspective.
The Financial Pressure: Payment Error Rates (PER)
A critical driver of current administrative changes is the shift in fiscal accountability. Under the new reconciliation law, states are now financially responsible for a portion of SNAP benefit costs if their payment error rate exceeds 6%.
This has triggered a "defensive administration" trend. For instance, Arizona has recently pivoted to require rigorous, proactive documentation for all exemption claims, effectively ending its previous practice of relying on client statements. This shift illustrates a broader tension: the desire for program integrity versus the administrative burden placed on low-income households. If a state fears the financial penalty of an overpayment, it is incentivized to create bureaucratic barriers that may inadvertently discourage eligible, vulnerable people from applying for or maintaining their benefits.

Medicaid’s Tiered Verification Approach
Unlike SNAP, the Medicaid program has a distinct advantage: access to historical claims and encounter data. CMS has introduced a tiered approach for verifying medical frailty:
- Tier 1: Automated verification using claims data from the preceding 12 months.
- Tier 2: A combination of claims, encounter, and other administrative data.
- Tier 3: A manual, individualized review for cases where data is insufficient or absent.
While this system is designed to reduce the need for manual paperwork, it is not foolproof. New enrollees or those who have not utilized medical services in the past year will inevitably fall into the Tier 3 category, necessitating manual intervention. Furthermore, if providers fail to use standardized billing codes for conditions, even a patient with a severe, chronic illness could fail the automated Tier 1 or Tier 2 verification.
Implications for Patients and Providers
The shift toward more rigorous, data-driven, and documentation-heavy verification processes carries profound implications for the American social safety net.
The Erosion of Self-Attestation
The most significant impact of the 2028 rules is the limitation on self-attestation. By restricting the number of times an individual can attest to their own medical frailty, the government is essentially shifting the burden of proof entirely onto the healthcare system. For patients with complex, fluctuating conditions, this means repeated trips to doctors just to secure the paperwork required to maintain coverage.
Administrative Burden on Healthcare Systems
Providers are already facing burnout and administrative fatigue. By forcing doctors to act as gatekeepers for Medicaid eligibility, the policy risks diverting precious clinical time toward paperwork. Without standardized national forms or clear guidance on how to define "work-limiting" conditions, physicians are being placed in an uncomfortable position: acting as arbiters of federal policy rather than healers.
The Threat of "Churn"
The increased documentation requirements are likely to lead to "churn"—a phenomenon where individuals lose their health coverage due to procedural errors or the inability to navigate the paperwork, even if they technically remain eligible. This is particularly dangerous for patients with chronic illnesses who rely on consistent, uninterrupted care to maintain their health and, by extension, their ability to work.
Official Responses and Future Outlook
Federal officials maintain that these policies are designed to promote economic self-sufficiency while protecting those truly in need. However, advocacy groups and some state administrators have expressed deep concerns. Many states are currently struggling to update their IT infrastructure to handle the complexities of the new Medicaid mandates while simultaneously preparing for the tighter financial scrutiny of the PERM (Payment Error Rate Measurement) program.
The success of these programs will ultimately depend on whether states can find a "middle path." If they over-correct to avoid financial penalties, they risk stripping coverage from the very people the "medical frailty" exemption was designed to protect. If they remain too lenient, they face the risk of federal audits and potential fiscal clawbacks.
As the January 2027 deadline approaches, the focus must remain on transparency and administrative efficiency. Without clear, consistent, and compassionate guidance from federal agencies, the implementation of these work requirements could fundamentally alter the relationship between low-income Americans and the government agencies that provide their essential support. The coming years will be a test of whether a data-driven, high-stakes verification system can coexist with the foundational goal of providing a safety net for those who need it most.
About the Author