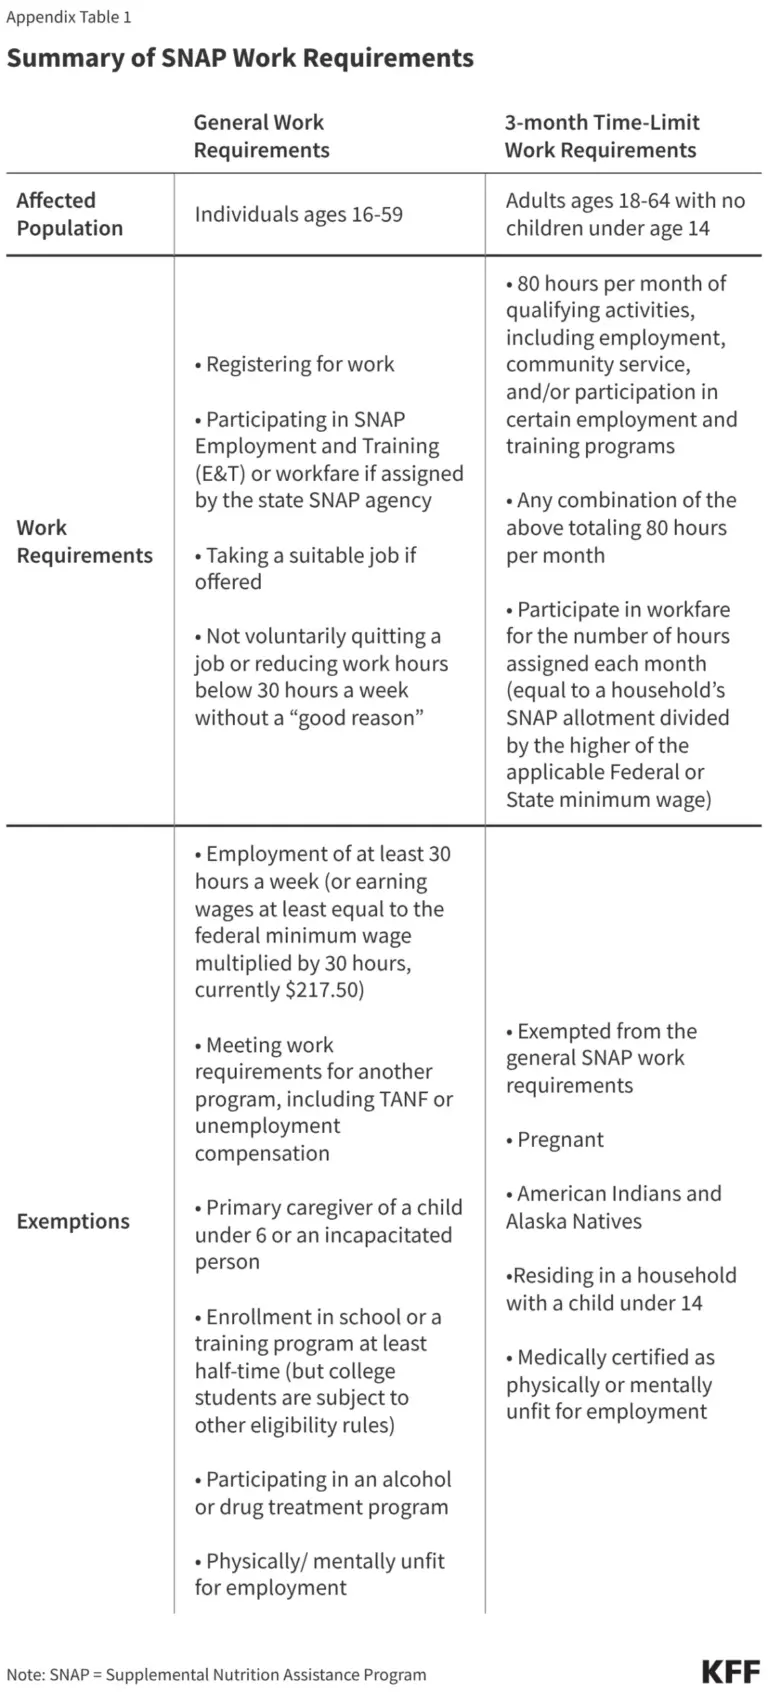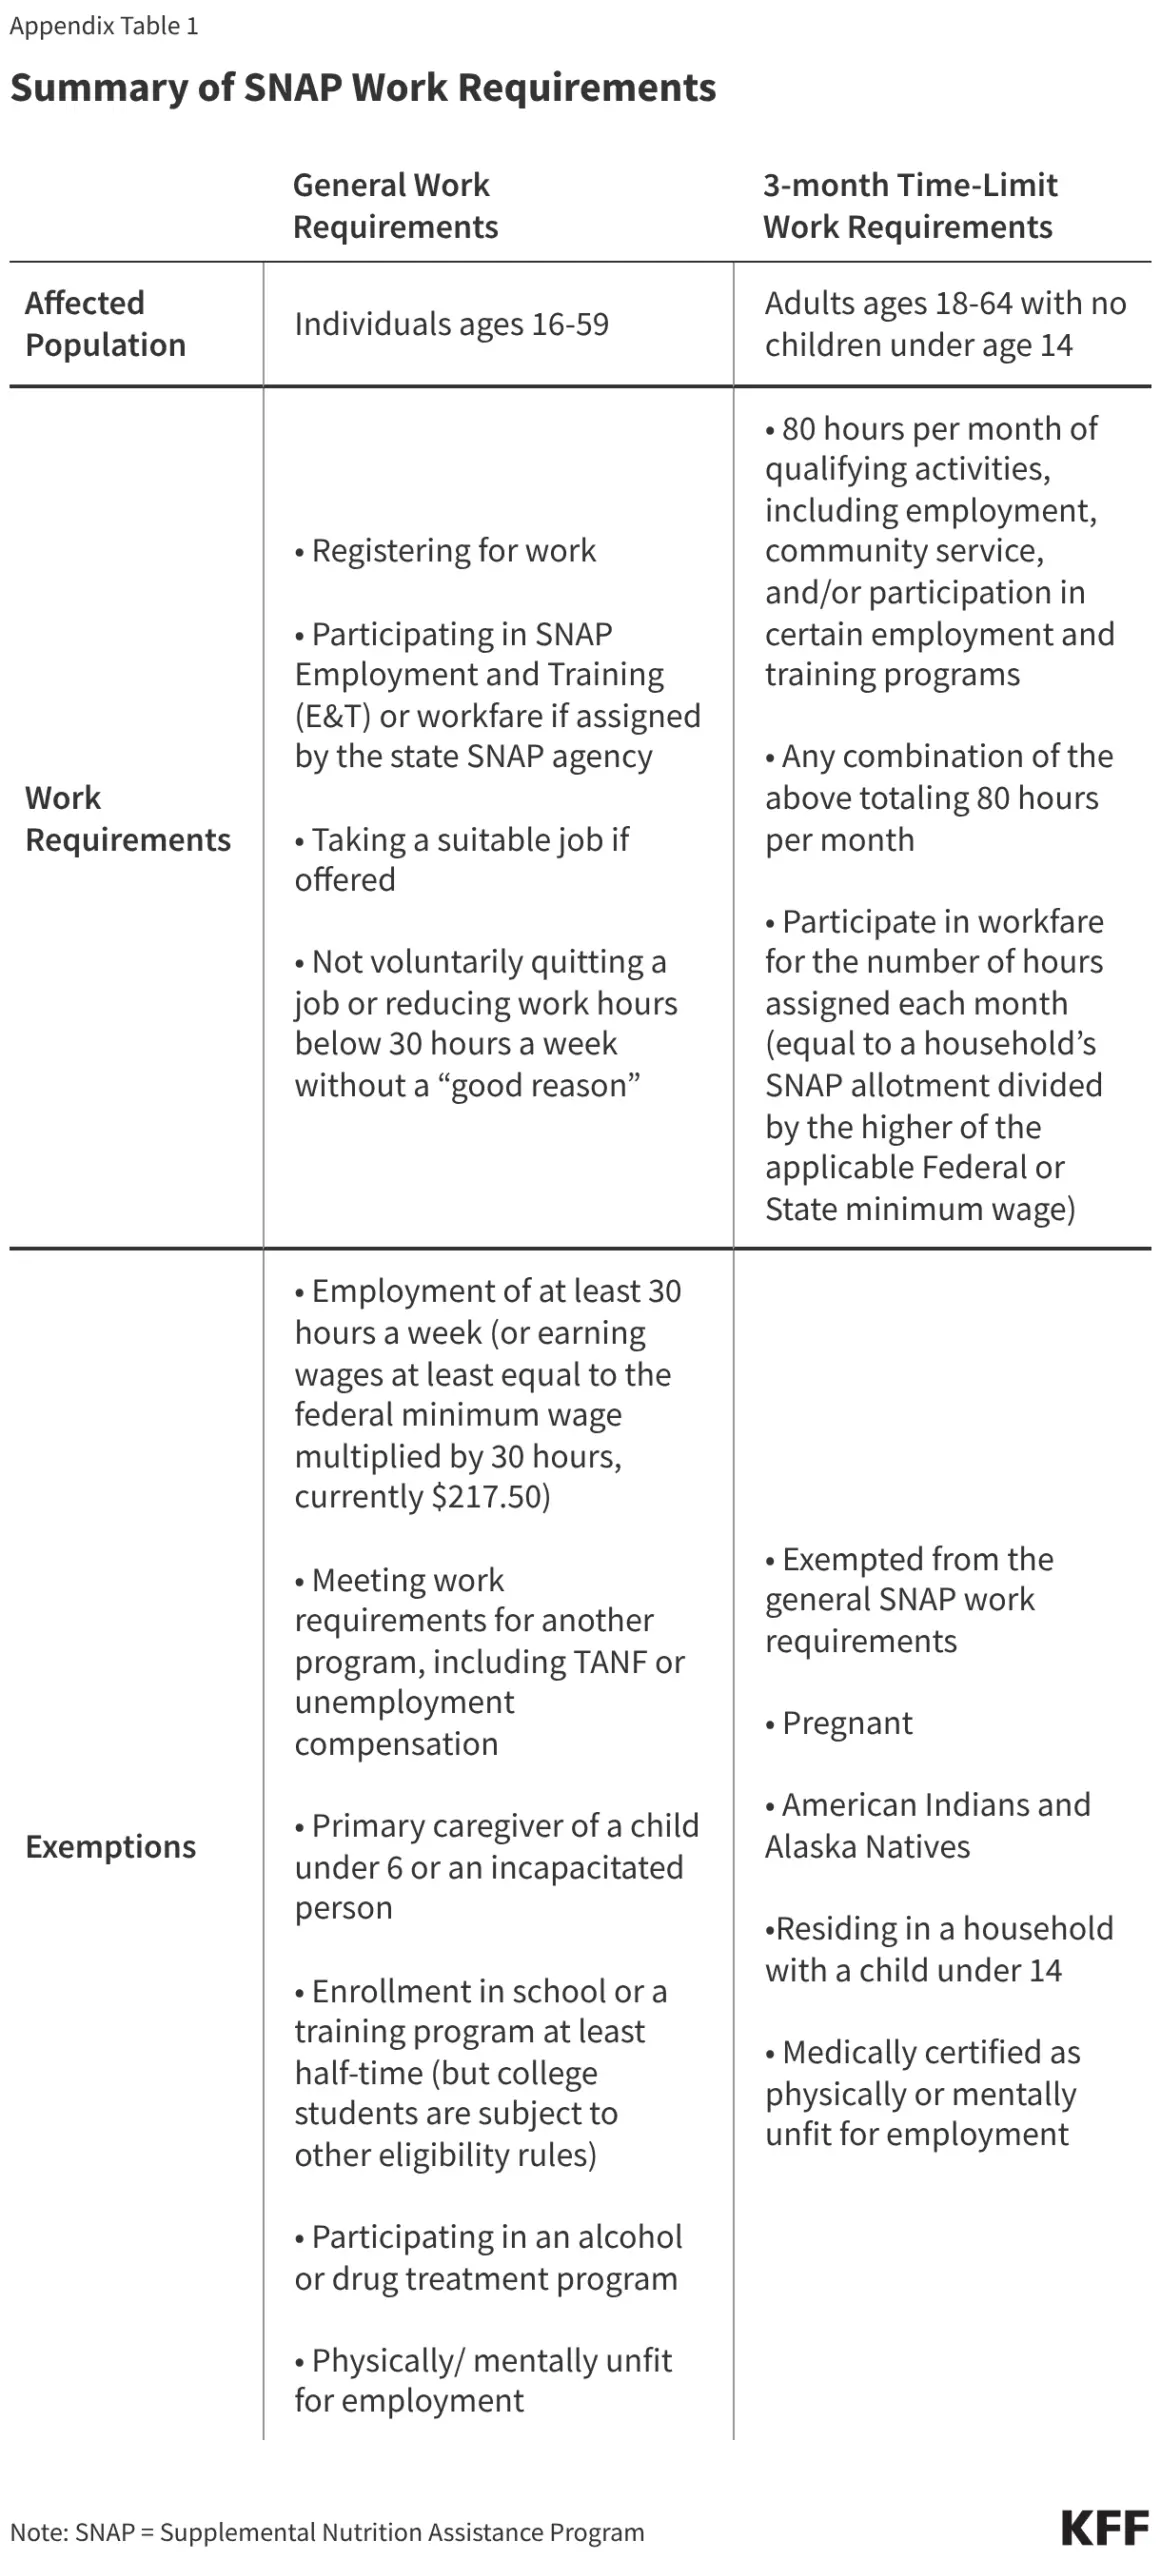
As the United States approaches a significant transformation in its social safety net, state administrators and federal regulators are bracing for a complex operational overhaul. By January 1, 2027, forty-four states will be mandated to tie Medicaid eligibility for Affordable Care Act (ACA) expansion enrollees to work requirements. This policy shift mirrors the long-standing structure of the Supplemental Nutrition Assistance Program (SNAP), which has historically utilized "fitness for work" criteria to determine aid eligibility.
The central challenge for states lies in identifying who is "medically frail"—and thus exempt—without triggering costly administrative errors or unfairly denying coverage to the most vulnerable.
Main Facts: The Intersection of SNAP and Medicaid
The federal government is imposing a new paradigm on Medicaid, shifting from a focus on pure income eligibility to one that includes labor market participation for non-disabled, non-elderly adults. However, the law provides a vital safeguard: the "medical frailty" exemption. To qualify, an individual must present a documented health condition that demonstrably impairs their ability to meet work requirements.
The transition is fraught with ambiguity. While the Centers for Medicare & Medicaid Services (CMS) has provided a framework for verification, it remains advisory rather than mandatory. Consequently, states are left to interpret how to define, verify, and document frailty. This creates a patchwork of potential policies, where an individual’s eligibility could change significantly depending on their state of residence.
Chronology of Implementation
The timeline for this transition is aggressive, forcing states to modernize their data systems and eligibility protocols on a compressed schedule:
- Pre-2026: States have historically relied on diverse, often subjective, methods to determine SNAP work exemptions.
- June 2026: CMS releases an interim final rule providing a "tiered" approach to Medicaid medical frailty verification, emphasizing the use of existing claims data.
- January 1, 2027: The federal deadline for the majority of states to implement work requirements for Medicaid expansion groups.
- October 2027: New federal regulations regarding SNAP Payment Error Rates (PER) take effect, increasing financial pressure on states to tighten verification processes to avoid penalties.
- January 1, 2028: The restriction on "self-attestation" in Medicaid takes full effect. States will be barred from accepting a client’s word alone as proof of medical frailty for more than one enrollment period, necessitating more rigorous documentation.
Supporting Data: Lessons from SNAP
To understand the challenges facing Medicaid, one must look at the administrative history of SNAP. Historically, SNAP has allowed for significant state discretion in defining "physical or mental unfitness." This has led to broad variance: some states include those experiencing homelessness or domestic violence survivors as categorically exempt, while others maintain a narrower definition.
The SNAP verification process relies heavily on in-person or phone interviews. According to a 2024 analysis, over half of state SNAP agencies grant eligibility workers significant discretion. An observer might see an individual using an oxygen tank and deem them exempt, bypassing the need for medical paperwork. While this reduces the burden on patients, it also introduces subjectivity that can lead to inconsistent outcomes.
The Documentation Dilemma
The reliance on medical providers to attest to a patient’s "fitness for work" is a recurring pain point. Currently, there is no standardized, nationwide form for verifying medical frailty. Some states require a physician’s signature on a specific form; others accept a phone call or a handwritten note. Because providers receive little guidance on how to evaluate the intersection of a medical condition and the ability to work, their assessments vary wildly, leaving many applicants in a state of limbo.
Official Responses and Strategic Shifts
State agencies are currently in a reactive posture. Faced with the dual pressure of implementing Medicaid work requirements and avoiding the steep financial penalties associated with the new SNAP Payment Error Rate (PER) mandates, administrators are opting for increased documentation requirements.
For instance, Arizona recently pivoted to requiring more granular proof for SNAP exemptions, moving away from simple client statements. This "defensive administration" is a direct response to the federal government’s plan to hold states financially liable for administrative errors.

CMS, for its part, is promoting a "tiered verification framework" for Medicaid:
- Tier 1: Verification through existing claims data (the most automated and efficient).
- Tier 2: Verification through a combination of claims and encounter data.
- Tier 3: A manual, high-touch process requiring documentation from the patient or provider.
CMS officials argue that this tiered approach will prevent unnecessary paperwork for the majority of enrollees. However, critics point out that this does not solve the problem for new applicants who lack a 12-month medical history, or for those whose providers fail to use standardized diagnostic coding.
Implications: The Risks of Administrative Burden
The transition raises three primary concerns for policymakers, providers, and enrollees:
1. Increased Administrative Costs
States will likely see an uptick in administrative overhead. Processing manual exemptions (Tier 3) is significantly more expensive than automated verification. As states scramble to update their IT infrastructure to interface with medical claims databases, the upfront costs of implementation could be substantial.
2. The "Chilling Effect" on Enrollment
The shift away from self-attestation in 2028 creates a high barrier to entry. Vulnerable populations—those with mental health struggles, unstable housing, or limited access to primary care—may struggle to navigate the complex documentation requirements needed to secure a medical frailty exemption. The result may be a "chilling effect," where eligible individuals drop off the rolls not because they are non-compliant, but because they are unable to navigate the administrative bureaucracy.
3. Provider Burden
The medical community is already facing burnout. Requiring providers to act as the final arbiters of an individual’s work capacity—a determination that is arguably social rather than purely medical—adds another layer of paperwork to the clinical workflow. If states do not provide clear, standardized guidance and simplified forms, many providers may opt out of the process, effectively penalizing the patients who need these exemptions most.
Conclusion: A Balancing Act
The effort to align Medicaid with the work-focused model of SNAP is an attempt to harmonize federal aid programs, but the operational realities are stark. While the use of claims data in Medicaid offers a technological advantage that SNAP lacks, the human element—the subjective evaluation of "fitness for work"—remains the weakest link in the chain.
As the 2027 and 2028 deadlines loom, the success of these programs will depend on whether states can find a middle ground. If states lean too heavily on documentation to avoid federal financial penalties, they risk stripping coverage from those who are truly unable to work. If they remain too lenient, they invite federal audits and fiscal sanctions.
For now, the policy environment remains one of extreme uncertainty. The coming years will serve as a critical test of whether the administrative state can successfully integrate labor requirements into health coverage without compromising the foundational promise of the Medicaid program: providing a safety net for those who, through illness or frailty, are unable to support themselves through traditional employment.
About the Author