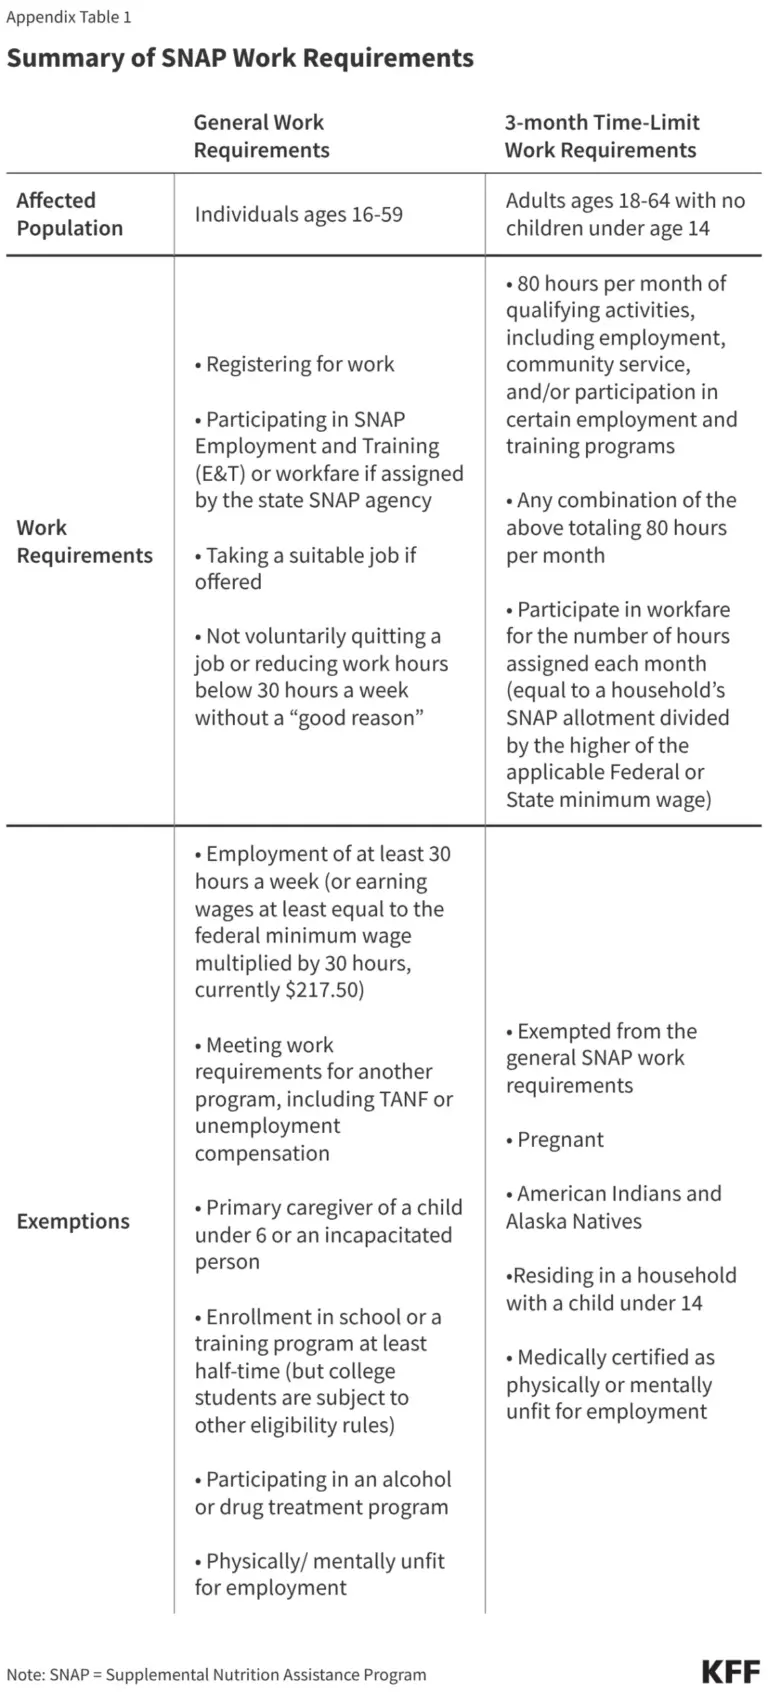
As the United States approaches a significant transformation in its social safety net, policymakers and state administrators are bracing for the implementation of new, stringent work requirements for federal aid programs. While the Supplemental Nutrition Assistance Program (SNAP) has long utilized work requirements to condition benefits for low-income households, the landscape is shifting. By January 1, 2027, 44 states will be mandated to link Medicaid eligibility for Affordable Care Act (ACA) expansion enrollees to work requirements.
This policy pivot brings the administrative challenges of "medical frailty" exemptions to the forefront. As states scramble to define how to verify who is truly "unfit for employment," they are looking toward the long-standing, albeit inconsistent, frameworks established by SNAP. The transition marks a critical juncture in how the government balances program integrity with the fundamental necessity of providing care to those who are medically unable to work.
Main Facts: The Policy Landscape
The upcoming mandate requires that adults in the ACA Medicaid expansion group—and those in specific waiver programs—meet work requirements to maintain coverage. However, the law provides a crucial "off-ramp": an exemption for individuals deemed "medically frail." To qualify, an enrollee must not only possess a qualifying condition but must also demonstrate that this condition directly impairs their ability to meet the stipulated work requirements.
The core challenge lies in the verification process. The Centers for Medicare & Medicaid Services (CMS) has provided a roadmap for states to verify these exemptions, but adoption is not mandatory. Consequently, the onus of creating a functional, fair, and legally defensible verification process rests with state agencies. This uncertainty mirrors the historical variability of SNAP, where states have historically wielded significant discretion in defining what constitutes a "physical or mental limitation."
Chronology of Implementation
- Historical Context: For decades, SNAP has operated with state-level discretion regarding work requirement exemptions, resulting in a fragmented landscape of definitions and verification methods.
- Current Phase: States are currently evaluating the CMS-issued guidance on the "tiered medical frailty framework."
- January 1, 2027: The mandatory deadline for 44 states to begin conditioning Medicaid eligibility on work requirements.
- January 1, 2028: A critical threshold for Medicaid; after this date, states will be severely restricted in their ability to accept self-attestation as a primary form of verification for medical frailty, shifting the burden toward data-driven or physician-backed proof.
- October 2027: The initiation of new financial accountability measures for SNAP, where states face penalties based on their payment error rates (PER).
Supporting Data: Lessons from SNAP
The SNAP experience serves as both a blueprint and a cautionary tale for Medicaid administrators. Under federal regulations, SNAP agencies define "physical or mental fitness" independently. This has led to a patchwork of definitions: some states include chronic homelessness or the trauma of domestic violence as factors, while others maintain a narrow, medical-only definition.
The Role of the Eligibility Interview
A mandatory component of the SNAP process is the eligibility interview. During these sessions, caseworkers often exercise discretion, using "visual observation"—such as identifying an oxygen tank or obvious mobility limitations—to grant immediate exemptions. However, the effectiveness of this system is hampered by inconsistency. An evaluation of SNAP exemption processes found that while many workers feel that requiring formal medical documentation would increase consistency, it simultaneously places an immense administrative burden on the individuals, the healthcare providers tasked with writing the notes, and the agency staff processing the paperwork.
The Financial Pressure of Error Rates
The incentive for states to be "cautious" in granting exemptions is growing. Under new reconciliation laws, states must pay a portion of SNAP benefit costs if their payment error rate (PER) exceeds 6%. This has already triggered behavioral changes. Arizona, for instance, has shifted from accepting client statements to requiring additional documentation to avoid the fiscal penalties associated with administrative errors. This move highlights a growing trend: administrative fear of federal penalties is often prioritized over the ease of access for vulnerable populations.
Official Responses and CMS Guidance
CMS has attempted to mitigate the potential for chaos by proposing a tiered medical frailty framework:
- Tier 1: Identification through automated claims and encounter data from the previous 12 months.
- Tier 2: A combination of claims data and supplemental information.
- Tier 3: An individualized, manual process involving documentation for cases where data is insufficient.
While this framework is intended to streamline the process, it assumes a level of data hygiene that many state Medicaid programs currently lack. For new applicants or those who have not accessed care recently, the data is non-existent, leaving them entirely reliant on the Tier 3 manual process.

State agencies have expressed concern that the CMS guidance is too abstract. Without clear, standardized definitions of "medical frailty," states fear that they will be vulnerable to federal audits. If an audit reveals that a state has frequently approved exemptions with "insufficient support," that state could face severe financial repercussions.
Implications for Patients and Providers
The shift toward more rigorous verification carries profound implications for both the healthcare system and the enrollees themselves.
The "Documentation Burden" on Providers
As states move away from self-attestation, the burden shifts to the medical community. Providers, who are already struggling with administrative burnout, will be tasked with filling out specific forms to verify a patient’s ability to work. Because there is no national standard for what these forms should contain, physicians may be forced to navigate a dizzying array of state-specific paperwork. North Carolina’s attempt to create a unified form for both Medicaid and SNAP is an outlier; most states remain disconnected in their approach.
The Erosion of Self-Attestation
The most significant change for Medicaid is the impending 2028 restriction on self-attestation. Throughout 2027, states may accept a patient’s word as a temporary measure. By 2028, however, that door closes. This policy assumes that all Medicaid enrollees have access to a primary care physician who can readily verify their health status. For the millions of low-income Americans who utilize emergency rooms or community clinics as their primary point of care, obtaining a formal medical attestation of "frailty" could become an insurmountable barrier to coverage.
Financial Penalties vs. Equitable Access
The overarching concern for state administrators is the "dual threat" of financial penalties. States are currently being squeezed by two fronts: the SNAP PER penalties (starting in 2027) and the Medicaid PERM (Payment Error Rate Measurement) program, which punishes eligibility errors exceeding 3%.
When the cost of an administrative error—granting an exemption to someone who might not strictly qualify—is high, states are incentivized to be overly restrictive. The "chilling effect" of these policies could result in the unintended loss of coverage for individuals with legitimate, yet poorly documented, medical needs.
Conclusion
The path toward 2027 is paved with significant administrative complexity. While the integration of data-driven, tiered verification methods offers a glimpse of a more modern, automated system, the reliance on manual documentation and the pressure to avoid financial penalties remain major hurdles.
As states finalize their approaches, the core question remains: will the desire for programmatic "integrity" and the mitigation of financial risk result in a system that protects the taxpayer, or will it create a bureaucratic gauntlet that leaves the most vulnerable populations without the health coverage they rely on to survive? The coming months will likely see a flurry of legislative and administrative activity as states attempt to navigate this delicate balance between fiscal responsibility and the mandate to serve those in need.
About the Author