In a landmark shift for American social safety nets, Nebraska officially became the first state in the nation to enforce stringent Medicaid work requirements on May 1, 2026. This policy implementation marks a pivotal moment in the ongoing national debate regarding the role of government-funded healthcare and the responsibilities of the individual. While the federal government set a broader timeline through the 2025 reconciliation law—mandating that states condition Medicaid eligibility on employment or specific exemptions starting January 1, 2027—Nebraska’s decision to fast-track these requirements has provided the country with its first real-world look at how such policies impact vulnerable populations.
As health policy analysts and government officials monitor the outcomes of these changes, the early data from Nebraska serves as a critical case study. With thousands of applications processed and renewals under scrutiny, the implications for Medicaid enrollees are profound, raising questions about bureaucratic accessibility, administrative burden, and the fundamental stability of health coverage for low-income adults.
The Chronology of Implementation: From Policy to Practice
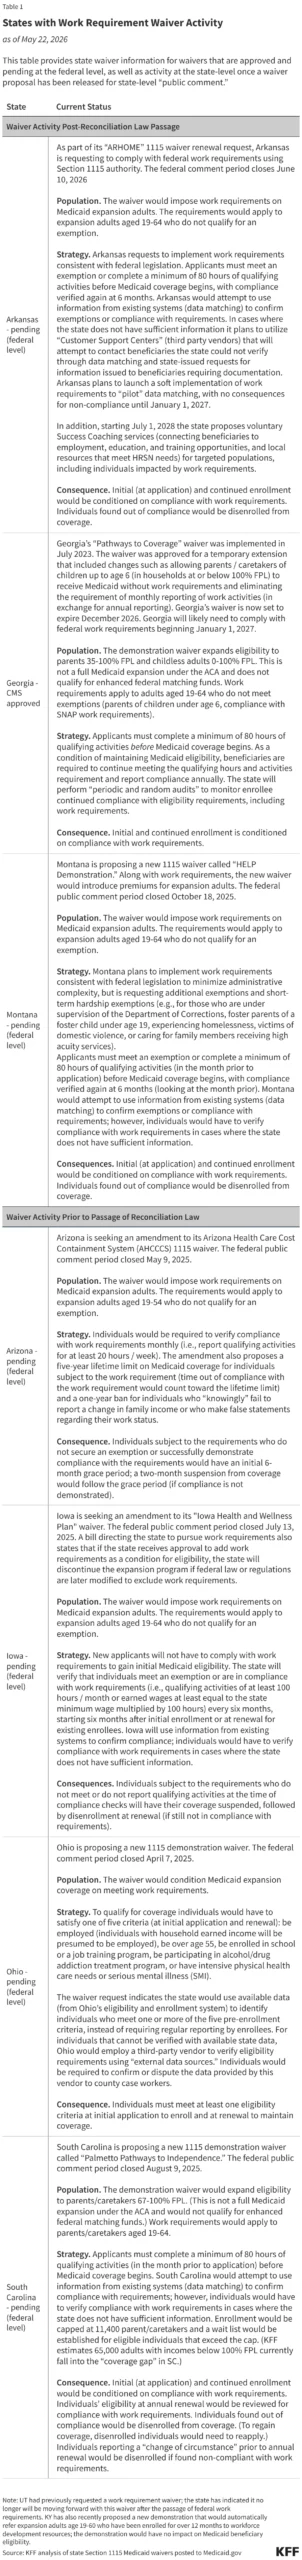
The journey toward Nebraska’s current Medicaid landscape began with the 2025 reconciliation bill, which fundamentally altered the landscape of the Affordable Care Act (ACA) Medicaid expansion. The legislation sought to standardize work requirements across the country, requiring states to mandate that adult enrollees either engage in qualifying work activities or meet specific exclusion criteria.
While the federal deadline looms for the rest of the nation, Nebraska moved aggressively. Governor Jim Pillen, alongside federal advisors, positioned the state as a laboratory for welfare reform. By May 1, 2026, the state had fully operationalized its verification system, setting the stage for a rollout that would impact both new applicants and those seeking to renew their existing coverage.
Throughout the summer of 2026, the Nebraska Department of Health and Human Services (DHHS) managed a complex transition. By August 2026, the first significant wave of data was compiled, offering the Medicaid Advisory Committee (MAC) and the public a glimpse into the initial impact of these requirements. This timeline is not merely a record of administrative change; it is a timeline of a shift in the philosophy of care, where access to medical services is now tethered to a verifiable labor status.
The Verification Mechanism: How Nebraska Processes Eligibility
Central to the success or failure of these mandates is the verification process itself. Nebraska has adopted a hybrid approach that utilizes existing state data alongside a mandatory self-declaration system.
The Data-Driven Approval Process
Where possible, the state attempts to automatically verify an individual’s employment status through existing government databases. When the state’s digital records confirm that an applicant is meeting the requisite number of work hours, an approval notice is sent automatically. This "passive" verification is designed to reduce the administrative burden on the state and the enrollee alike.
The Challenge of Self-Declaration
For thousands of citizens, however, the state’s data is insufficient. In these cases, the DHHS issues a formal notice detailing the specific information required to maintain eligibility. Applicants are then required to return a “declaration form” within a strict 30-day window. This form allows individuals to attest to their qualifying activities—which include employment, job training, or community service—or to declare that they meet an exclusion criterion, such as being a primary caregiver or suffering from a documented disability.
Hardship Exceptions
Recognizing that life circumstances do not always align with rigid employment metrics, Nebraska has implemented a series of short-term hardship exceptions. These include:
- Economic Distress: Residents in counties experiencing high unemployment rates.
- External Crises: Individuals impacted by natural disasters.
- Medical Necessity: Those admitted to hospitals or nursing facilities, or those forced to travel long distances for specialized medical care for themselves or their dependents.
While the state currently permits self-declaration through 2027, federal rules are set to tighten significantly by January 2028. After that date, the state will be required to demand formal documentation rather than simple self-attestation, a change that many experts fear will create a much higher "churn" rate, where eligible individuals lose coverage simply because they cannot navigate the complexities of documentation.
Analyzing the Data: Early Outcomes and Coverage Trends
The initial data presented to the Nebraska Medicaid Advisory Committee in September 2026 provides a stark look at the consequences of the new requirements.
New Applicants: The 14% Disparity
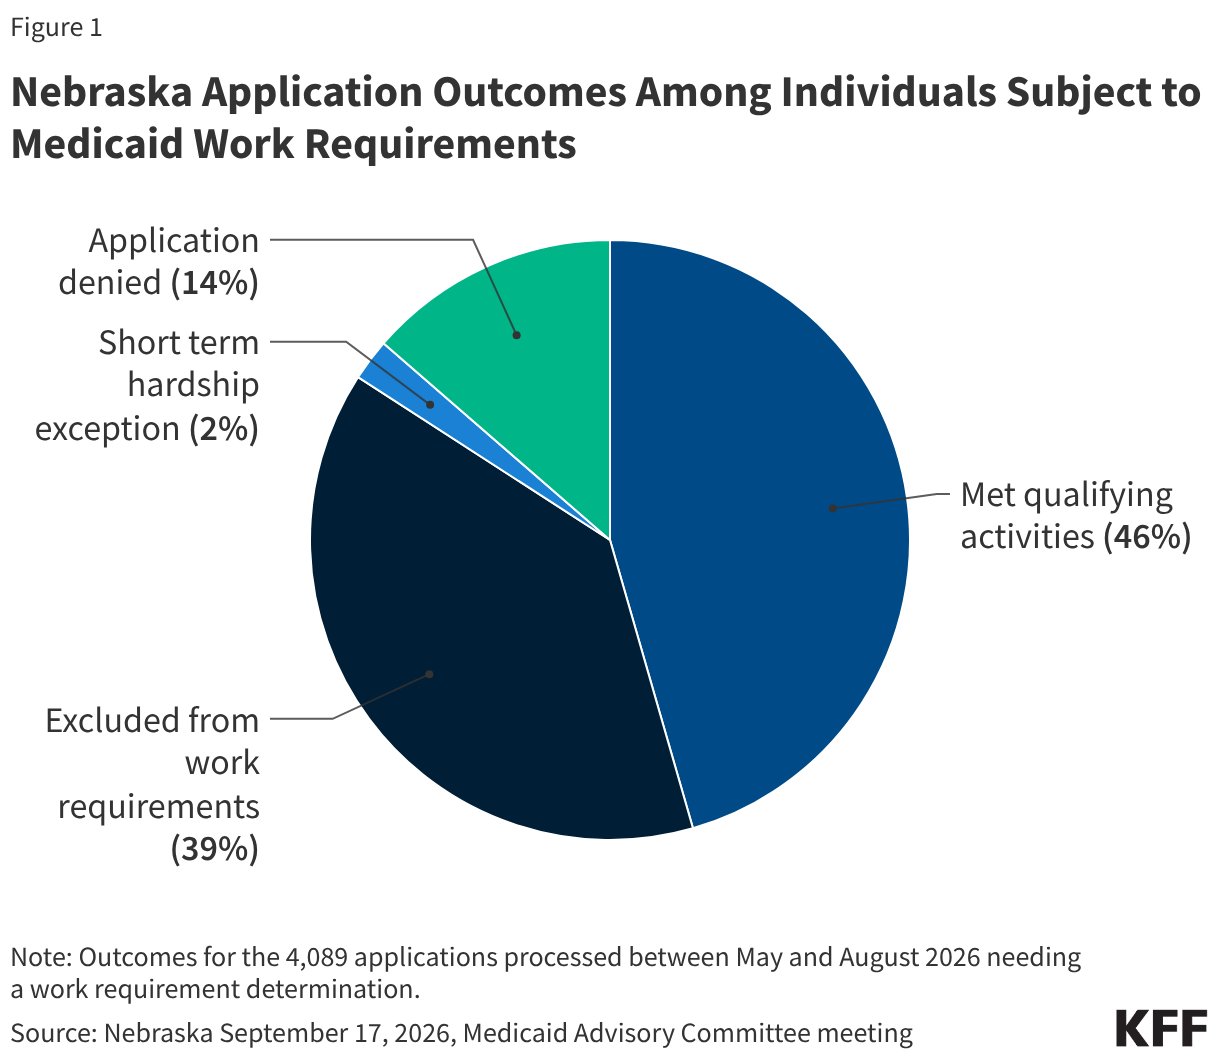
Between May and August 2026, the state processed over 9,600 applications. Of those specifically subject to the new work requirements, 86% were able to meet the criteria or secure an exemption. However, 14% of applicants—a significant portion—were denied coverage. While it is important to note that many applicants were denied for standard reasons like exceeding income thresholds, the 14% figure specifically tied to work requirement non-compliance suggests that a meaningful segment of the population is falling through the cracks.
Renewals: The Risk of Disenrollment
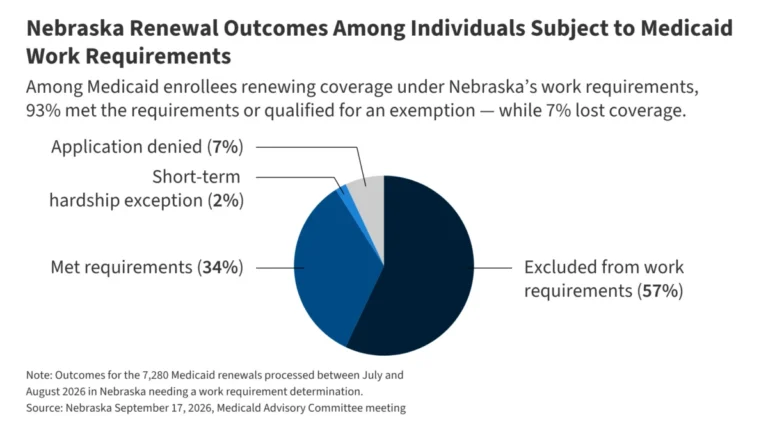
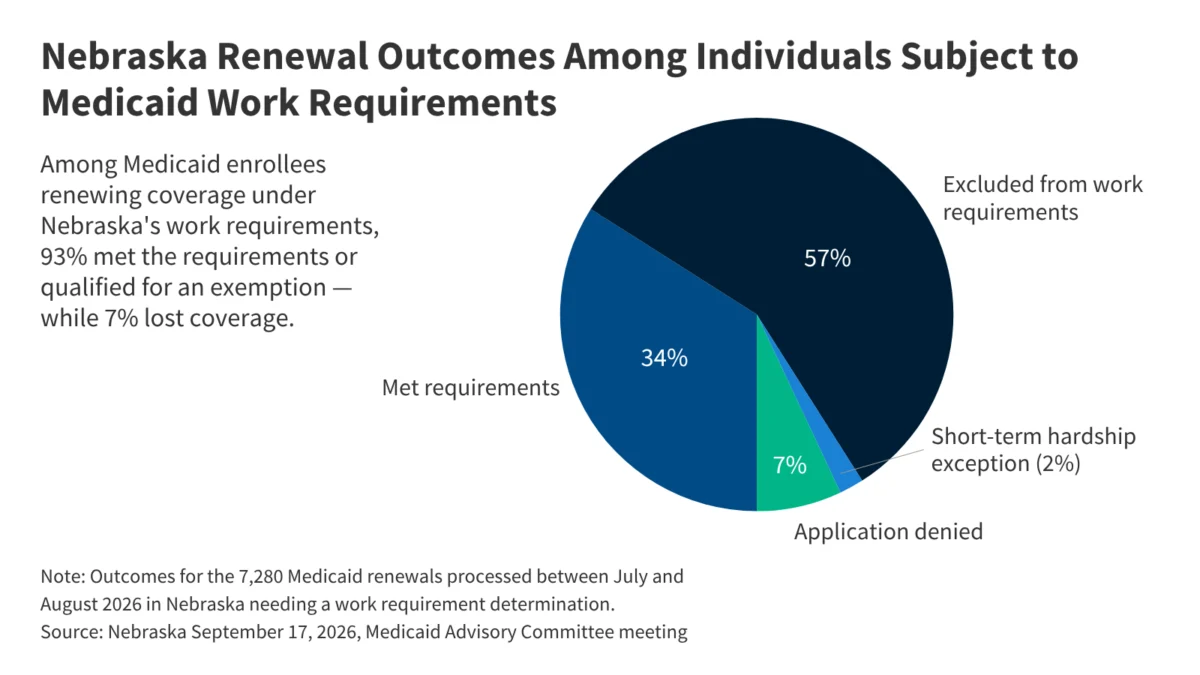
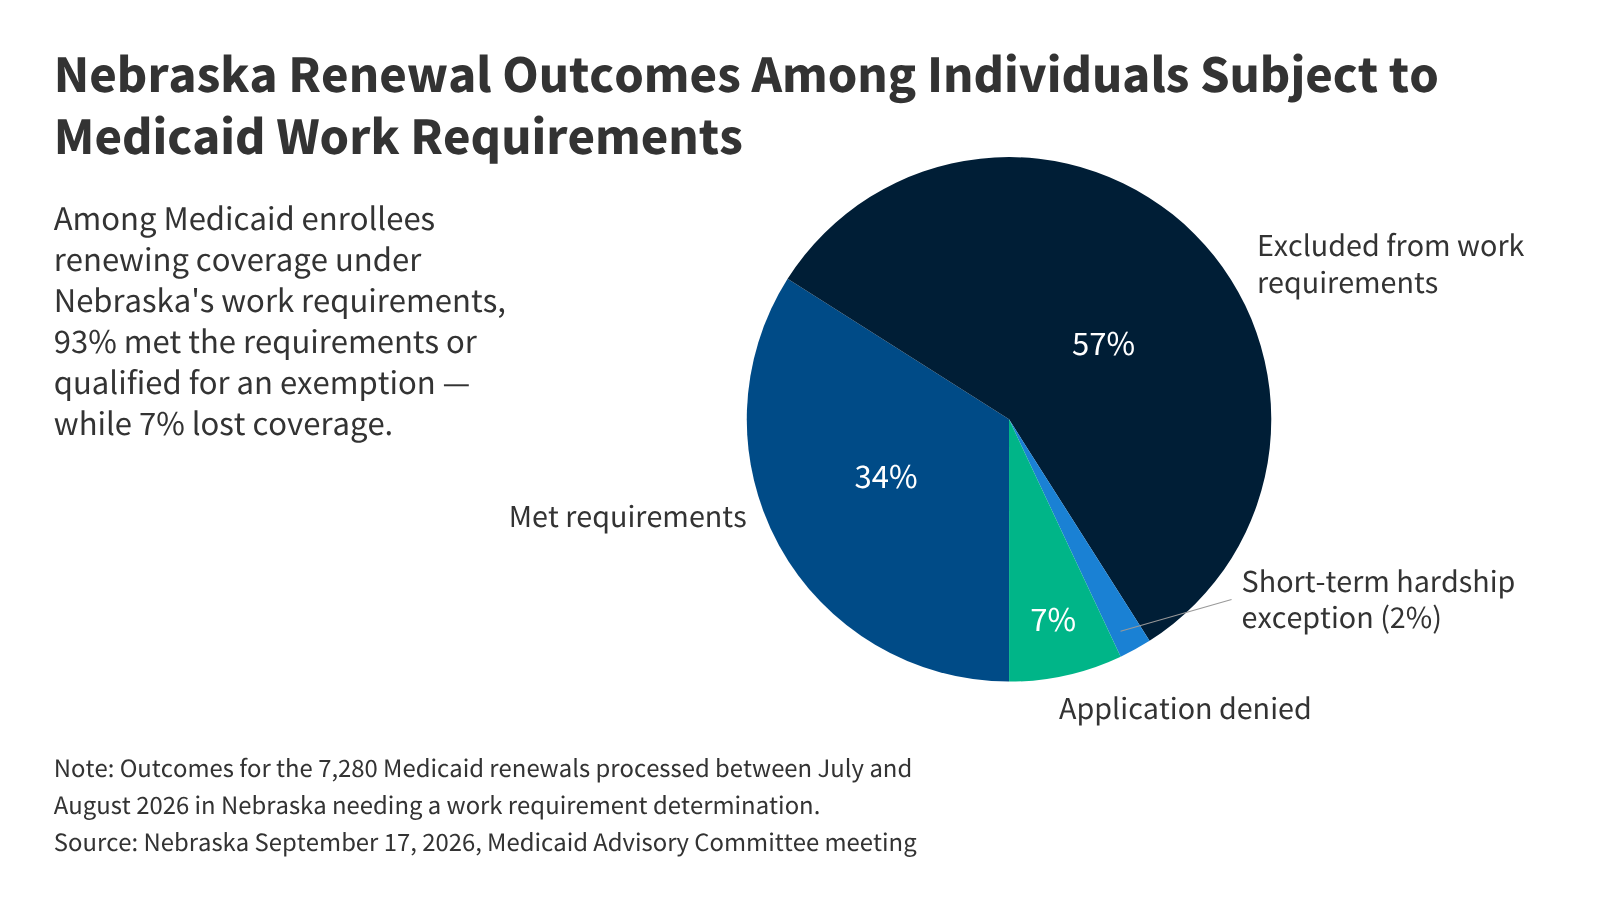
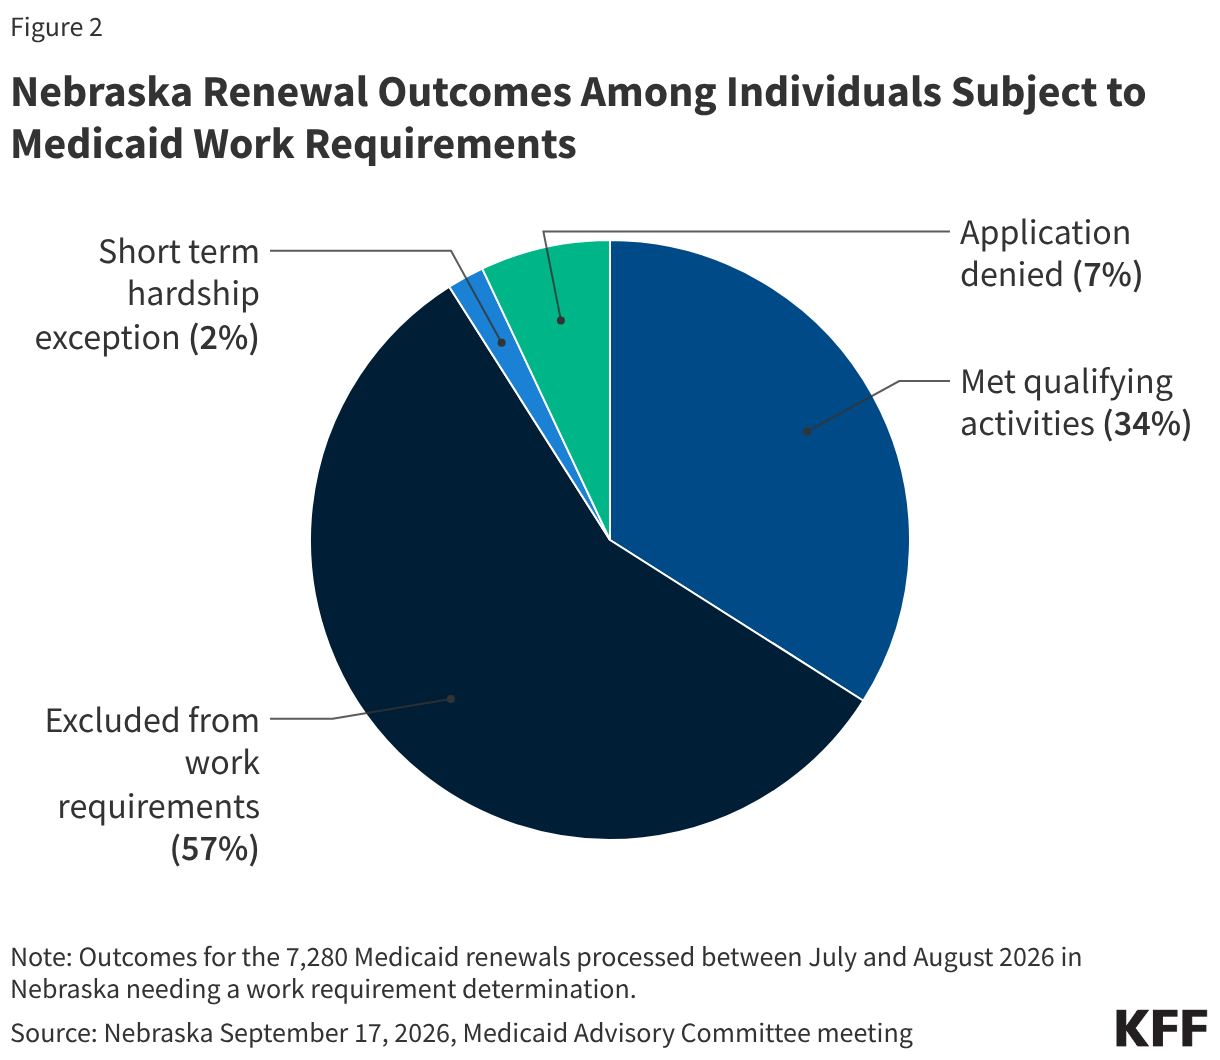
The trend was slightly more favorable for those already enrolled in the program. Of the 7,280 renewals processed, 93% maintained their coverage. Yet, 7% of enrollees lost their benefits. For a family living on the margins, a 7% loss in a single cycle represents a significant disruption to primary care, prescription access, and the management of chronic conditions.
These figures raise a critical question: Are these individuals truly ineligible for Medicaid, or are they victims of administrative friction? When an individual fails to respond to a notice of non-compliance, it is often difficult to distinguish between someone who has found employment elsewhere and someone who simply lacked the resources or awareness to complete the necessary paperwork.
Implications: The Road Ahead for Medicaid
The implications of Nebraska’s policy are far-reaching. As the state prepares for more stringent documentation requirements in 2028, the potential for increased disenrollment is high.
The Problem of "Administrative Churn"
Research from the Kaiser Family Foundation (KFF) and other policy observers suggests that "administrative burden" is a primary driver of coverage loss. Even if an individual is perfectly eligible for Medicaid, the requirement to provide periodic, specific proof of work status can be an insurmountable hurdle for those with limited internet access, unstable housing, or multiple part-time jobs in the gig economy.
Medical Frailty and Future Scrutiny
The Centers for Medicare & Medicaid Services (CMS) has already signaled that Nebraska’s process for verifying "medical frailty"—a key exemption category—needs revision. If the state is forced to adopt more rigid verification standards for these vulnerable groups, the number of people who qualify for exemptions could shrink, further driving up disenrollment numbers.
The Broader Political Landscape
This initiative is a centerpiece of the broader "Health in the 2026 Midterm Elections" conversation. The debate remains polarized: proponents argue that these requirements promote dignity through work and ensure that taxpayer-funded programs are directed toward those most in need. Opponents, meanwhile, contend that the policy effectively acts as a "coverage tax," punishing the poor for the instability of the modern labor market and creating a bureaucratic nightmare that ultimately saves the state little money while harming public health.
Conclusion: A Cautionary Tale or a Blueprint?
Nebraska’s experiment with Medicaid work requirements serves as a mirror for the rest of the nation. As other states prepare to meet the 2027 federal deadline, they will look to Nebraska’s data to refine their own processes.
The early evidence suggests that while the majority of enrollees are already working or exempt, a notable minority—the 7% of renewals and the 14% of new applicants—are finding themselves excluded from the system. As the state moves toward 2028 and the end of self-attestation, the true impact of these policies will become clearer. Will the state be able to support those who struggle to meet these requirements, or will the "work" mandate result in a permanent reduction in the state’s insured population?
For policymakers and advocates alike, the lesson is clear: the transition from theory to practice is rarely seamless. The next two years will be a defining period, not just for Nebraska, but for the fundamental structure of the American social safety net. As the data continues to flow, the challenge will be to balance the stated goal of economic self-sufficiency with the core mandate of public health: ensuring that no citizen is denied care due to the complexity of the forms they are asked to sign.
About the Author