The Medicaid and Children’s Health Insurance Program (CHIP) remain the bedrock of the American social safety net, providing essential health and long-term care coverage to millions of low-income children, adults, seniors, and individuals with disabilities. However, beneath the surface of these federal-state partnerships lies a complex, fragmented system. Because these programs are jointly financed but state-administered under broad federal guidelines, the reality of "coverage" varies drastically depending on a citizen’s zip code.
New data released in 2026 highlights the widening chasm in how states manage their health programs. From expansion status to income eligibility thresholds, the landscape of American healthcare is defined more by state-level policy decisions than by a unified national standard.
The Landscape of American Health Coverage
Medicaid and CHIP are not monolithic entities. While the federal government mandates certain eligibility groups and services, states wield significant power to define the scope of their programs. This "federalism in action" has created a patchwork of coverage.
In some states, Medicaid serves as a robust engine for public health, reaching deep into the low-income population through aggressive expansion efforts and elevated income caps. In others, the program functions as a more restrictive safety net, limited to the mandatory floors set by federal statute. This divergence reflects a fundamental tension in American governance: the balance between federal oversight and the prioritization of state-level autonomy.
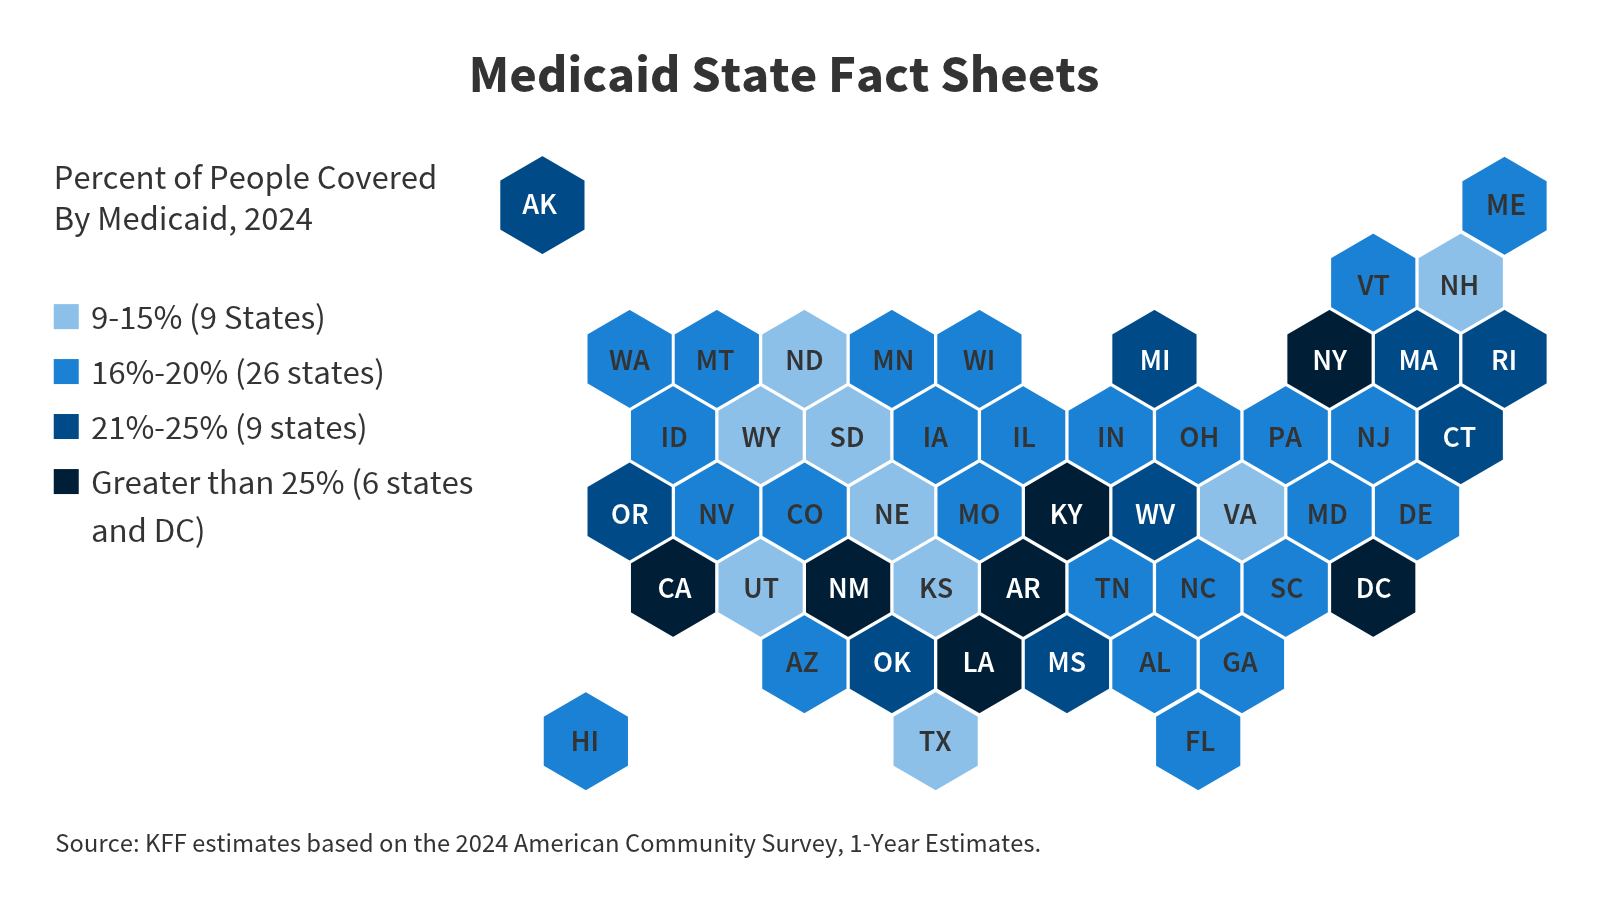
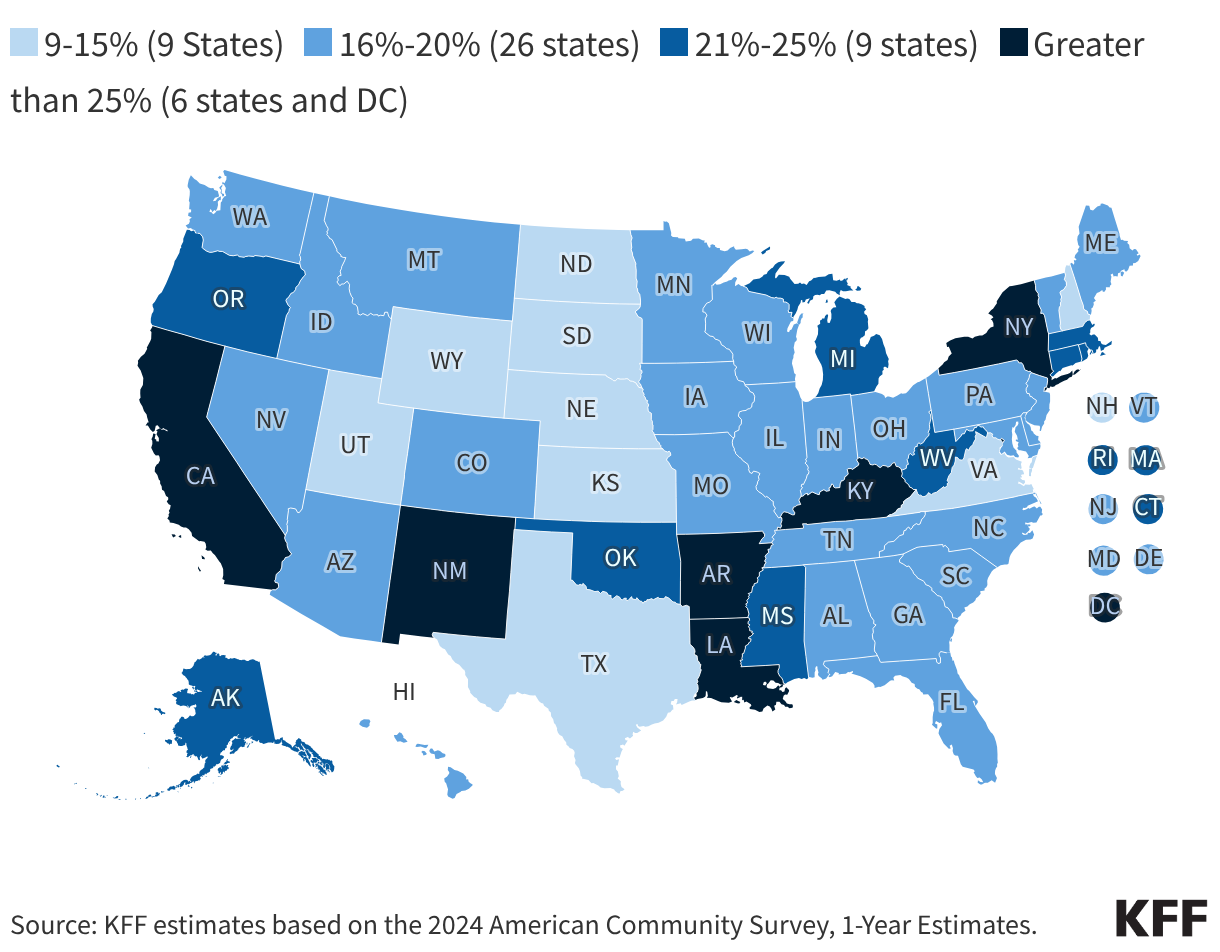
As of 2026, the enrollment statistics tell a story of regional disparity. The latest interactive maps and data tables from KFF provide a comprehensive, state-by-state snapshot of these trends, illustrating that where a person lives is often the most significant determinant of their healthcare security.
A Chronology of Policy Evolution
To understand the current state of Medicaid, one must look at the historical milestones that have shaped the program since its inception in 1965.
- 1965: The Foundation. Medicaid is established under Title XIX of the Social Security Act, designed to provide medical assistance to certain low-income individuals.
- 1997: Expansion for Children. The Children’s Health Insurance Program (CHIP) is created to cover children in families who earn too much to qualify for Medicaid but cannot afford private insurance.
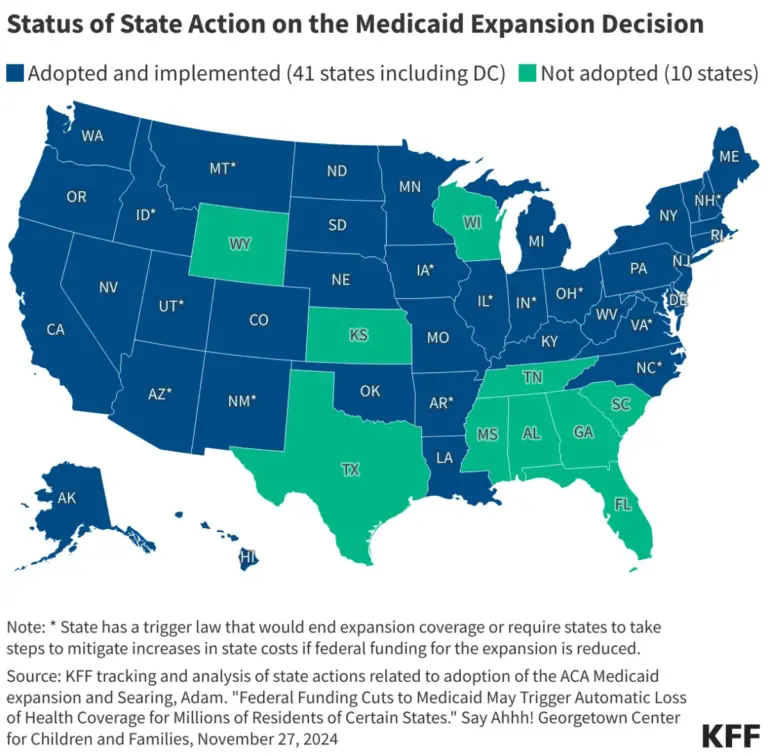
- 2010: The ACA Watershed. The Affordable Care Act (ACA) authorizes the expansion of Medicaid to nearly all adults with incomes up to 138% of the federal poverty level. This creates the first major policy "fault line" between states that opt into the expansion and those that do not.
- 2020–2023: The Pandemic Pause. During the COVID-19 public health emergency, states were prohibited from disenrolling individuals from Medicaid in exchange for enhanced federal funding. This led to record-high enrollment levels.
- 2023–2024: The "Unwinding." Following the end of the continuous enrollment provision, states began the massive administrative task of redetermining eligibility for millions of enrollees, leading to significant shifts in coverage numbers.
- 2026: The Current Reality. As of mid-2026, the healthcare system has largely stabilized post-unwinding, but the disparities in coverage rates—driven by economic conditions, legislative choices, and demographic shifts—are more pronounced than ever.
Supporting Data: The Anatomy of Disparity
The data compiled for 2026 confirms that Medicaid is highly sensitive to state-specific socioeconomic variables.
Enrollment and Eligibility
Enrollment is not merely a function of poverty rates; it is a function of policy. States that chose to expand Medicaid have consistently seen higher per-capita enrollment rates among working-age adults. Conversely, states that have resisted expansion show higher concentrations of "coverage gaps"—individuals who earn too much for traditional Medicaid but too little to qualify for subsidized marketplace plans.
The Role of Demographics
State populations differ in age, racial composition, and disability status. These demographic realities force states to tailor their Medicaid budgets. For example, states with aging populations often allocate a disproportionate share of their Medicaid funds to long-term care and nursing facilities, whereas states with younger, immigrant-heavy populations focus more heavily on pediatric care and maternal health coverage.
Spending Patterns
Medicaid spending is one of the largest line items in every state budget. However, the distribution of this spending is revealing. While most enrollees are children and non-disabled adults, the majority of spending is consistently tied to the aged, blind, and disabled populations. Understanding this expenditure split is essential for policymakers attempting to reform the system without compromising care for the most vulnerable.
Official Responses and Political Implications
The variation in state Medicaid programs has not gone unnoticed by federal policymakers or public health advocates.
The Federal Perspective
The Centers for Medicare & Medicaid Services (CMS) has increasingly utilized "1115 Waivers"—demonstration projects that allow states to test new ways of delivering care. The current federal administration has encouraged states to use these waivers to address "social determinants of health," such as housing instability and food insecurity. However, some states have used these same mechanisms to implement work requirements, a policy approach that has sparked intense legal and political battles.
The State Perspective
State governors and legislatures often frame their Medicaid decisions through the lens of fiscal responsibility. Proponents of limited expansion argue that Medicaid must remain focused on the most vulnerable and that expanding to able-bodied adults strains state coffers and crowds out private market competition. On the other side, proponents of expansion argue that the long-term economic benefits—such as a healthier workforce, reduced emergency room reliance, and federal funding influxes—far outweigh the administrative costs.
Implications: The Future of Health Equity
The implications of this fragmented system are profound. When healthcare access is dependent on geography, the result is an inherently unequal society.
1. Health Outcomes
Studies consistently show that Medicaid expansion is linked to improved health outcomes, including lower mortality rates, earlier cancer diagnoses, and better management of chronic conditions like diabetes and hypertension. The "gap" in coverage in non-expansion states translates into measurable disparities in life expectancy and quality of life.
2. Economic Stability
Medicaid acts as a vital economic stabilizer, particularly in rural areas where hospitals are often the largest employers. The closure of rural hospitals is frequently tied to a state’s decision regarding Medicaid expansion; when hospitals cannot recover the cost of treating uninsured patients, the entire community’s access to care is jeopardized.
3. The Future of Reform
As we look toward the latter half of the 2020s, the debate over Medicaid is unlikely to subside. Proposals for "block grants"—which would provide states with a fixed amount of federal funding rather than the current open-ended match—remain a point of contention. While supporters argue this would provide states with more flexibility and budgetary certainty, critics warn that it would lead to deep cuts in coverage and services during economic downturns.
Conclusion: Accessing the Data
For citizens, researchers, and policymakers, the 2026 fact sheets serve as more than just a collection of statistics. They are a mirror held up to the American social contract. By visualizing the percentage of people covered, the eligibility levels, and the expansion status of each state, these tools allow for a more informed conversation about what it means to be "covered" in the United States.
As the data makes clear, the mission of Medicaid—to protect the health of those who cannot afford it—remains unfinished. Whether through legislative reform at the state level or continued federal oversight, the goal remains the same: narrowing the gap between the promise of health equity and the reality of the regional divide.
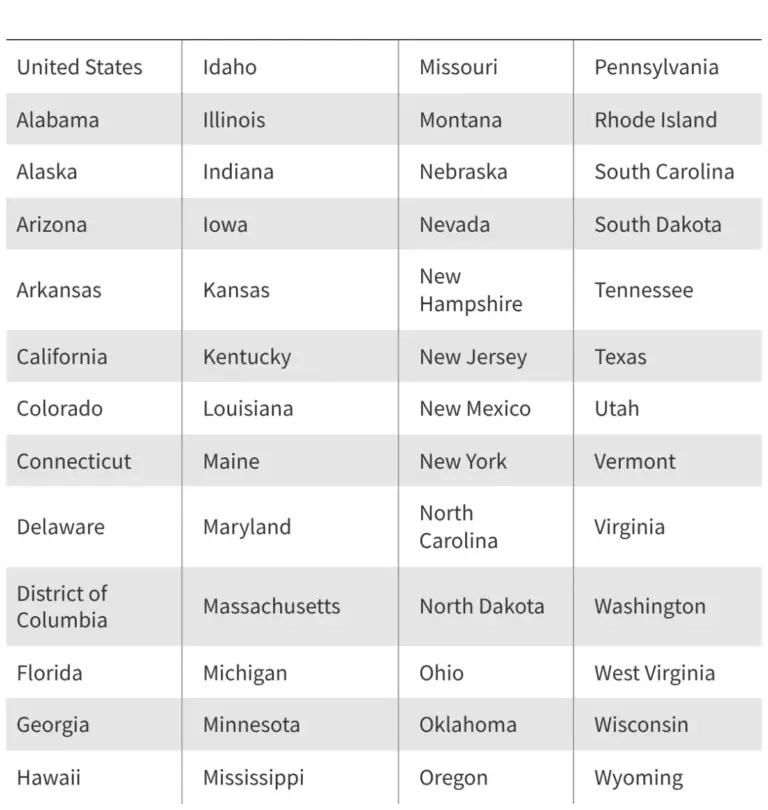
For those interested in exploring the specific data for their region, the interactive tools provided by the Kaiser Family Foundation (KFF) and other health policy analysts offer the most granular view into the enrollment, demographic, and spending patterns currently defining the nation’s health landscape.
Methodological Note
The data presented in this overview is derived from the latest 2026 reports, including state health indicators, federal enrollment figures, and ongoing longitudinal studies of Medicaid expansion decisions. Readers are encouraged to review the specific state fact sheets to understand the interplay between local policy and federal guidelines that shapes their own community’s health safety net.
About the Author