More than a decade after the passage of the Affordable Care Act (ACA), the landscape of American public health insurance remains deeply fragmented. At the heart of this divide is the Medicaid expansion—a policy cornerstone designed to provide a safety net for low-income adults. While the expansion has fundamentally altered the trajectory of health coverage in the United States, it has also become a focal point of intense political debate, state-level experimentation, and evolving financial strategies.
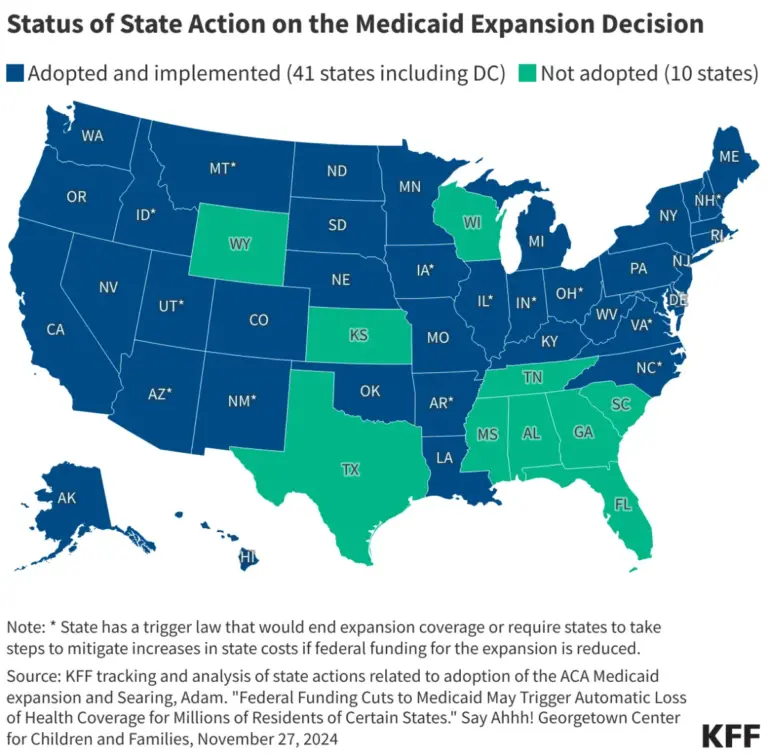
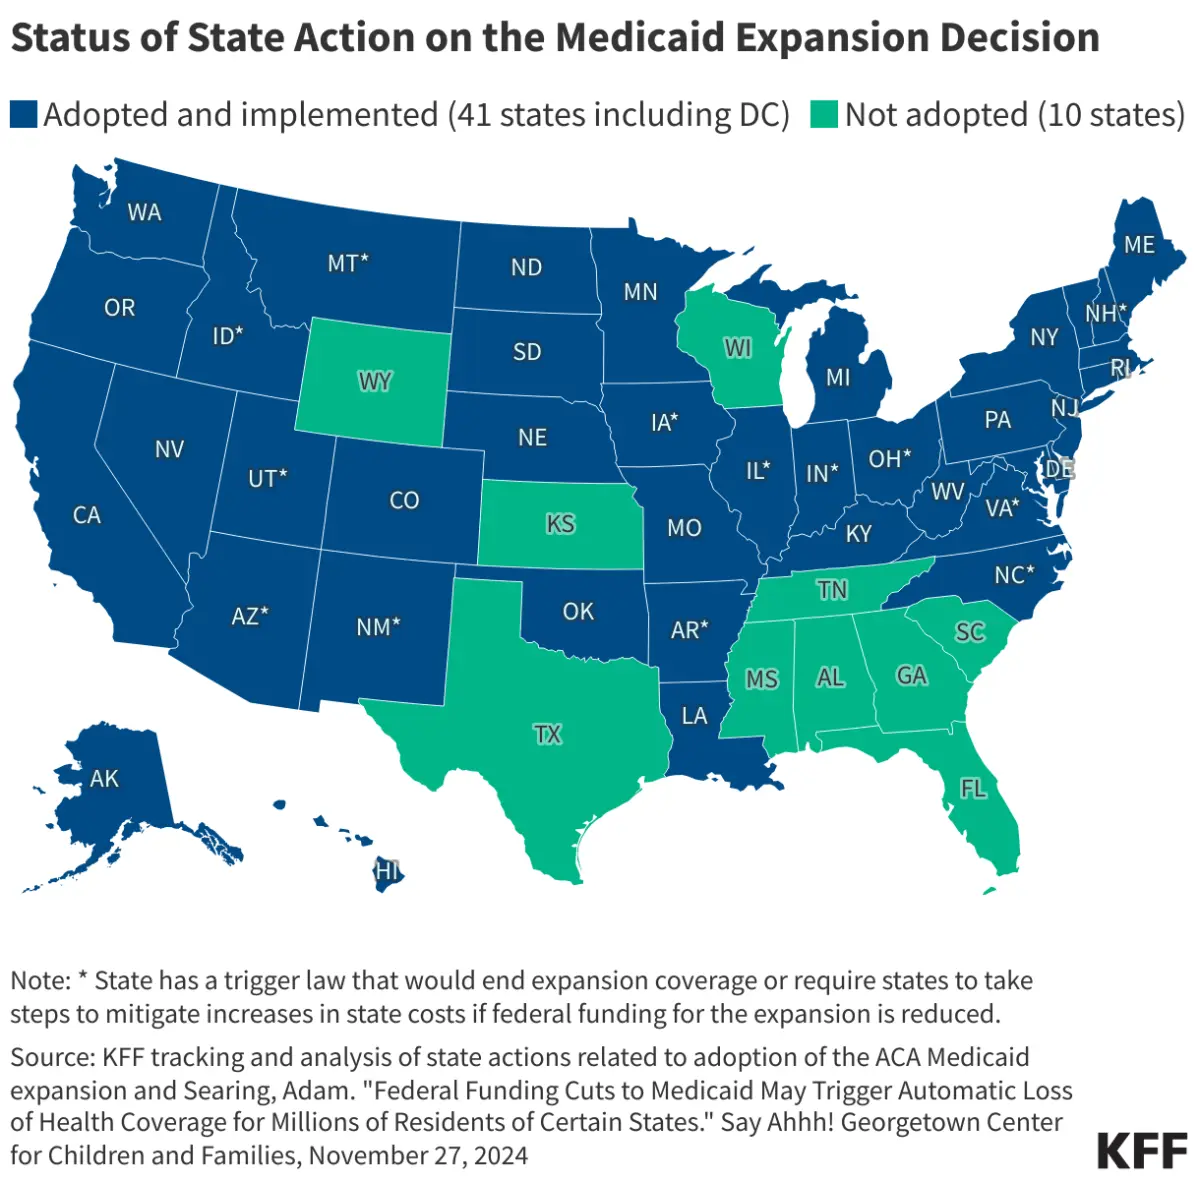
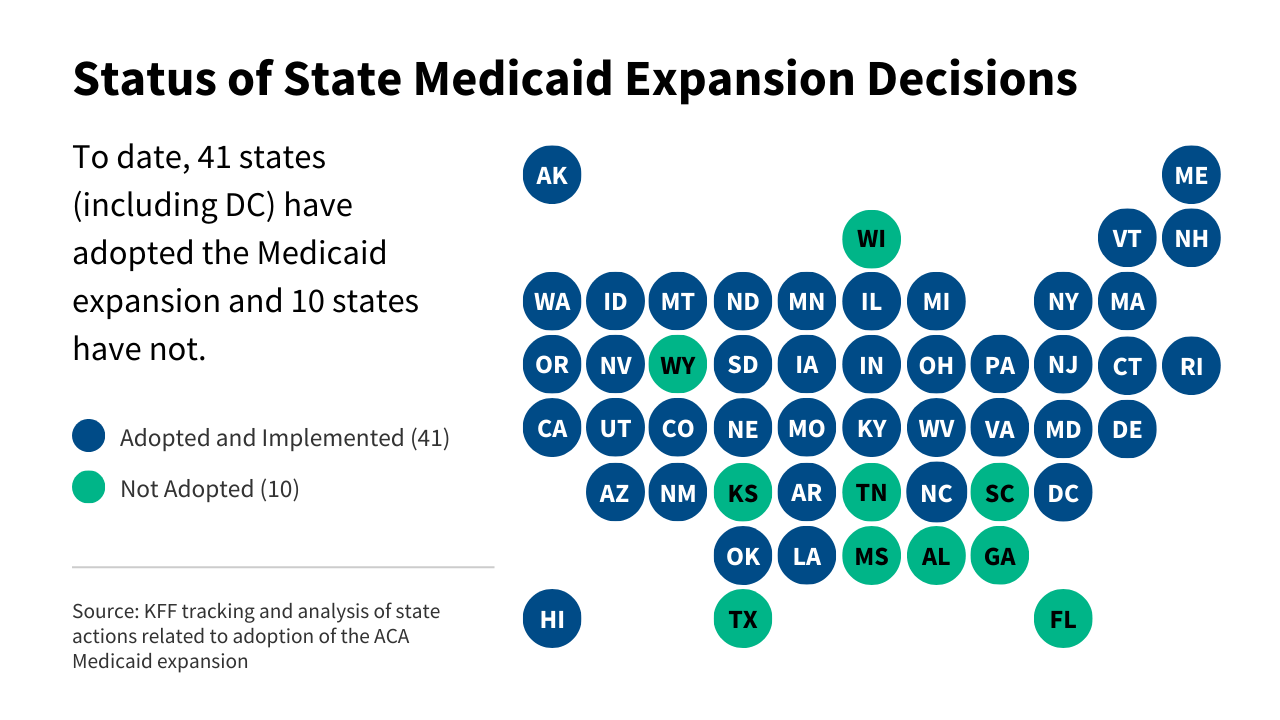
As of late 2024 and heading into 2025, the nation remains split. Forty-one states, including the District of Columbia, have embraced the expansion, while 10 states continue to hold out. This article explores the mechanics, the historical trajectory, the data-driven realities, and the profound implications of this ongoing policy struggle.
The Mechanics of Expansion: Defining the Eligibility Threshold
The ACA’s Medicaid expansion was designed to bridge the "coverage gap" for adults who were previously ineligible for traditional Medicaid—which was historically reserved for specific categories like children, pregnant women, and people with disabilities—but who earned too little to qualify for private insurance subsidies on the ACA marketplace.
Under the federal guidelines, states that opt into the expansion receive an enhanced Federal Medical Assistance Percentage (FMAP), which covers a significant portion of the costs for the expansion population. Eligibility is set at 138% of the Federal Poverty Level (FPL). For the 2025 fiscal year, this translates to an annual income threshold of $21,597 for an individual.
By raising the income cap, the expansion transformed Medicaid from a categorical program into an income-based one for the vast majority of non-elderly adults. This shift was intended to provide a stable foundation of health security, reducing uncompensated care costs for hospitals and improving long-term health outcomes for millions of low-income workers.
A Chronological Look at the Expansion Landscape
The Genesis: 2010–2014
The journey began with the signing of the Affordable Care Act in 2010. However, the legal landscape shifted dramatically in 2012 when the Supreme Court ruled in National Federation of Independent Business v. Sebelius that the federal government could not coerce states into expanding Medicaid by threatening to pull funding for their existing programs. This effectively turned the mandatory expansion into a voluntary one, setting the stage for the state-by-state political tug-of-war that persists today.
The Middle Years: 2015–2020
During this period, expansion became a proxy for the broader political polarization in the United States. While "Blue" states moved quickly to adopt the policy, many "Red" states initially resisted, citing concerns over long-term fiscal sustainability and philosophical objections to the expansion of government programs. However, grassroots pressure—often fueled by rural hospital closures—began to change the narrative. Voters in states like Idaho, Nebraska, and Utah bypassed recalcitrant legislatures through ballot initiatives, forcing expansion into reality.
The Modern Era: 2021–Present
In recent years, the focus has shifted from initial adoption to the implementation of "guardrails" and "trigger laws." States are now navigating the complexities of Section 1115 waivers, which allow them to impose requirements—such as work reporting or premium payments—that deviate from federal standards. Furthermore, the discourse has pivoted toward fiscal contingency, with several states codifying "trigger laws" that would automatically roll back or terminate expansion if federal funding levels were to drop.
Data and Trends: The Current State of Play
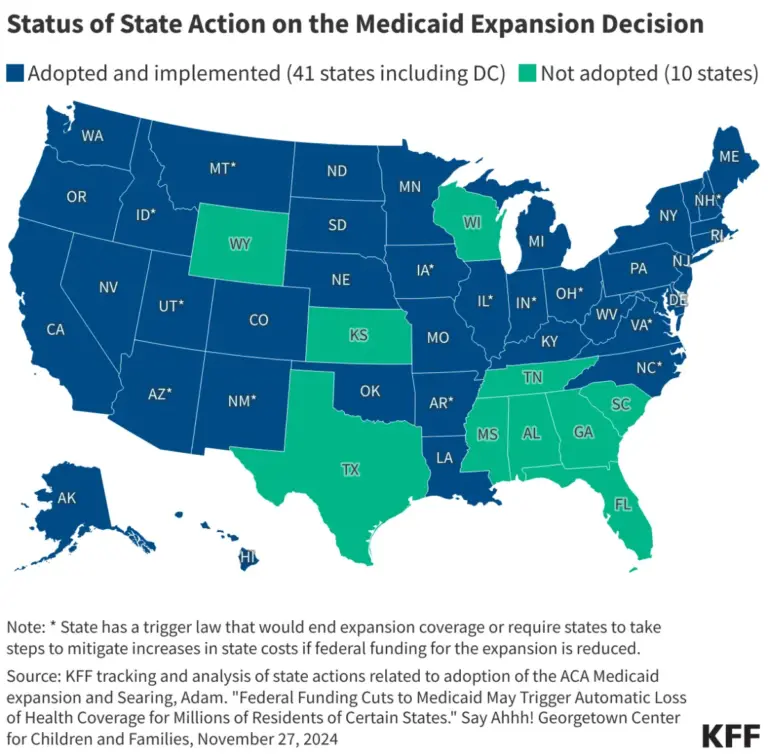
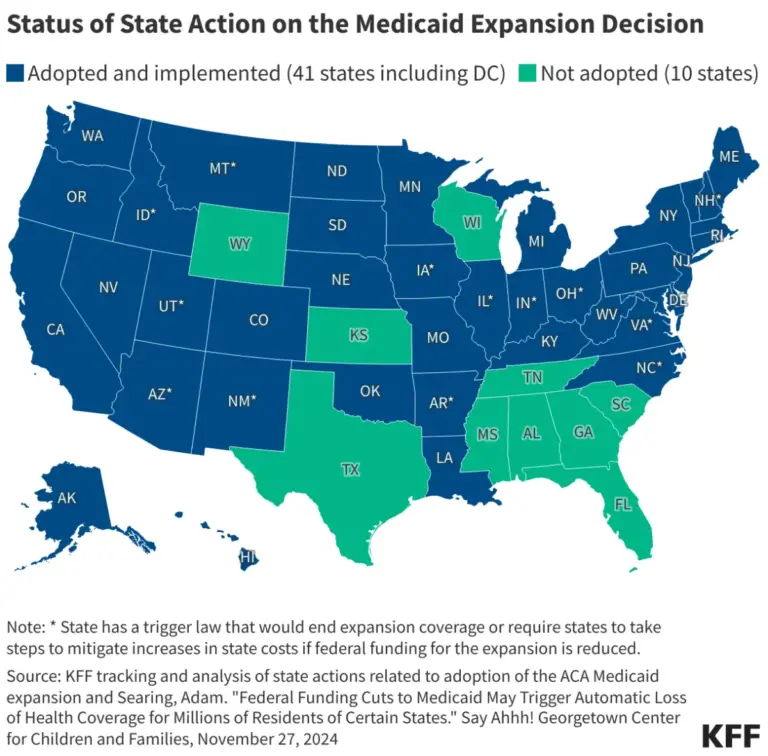
According to the latest tracking from KFF (Kaiser Family Foundation), the current map of the United States reveals a clear geographic trend. The expansion has been widely adopted across the West, Northeast, and much of the Midwest, while the South remains the primary region of non-expansion.
The "Trigger" Phenomenon
A critical, often overlooked aspect of the current debate involves "trigger laws." These legislative mechanisms are designed to protect states from sudden fiscal shocks. For instance, if the federal government were to reduce the FMAP—the rate at which it matches state Medicaid spending—these laws would allow states to automatically scale back or terminate their expansion programs.
States like South Dakota and West Virginia have actively scrutinized these mechanisms. In Virginia, a recent legislative effort sought to remove an automatic termination clause, proposing instead that a committee be formed to manage the transition if federal funding were to fluctuate. This shift signifies a move from "all-or-nothing" politics to more nuanced, risk-averse financial management.
Regional Variations and Limited Expansions
It is essential to distinguish between full ACA expansion and limited coverage programs. Some states, while not technically expanding under the ACA guidelines, have implemented piecemeal, limited coverage expansions. These often fail to qualify for the enhanced federal matching funds, leaving the state to shoulder a larger percentage of the financial burden. These initiatives are often framed as "targeted solutions" to address specific gaps in care, such as maternal health or substance abuse treatment, without committing to the full breadth of the ACA framework.
Official Responses and Political Dynamics
The political arguments surrounding Medicaid expansion are as varied as the states themselves. Proponents argue that expansion is a moral imperative that saves lives, improves economic productivity, and bolsters the financial health of rural healthcare providers. They point to the reduction in the uninsured rate and the improved access to preventative care as evidence of the program’s success.
Conversely, opponents remain wary of the long-term cost burden on state budgets. The primary argument against expansion centers on the fear of future federal austerity. If the federal government were to reduce its contribution, state taxpayers would be forced to cover the shortfall or face significant service cuts. This "fiscal sovereignty" argument is the bedrock of the opposition in the remaining 10 non-expansion states.
Furthermore, some policymakers advocate for private-sector alternatives, arguing that subsidized private insurance through the ACA marketplace is a more efficient delivery mechanism than expanding a public entitlement program.
Implications: The Future of American Healthcare
The implications of the current status quo are profound. For residents in non-expansion states, the "coverage gap" remains a stark reality. These individuals earn too much for traditional Medicaid but too little to afford private insurance, leaving them effectively invisible to the healthcare system until they encounter a catastrophic medical emergency.
The Economic Impact
For states, the economic ripple effects are significant. Expansion states often see a net positive impact on their budgets due to increased tax revenue from a healthier workforce and the influx of federal dollars into their healthcare sectors. In contrast, non-expansion states continue to see high rates of uncompensated care, which places a heavy burden on hospitals—particularly rural facilities that operate on razor-thin margins.
The Long-Term Stability Challenge
The stability of the Medicaid expansion is not guaranteed. As the political climate shifts, the federal-state partnership is under constant pressure. The prevalence of trigger laws suggests that state governments are preparing for a future where federal funding is less certain. This atmosphere of skepticism hampers long-term planning and leaves millions of Americans in a state of perpetual uncertainty regarding their coverage.
Moving Toward Equity
Achieving universal or near-universal coverage in the United States requires reconciling these state-level differences. The ongoing debate over the ACA is no longer just about whether to expand, but how to sustain the expansion in a way that respects state fiscal constraints while ensuring equitable access to care. As we look toward the mid-2020s, the focus will likely remain on legislative adjustments, the role of 1115 waivers, and the potential for federal policy interventions that provide states with more flexibility to maintain these programs.
Conclusion
The Medicaid expansion under the Affordable Care Act remains one of the most consequential health policy developments in modern American history. It has successfully insured millions, stabilized the finances of countless healthcare providers, and fundamentally changed the relationship between the state and the citizen in terms of health responsibility.
However, the fact that 10 states have yet to adopt the expansion serves as a reminder of the deep-seated ideological and economic fissures that define the American landscape. Whether through future ballot initiatives, legislative compromises, or shifts in federal policy, the evolution of the Medicaid expansion will continue to be a primary driver of the nation’s health equity agenda. For now, the "Great Divide" persists—a testament to the ongoing struggle to balance the promise of universal care with the realities of federalism and fiscal policy.
About the Author