The landscape of American foreign assistance has undergone its most radical transformation in decades. Following the dissolution of the U.S. Agency for International Development (USAID) and a sweeping reorganization of global health programs, the U.S. State Department has formally transitioned to a model centered on the America First Global Health Strategy (AFGHS). As of late 2026, this pivot—initiated during President Trump’s second administration—has reached a critical implementation phase, signaling a departure from traditional multilateral development aid toward a highly structured, bilateral, and co-investment-based framework.
The Genesis of a New Paradigm: Main Facts
The America First Global Health Strategy, launched in September 2025, represents the culmination of a multi-year effort to centralize and reorient U.S. health investments. At its core, the policy moves away from the decentralized project-based funding that characterized previous administrations. Instead, the U.S. now relies on bilateral Memoranda of Understanding (MOUs) negotiated directly with partner nations.
As of late 2026, the U.S. has secured 36 such agreements, representing a total financial commitment of $26.7 billion. Of this, the U.S. has pledged $15.9 billion, with partner nations contractually obligated to provide $10.3 billion in co-investment. This "skin in the game" requirement is a hallmark of the new strategy, intended to ensure sustainability and local ownership of health outcomes.
To facilitate the operationalization of these MOUs, the State Department introduced the "Advancing Global Health" Annual Program Statement (AGH/APS). This competitive funding mechanism acts as a bridge, allowing the U.S. to solicit specialized applications from private for-profit enterprises, universities, faith-based organizations, and public institutions to execute the goals set out in the bilateral agreements.
A Chronology of the Transition
The timeline of this transition reflects the administrative urgency of the second Trump term:
- Early 2025: The administration announces the reduction of supported global health projects and the formal dissolution of USAID’s independent authority, shifting oversight to the State Department’s Bureau of Global Health Security and Diplomacy.
- September 2025: The America First Global Health Strategy is officially released, establishing the framework for bilateral MOUs.
- March 2026: The State Department announces the AGH/APS, an open-ended funding mechanism designed to distribute up to $4.5 billion over four windows.
- March–October 2026: The first three funding windows are completed, resulting in the release of 12 "addenda" (specific solicitations for projects) totaling $1.43 billion.
- November 2026–January 2027: The fourth and final funding window is initiated, aiming to finalize the allocation of the remaining $3 billion in the APS budget.
Supporting Data: The Anatomy of Funding
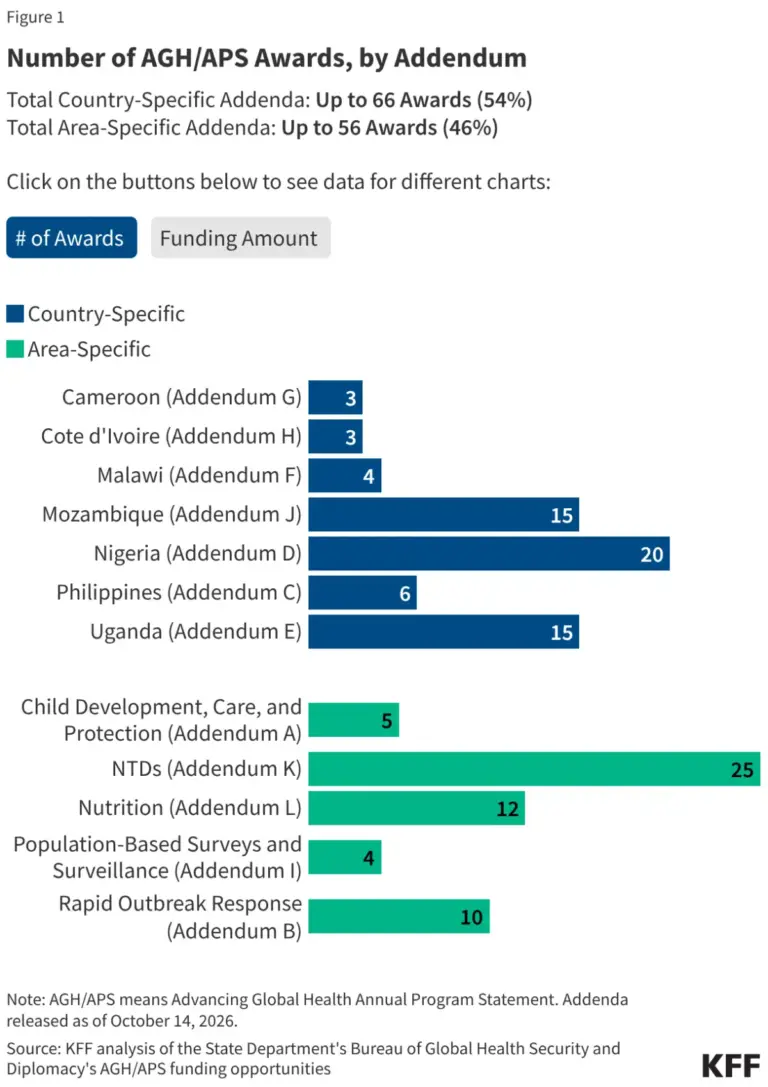
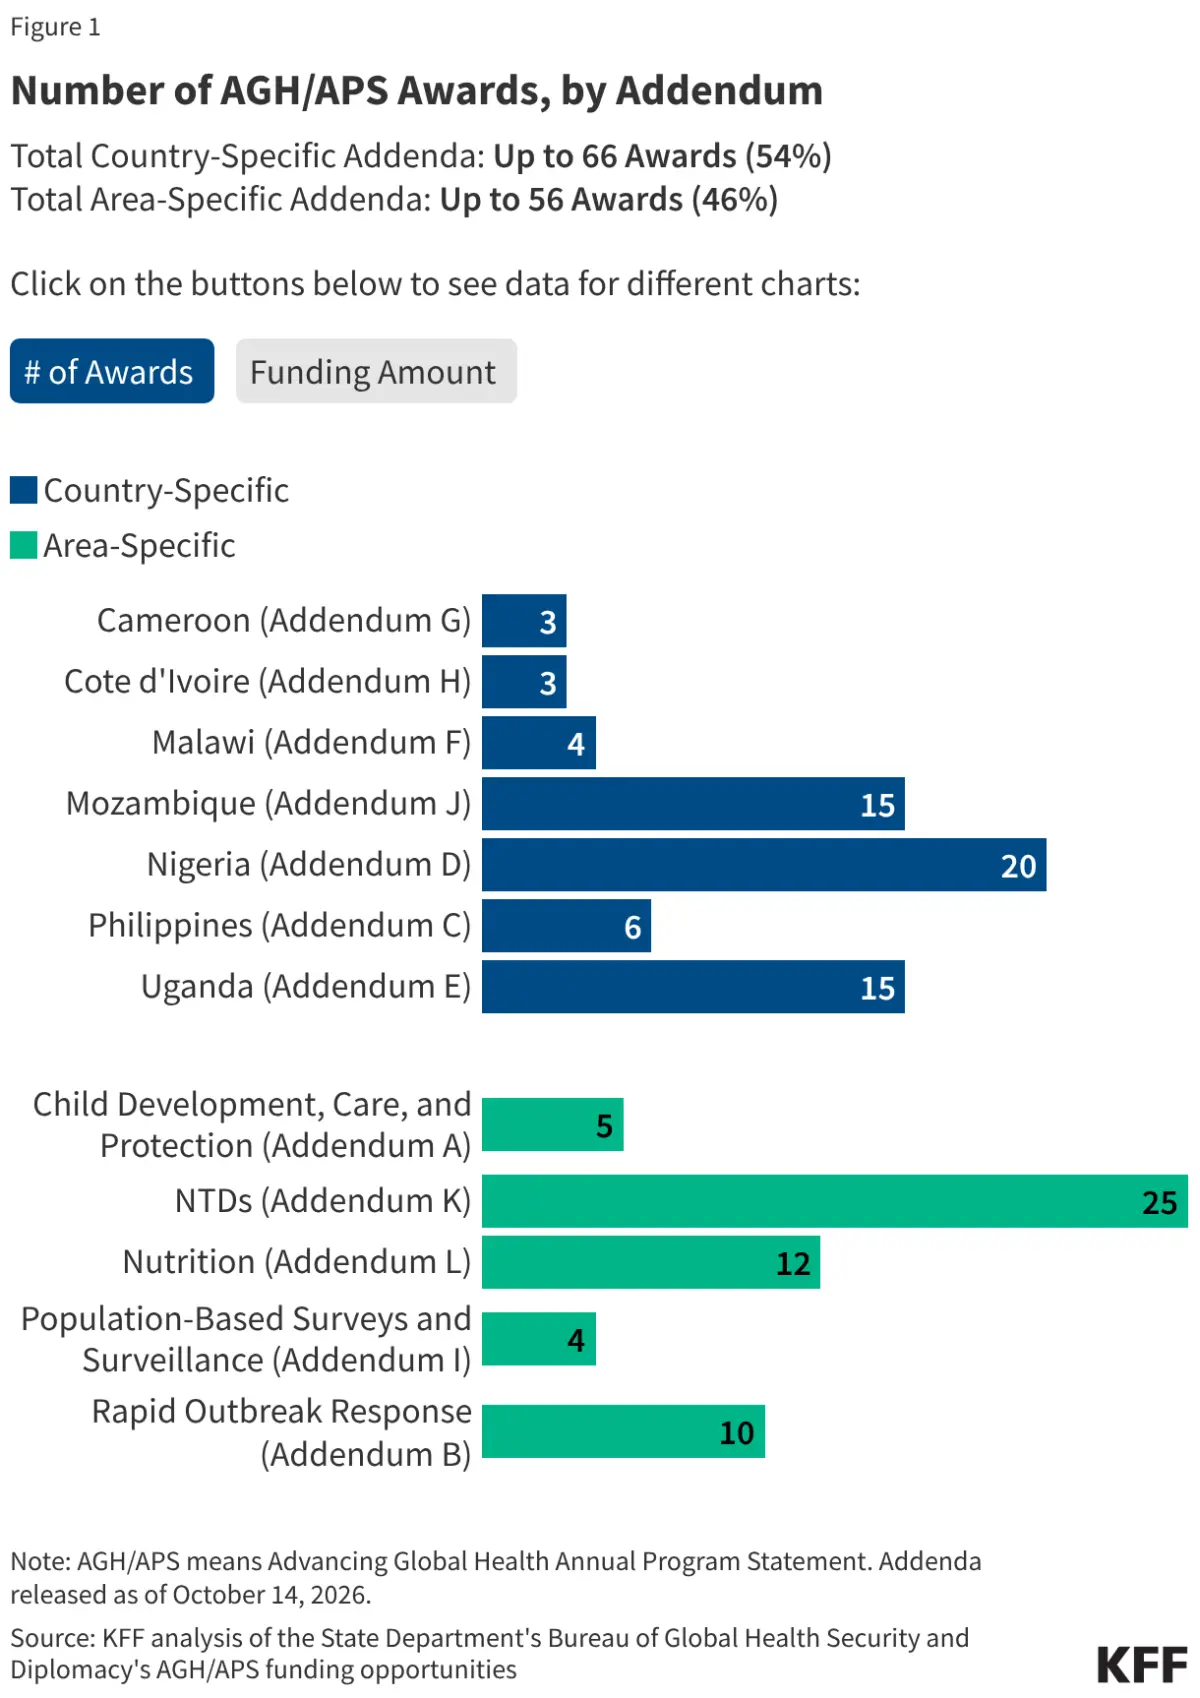
The data gathered from the first three funding windows provides a clear picture of where U.S. priorities lie under the new regime. The $1.43 billion committed across 122 potential awards is split almost evenly between country-specific initiatives (51%) and area-specific global health programming (49%).
Country-Specific Focus
The country-specific addenda focus on high-burden nations where the U.S. has deep-seated interests. Nigeria and the Philippines stand out as the largest recipients, with $200 million allocated to each. Nigeria’s funding focuses on expanding health insurance, digital health integration, and laboratory infrastructure, while the Philippines program emphasizes U.S. technology standards and private-sector partnerships. Other key partners include Mozambique ($180M), Uganda ($60M), and Cote d’Ivoire ($50M).
Area-Specific Priorities
The area-specific addenda reveal a strategic focus on health security and sustainability:
- Rapid Outbreak Response: $290 million allocated to ensure the U.S. and its partners can contain infectious threats at their source.
- Neglected Tropical Diseases (NTDs): $162 million targeted at 31 countries across three continents, emphasizing the elimination of disease transmission.
- Nutrition and Child Health: Over $167 million combined, focusing on the critical "first 1,000 days" of development and sustainable nutrition financing.
Official Responses and Strategic Rationale
The State Department has positioned this shift as a move toward "accountable, sustainable, and transparent" aid. By moving toward Government-to-Government (G2G) funding agreements, the administration argues it is eliminating the "middleman" of international non-governmental organizations (INGOs) that previously managed the bulk of U.S. global health aid.
According to briefing materials provided by the Bureau of Global Health Security and Diplomacy, the primary rationale for this shift is "fiscal sovereignty." By requiring partner countries to contribute a significant portion of the total funding envelope, the U.S. claims to be fostering a "graduation" model where countries eventually phase out the need for American assistance entirely.

Critics, however, have raised concerns about the transition’s speed and the capacity of local governments to manage large-scale funding. Public health advocates point out that while G2G funding is a stated goal, the infrastructure to manage these billions in a transparent manner is still, by the State Department’s own admission, "nascent."
Implications for Global Health
The move to the AFGHS model creates several critical implications for the future of global health:
1. The Rise of Private-Sector Involvement
The inclusion of "U.S. and foreign private for-profit enterprises" as eligible applicants for APS funding marks a sea change. The U.S. is explicitly looking to export its own technological and commercial solutions—such as digital health platforms and supply chain innovations—rather than relying solely on traditional development contractors. This effectively turns global health aid into a vehicle for U.S. market expansion.
2. Concentration of Power in the State Department
By consolidating decision-making within the State Department, the administration has moved global health out of the realm of "development aid" and firmly into the realm of "foreign policy." This implies that future health spending will be more closely tethered to bilateral diplomatic relations and geopolitical alignment with Washington.
3. Risk to Vulnerable Populations
The transition risks creating a "funding gap" during the shift from legacy USAID projects to new G2G or private-sector-led initiatives. While the $1.43 billion in new funding is significant, the total loss of the USAID ecosystem, which managed long-term, multi-generational health programs, could lead to a decline in service delivery in countries that lack the immediate capacity to take over these responsibilities.
4. The Sustainability Challenge
The "co-investment" model is ambitious. While it works well in middle-income countries with established tax bases, it remains to be seen whether the poorest partner nations will be able to sustain their 30-40% share of health expenditures over the long term. If a partner country fails to meet its co-investment goals, the bilateral agreement remains in a state of legal and financial limbo, potentially cutting off funding entirely.
Future Outlook: Monitoring the Implementation
As the world moves into 2027, the focus of the global health community will be on the actual distribution of the 122 awards announced in the first three windows. To date, no awards have been publicly finalized, creating a period of extreme uncertainty for existing health projects on the ground.
Monitoring the implementation of these MOUs will be essential. If the G2G model succeeds, it may well provide a blueprint for a more efficient, host-country-led future for global health. However, if the transition proves too rapid or if the focus on private-sector partnerships neglects the foundational, non-profitable aspects of public health, the consequences for maternal health, disease surveillance, and epidemic readiness could be severe.
For now, the U.S. global health landscape is in a state of managed flux. The America First strategy is no longer a set of theoretical policy goals; it is a live, multibillion-dollar experiment in international development. Whether it succeeds in building sustainable health systems or merely shifts the burden of risk onto fragile nations remains the defining question of the decade.
About the Author