Introduction: The Power of Section 1115
Section 1115 of the Social Security Act stands as one of the most consequential tools in American healthcare policy. It grants the Secretary of Health and Human Services (HHS) the authority to approve “demonstration waivers,” allowing states to bypass traditional federal Medicaid statutes to test innovative approaches. These waivers are intended to “promote the objectives of the Medicaid program,” but in practice, they have become a primary theater for the ideological tug-of-war between presidential administrations.
As of late 2026, the Medicaid landscape is undergoing a significant transformation. Following the transition of power in early 2025, the policy priorities governing these waivers have shifted dramatically. From the rescission of Health-Related Social Needs (HRSN) guidance to the impending implementation of federal work requirements, the regulatory environment for state Medicaid programs is in a state of flux. This article tracks the evolution of these waivers, the legislative mandates shaping them, and the implications for millions of low-income Americans.
The Core Mechanisms of Change
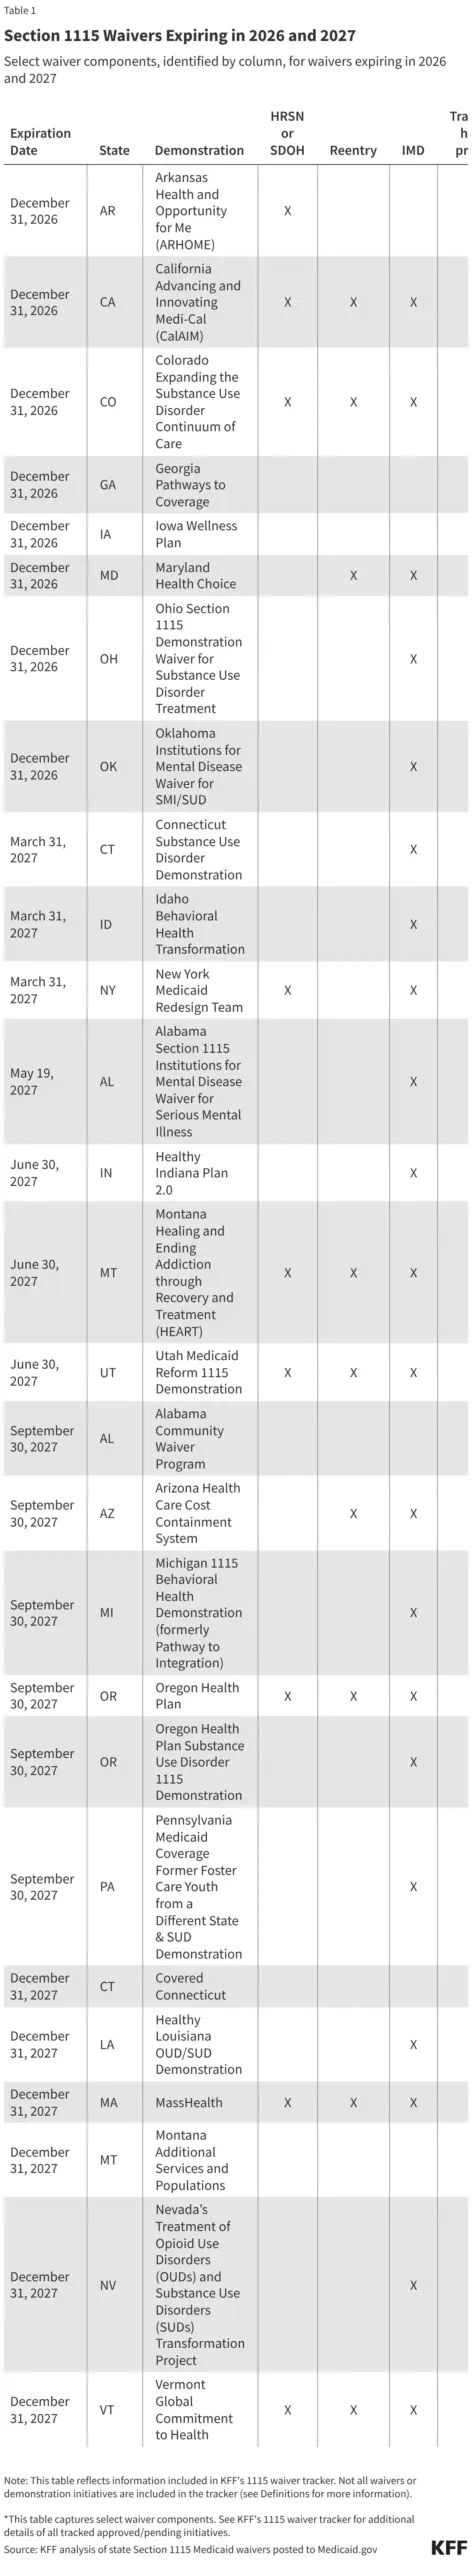
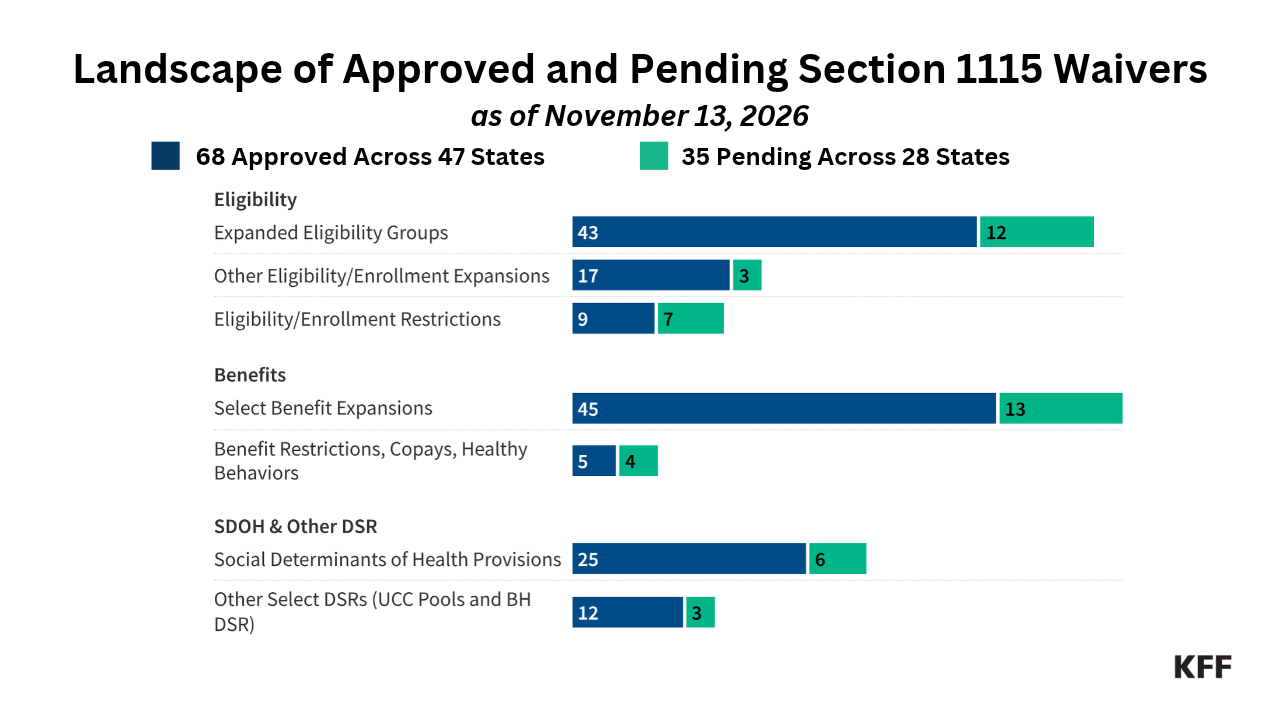
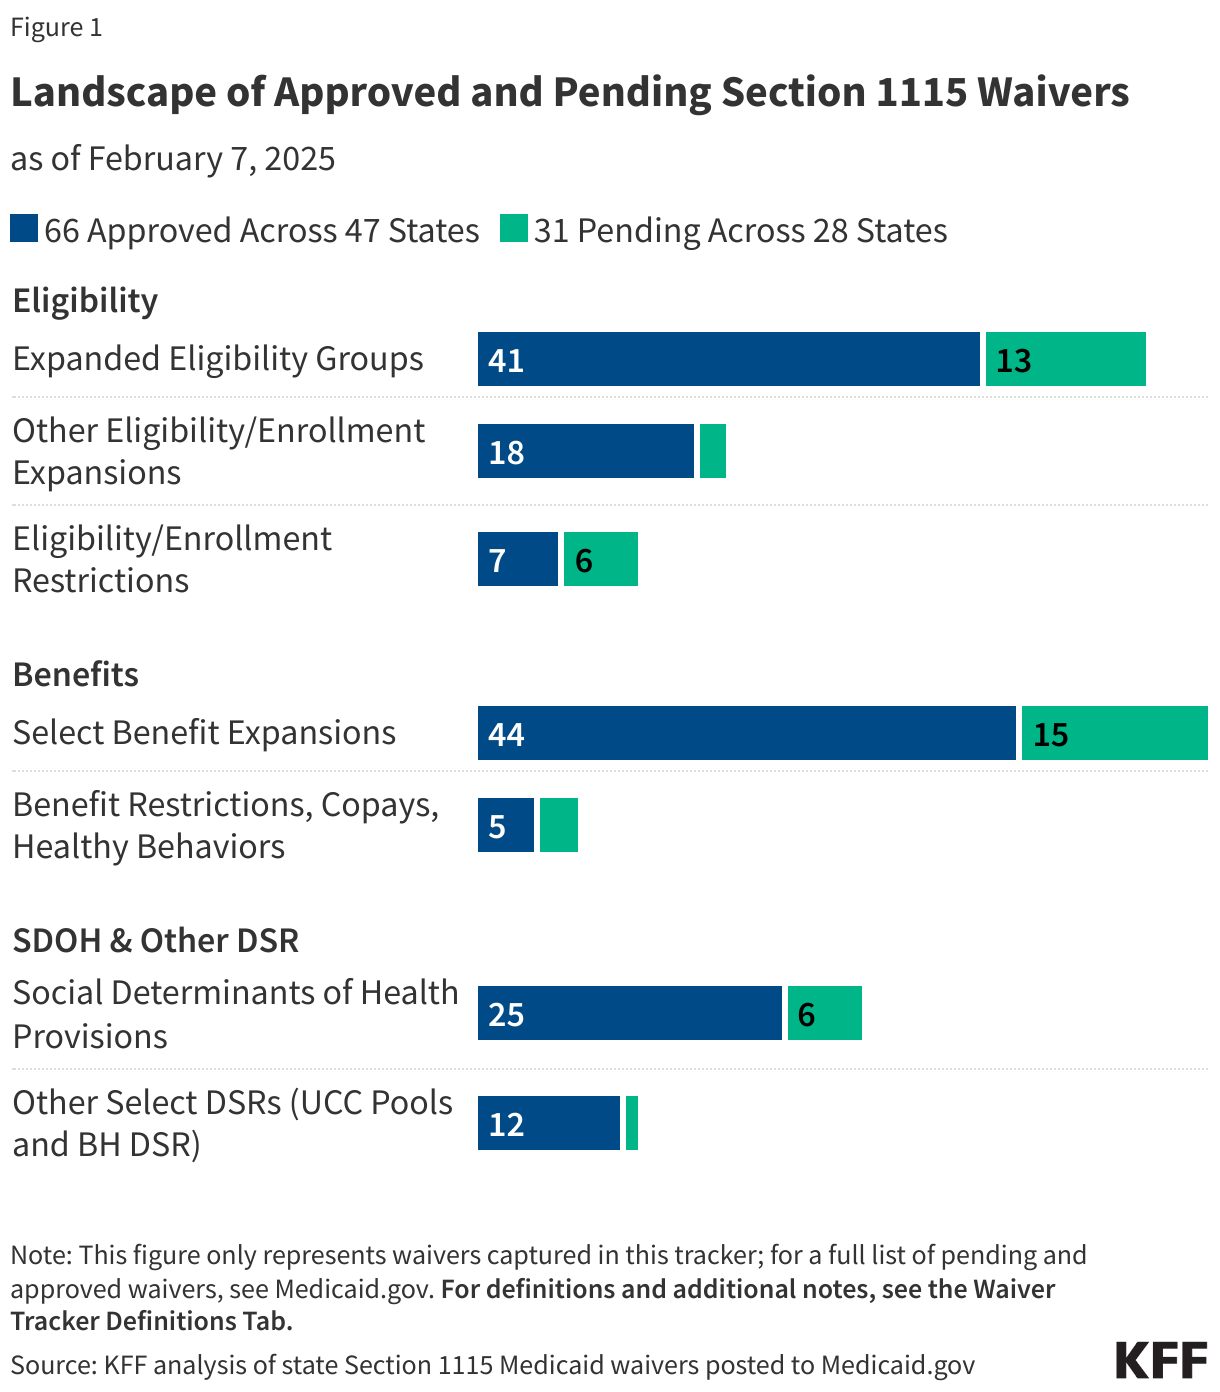
Section 1115 waivers allow states to experiment with eligibility criteria, benefit packages, and delivery system reforms. While nearly every state currently operates at least one active waiver, the nature of these programs is highly sensitive to the political climate in Washington.
For the past several years, the central tension has involved the balance between "expanding access" and "enforcing personal responsibility." Under the Biden administration, waivers frequently prioritized continuous eligibility for children, addressing social determinants of health (SDOH), and supporting reentry for incarcerated individuals. Conversely, the current administration has moved to prioritize work requirements, phase out specific funding streams like "Designated State Health Programs" (DSHP), and terminate support for multi-year continuous eligibility.
Chronology of Policy Shifts (2025–2026)
The last twenty-four months have been defined by rapid administrative adjustments:
- January 2025: A new federal administration takes office, signaling a departure from the previous emphasis on broad-based Medicaid expansion support.
- March 2025: The Centers for Medicare & Medicaid Services (CMS) formally rescinds the Biden-era guidance on Health-Related Social Needs (HRSN). While existing approvals remain valid, the door for new, broad-based social support funding is narrowed to a strict "case-by-case" review.
- April 2025: CMS announces the phase-out of federal funding for Designated State Health Programs (DSHP), a move that puts financial pressure on states that relied on these funds to bolster their Medicaid infrastructure.
- July 2025: In a major policy reversal, the administration releases guidance confirming that it will neither approve new nor extend existing waivers for continuous Medicaid eligibility for children or adults.
- January 2027 (Upcoming): The mandatory implementation of federal work requirements for ACA expansion adults, as dictated by the 2025 tax and spending reconciliation law, takes effect.
- October 2028: The prohibition on enrollment fees and premiums for ACA expansion adults becomes effective, a final vestige of legislative protections that survive the current administrative shifts.
Work Requirements: A New Era of Enforcement
Perhaps the most contentious issue in current Medicaid policy is the implementation of work requirements. Historically, these requirements faced intense litigation and administrative resistance. However, the 2025 federal budget law fundamentally changed the legal playing field by codifying mandatory work requirements for ACA expansion adults.
The Shift to State Plan Amendments (SPAs)
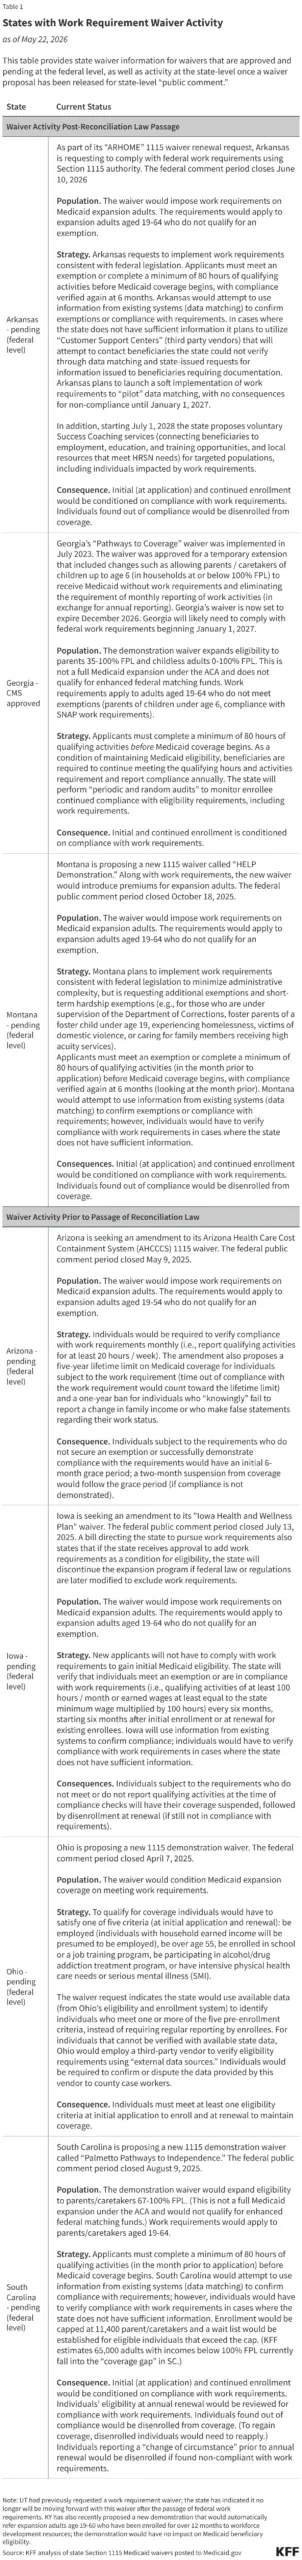
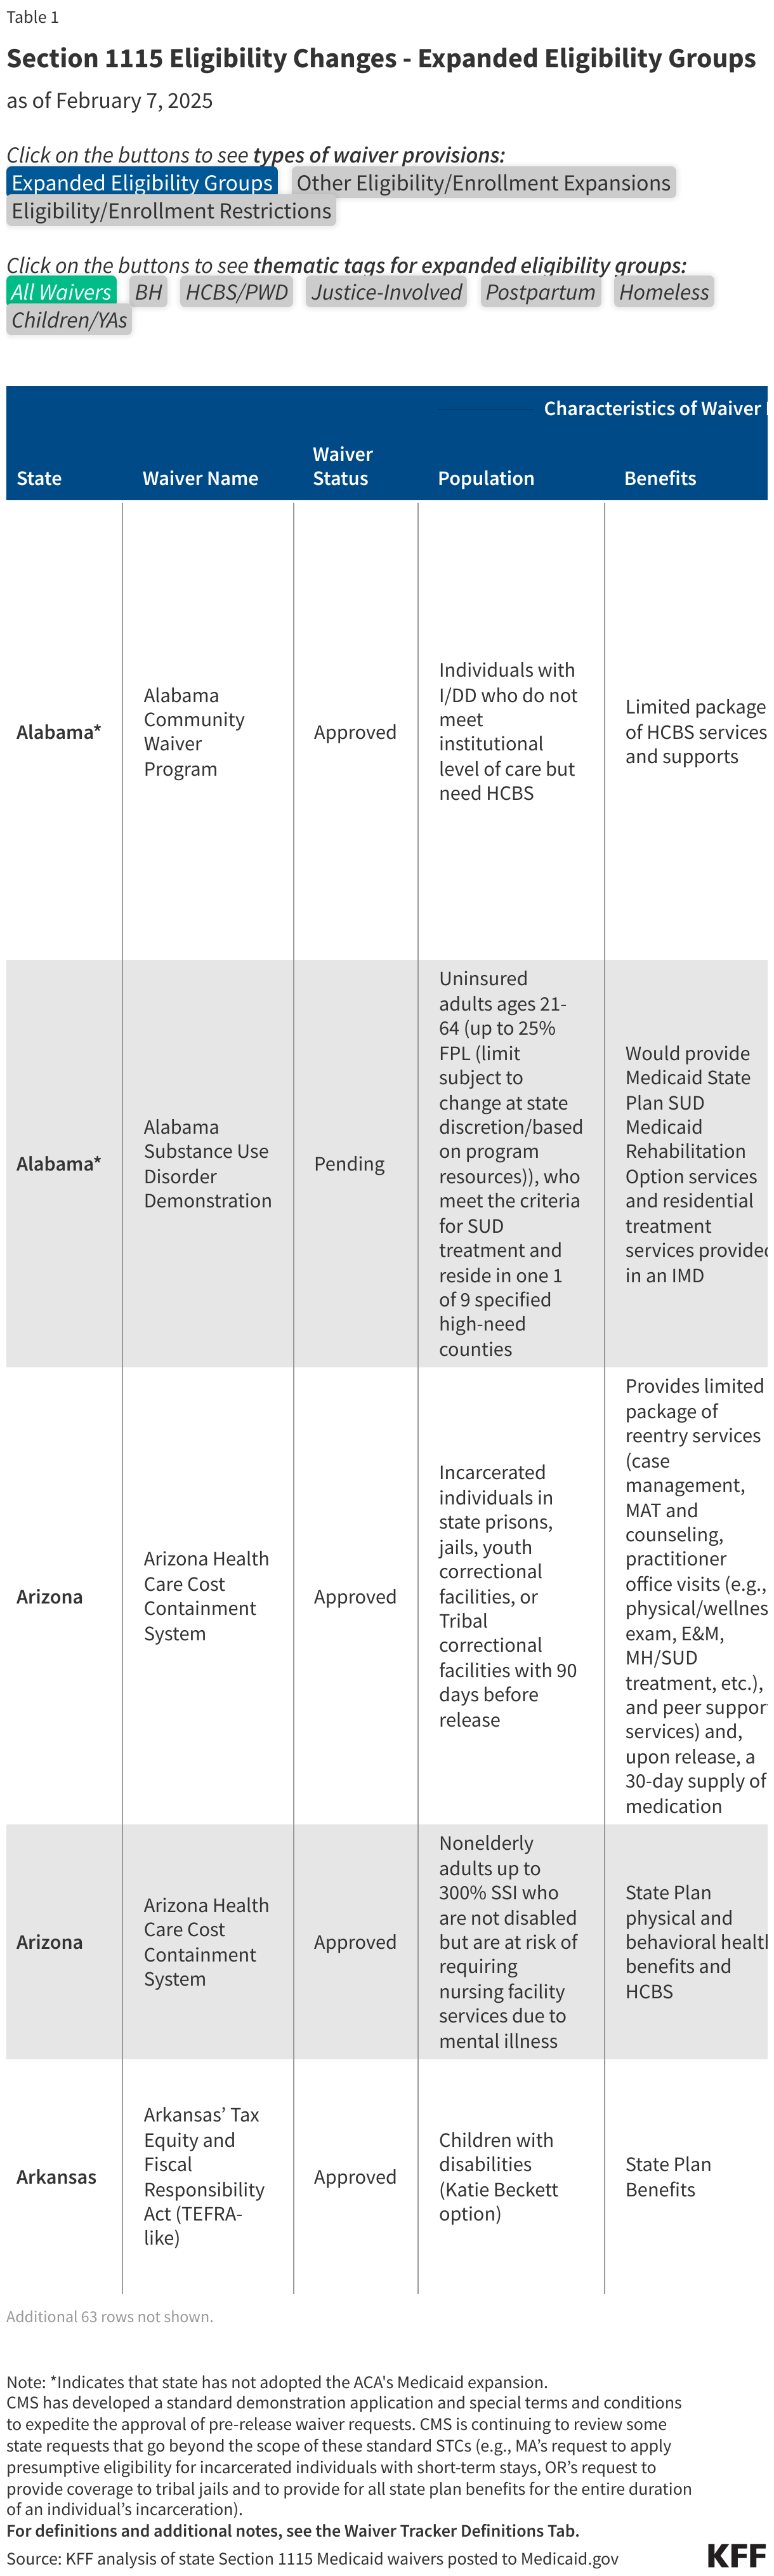
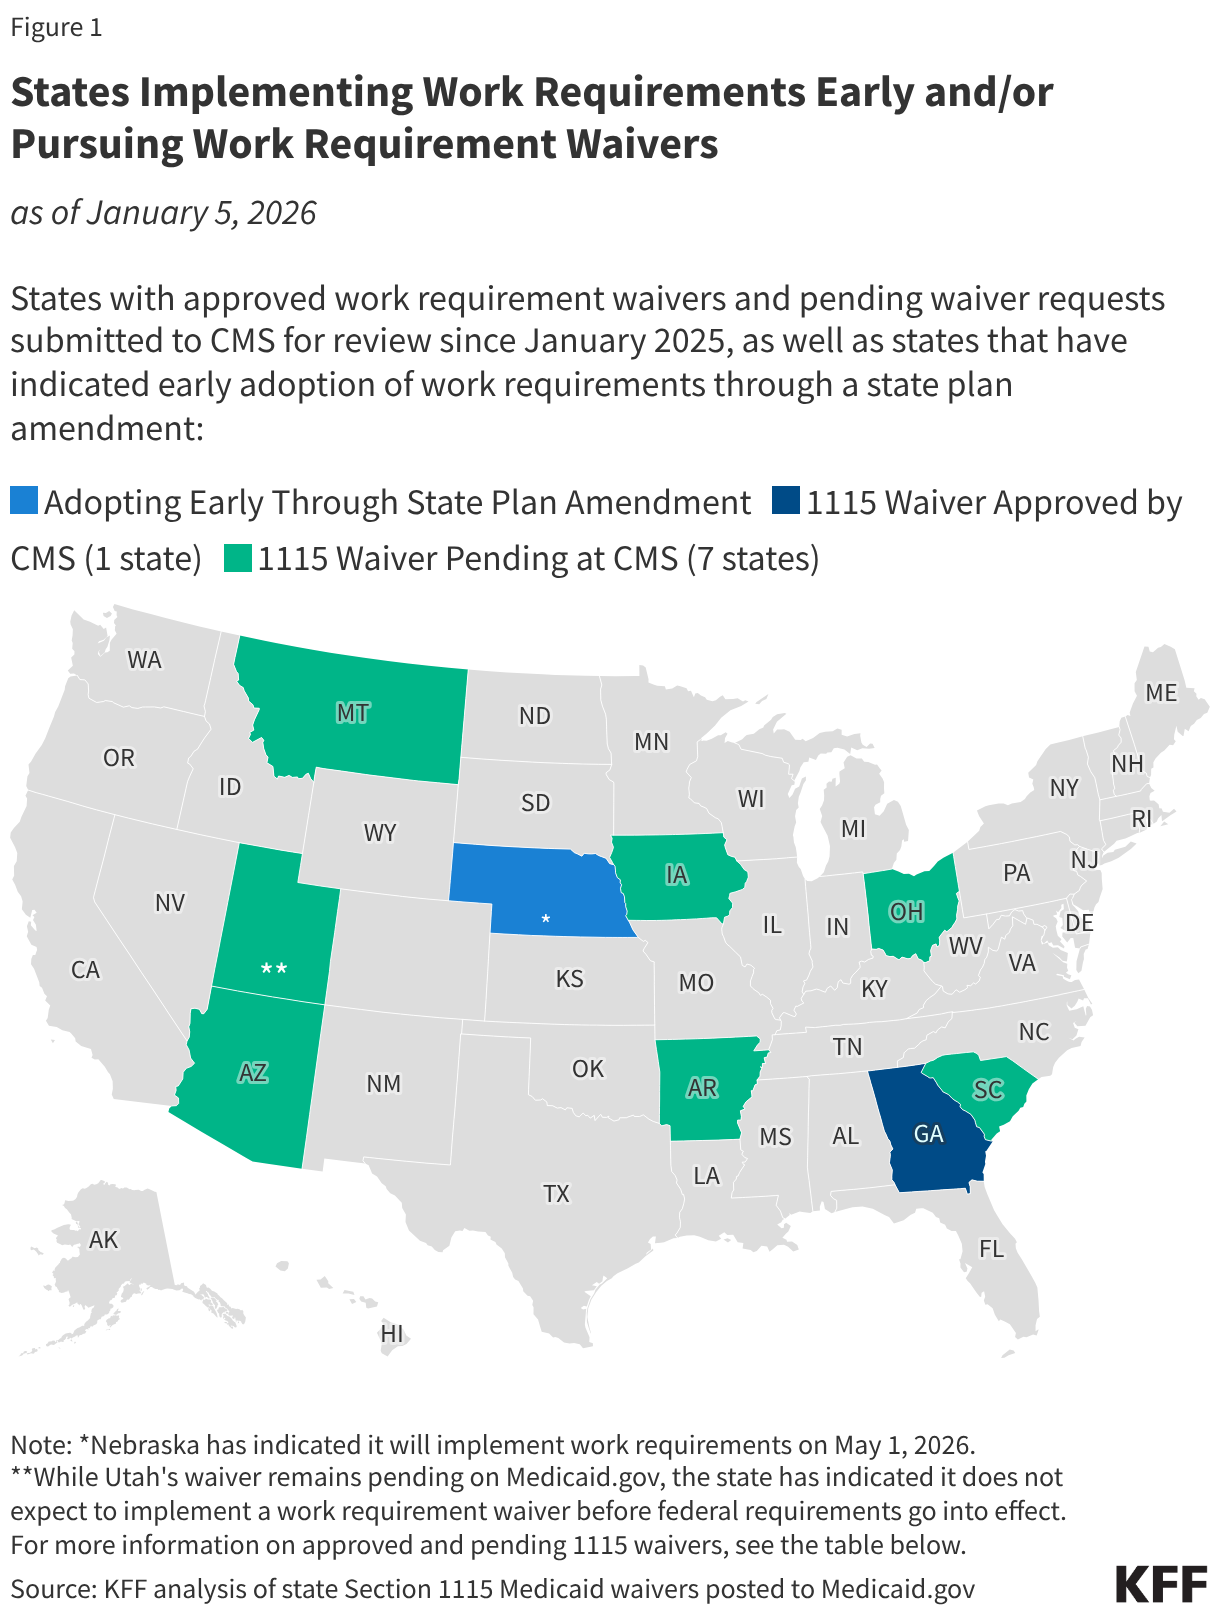
While states previously used Section 1115 waivers to pursue work requirements, the 2025 law provides a new federal mandate. States looking to enforce these rules early—before the national deadline of January 1, 2027—are now opting for State Plan Amendments (SPAs) rather than the more cumbersome waiver process.
Nebraska, for instance, has announced an early enforcement date of May 1, 2026. Montana and Iowa are following suit, with implementation dates later in 2026. Arkansas has opted for a "soft" launch, testing the infrastructure without initiating disenrollments until the federal deadline.
The Status of Georgia
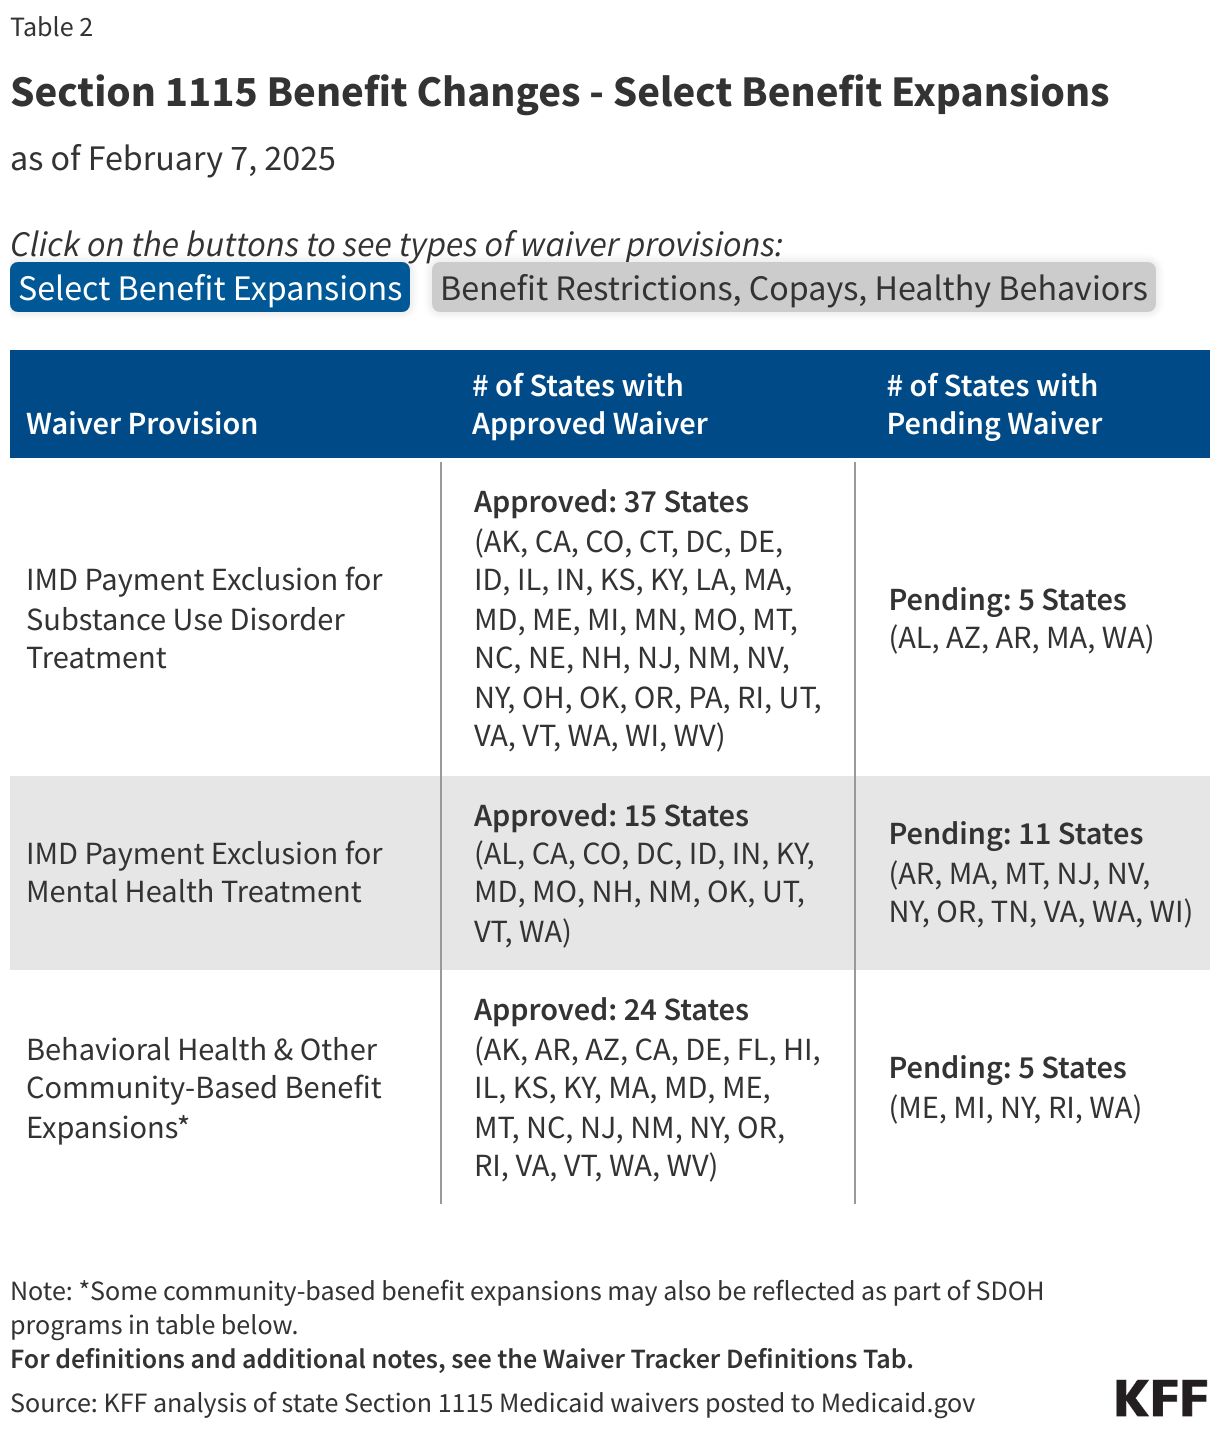
Georgia remains a unique case study. Following successful litigation against the previous administration’s attempts to halt its program, Georgia currently operates the only active, court-upheld work requirement waiver. However, the state’s current authority is set to expire on December 31, 2026. At that point, Georgia will be required to transition into compliance with the new federal standard, marking the end of its experimental phase.
Addressing Social Determinants of Health (SDOH)
The movement to integrate housing, nutrition, and environmental support into Medicaid—collectively known as Health-Related Social Needs (HRSN)—gained significant momentum under the previous administration. States were encouraged to use Section 1115 authority to provide non-medical services, such as rent support for the homeless or nutritional counseling for those with chronic illnesses.

The current administration’s decision to rescind the overarching HRSN framework does not mean the end of these programs, but it significantly raises the barrier to entry. Future state applications will be scrutinized under a much more restrictive lens. The "case-by-case" policy suggests that states must now justify these investments as strictly clinical in nature, rather than broad public health initiatives.
Supporting Reentry: The Inmate Exclusion Policy
One area of bipartisan consensus—though implemented through different methodologies—is the effort to reduce recidivism through better healthcare transitions. The "inmate exclusion policy" traditionally forbids Medicaid from paying for services during incarceration. However, recent waivers allow for pre-release coverage, ensuring that individuals leaving the justice system have immediate access to medication and mental health services.
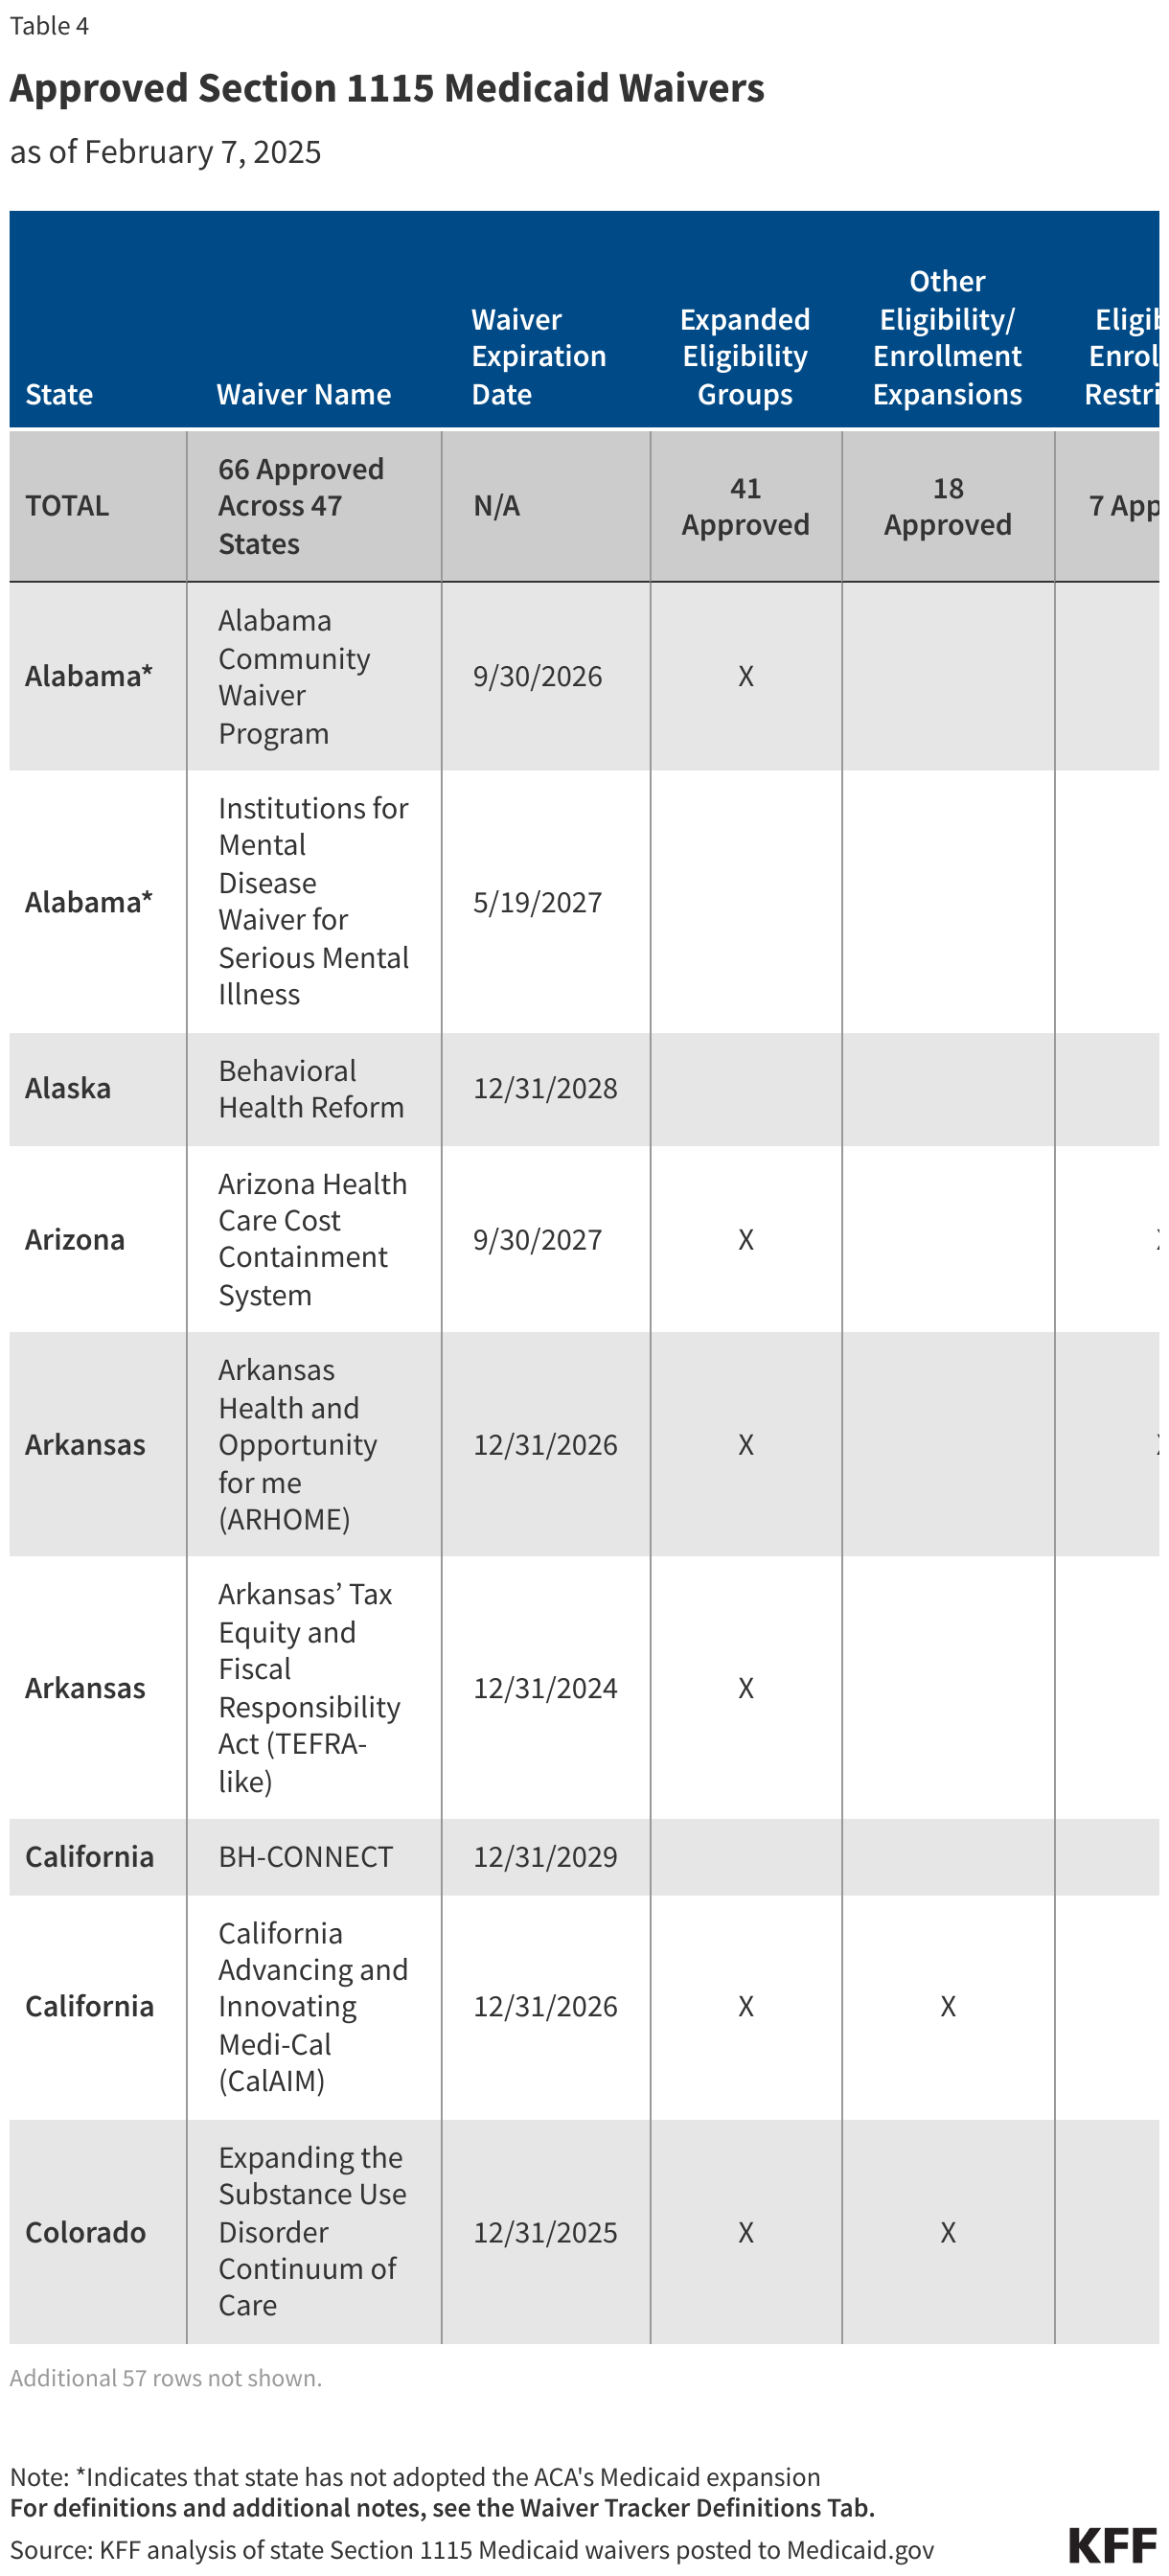
The Biden administration approved 19 such waivers. In September 2026, the current administration approved an additional five, signaling that while the approach to "social" waivers is tightening, the focus on reentry services remains a priority, likely due to its potential for long-term fiscal savings and public safety benefits.
Implications for the Future of Medicaid
The End of Continuous Eligibility
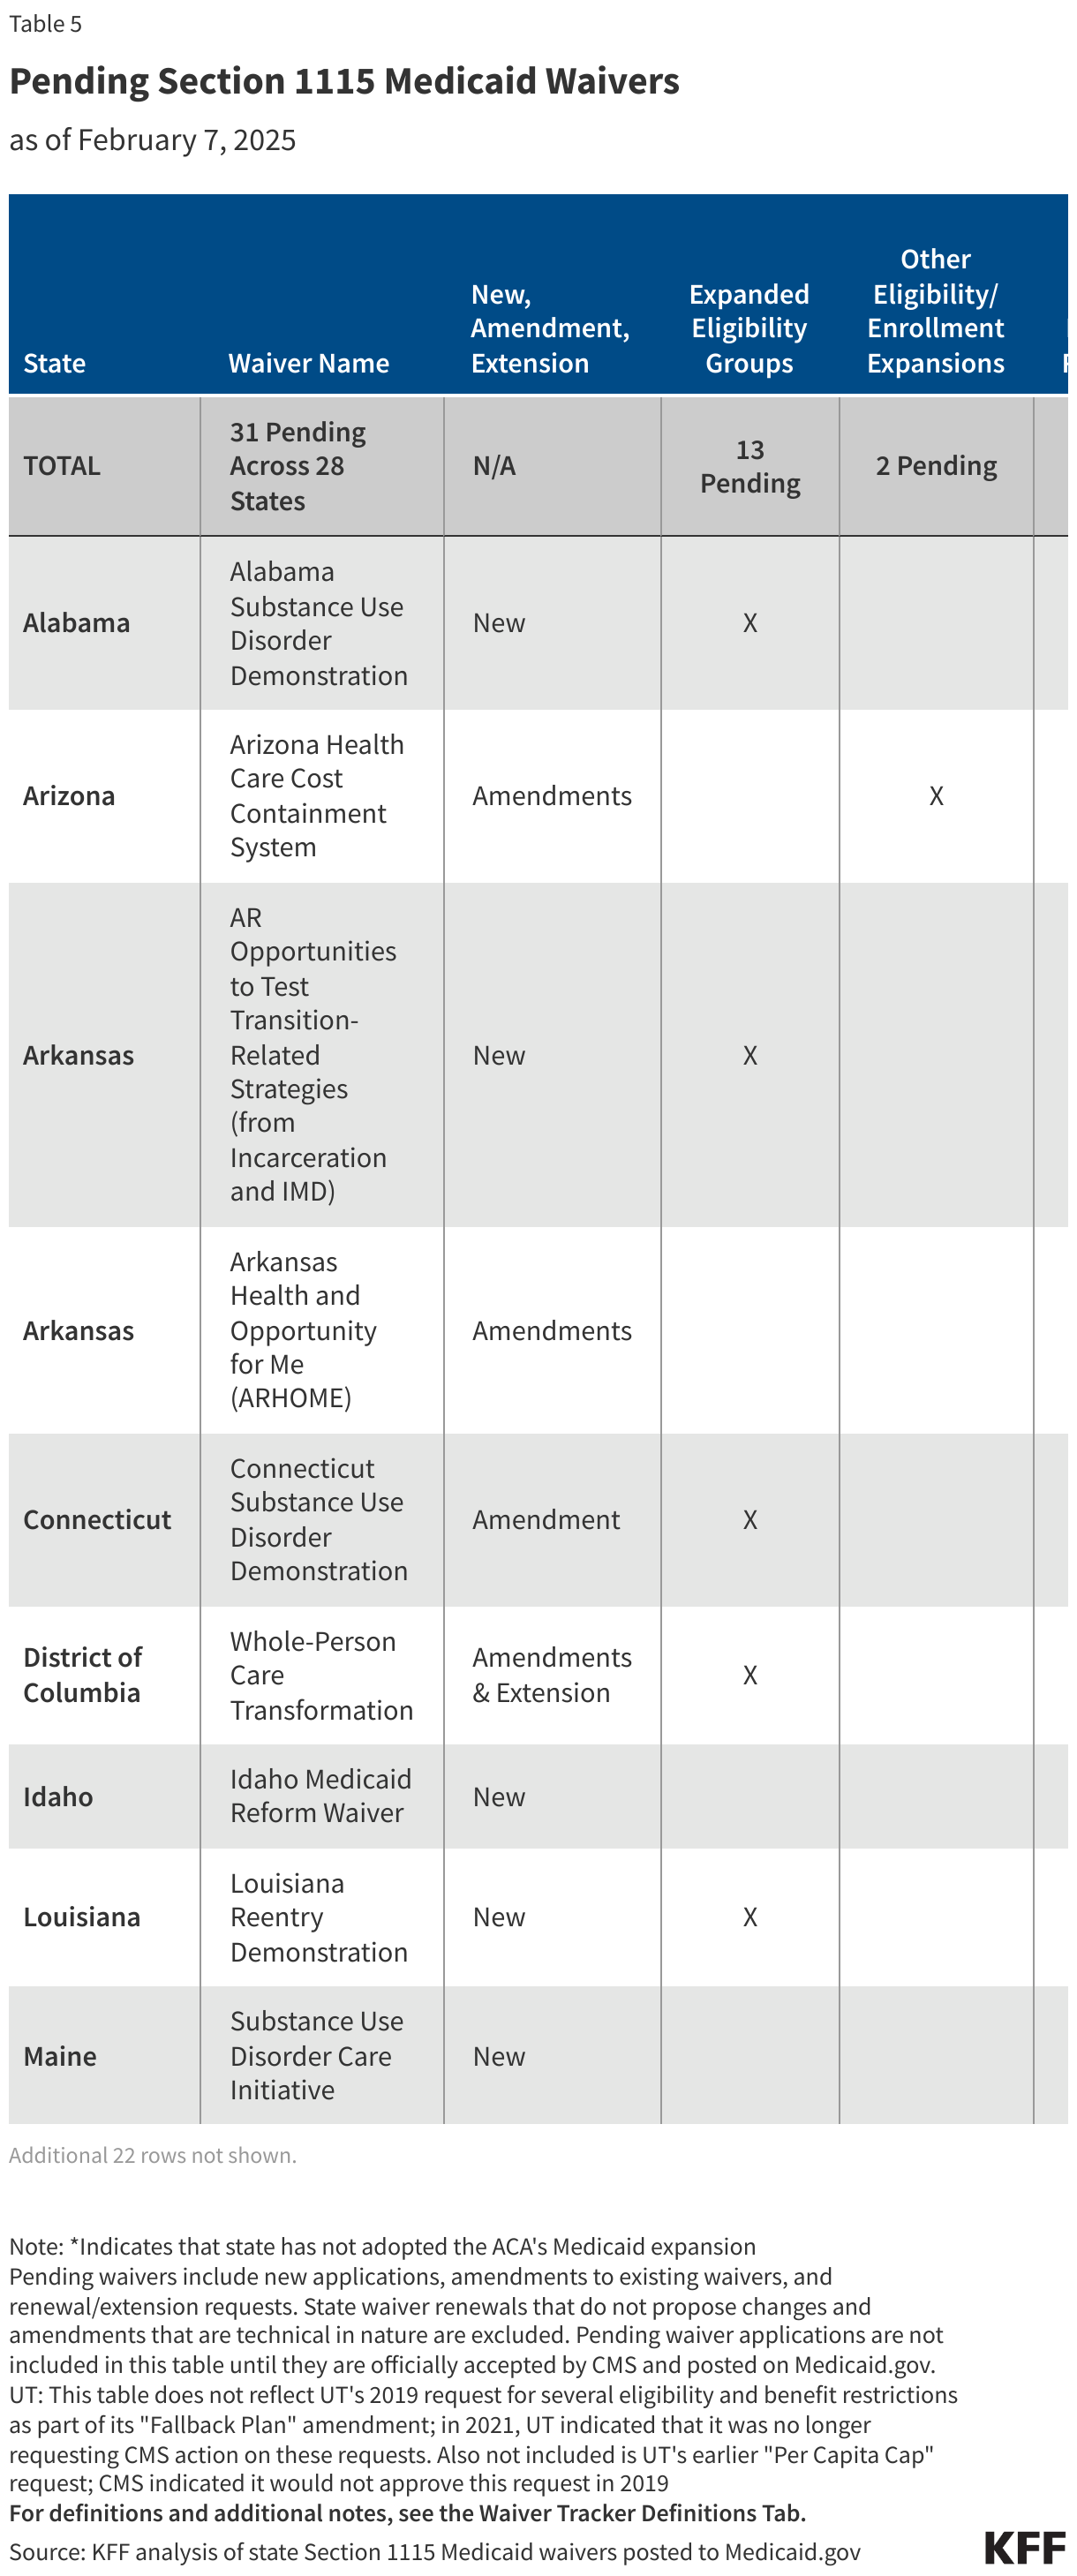
The decision to phase out continuous eligibility is perhaps the most direct threat to coverage stability. Research has consistently shown that "churn"—the phenomenon of beneficiaries losing and regaining coverage due to minor administrative glitches or income fluctuations—leads to gaps in care and increased long-term costs. By ending these waivers, the administration is effectively reversing years of effort aimed at maintaining a consistent "medical home" for the nation’s most vulnerable children.
Fiscal Pressures on States
The removal of DSHP funding and the potential for increased administrative burdens associated with tracking work requirements place states in a difficult fiscal position. Governors are now faced with a choice: absorb the costs of maintaining these programs with state-only dollars or scale back benefits to fit within the new, more restrictive federal framework.
The Role of the Judiciary
As seen in the case of Indiana’s "Healthy Indiana Plan 2.0," the courts remain a major player. When a federal district court vacated Indiana’s authority to charge premiums and waive retroactive eligibility, it demonstrated that even with administrative backing, state policies must still comport with the overarching spirit of the Social Security Act. Future litigation regarding work requirements and the rescission of HRSN guidance is highly probable.
Conclusion: A System at a Crossroads
The Section 1115 waiver program remains a vital, if volatile, instrument of American health policy. As of late 2026, the program is moving away from the "whole-person" approach favored in the early 2020s and toward a model that emphasizes traditional eligibility standards, strict compliance, and a narrower definition of medical necessity.
For states, the path forward requires a delicate balancing act. They must navigate the impending federal mandates for 2027 while managing the expiration of innovative programs that had, until recently, enjoyed broad federal support. For the millions of Americans enrolled in Medicaid, the shifting landscape means that the stability of their coverage may increasingly depend on which state they call home, as the federal government retreats from a unified vision of expanded access and toward a more decentralized, restrictive model of oversight.

As we look toward 2027 and 2028, the data tracked by KFF and other policy analysts will be essential in determining the real-world impact of these policies. The transition from the "waiver-heavy" era of the mid-2020s to the "enforcement-heavy" era of the late-2020s will likely define the health outcomes of a generation of Medicaid participants.
About the Author