Introduction: A Fundamental Shift in Federal Oversight
For decades, Section 1115 Medicaid demonstration waivers have served as the primary laboratory for state-led health policy innovation. By allowing states to bypass traditional federal statutory requirements, these waivers have enabled the testing of diverse initiatives—from expanding coverage for low-income adults to addressing social determinants of health and facilitating reentry services for the formerly incarcerated. However, as of January 1, 2027, the rules governing these experiments have undergone a tectonic shift.
Driven by the 2025 reconciliation law signed by President Trump, the federal government has moved to codify and tighten the long-standing, yet previously flexible, requirement of "budget neutrality." This transition marks the end of an era of broad administrative latitude, ushering in a period of rigorous actuarial scrutiny, restricted funding mechanisms, and heightened oversight from the Centers for Medicare and Medicaid Services (CMS).
Main Facts: Codifying Fiscal Discipline
At the heart of the current policy environment is the legislative mandate that Section 1115 waivers must be budget neutral to the federal government. Historically, "budget neutrality" meant that the total federal spending under a waiver could not exceed the projected spending that would have occurred without the waiver. While this concept was a cornerstone of past administrations, it was previously a policy guideline rather than a strict federal statute.
The 2025 reconciliation law fundamentally altered this landscape by:
- Codifying Budget Neutrality: For the first time, the requirement is enshrined in federal law.
- Mandatory Actuarial Certification: CMS Chief Actuaries are now required to formally certify that every waiver is budget neutral before it can be approved.
- Rigorous Analytic Requirements: States must now provide comprehensive, data-driven, and peer-comparable analyses of the projected financial impact of every individual demonstration activity.
- Administrative Tightening: CMS has signaled an intent to shift states away from 1115 authority toward existing "State Plan" or "1915 authority," effectively narrowing the scope of what is considered an appropriate use of a demonstration waiver.
Chronology of Policy Evolution
The path to the current regulatory environment has been marked by a series of significant administrative and legislative milestones:
- 2018–2020: The first Trump administration introduced changes to budget neutrality calculations, aiming to limit the federal spending ceiling for waiver-based programs.
- 2021–2024: The Biden administration pivoted toward broader flexibility, encouraging waivers that addressed health-related social needs (HRSN) and permitted states to use "hypothetical" expenditure models—waivers that did not require offsetting savings.
- July 4, 2025: President Trump signed the 2025 reconciliation law, establishing the statutory framework for the current budget neutrality requirements.
- 2025–2026: The Government Accountability Office (GAO) issued a series of reports questioning the transparency of "hypothetical" expenditures and calling for more stringent oversight of state spending baselines.
- June 2026: CMS released formal guidance outlining the new, restrictive approach to budget neutrality, set to take effect on January 1, 2027.
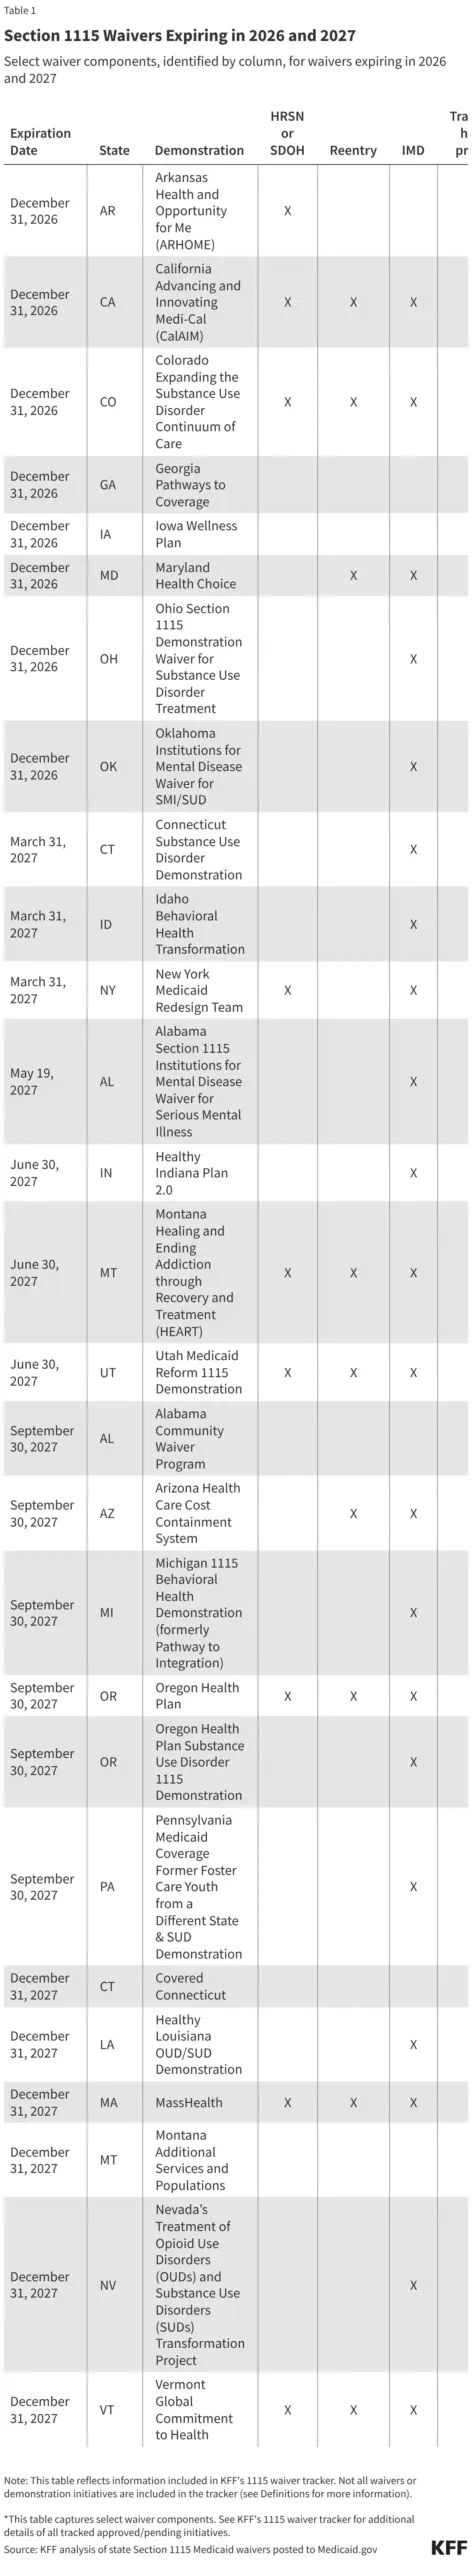
- August 2026: Arkansas became the first high-profile casualty of the new rules, with CMS announcing it would not renew the state’s "ARHOME" waiver, which funneled Medicaid expansion populations into ACA Marketplace plans.
- September 2026: Despite the tightening environment, CMS approved reentry waivers for D.C., Louisiana, Maine, Minnesota, and Nevada, signaling a selective approval process for specific populations.
Supporting Data: The Impact on State Innovation
The shift in policy is not merely academic; it has immediate, tangible consequences for state budgets. The primary mechanism of these waivers—the ability to generate "savings" and reinvest them into new initiatives—is under threat.
The "ARHOME" Precedent
Arkansas’s experience provides a sobering case study for other states. The ARHOME program allowed for the integration of Medicaid expansion with the private insurance market. Under the new 2027 guidelines, this model was deemed incompatible with the stricter neutrality requirements. Consequently, the state has been forced to seek a two-year extension to develop a new, compliant delivery system, creating significant uncertainty for thousands of enrollees.
The Reentry Landscape
While CMS has tightened the belt on general waivers, the late-2026 approvals for reentry services show that the federal government remains interested in specific, high-priority areas. However, these approvals come with a caveat: the infrastructure costs associated with these programs will no longer be treated as "hypothetical" expenditures. States will now have to navigate complex pathways for administrative claiming to fund the rollout of these services, a significant departure from the previous, more lenient fiscal environment.
Official Responses and Administrative Guidance
The CMS leadership has maintained that these changes are necessary to ensure the long-term fiscal sustainability of the Medicaid program. In its June 2026 guidance, the agency explicitly stated that the era of "automatic" approvals or "fast-track" renewals is over. The rescission of the 2015 fast-track guidance means that even minor, straightforward renewals will now be subject to the same level of scrutiny as entirely new, complex demonstrations.
Republican leadership in the House, particularly the Committee on Energy and Commerce, has lauded these changes, arguing that the previous approach allowed for "an expensive history of demonstration waivers" that lacked sufficient congressional oversight. For many lawmakers, the new rules are a necessary correction to prevent states from using the waiver process to bypass legislative intent regarding Medicaid funding.
Implications for the Future of Medicaid
The implications for state health departments are profound. The current environment creates a "high-barrier-to-entry" scenario for new innovations.
1. Reduced State Flexibility
States that rely on 1115 waivers to fund social services, traditional healing practices, or delivery system reforms may find that these programs no longer "pay for themselves" under the new calculus. When an activity is labeled as "1115-only," the state must now demonstrate net savings to offset the cost. If those savings cannot be found—and with CMS restricting the ability to roll over savings from previous years—many of these programs will effectively become unaffordable.
2. The End of "Hypothetical" Expenditures
The move away from allowing "hypothetical" expenditures (where states did not have to prove cost-neutrality because the program was viewed as a policy priority) will likely stifle experimentation. Initiatives like HRSN, which were championed by the previous administration, are now at risk of being categorized as non-essential expenditures that must be funded through internal state savings rather than federal "budget neutrality" buffers.
3. A Longer Approval Timeline
The National Association of Medicaid Directors (NAMD) has warned that the new requirements will significantly lengthen the already-lengthy approval process. Because states must now conduct rigorous, pre-approval actuarial analyses, the time from application to implementation will likely expand from the typical 1–2 years to even longer periods of negotiation. This creates a "policy gridlock" where states are hesitant to propose ambitious reforms, fearing the administrative burden and the high probability of rejection.
4. Uncertainty for Existing Waivers
Perhaps the most immediate concern is the status of existing waivers. As current 1115 demonstrations reach their expiration dates, states will be forced to renegotiate them under the 2027 guidelines. Programs that were considered "budget neutral" as recently as 2025 may be rejected or forced to undergo drastic downsizing to meet the new, more rigid standards.
Conclusion: The Path Ahead
The landscape for Medicaid innovation has been fundamentally altered. As states approach the 2027 threshold, they must prepare for a future defined by actuarial rigor and fiscal conservatism. While the door for innovation remains open, it is now guarded by strict, statutory requirements that prioritize federal cost containment above state-level flexibility.
The coming months, as CMS releases further rulemaking and clarifies the treatment of existing waivers, will be critical. States, advocates, and health policy experts will be watching closely to see if the new, more restrictive approach leads to a more stable Medicaid program, or if it inadvertently dismantles the creative, localized solutions that have defined American health policy for the last two decades. The "laboratories of democracy" are still open, but the price of entry has never been higher.
About the Author