For millions of Americans, the Medicaid and Children’s Health Insurance Program (CHIP) represent the critical bridge between financial insolvency and essential medical care. As a joint federal-state venture, these programs provide a foundation for healthcare and long-term support for low-income children, families, the elderly, and individuals with disabilities. However, as new data from 2024 and 2026 indicates, the "safety net" in the United States is far from uniform. Depending on one’s zip code, the breadth, eligibility, and accessibility of Medicaid coverage can shift dramatically, turning the American healthcare landscape into a complex patchwork of state-level policy decisions.
The Architecture of Inequality: Why Programs Vary
The fundamental structure of Medicaid is rooted in a federal-state partnership. While the federal government establishes broad guidelines and provides matching funding, states are granted significant autonomy in administering their specific programs. This administrative design was intended to allow for localized flexibility, but it has resulted in a fragmented system where the "same" program can look vastly different from state to state.
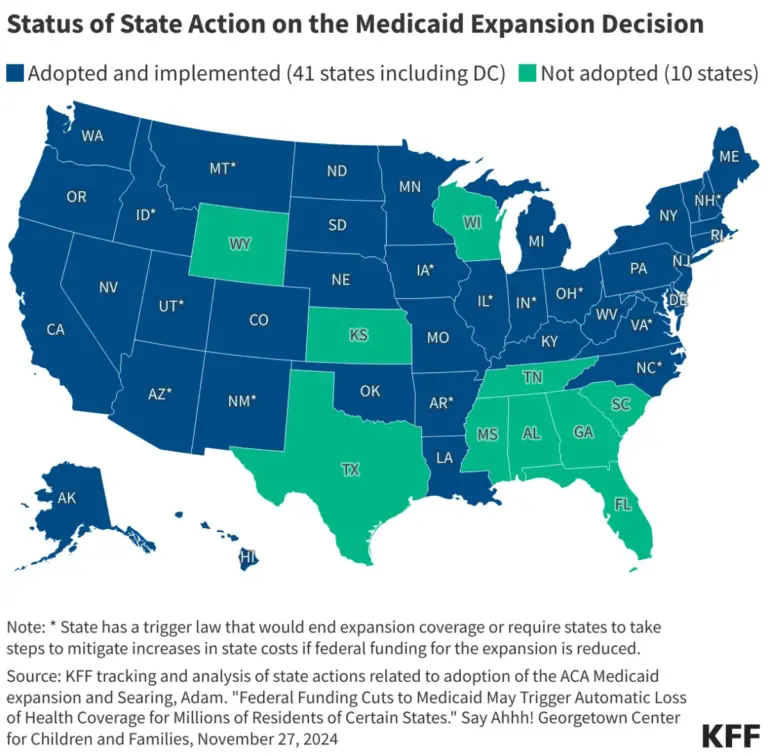
The variance is primarily driven by state-specific policy choices. The most significant of these remains the decision to adopt the Affordable Care Act (ACA) Medicaid expansion. States that have opted into the expansion have significantly broadened their eligibility criteria, allowing low-income adults without dependent children to qualify for coverage—a demographic that was historically excluded from the program. Conversely, states that have resisted expansion create a "coverage gap," where individuals earn too much to qualify for traditional Medicaid but too little to afford private insurance on the ACA marketplace.
Beyond expansion, states exercise discretion in setting income limits above federal minimums for specific groups, such as pregnant women, children, and the disabled. Furthermore, demographic factors—including the age distribution of a state’s population, the local cost of living, and the prevalence of specific health conditions—dictate the financial burden on state budgets, further influencing how robustly a state chooses to fund its program.
Chronology: A Decade of Transformation
To understand the current state of Medicaid, one must look at the evolution of the program over the last decade.
- 2014: The implementation of the ACA Medicaid expansion begins, marking the most significant shift in the program’s history. States begin to diverge as some embrace the federal funding to expand coverage while others opt out due to political and fiscal concerns.
- 2020-2023: The COVID-19 pandemic triggers the "Continuous Enrollment Provision." To ensure stability during the public health crisis, states were prohibited from disenrolling individuals from Medicaid in exchange for enhanced federal funding. This led to record-high enrollment numbers across all states.
- 2023-2024: The "unwinding" of the continuous enrollment provision begins. States initiate the massive administrative task of redetermining eligibility for millions of enrollees. This period highlights the vast differences in state administrative capacity, with some states managing the transition smoothly while others face significant backlogs and coverage losses.
- 2026: Current data highlights the stabilization of these programs. With the expansion status largely settled in most states, the focus shifts toward long-term sustainability, the integration of new health technologies, and addressing the remaining uninsured populations that fall through the cracks of state-level policy.
Supporting Data: Visualizing the Disparity
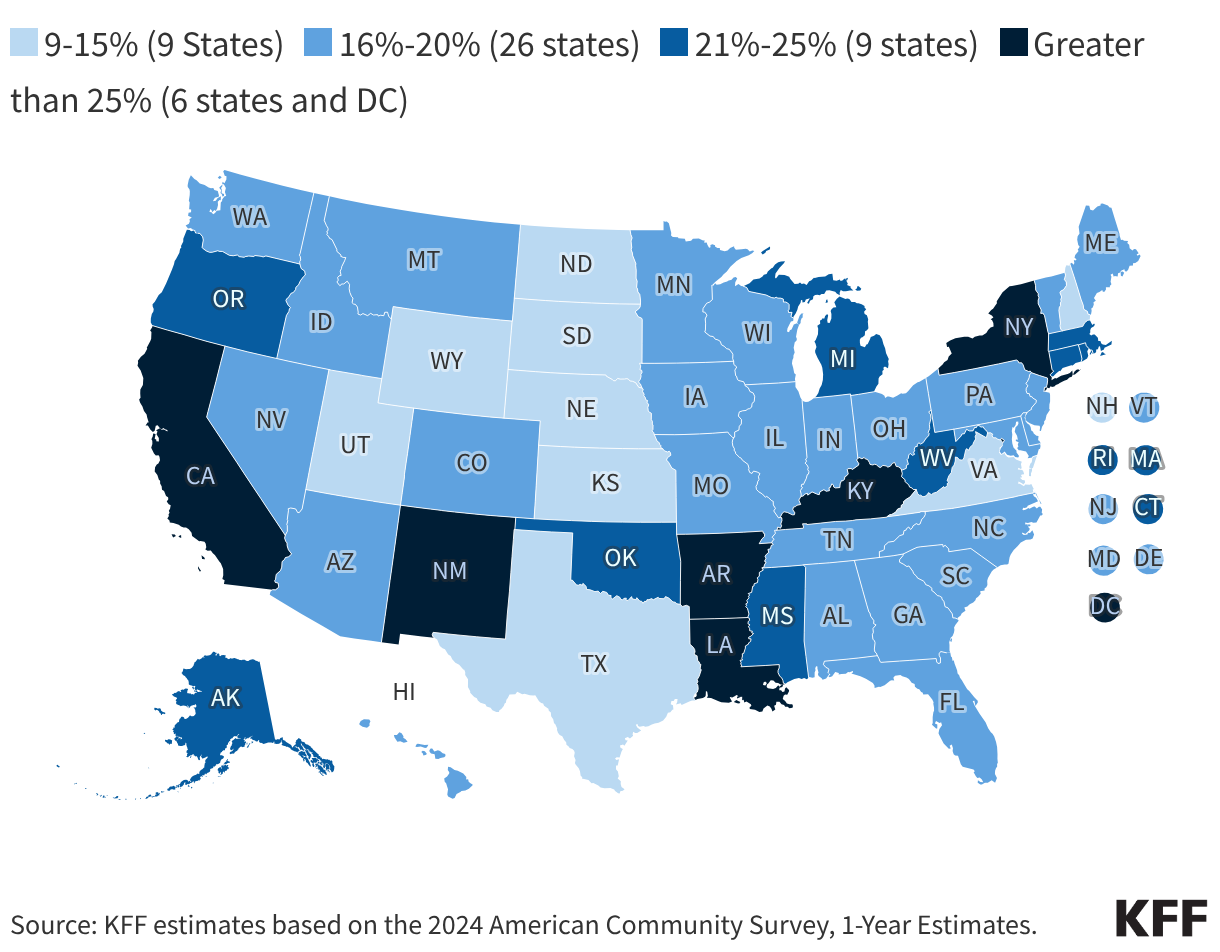
The 2024 data reveals a striking geographic divide in Medicaid penetration. When mapping the percentage of people covered by Medicaid, the correlation between state policy and coverage rates is undeniable.
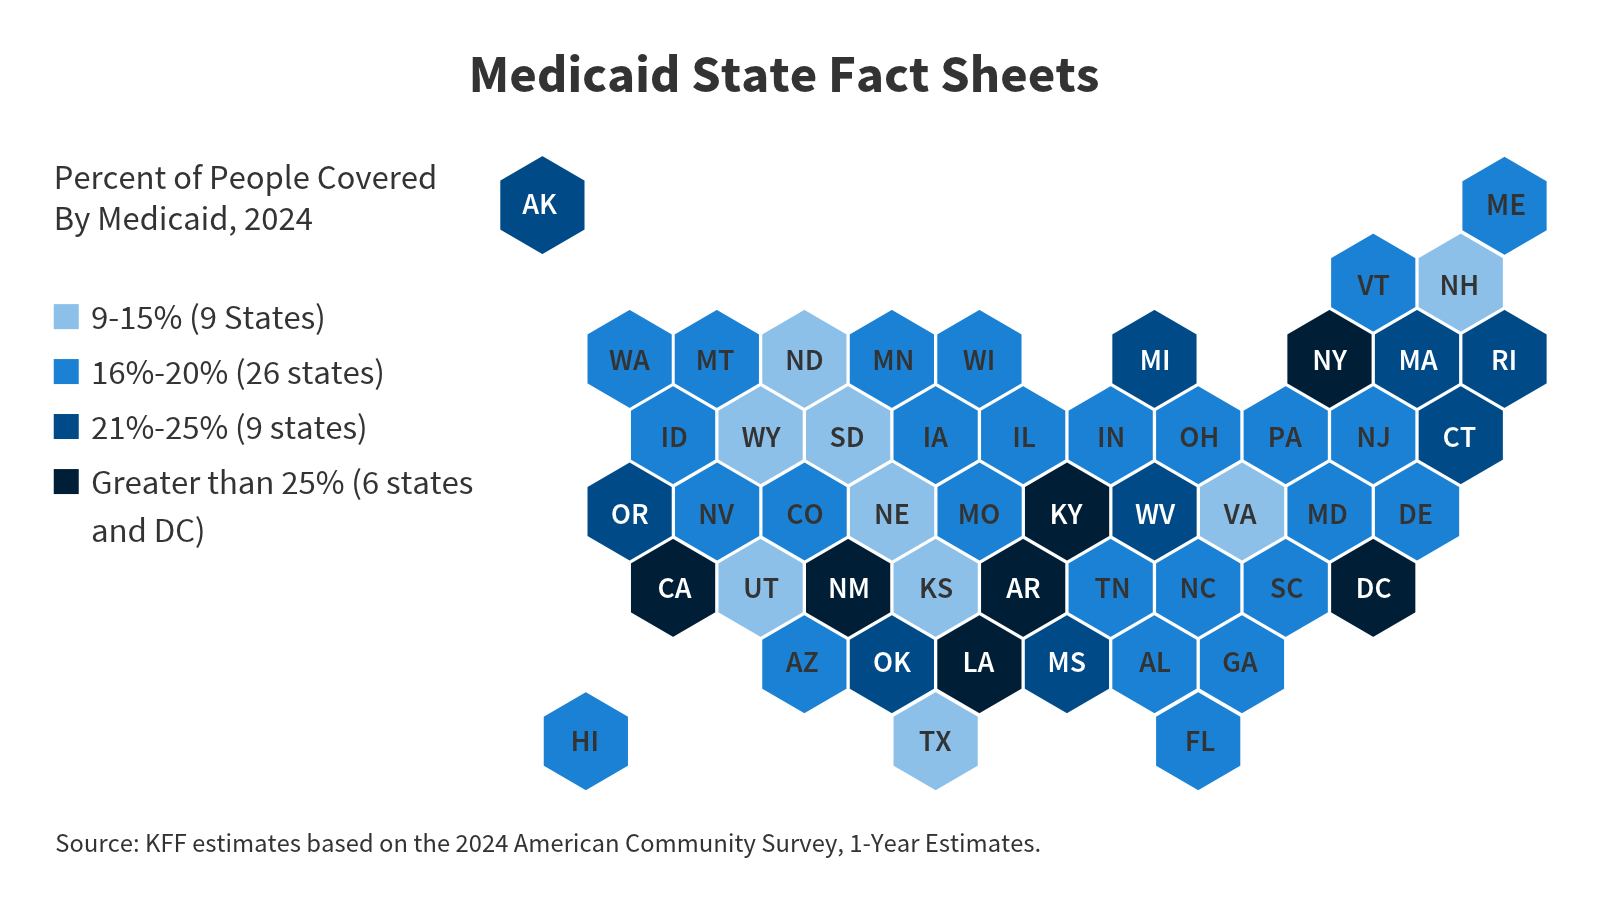
In states that aggressively pursued expansion and utilized higher income thresholds, Medicaid enrollment as a percentage of the population remains notably higher. These states often demonstrate a more robust commitment to public health infrastructure. In contrast, states that have maintained restrictive eligibility requirements show lower enrollment, which often mirrors higher uninsured rates among non-elderly adults.
The 2026 enrollment metrics, analyzed alongside Congressional District maps, demonstrate that Medicaid is not just an urban or rural issue; it is a pervasive economic reality. In districts with high poverty rates, Medicaid serves as the primary insurer, often covering more than 40% of the population. The fiscal impact of this coverage is significant, as federal dollars flow into these regions, supporting not just the health of the populace but the economic viability of local hospitals and healthcare providers.
The Cost of Coverage: Spending and Allocation
The distribution of Medicaid spending is a point of constant contention in state legislatures. While children and families represent the bulk of the enrollment numbers, the majority of Medicaid spending is directed toward the elderly and individuals with disabilities, primarily for long-term care services.
As states navigate their 2026 budgets, the tension between these two groups is palpable. Policymakers are under pressure to manage rising costs associated with an aging population while simultaneously trying to maintain access for children. The data indicates that states with higher per-capita spending often provide more comprehensive waiver programs, allowing for home-based care rather than institutionalized nursing home stays. This is widely regarded as both a more humane and a more cost-effective approach, yet the administrative complexity prevents all states from adopting it at scale.
Official Responses and Political Implications
The variation in Medicaid policy is rarely accidental; it is the product of intense political deliberation.
Supporters of state-level flexibility argue that states are better positioned to know the needs of their specific residents. "One size does not fit all," argue state-level officials in more restrictive states, citing concerns over budget volatility and the potential for over-reliance on federal funding. They advocate for work requirements and other eligibility restrictions as a means to encourage workforce participation and ensure that the program remains targeted at those most in need.
Conversely, public health advocates and federal policymakers point to the clear correlation between expansion and better health outcomes. "Health is a fundamental prerequisite for economic participation," argues a spokesperson for a leading health policy institute. "By denying coverage to low-income workers, states are essentially creating a drag on their own economies and increasing the long-term burden on emergency departments, which are forced to provide uncompensated care."
The debate has moved into the courts and the halls of Congress, with ongoing discussions about whether to implement a federal floor for eligibility that would override state-level restrictions. However, given the current political climate, such a mandate faces significant opposition from proponents of "states’ rights."
Implications for the Future
The state of Medicaid in 2026 serves as a mirror to the broader American social contract. The data shows that while the program is highly effective at its core mission—reducing the number of uninsured and providing essential services—it is simultaneously hindered by the structural inequities inherent in a fragmented system.
For the individual, this means that the quality of one’s healthcare is often determined by the political leanings of their state capital. An individual with a chronic illness might receive comprehensive support and home-based care in one state, while an individual with the exact same condition in a neighboring state might find themselves navigating a restrictive, underfunded system that offers little more than emergency room access.
Looking ahead, the focus for researchers and policymakers must be on:
- Administrative Modernization: Reducing the "red tape" that leads to the churn of eligible enrollees losing coverage during the renewal process.
- Addressing the Coverage Gap: Seeking legislative pathways to ensure that those who fall into the gap in non-expansion states are provided with a bridge to coverage.
- Long-Term Care Sustainability: Preparing for the "silver tsunami" of an aging population that will require Medicaid-funded long-term care, which will place unprecedented strain on state budgets.
In conclusion, while Medicaid continues to be a vital lifeline for millions, the disparities exposed by the latest data indicate that the system is in need of a renewed national conversation. If the goal of the program is to ensure equitable access to health, the current structure of state-by-state variance must be reconciled with the need for a consistent, baseline standard of care that applies to every American, regardless of where they live. Until that bridge is built, the American safety net will continue to operate as a series of disconnected, albeit essential, fragments.
About the Author