Since the enactment of the Affordable Care Act (ACA) in 2010, the American healthcare landscape has been fundamentally reshaped by the federal government’s attempt to close the "coverage gap." At the heart of this transformation is the Medicaid expansion, a policy mechanism designed to extend health insurance to nearly all adults with incomes up to 138% of the Federal Poverty Level (FPL)—equating to an annual income of $21,597 for an individual as of 2025.
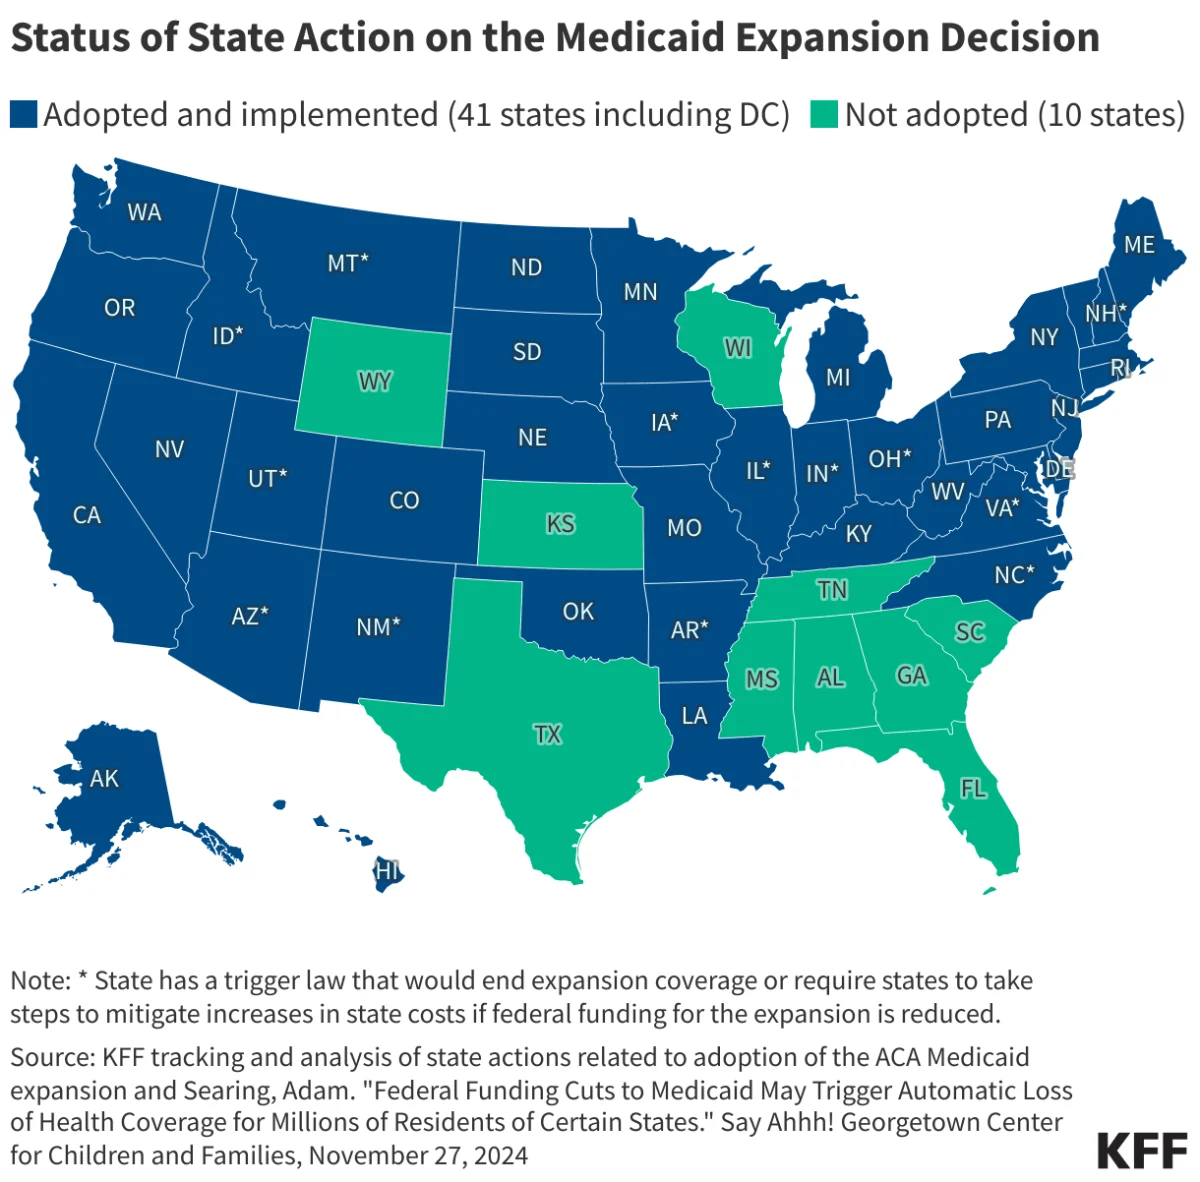
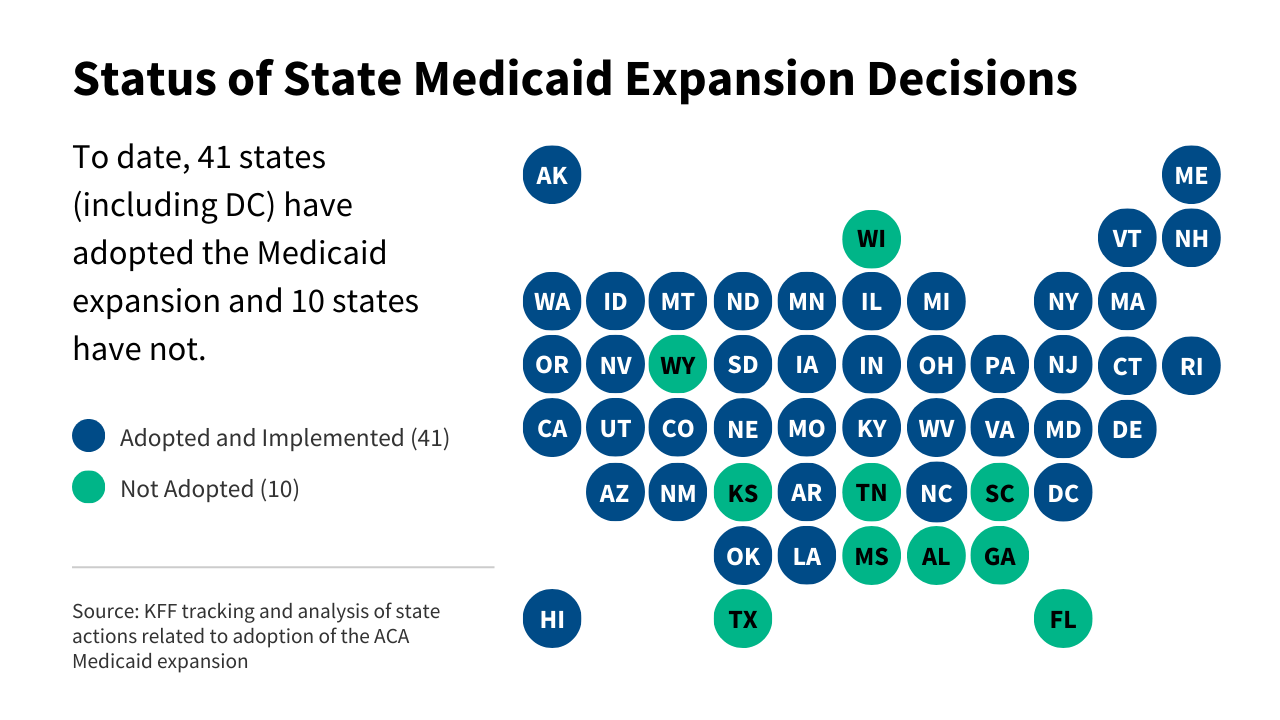
While the policy was envisioned as a national standard, its implementation has become one of the most significant points of political and administrative friction in modern American history. Today, the United States remains divided, with 41 jurisdictions (including the District of Columbia) embracing the expansion and 10 states holding firm in their refusal to adopt it.
The Core Mechanics of Medicaid Expansion
The Medicaid expansion was designed to provide a financial incentive for states to cover low-income populations that were previously ineligible for the program. Under the ACA, the federal government covers a significant portion of the costs for the expansion population through an enhanced Federal Medical Assistance Percentage (FMAP). This federal support is intended to ease the fiscal burden on state budgets, allowing states to provide robust coverage for millions of working-class citizens who fall into the "coverage gap"—earning too much to qualify for traditional Medicaid but too little to afford private insurance premiums.
However, the path to expansion has been anything but uniform. The Supreme Court’s 2012 ruling in NFIB v. Sebelius effectively made the expansion optional for states, transforming what was intended to be a national mandate into a state-by-state political negotiation.
A Chronology of Policy Evolution
The trajectory of the Medicaid expansion can be segmented into several distinct phases, each defined by evolving political climates and shifting economic priorities.
2010–2013: The Foundation and the Court
Following the signing of the ACA, the federal government anticipated universal adoption. The promise of enhanced federal funding was the primary carrot, while the stick was the threat of losing federal funding for the entire Medicaid program. The 2012 Supreme Court ruling nullified that threat, creating the current, fractured map.
2014–2018: The Early Adopters and the Resistance
States with Democratic-led legislatures or governors were the first to move, quickly integrating the expansion into their social safety nets. Conversely, many Republican-led states resisted, citing concerns over long-term fiscal sustainability and ideological opposition to federal intervention in state affairs. During this period, the "coverage gap" emerged in states like Texas, Florida, and Georgia, leaving millions in limbo.
2019–2024: The Era of Ballot Initiatives and Waiver Debates
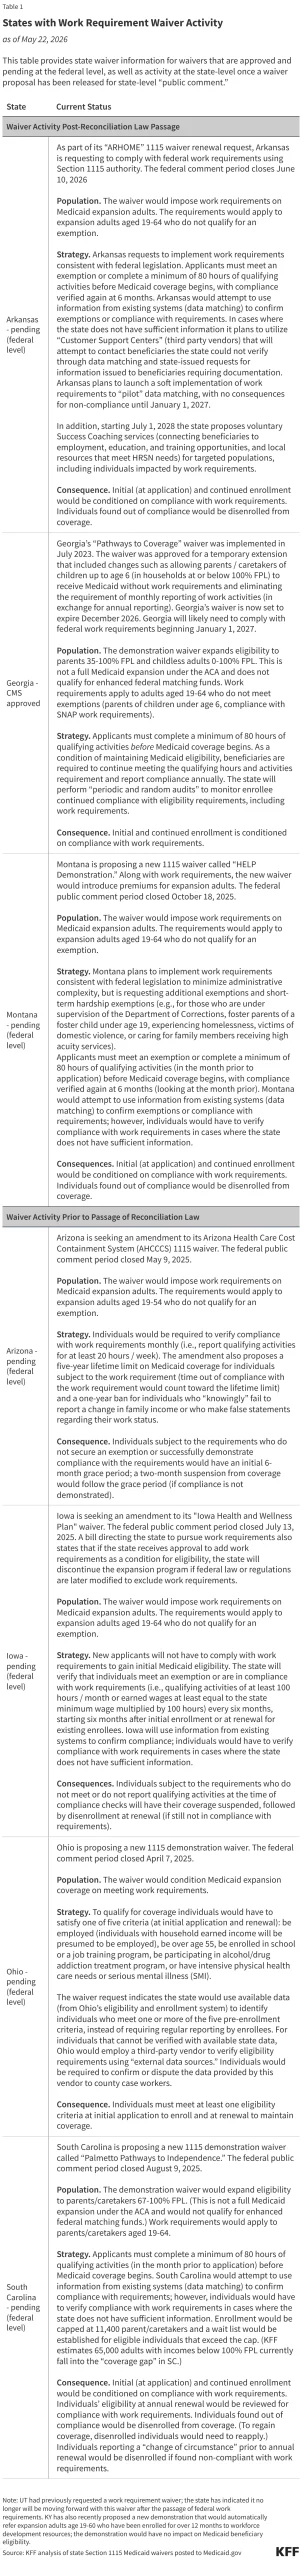
Recognizing that legislative pathways were often blocked by political gridlock, proponents began leveraging voter-led ballot initiatives. States such as Idaho, Nebraska, and Utah saw citizens bypass their legislatures to force expansion through the ballot box. Simultaneously, the conversation shifted toward "Section 1115 waivers," where states attempted to add work requirements or other restrictions to their expansion programs. While many of these were challenged in court, they signaled a new phase of "conditional" expansionism.
Supporting Data: The Current State of Play
As of early 2025, the map of American health policy remains starkly divided. KFF tracking indicates that 41 states have implemented the expansion, leaving 10 holdouts.
The Financial Incentive
The enhanced FMAP remains the primary driver of economic analysis for state legislatures. In states that have adopted the expansion, the influx of federal dollars has not only reduced the burden of uncompensated care on hospitals but has also acted as an economic stimulus in rural communities. Conversely, in the 10 non-expansion states, the lack of federal funding continues to place a heavy burden on state-funded safety nets and local medical facilities.
The "Trigger" Law Complication
A critical, often overlooked aspect of the current debate is the existence of "trigger laws." Some states have enacted legislation that makes their continued participation in the Medicaid expansion contingent upon the federal government maintaining its current level of funding. If federal support were to drop, these laws would automatically terminate the state’s expansion program.
Recent legislative activity in states like South Dakota, West Virginia, and Virginia highlights the volatility of this environment. While some legislatures have sought to harden these triggers to protect state budgets, others have debated removing them to provide more stability for the millions of residents currently relying on that coverage.
Official Responses and Political Maneuvering
The political response to the expansion is rarely monolithic. It involves a complex interplay between executive branch priorities and legislative oversight.
The Executive Perspective
In non-expansion states, Governors often play a dual role. Some have utilized the executive budget process to introduce expansion proposals, attempting to frame the move as a fiscally responsible way to bring federal tax dollars back to the state. Others have remained staunchly opposed, arguing that the expansion creates a permanent dependency on federal funding that could be withdrawn at any time.
The Legislative Perspective
Legislative chambers remain the primary battleground. In states where expansion has stalled, opponents frequently cite concerns over "crowd-out"—the fear that individuals will leave private insurance for public coverage—and the potential for future tax increases. Proponents, meanwhile, emphasize the health outcomes: lower maternal mortality rates, improved management of chronic diseases, and increased access to behavioral health services.
Implications for the Future of American Healthcare
The implications of the current "status quo" are profound and far-reaching.
Impact on Health Equity
The geographic disparity in health coverage has led to significant inequities. A citizen’s ability to access preventative care, cancer screenings, or mental health support is often determined by their zip code. The "coverage gap" has created a two-tiered system of healthcare in the United States, where access is not treated as a universal right, but as a byproduct of state-level policy decisions.
Fiscal Sustainability and Federal Reliance
The reliance on federal matching funds creates a unique set of risks. If the federal government ever moves to consolidate Medicaid funding—perhaps through block grants—states that have expanded their programs under the current FMAP structure could face massive budget shortfalls. This is why the debate over "trigger laws" is so consequential; it represents a hedging of bets against an uncertain federal fiscal future.
The Shift Toward Managed Care and Waivers
We are seeing a shift in how expansion is administered. States are increasingly looking to managed care organizations to handle the expansion population, often layering on complex eligibility requirements. This administrative complexity can lead to "churn"—where individuals gain and lose coverage due to minor fluctuations in income or clerical errors. Ensuring continuity of care remains the biggest operational challenge for states that have adopted the expansion.
Conclusion
The Affordable Care Act’s Medicaid expansion has undeniably succeeded in its primary goal of reducing the number of uninsured Americans. However, its incomplete adoption across the country leaves the American safety net frayed and inconsistent.
As we look toward the remainder of the decade, the focus is likely to shift from initial adoption to long-term maintenance. The 10 remaining states will continue to face pressure from healthcare providers and patient advocacy groups to expand, while the 41 participating states will be forced to grapple with the realities of managing these programs amidst potential federal budget adjustments.
The Medicaid expansion is no longer just a policy debate; it is a permanent fixture of the American socio-political landscape. Whether the map eventually turns completely blue or remains a checkerboard of political identity will depend on the continued ability of policymakers to balance fiscal conservatism with the undeniable public health benefits of universal access. The data is clear: where the expansion has been implemented, lives are being saved, and financial strain on individuals is being mitigated. Yet, until the coverage gap is fully bridged, the promise of the ACA remains unfulfilled for millions of Americans.
About the Author