Executive Summary: The Evolving Landscape of Medicaid Flexibility
Section 1115 of the Social Security Act grants the Secretary of Health and Human Services (HHS) the authority to approve "demonstration projects" that allow states to test innovative approaches to the Medicaid program. These waivers permit states to deviate from federal statutory requirements, provided the Secretary determines the proposal is likely to "promote the objectives" of Medicaid.
As of late 2026, the landscape of these waivers is undergoing a significant transformation. The transition from the Biden-Harris administration to the second Trump administration has marked a pivot point in federal priorities. While the previous administration utilized 1115 authority to emphasize social determinants of health (SDOH), justice-involved reentry, and extended continuous eligibility for children, the current administration has moved to rescind key guidance, tighten oversight, and prioritize traditional program structures, including mandatory work requirements.
The Mechanics of Flexibility
At its core, a Section 1115 waiver is a tool for state-level policy experimentation. States use this authority to modify eligibility, expand benefits, or restructure service delivery systems. Because Medicaid is a joint federal-state program, these waivers function as a negotiation between state houses and the federal government.
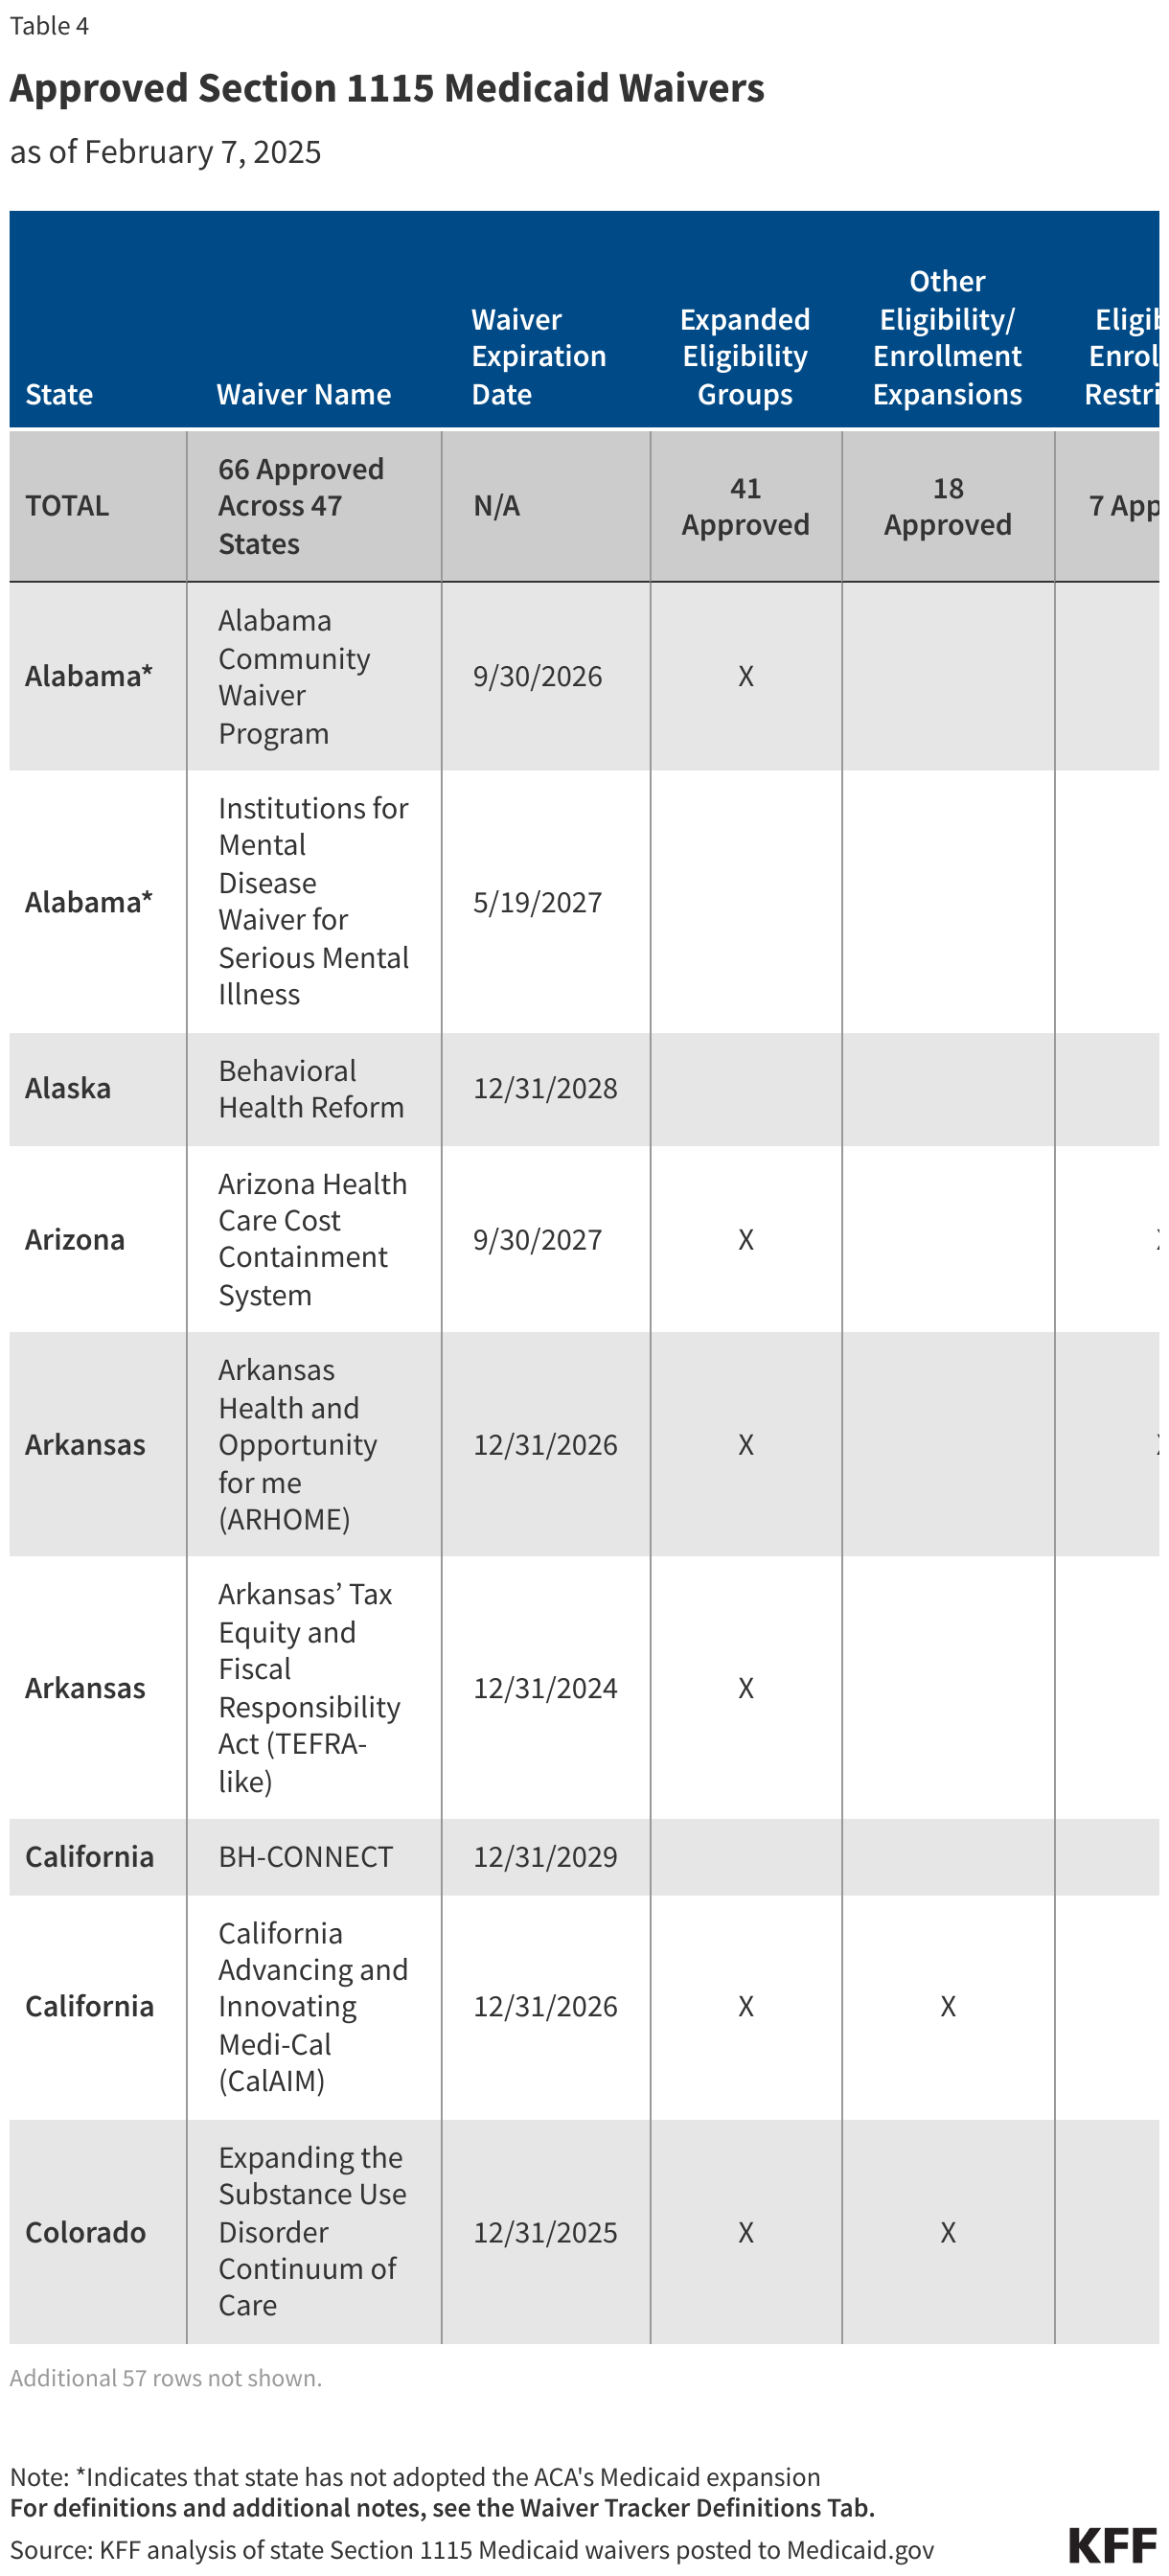
Nearly every state in the union currently operates at least one active Section 1115 waiver, illustrating the program’s reliance on state-specific tailoring. However, the "objectives" of these waivers—whether they prioritize broad access to care or fiscal austerity and administrative efficiency—often reflect the prevailing political ideology of the White House.
Chronology of Regulatory Shifts (2023–2026)
The trajectory of 1115 policy over the past three years highlights a rapid cycle of administrative rulemaking and subsequent reversal:
- 2023: The Biden administration issues a comprehensive framework for Health-Related Social Needs (HRSN), allowing states to use federal Medicaid funds for services like nutrition support and housing assistance. Simultaneously, new guidance encourages states to adopt "pre-release" coverage for incarcerated individuals to facilitate smoother transitions to community-based care.
- January 2024: Mandatory 12-month continuous eligibility for children takes effect nationwide via the Consolidated Appropriations Act, building on existing waiver momentum.
- March 2025: The Trump administration formally rescinds the HRSN guidance. While existing waivers remain intact, the federal government pivots to a "case-by-case" review process, signaling a more restrictive approval environment.
- April 2025: The administration moves to phase out "Designated State Health Programs" (DSHP) funding, a common tool states used to finance waiver-related infrastructure.
- July 2025: A critical inflection point occurs when the administration releases guidance confirming it will no longer approve or extend multi-year continuous eligibility for children or adults. Additionally, initiatives aimed at bolstering the Medicaid workforce for primary care and behavioral health are slated for sunsetting.
- January 2027: The effective date for the federal mandate requiring states to implement work requirements for ACA expansion adults.
Key Policy Themes: From Expansion to Restriction
1. Work Requirements: The Return of a Central Pillar
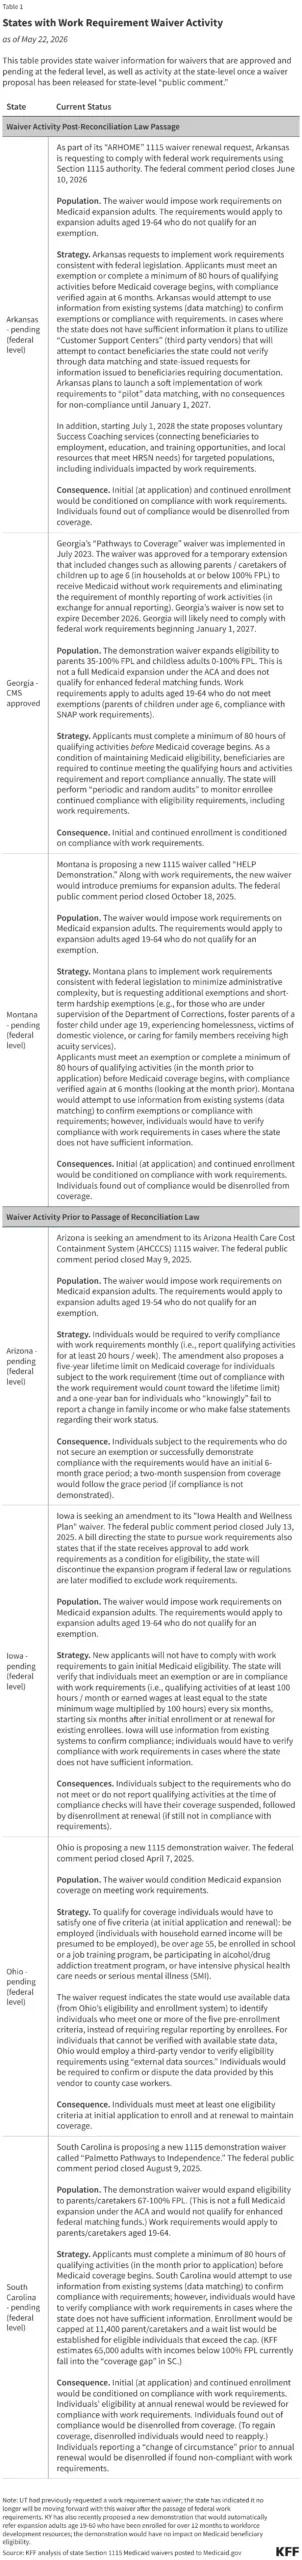
The implementation of work requirements represents one of the most contentious areas of Medicaid policy. Following the 2025 federal budget law, states are now required to condition eligibility on work status. While some states are opting to implement these via State Plan Amendments (SPAs) to beat the January 2027 deadline, others are navigating the waning utility of 1115 waivers for this purpose.
Georgia remains a notable outlier as the only state with an active work requirement waiver that survived extensive litigation. However, even Georgia must pivot to align with the new federal standard by the start of 2027. Nebraska, Montana, and Iowa are among the states preparing for early enforcement through SPAs, setting the stage for a national shift in how Medicaid enrollment is maintained.
2. Social Determinants of Health (SDOH)
Under the previous administration, the HRSN framework was a cornerstone of federal policy. By addressing housing and nutrition as "health-related," the program sought to reduce long-term medical costs. Today, while current approvals stand, the policy environment is significantly cooler. The shift to a "case-by-case" review suggests that new, expansive SDOH waivers face an uphill battle for federal approval. States must now demonstrate that such investments yield immediate, measurable clinical outcomes rather than broader systemic benefits.
3. Justice-Involved Reentry
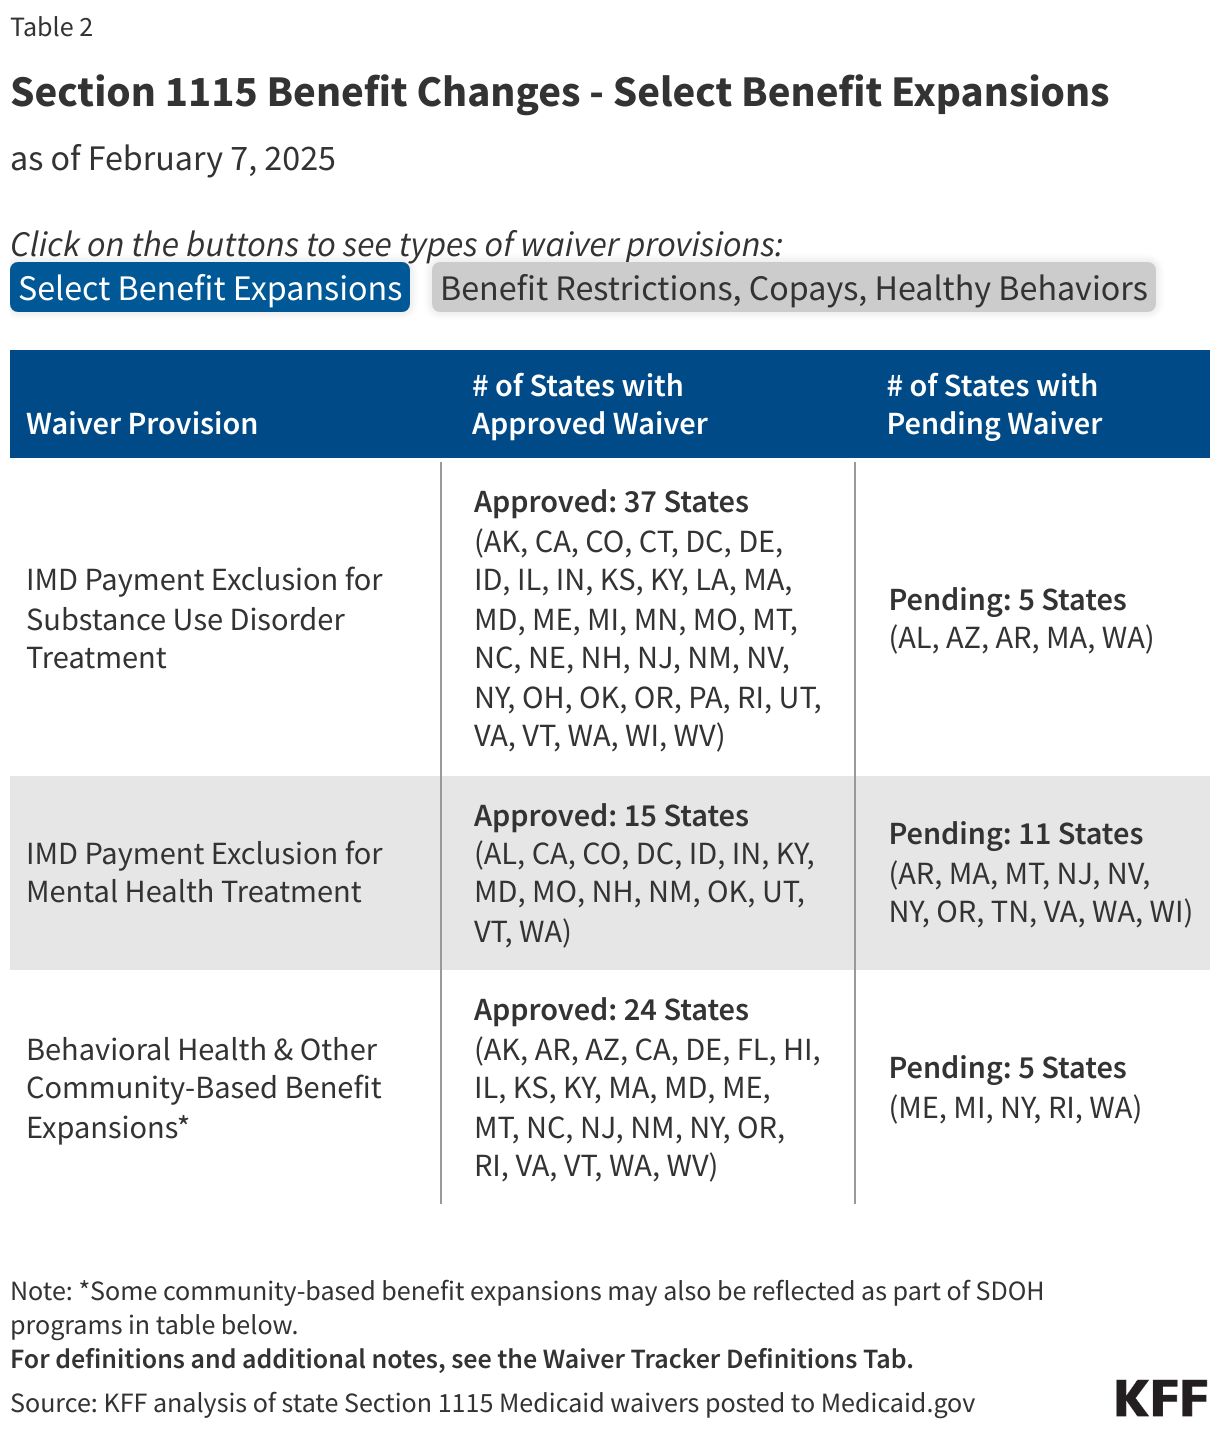
The "pre-release" coverage model is one of the few areas of bipartisan agreement. Both Democratic and Republican governors have pursued these waivers to ensure that individuals leaving incarceration have immediate access to health coverage, which is statistically linked to lower recidivism and better health outcomes. Despite the change in administration, the Trump team approved five additional reentry waivers in late 2026, suggesting that this specific type of demonstration may continue to find favor even as other expansionary policies are curtailed.
Supporting Data: The Current State of Play
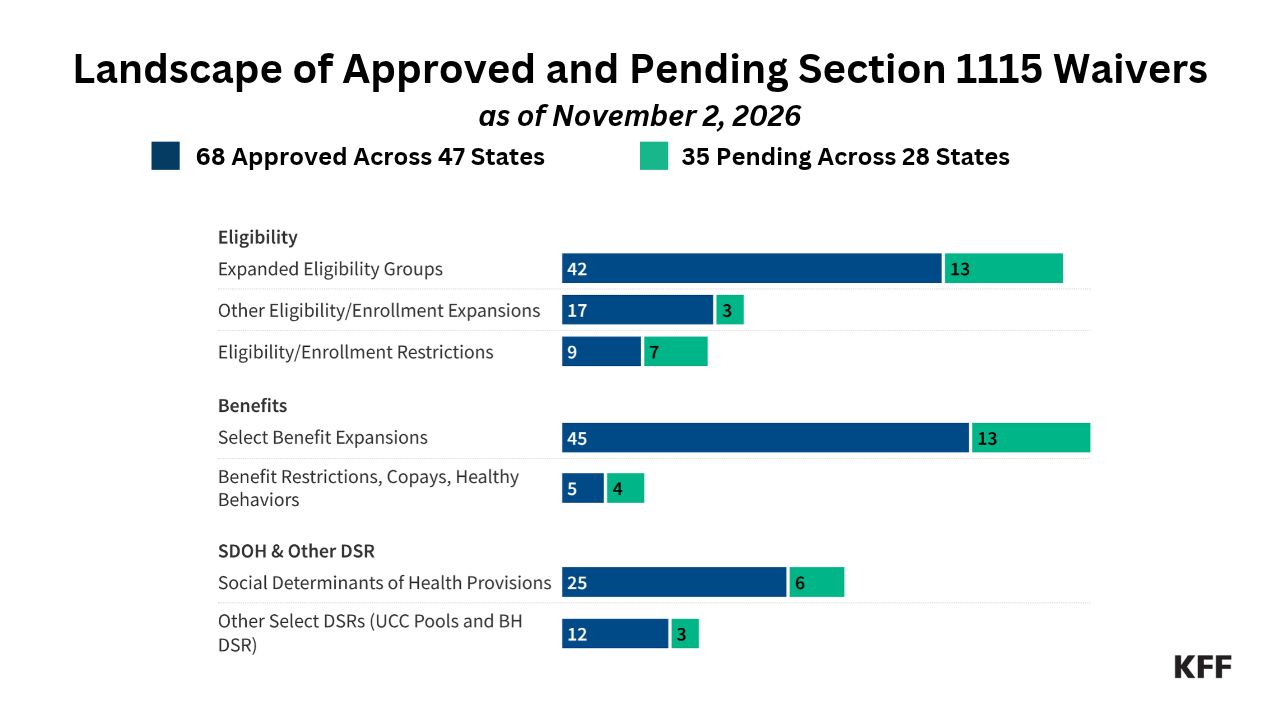
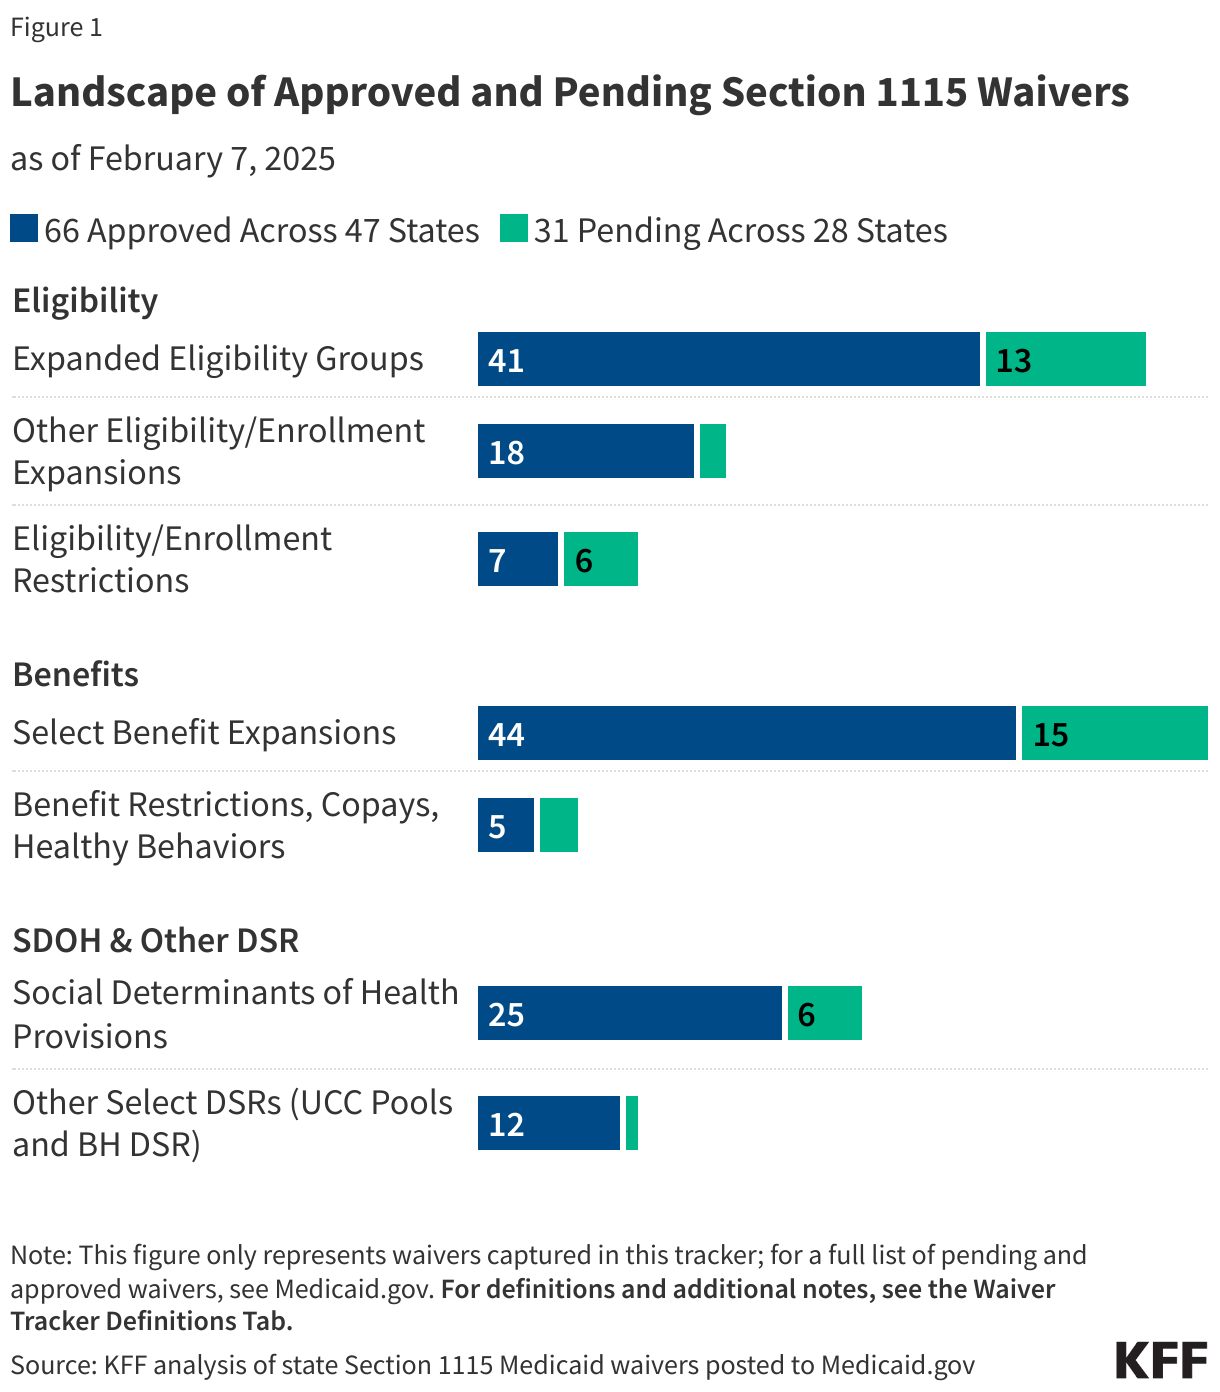
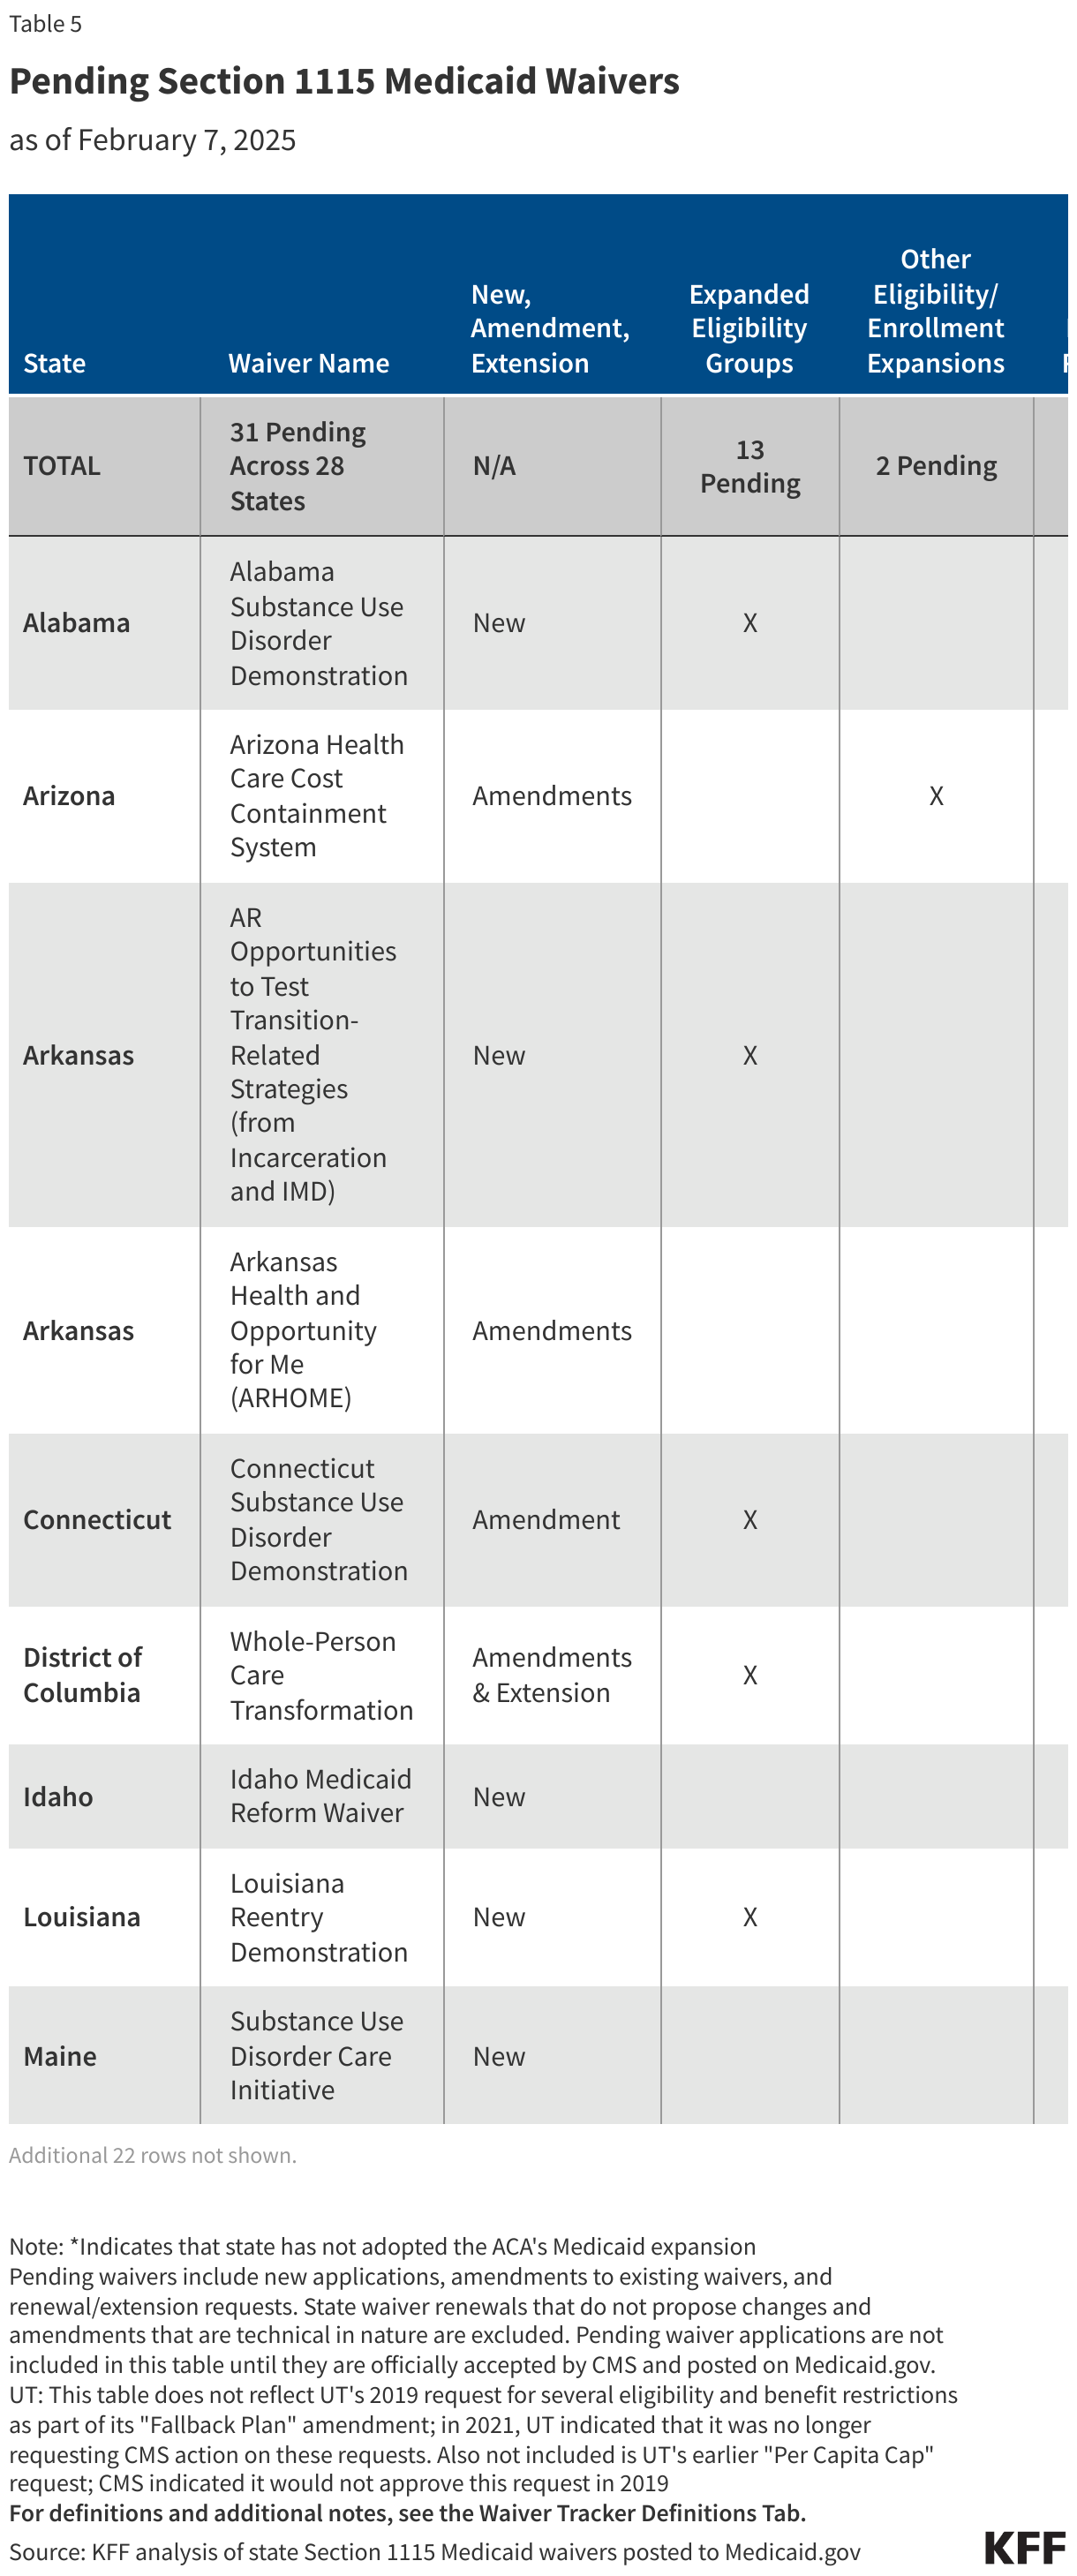
Analysis of current Medicaid.gov filings indicates a stark contrast between the breadth of active waivers and the narrowing scope of pending applications.

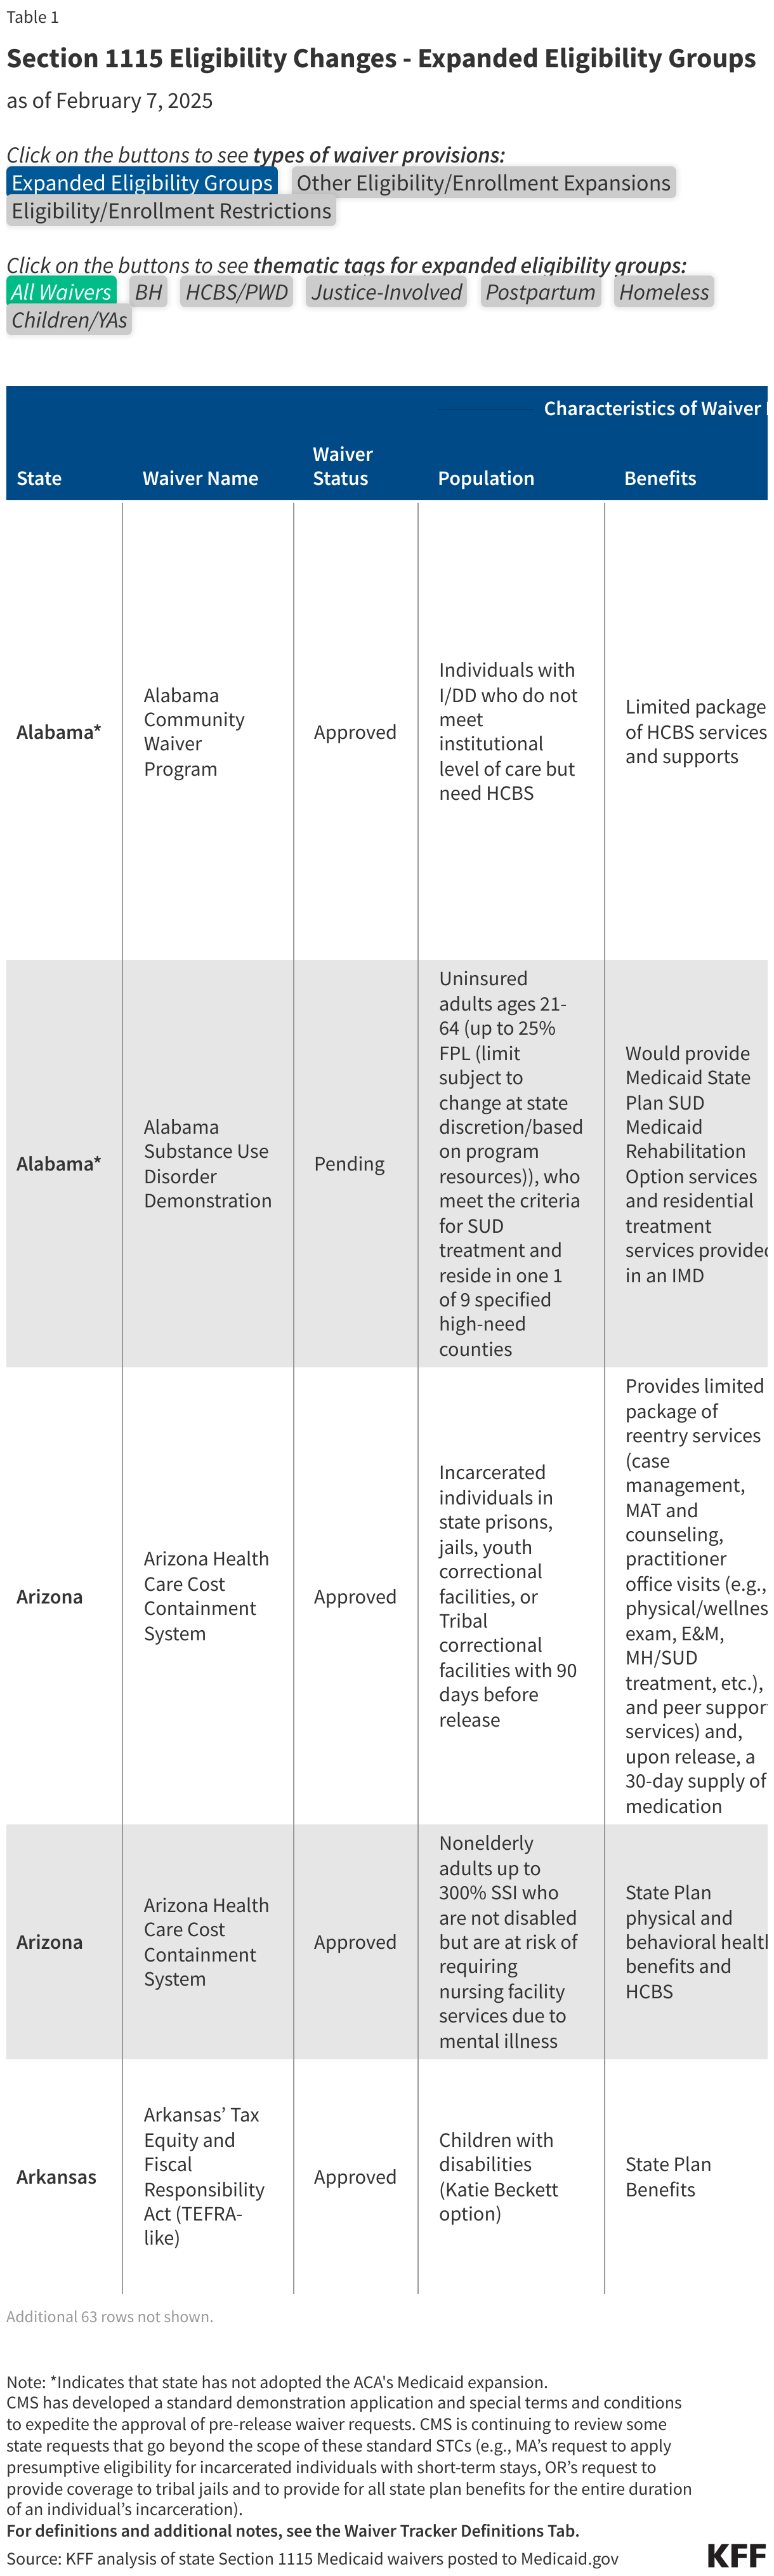
- Eligibility Expansions: Historically, waivers were used to expand coverage to specific vulnerable populations, such as those with behavioral health needs or children with complex disabilities. The current pipeline of pending waivers is significantly thinner in these areas compared to 2024, as states wait to see how the administration’s new, more restrictive criteria will be applied to future applications.
- Benefit Restrictions: There is a growing trend toward "healthy behavior" incentives and stricter copayment structures. Several states are actively proposing to remove previously approved incentives, signaling a move toward more traditional, fee-for-service-oriented benefit structures.
Official Responses and Administrative Stance
The federal government’s posture is characterized by a "return to basics." The administration’s official guidance emphasizes that Medicaid is a safety-net program intended for low-income individuals who meet strict eligibility criteria, and that the "waiver" process should not be used as a backdoor for permanent, large-scale expansions of the program.
State Medicaid directors find themselves in a precarious position. Those who invested heavily in infrastructure for HRSN or multi-year continuous eligibility now face the reality that these programs may not be renewed. The transition period between 2026 and 2028—when premium prohibitions for ACA expansion adults also kick in—is creating a complex regulatory environment where states must balance new federal mandates with the sunsetting of their own, previously approved innovations.
Implications for the Future of Medicaid
The "Churn" Factor
The move to end multi-year continuous eligibility and strictly enforce work requirements is expected to increase "churn"—the phenomenon where beneficiaries cycle on and off the program due to administrative requirements. Public health advocates warn that this will lead to fragmented care and, ultimately, higher costs for emergency departments as preventative care is disrupted.
Legal and Fiscal Uncertainty
The legal landscape remains volatile. As seen in the case of the "Healthy Indiana Plan 2.0," federal courts are increasingly willing to vacate waivers that they believe exceed the Secretary’s authority or conflict with the underlying intent of the Medicaid statute. The appeal by Indiana regarding premiums and non-emergency medical transportation (NEMT) suggests that litigation will remain a primary tool for both states and advocacy groups to shape the future of these programs.
A Narrower Window for Innovation
The era of broad, administration-led "demonstration" opportunities appears to be drawing to a close. Future 1115 waivers are likely to be limited to targeted, small-scale pilot programs rather than the systemic transformations that defined the 2022–2024 period. For states, this means that the "flexibility" promised by Section 1115 is becoming increasingly constrained by federal mandates and a more rigorous, skeptical review process.
Conclusion
The Section 1115 waiver program remains a vital, albeit increasingly restricted, component of the American healthcare landscape. As the U.S. moves toward the 2027 implementation of federal work requirements, the focus of state Medicaid programs will necessarily shift from expansion and social-need integration to administrative compliance and the maintenance of core, traditional services. While the "reentry" and "justice-involved" initiatives provide a rare area of continued growth, the overarching trend is one of retrenchment. Policymakers, healthcare providers, and beneficiaries must prepare for a period of adjustment as these federal changes ripple through the state-level systems that provide coverage to millions of Americans.
About the Author