The landscape of American public health is undergoing a tectonic shift. Following the enactment of the 2025 federal reconciliation law, states across the nation are grappling with a dual crisis: a massive contraction in federal Medicaid funding and a complex mandate to overhaul their internal healthcare delivery systems. As the Congressional Budget Office (CBO) projects a $911 billion reduction in federal Medicaid spending over the 2025–2034 period, the safety net that supports millions of low-income Americans is being fundamentally restructured, setting the stage for a volatile period in state fiscal policy and healthcare access.
The Magnitude of the Shift: Main Facts
The 2025 reconciliation law is not merely a budgetary adjustment; it represents a philosophical and structural pivot in how the federal government interacts with state Medicaid programs. By 2034, the CBO estimates that the cumulative effect of these changes will result in 7.5 million additional uninsured individuals.
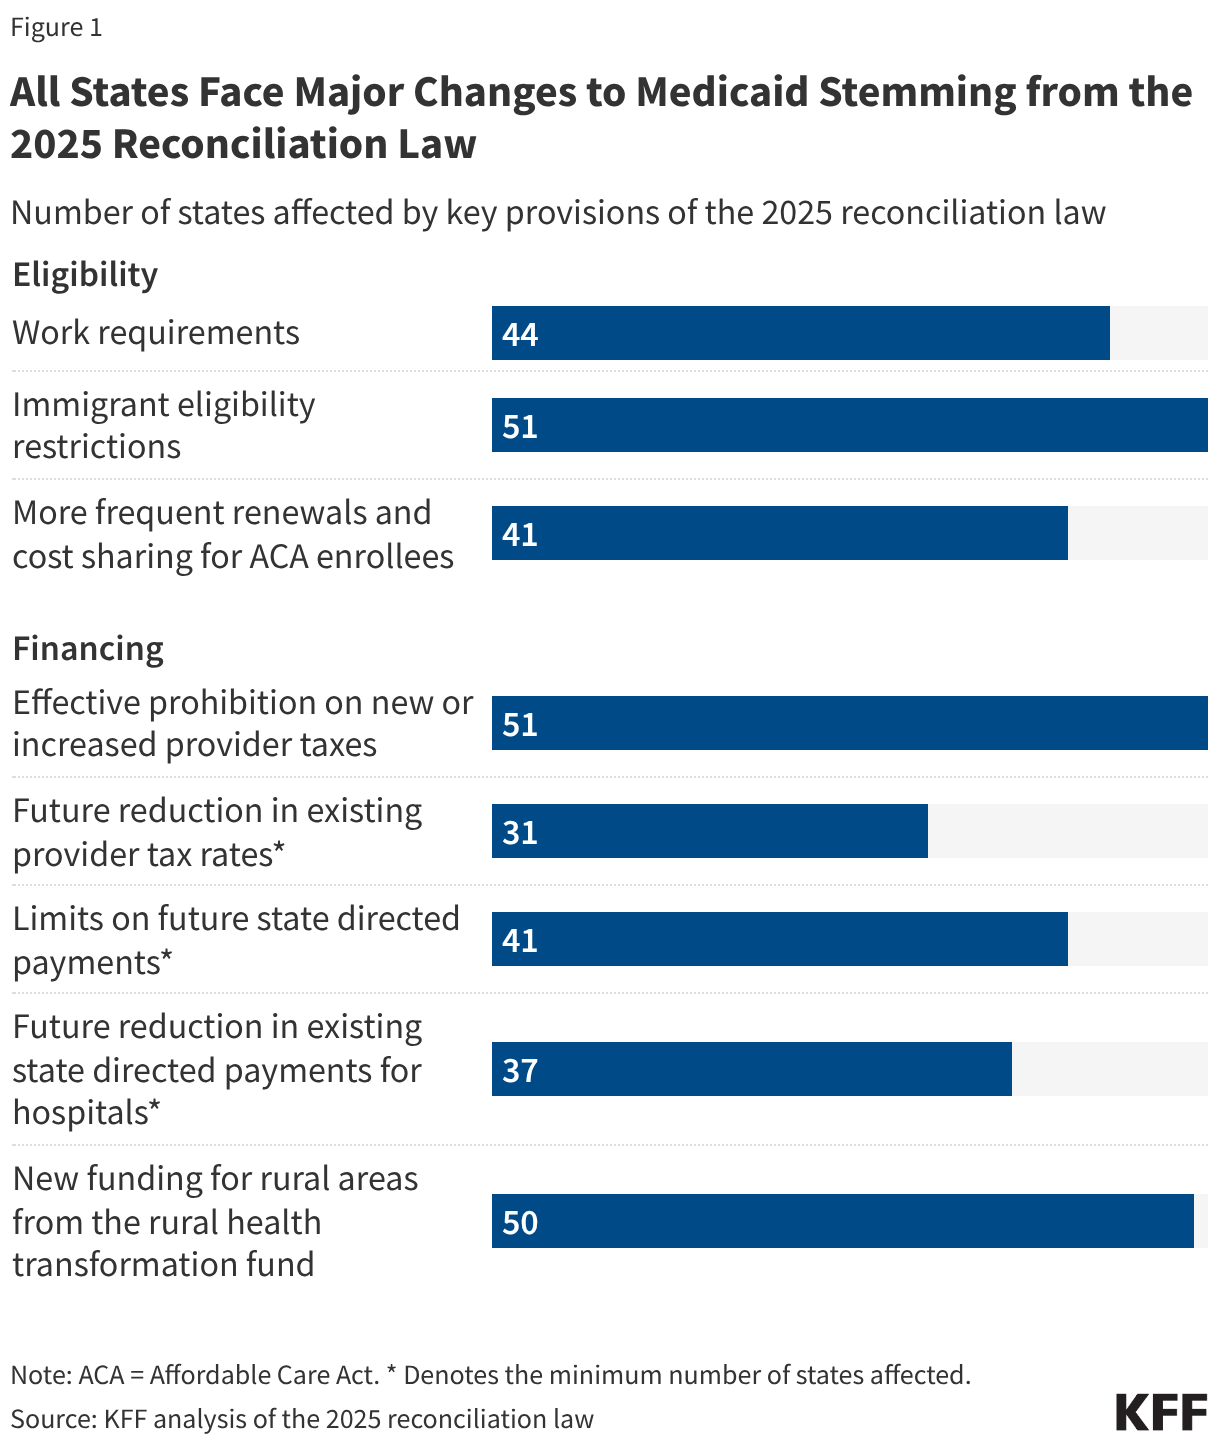
While policymakers attempted to soften the blow with a $50 billion "rural health transformation program"—a stopgap fund designed to support vulnerable rural hospitals—analysts are clear: these funds are insufficient to offset the broader federal retrenchment. All 50 states have accepted their first-year allotments from this fund, yet the long-term sustainability of rural health systems remains in jeopardy as the fiscal clock on these federal grants begins to tick.

Chronology of the Transition
The implementation of these changes is occurring in a staggered, high-pressure environment:
- 2025: Enactment of the reconciliation law. States begin receiving initial allotments from the $50 billion rural health fund.
- 2026: A critical pivot point. With 36 states holding gubernatorial elections, the administrative burden of implementing complex federal mandates will coincide with a period of intense political transition. At least 19 states are guaranteed to see new leadership, potentially disrupting continuity in Medicaid administration.
- 2027: The threshold for provider tax limits begins to tighten. Starting October 1, the ceiling for net patient revenue collection will drop by 0.5 percentage points annually until it hits a 3.5% floor.
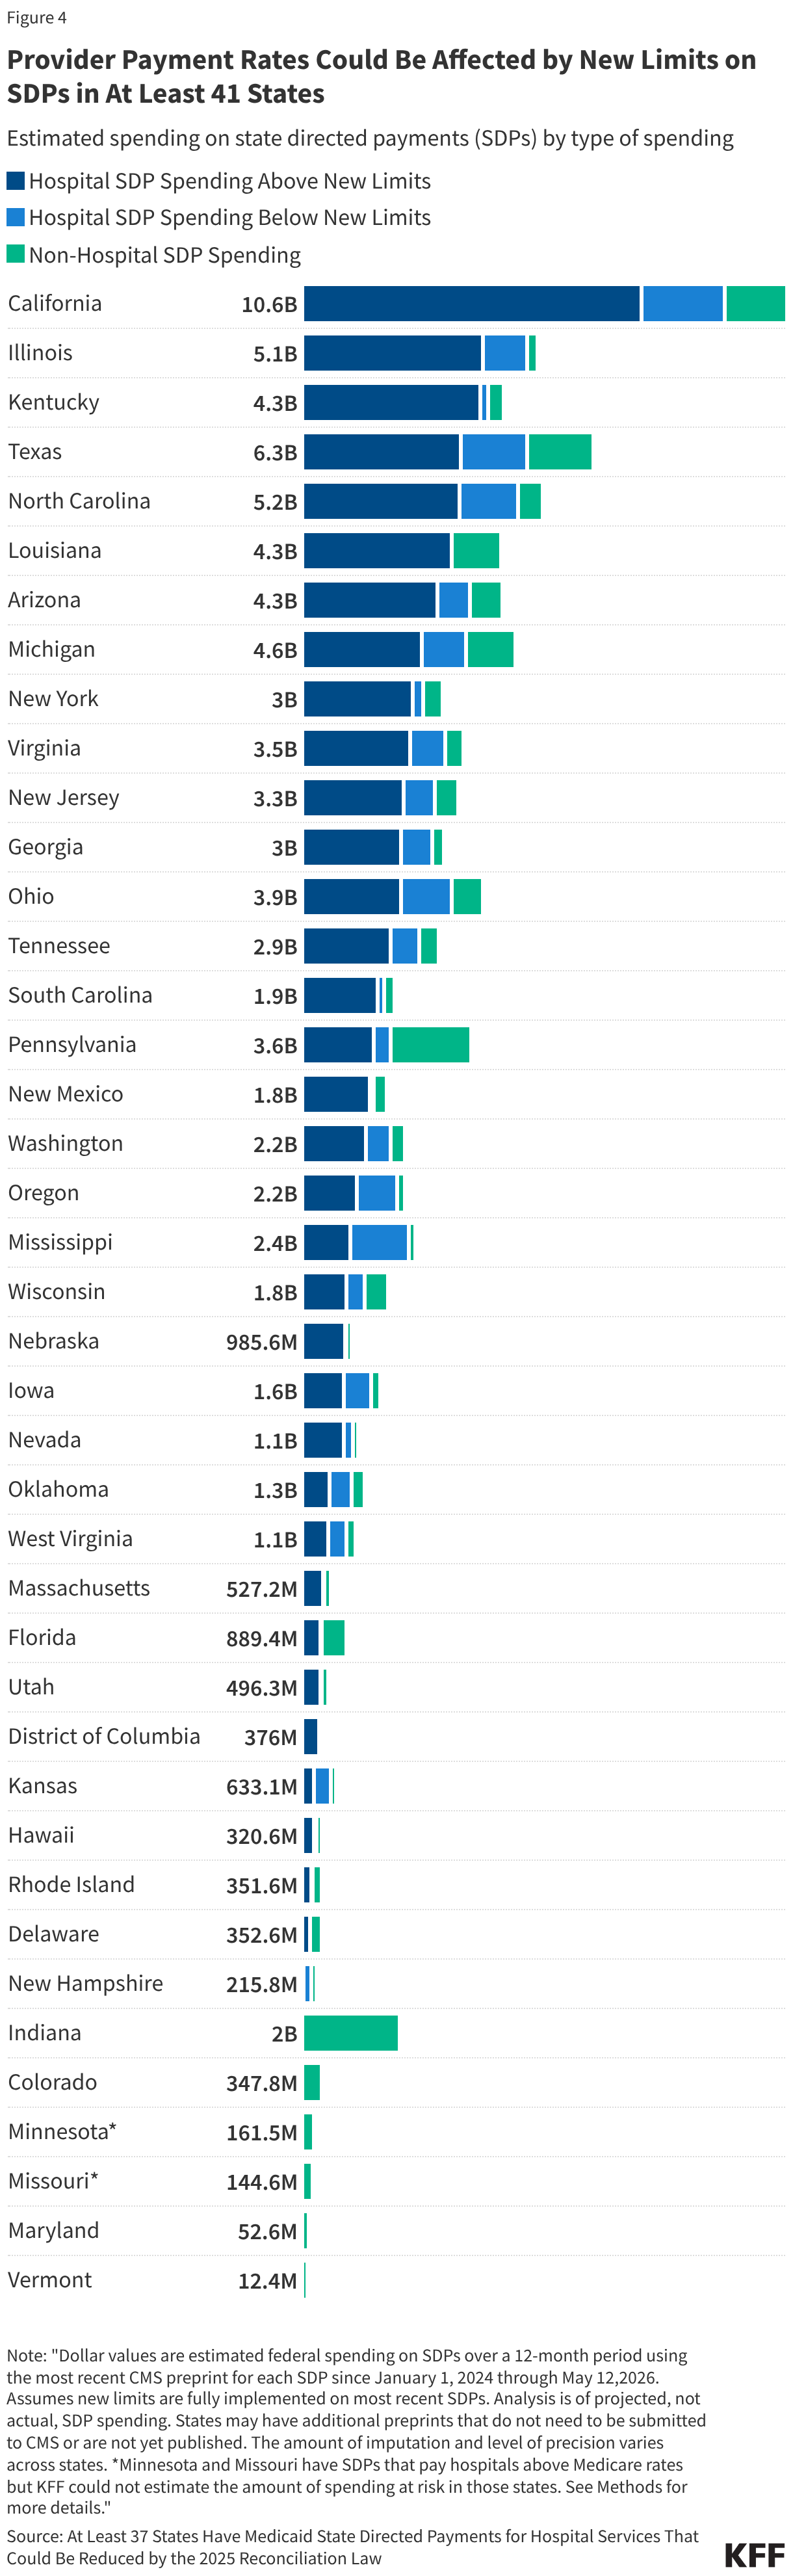
- 2028: New federal caps on State Directed Payments (SDPs) take full effect on January 1. This date marks a potential cliff for hospital funding in at least 37 states that currently rely on these mechanisms to bridge the gap between Medicaid reimbursement and private insurance rates.
- 2034: The end of the ten-year projection window, at which point the cumulative loss of coverage is expected to peak at 7.5 million people.
Supporting Data: The Anatomy of the Cuts
The impact of the 2025 law is uneven, hitting states that embraced the Affordable Care Act (ACA) expansion with disproportionate force. The law introduces three primary mechanisms of restriction:
1. Eligibility Tightening
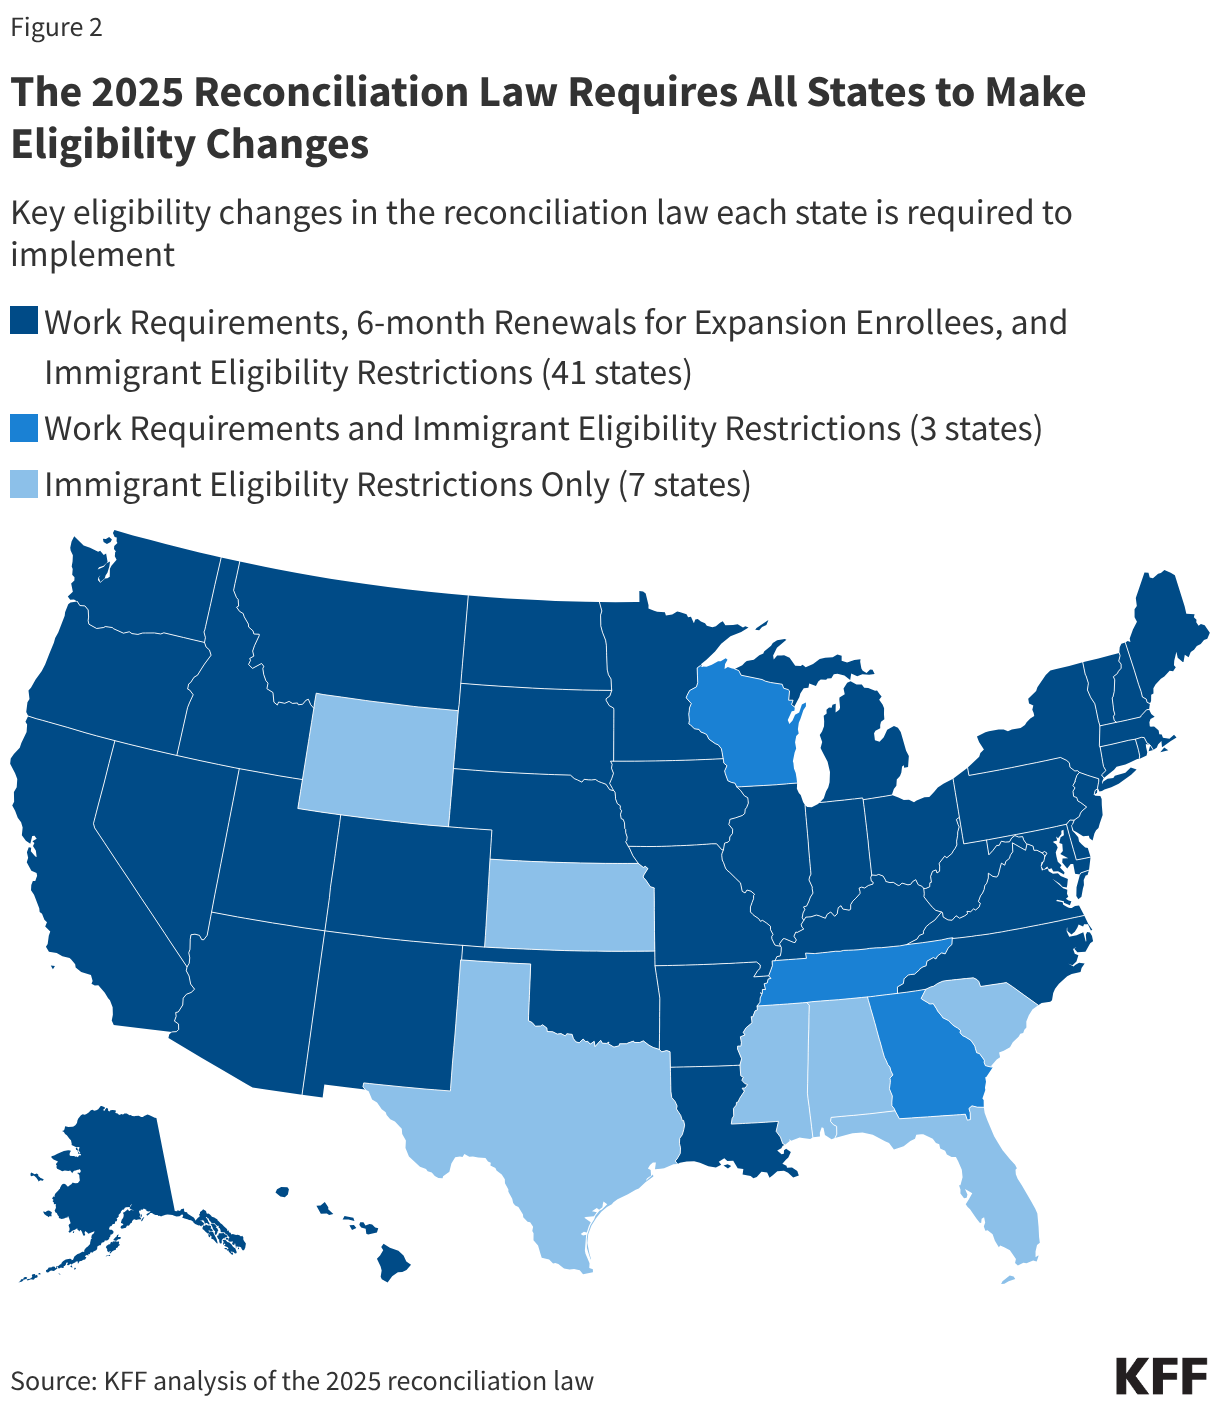
The legislation mandates stricter work requirements and more frequent eligibility redeterminations. By limiting the window for retroactive coverage—reducing it to two months for traditional enrollees and one month for expansion enrollees—the law effectively increases the "administrative churn" that leads to coverage gaps. States that expanded Medicaid are particularly vulnerable to these changes, as the new cost-sharing requirements for adults earning 100%–138% of the Federal Poverty Level (FPL) create new barriers to retention.
2. Financing and Provider Taxes
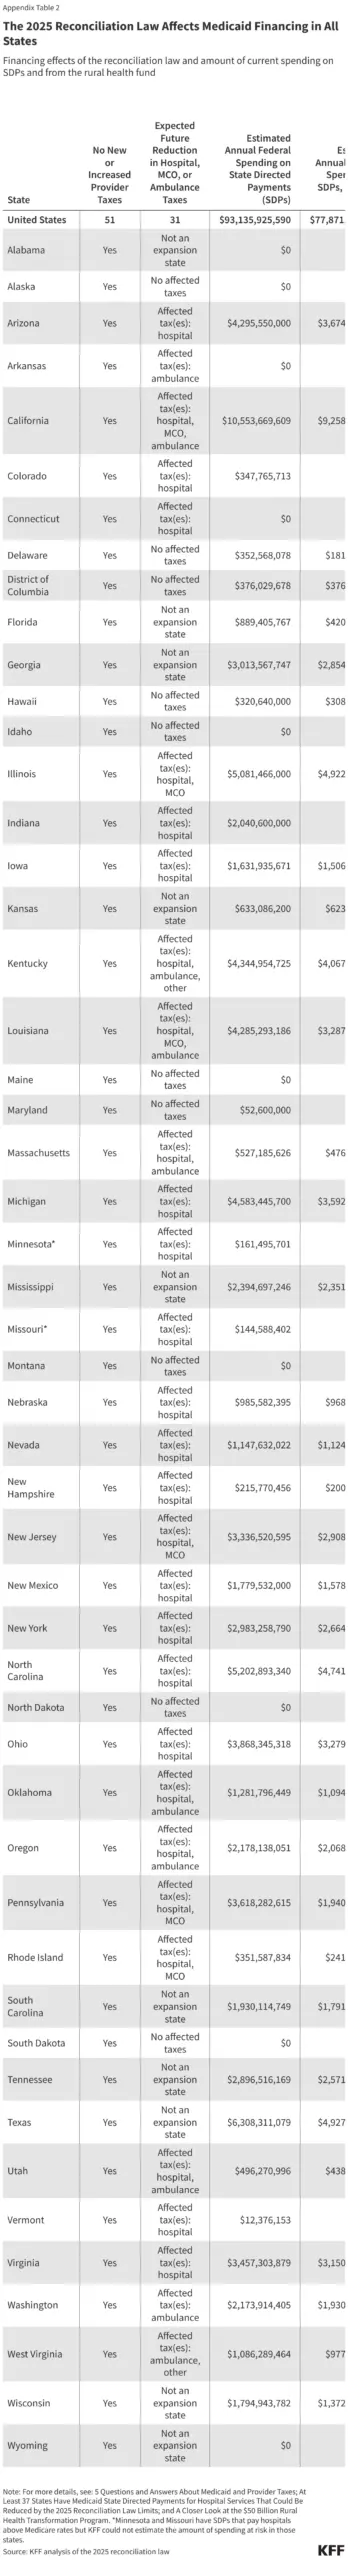
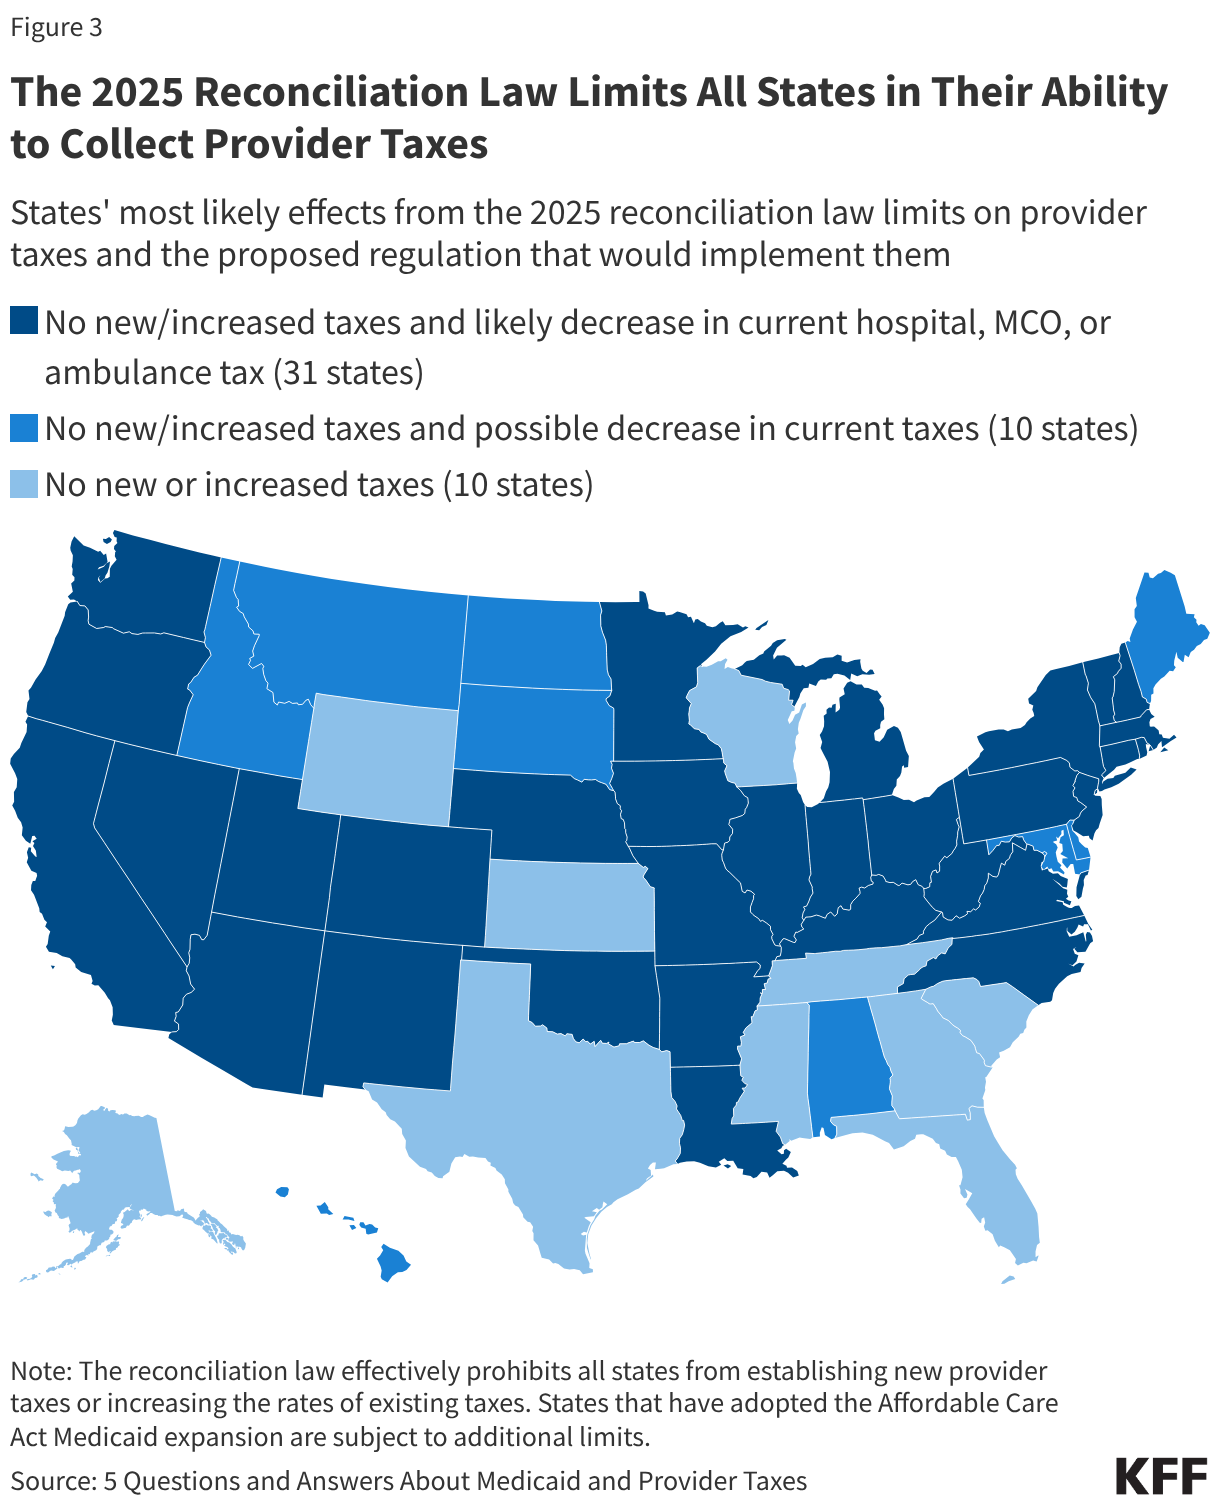
States have historically relied on provider taxes to generate the state share of Medicaid funding. The new law imposes strict caps on these taxes. By limiting the percent of net patient revenues that can be taxed, the federal government is effectively stripping states of a primary tool used to buffer against federal funding cuts. With at least 31 states currently exceeding the 3.5% threshold for certain hospital or managed care taxes, a significant revenue crisis is looming.
3. The SDP "Funding Cliff"
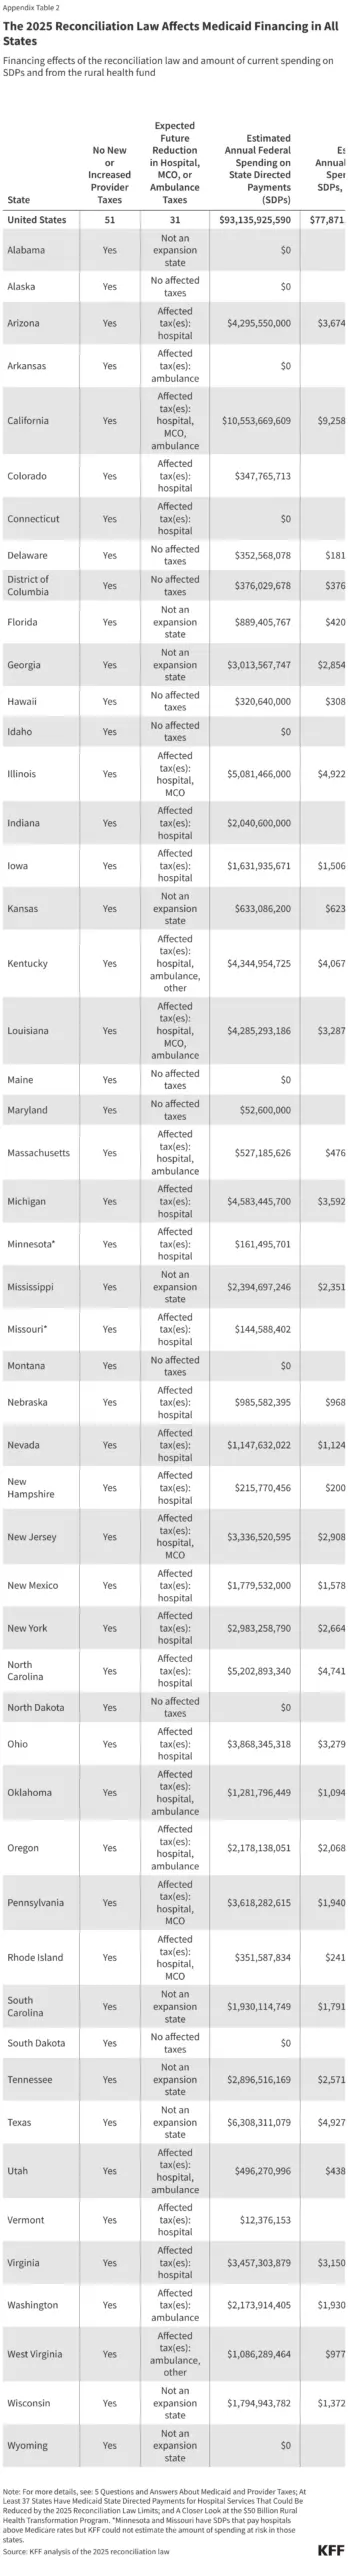
State Directed Payments (SDPs) are the current lifeblood of many hospital systems. Currently, the federal government spends roughly $93 billion annually on these programs, with $78 billion earmarked for hospital services. KFF estimates that $60 billion of this funding exceeds the new federal limits. This means that starting in 2028, hospitals in states like California, Texas, and Illinois face the prospect of a massive, sudden reduction in Medicaid payments, likely forcing them to reduce services or staff.
Official Responses and Political Implications
The political climate surrounding these changes is fraught. In states with upcoming gubernatorial elections, the mandate to implement these cuts creates a "hot potato" scenario for incumbent administrations. If a change in leadership occurs, the incoming administration will inherit a system mid-transformation, with federal rules that are still being finalized.
State health departments have expressed concern that the administrative costs of implementing these new, more complex eligibility requirements may actually offset the savings derived from lower enrollment. "We are being asked to do more with less, while simultaneously building the infrastructure to deny the very people we were previously encouraged to enroll," noted one state health official on the condition of anonymity.
Furthermore, the reliance on the $50 billion rural health fund has been criticized as a "band-aid on a bullet wound." While the funding formula—which distributes 25% based on "state need" and 25% on "proposed initiatives"—aims to be equitable, the disparity is stark. Grants per rural resident range from a mere $66 in Texas to over $6,300 in Rhode Island. This variance highlights the difficulty of creating a one-size-fits-all solution for a national crisis.
Implications: The Road Ahead
The implications of the 2025 reconciliation law are profound and multifaceted:
1. The Shift to Uncompensated Care
As Medicaid enrollment declines, the burden of health costs will not disappear; it will merely shift. Hospitals, particularly those in rural or underserved areas, will see an increase in "charity care" and uncompensated costs. Without the influx of federal dollars provided by SDPs, many of these institutions may face insolvency, leading to the closure of emergency rooms and maternity wards in vulnerable communities.
2. State Budgetary Volatility
States are already dealing with slowing revenue growth. The combination of losing provider tax revenue and the necessity of maintaining state-level Medicaid programs under stricter federal rules will force governors to make painful choices. Expect to see significant debates in state legislatures regarding the reallocation of general funds to keep healthcare systems afloat—a move that will inevitably pull money away from education, infrastructure, and public safety.
3. Administrative Paralysis
The 2026 election cycle is likely to create a "policy vacuum." As candidates campaign on the future of their states’ healthcare, the actual administrative work of redetermining eligibility and restructuring provider payments may slow down. This uncertainty creates a "wait and see" approach that could further destabilize the Medicaid managed care market, as private insurers may hesitate to bid on contracts that are subject to such volatile funding rules.
4. The Rural Divide
The rural health transformation program is a time-limited experiment. Because the funds are exhausted over a five-year period, there is no guarantee of what happens on year six. If the initiatives funded by these grants do not result in permanent systemic efficiencies, rural healthcare systems will face a "second shock" once the money runs out, potentially leading to a broader collapse of rural access.
Conclusion
The 2025 reconciliation law represents a fundamental shift in the social contract between the state, the federal government, and the healthcare provider. While proponents argue that these measures provide necessary fiscal discipline, the reality on the ground suggests a period of significant instability. With coverage losses expected to climb into the millions and hospital funding formulas facing a multi-billion dollar contraction, the next decade will be defined by how state governments manage this transition. For millions of Americans, the outcome of this policy shift will determine not just the affordability of their care, but the very existence of the providers they rely upon. As the nation moves toward the 2026 midterms, the "Medicaid question" has shifted from one of expansion to one of survival.
About the Author