The landscape of American public health coverage is currently undergoing a structural shift. With over three-quarters of the nation’s Medicaid beneficiaries now enrolled in comprehensive Managed Care Organizations (MCOs), the program has shifted from a state-administered safety net to a system dominated by private-sector administration. In Fiscal Year 2024 alone, this managed care delivery model accounted for half of all Medicaid spending.
However, this stability is being tested. A confluence of new federal budget mandates, shifting actuarial projections, and a strategic pivot by the nation’s largest health insurers is creating a climate of uncertainty that threatens to disrupt care for millions of vulnerable enrollees. As major players like Elevance Health begin to retreat from state markets, the long-term viability of the Medicaid managed care model faces its most significant stress test in recent memory.
Main Facts: The New Regulatory and Economic Reality
The 2025 federal budget reconciliation law serves as the primary catalyst for the current market instability. By introducing more frequent eligibility redeterminations for expansion adults and new federal work requirements, the law has complicated the already intricate process of setting capitation rates.
In the Medicaid managed care system, MCOs operate on a "capitation" model—a fixed, per-member-per-month payment designed to cover all necessary services. Because these rates must be actuarially sound and are set prospectively, they rely heavily on accurate predictions of member health status, or "acuity." When federal policies change the composition of the Medicaid population—such as pushing healthier, working-age adults off the rolls—the remaining pool of enrollees often becomes more expensive to treat.
Actuaries are struggling to project these shifts, and insurers are signaling that they are no longer willing to absorb the financial risk associated with this unpredictability. The financial data bears this out: according to an analysis of National Association of Insurance Commissioners (NAIC) data, the average Medical Loss Ratio (MLR)—the portion of premium revenue spent on actual medical care—for the Medicaid market climbed from 88% in 2023 to 91% in 2024. This represents the highest average MLR in a decade, indicating that insurers are facing razor-thin margins, or even losses, on their Medicaid portfolios.

Chronology of the Market Pivot
The current wave of market exits did not happen in a vacuum. It follows years of turbulence triggered by the "unwinding" of the pandemic-era continuous enrollment provision, which saw millions of people lose coverage as states resumed eligibility checks.
- Late 2023: Emerging data indicates that the post-unwinding Medicaid population is significantly sicker and costlier than pre-pandemic cohorts.
- FY 2024-2025: Numerous states seek federal approval to retroactively adjust capitation rates to account for the unexpectedly high acuity of remaining members.
- July 2026: During a second-quarter earnings call, Elevance Health executives publicly announce a strategic review of their Medicaid portfolio, stating they will exit markets where the "economics don’t support sustainable performance."
- August 1, 2026: Wellpoint DC (an Elevance subsidiary) officially exits the District of Columbia’s Medicaid program following a mutual agreement with the DC Department of Health Care Finance.
- September 2026: The Louisiana Department of Health confirms that Elevance’s "Healthy Blue" plan will cease operations in the state at the end of the year.
- Ongoing (2026-2027): Industry analysts continue to monitor the remaining "Big Five"—Centene, UnitedHealth Group, Molina, and Aetna/CVS—for further signs of market contraction.
Supporting Data: The Concentration of Power
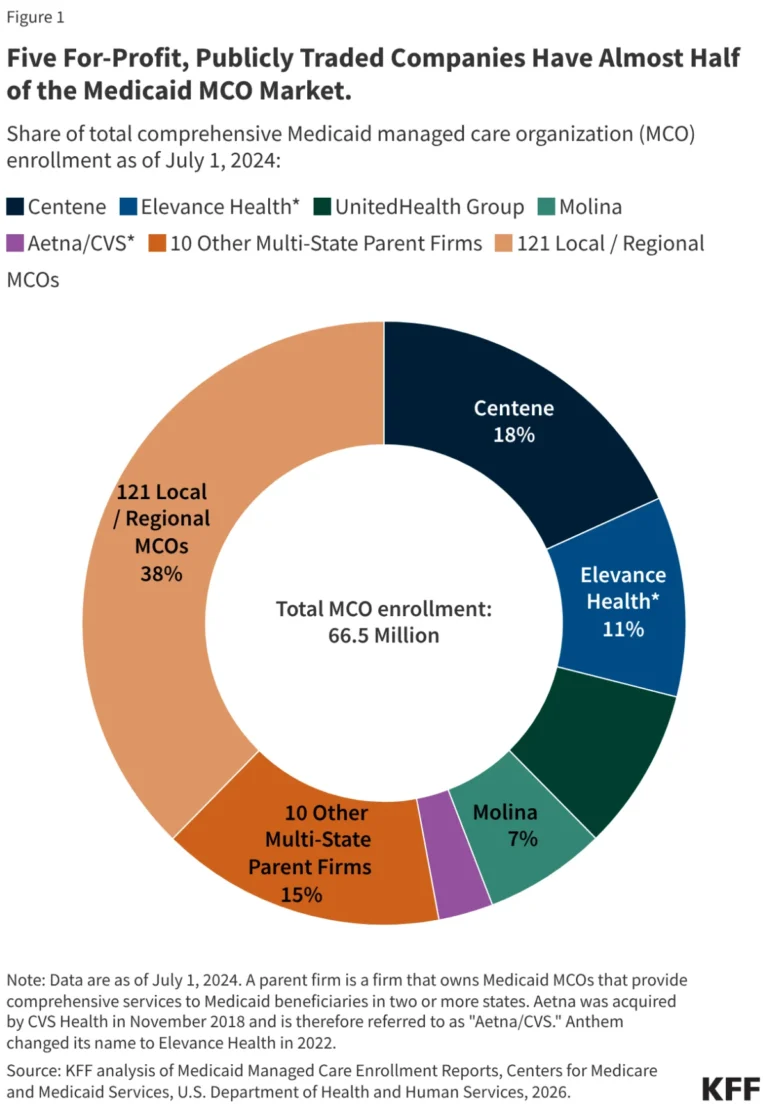
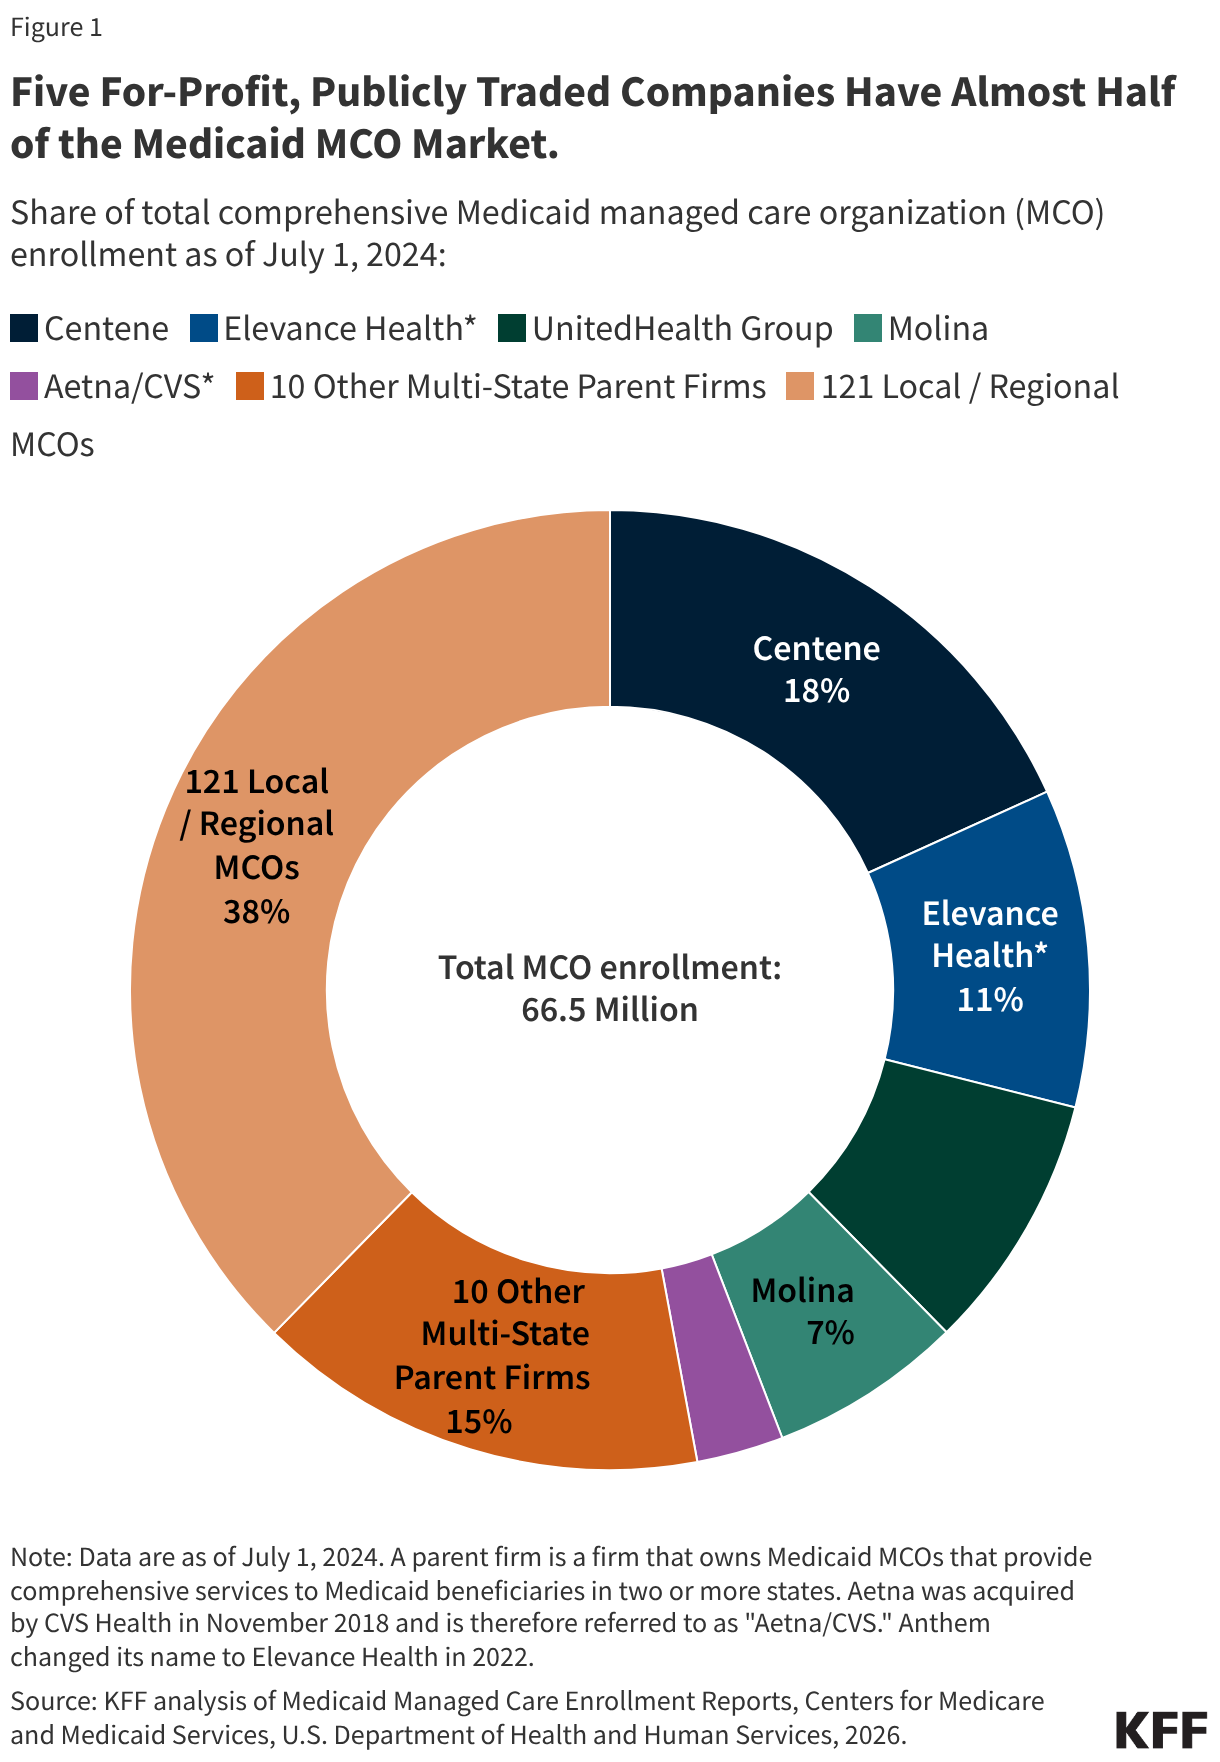
The Medicaid market is highly consolidated. Five for-profit, publicly traded companies—Centene, Elevance Health, UnitedHealth Group, Molina, and Aetna/CVS—account for nearly 50% of all Medicaid MCO enrollment nationally.
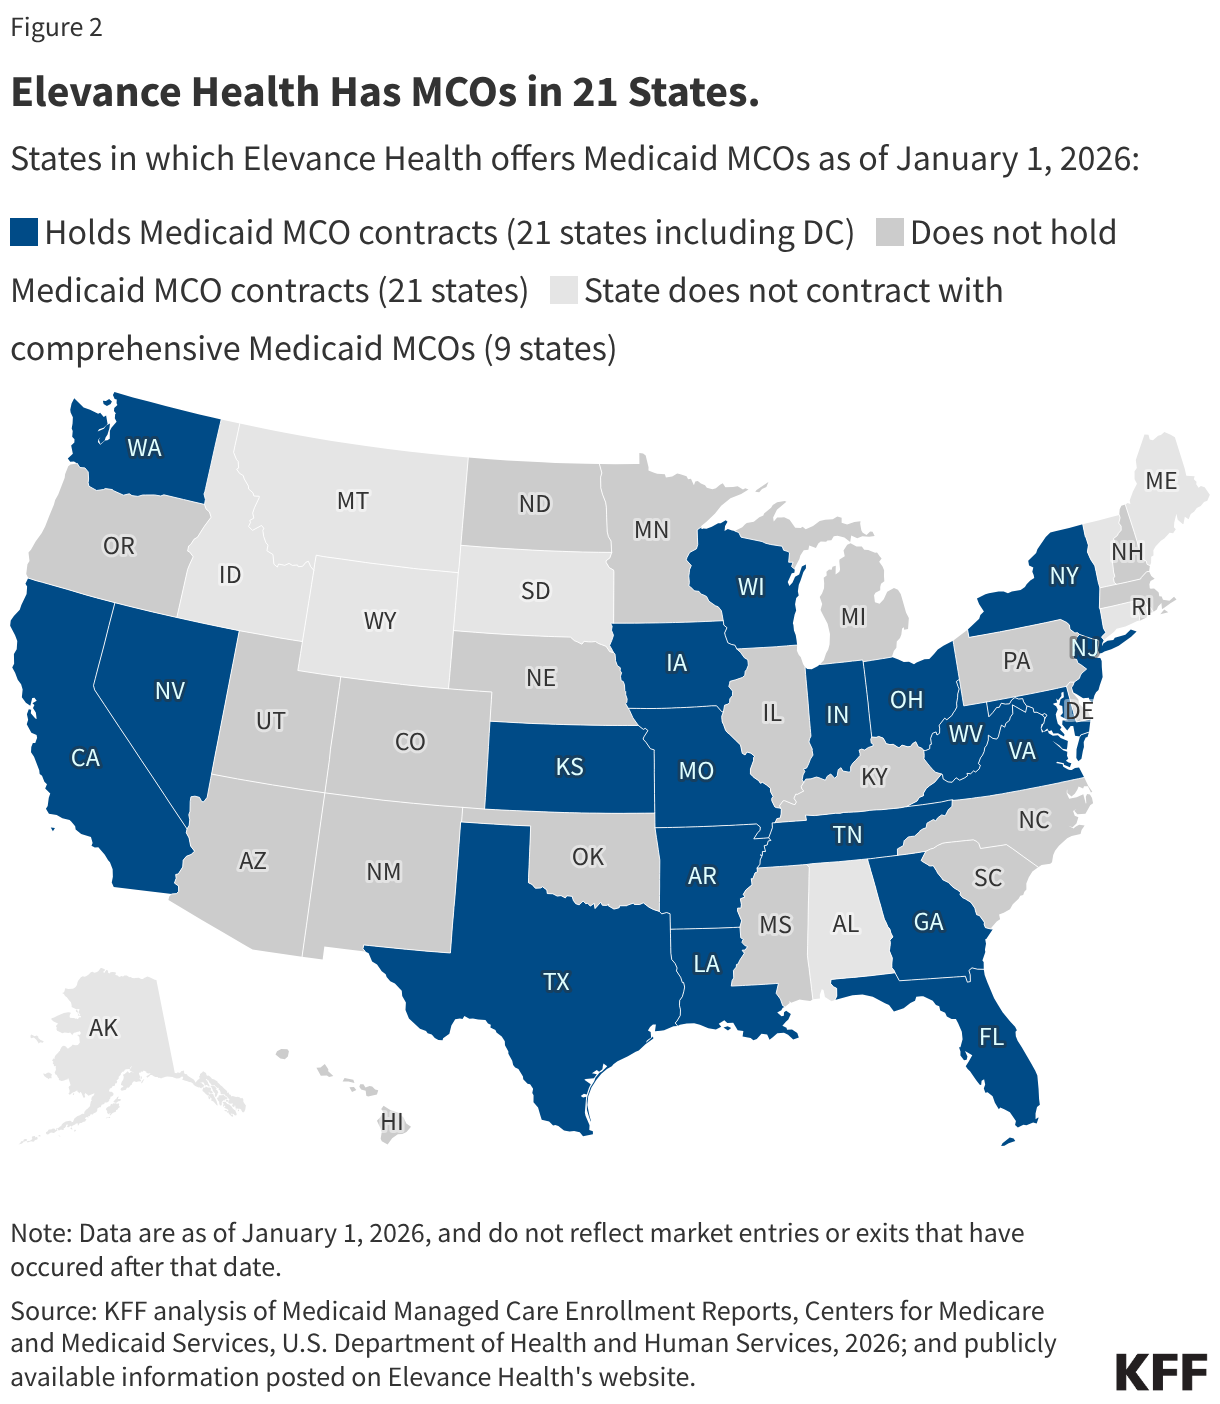
These firms maintain massive geographic footprints, with each operating in at least 13 states. Because of this concentration, a decision by a single parent firm to exit a market is not merely a business transaction; it is a public health event. When a company like Elevance, which operates in 21 states, determines that a market is no longer sustainable, it necessitates a massive re-enrollment effort for thousands of members, placing an immense administrative burden on state agencies and local providers.
The financial pressure is further exacerbated by state-level policies. As states grapple with their own budget constraints, many are tightening caps on provider taxes and reducing state-directed payments. These fiscal tightening measures, combined with the federal mandates of the 2025 reconciliation law, have created a "perfect storm" for insurers, forcing them to choose between profitability and market share.
Official Responses and Strategic Outlook
The response from the insurance sector has been one of cautious retrenchment. During Q2 2026 earnings calls, while other industry giants like Centene and UnitedHealth did not explicitly announce mass exits, they emphasized a "disciplined approach" to capital allocation. Centene’s move to exit Arkansas’s Medicaid expansion program in 2027 serves as a bellwether, suggesting that even if firms remain in major markets, they may begin to prune specific, high-risk or low-margin segments of their business.
Elevance Health executives have been the most vocal, noting that while the extreme acuity spikes seen during the unwinding have begun to moderate, overall medical utilization remains significantly higher than pre-2020 levels. The firm has projected a negative 1.75% operating margin for its Medicaid segment in 2026, a figure that effectively necessitates a pivot to maintain shareholder value.
State officials, meanwhile, are caught in a difficult position. While they possess the authority to mandate contract requirements—such as requiring exiting plans to provide transition services and transfer data to new carriers—they have little power to force a private entity to remain in a market where it is losing money.
Implications: The Human and Systemic Cost
The potential consequences of this market instability are multi-layered, affecting stakeholders from the patient to the policymaker.
For Enrollees: Care Disruption
The most immediate danger is to the enrollees themselves. When an MCO exits a market, patients often face a "continuity of care" crisis. Even with federal safeguards in place, the administrative reality is that patients may be forced to switch doctors, lose access to long-standing care teams, or face gaps in prior authorizations for life-sustaining medications. For individuals with chronic conditions or those currently pregnant, these transitions are not just administrative hurdles—they are direct risks to health outcomes.
For Providers: Administrative Burden
Physicians, clinics, and hospitals are also under strain. When an MCO exits, providers must navigate the credentialing and billing processes of a new plan. This adds a layer of red tape that diverts resources away from clinical care. In regions where a single insurer previously held a large market share, the transition can lead to significant revenue cycle disruptions for community health centers that rely heavily on Medicaid reimbursements.
For the Market: The Competition Paradox
There is a complex debate regarding the long-term impact on market health. Some analysts argue that the exit of lower-performing plans could ultimately lead to a more efficient, higher-quality market. However, the prevailing concern is one of reduced competition. In states where only a few insurers operate, the exit of one or two firms leaves the remaining plans with increased leverage, which could drive up costs for states and limit the variety of plans available to beneficiaries.
Looking Ahead
The 2025 reconciliation law and the resulting wave of insurer exits mark a pivotal moment for the Medicaid program. As states continue to balance their budgets against the rising cost of health care, the reliance on the private sector will be tested. Whether this era of volatility leads to a more sustainable, streamlined managed care model or a fracturing of the nation’s primary safety net remains to be seen. What is clear is that the "set it and forget it" era of Medicaid managed care is over; the future of the program will require a more proactive, adaptive, and collaborative approach between state governments and their private-sector partners.
About the Author