As the United States barrels toward the 2026 midterm elections, a seismic shift in the nation’s social safety net has moved to the center of the political discourse. The 2025 reconciliation law, a sweeping piece of legislation enacted by Congress last year, has fundamentally altered the trajectory of Medicaid—the bedrock of American health coverage for the nation’s most vulnerable populations.
With 81 million enrollees, Medicaid currently functions as the primary provider of comprehensive health and long-term care for low-income families, individuals with disabilities, and the elderly. It is a financial pillar of the U.S. health system, accounting for approximately $1 out of every $5 spent on healthcare nationwide. However, new projections from the Congressional Budget Office (CBO) suggest that the landscape is set for a dramatic, decade-long contraction.
The Fiscal Reality: A $911 Billion Shift
The cornerstone of the 2025 reconciliation law is a massive reduction in federal Medicaid spending. According to the CBO’s most recent analysis, the legislation is projected to slash federal outlays by $911 billion between 2025 and 2034. The human cost of this fiscal tightening is equally stark: experts estimate the law will result in 10 million additional uninsured Americans by 2034.
This contraction presents a "trilemma" for state governors and legislatures. To compensate for the evaporation of federal dollars, states are now facing a series of agonizing choices: implement deep cuts to Medicaid benefits, slash funding for other essential state programs like education or infrastructure, or raise taxes on their residents. The impact of these choices will not be felt equally; states that aggressively expanded Medicaid under the Affordable Care Act (ACA) are expected to bear the brunt of the burden.
A Chronology of the 2025 Legislative Overhaul
To understand the current volatility in the healthcare sector, one must look at the timeline of the legislative changes that have brought the system to this juncture:
- Early 2025: Congress introduces the reconciliation package, framed by proponents as a necessary step toward long-term fiscal sustainability and federal deficit reduction.
- Mid-2025: The legislation is signed into law. Immediately, healthcare advocacy groups and state budget offices begin modeling the potential fallout, noting that the "reconciliation" process bypassed traditional long-form debate, leading to rapid, systemic changes.
- Late 2025: Initial administrative data begins to reflect the tightening of eligibility criteria and the sunsetting of certain pandemic-era protections, leading to the first waves of enrollment churn.
- 2026 (The Current Moment): As the midterm elections approach, the political implications of the law become clear. Healthcare costs have surged to the top of the list of voter concerns, with the legislative impact on Medicaid becoming a primary wedge issue in congressional campaigns across the country.
Supporting Data: Mapping the Coverage Landscape
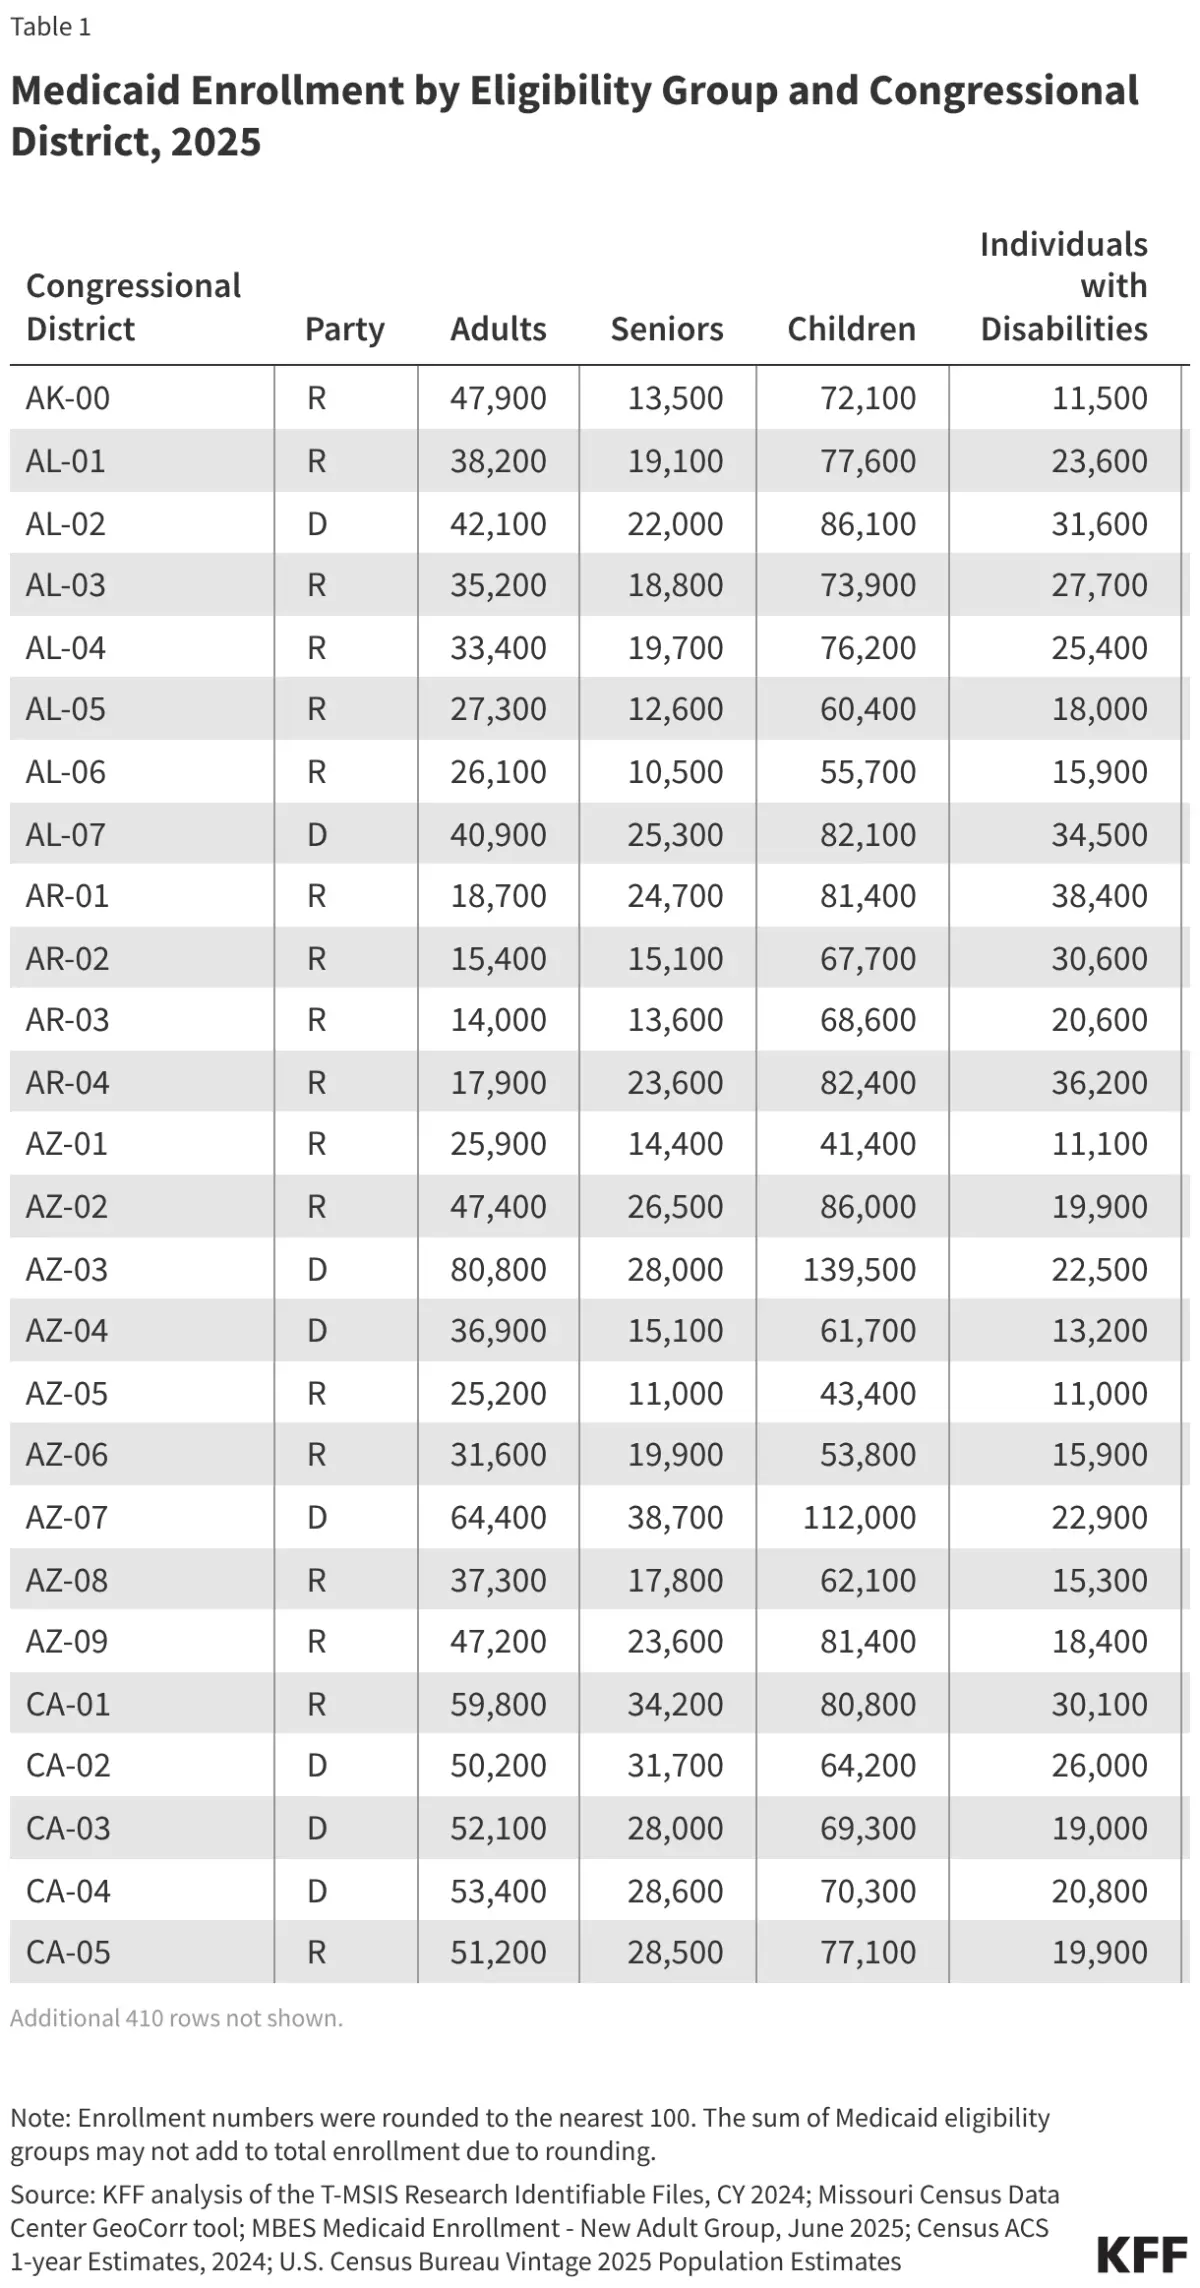
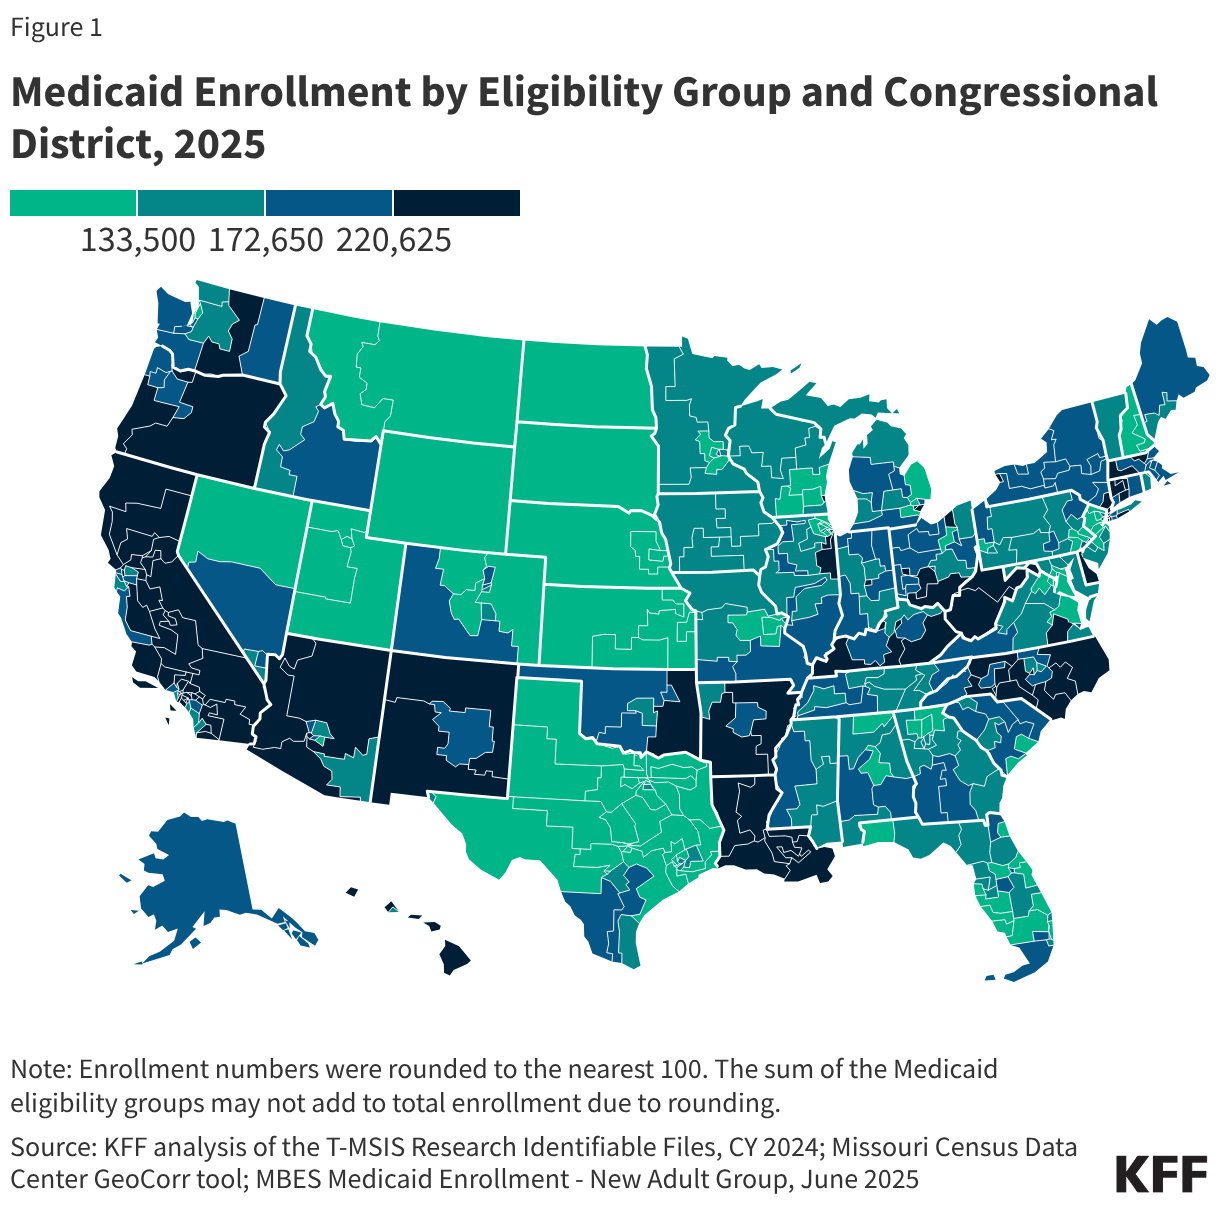
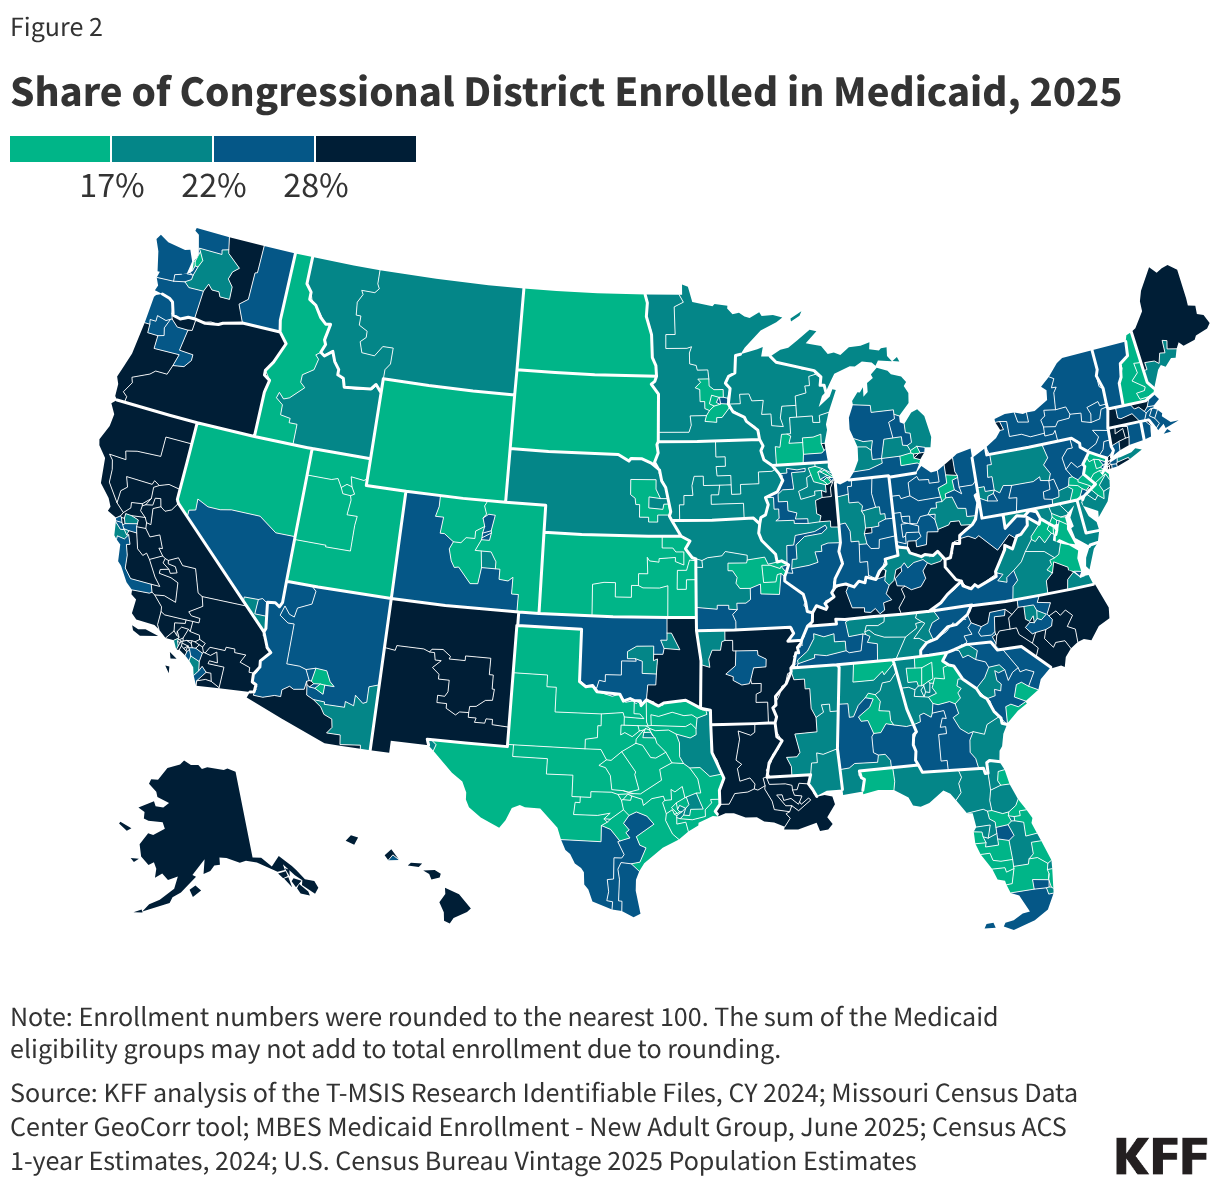
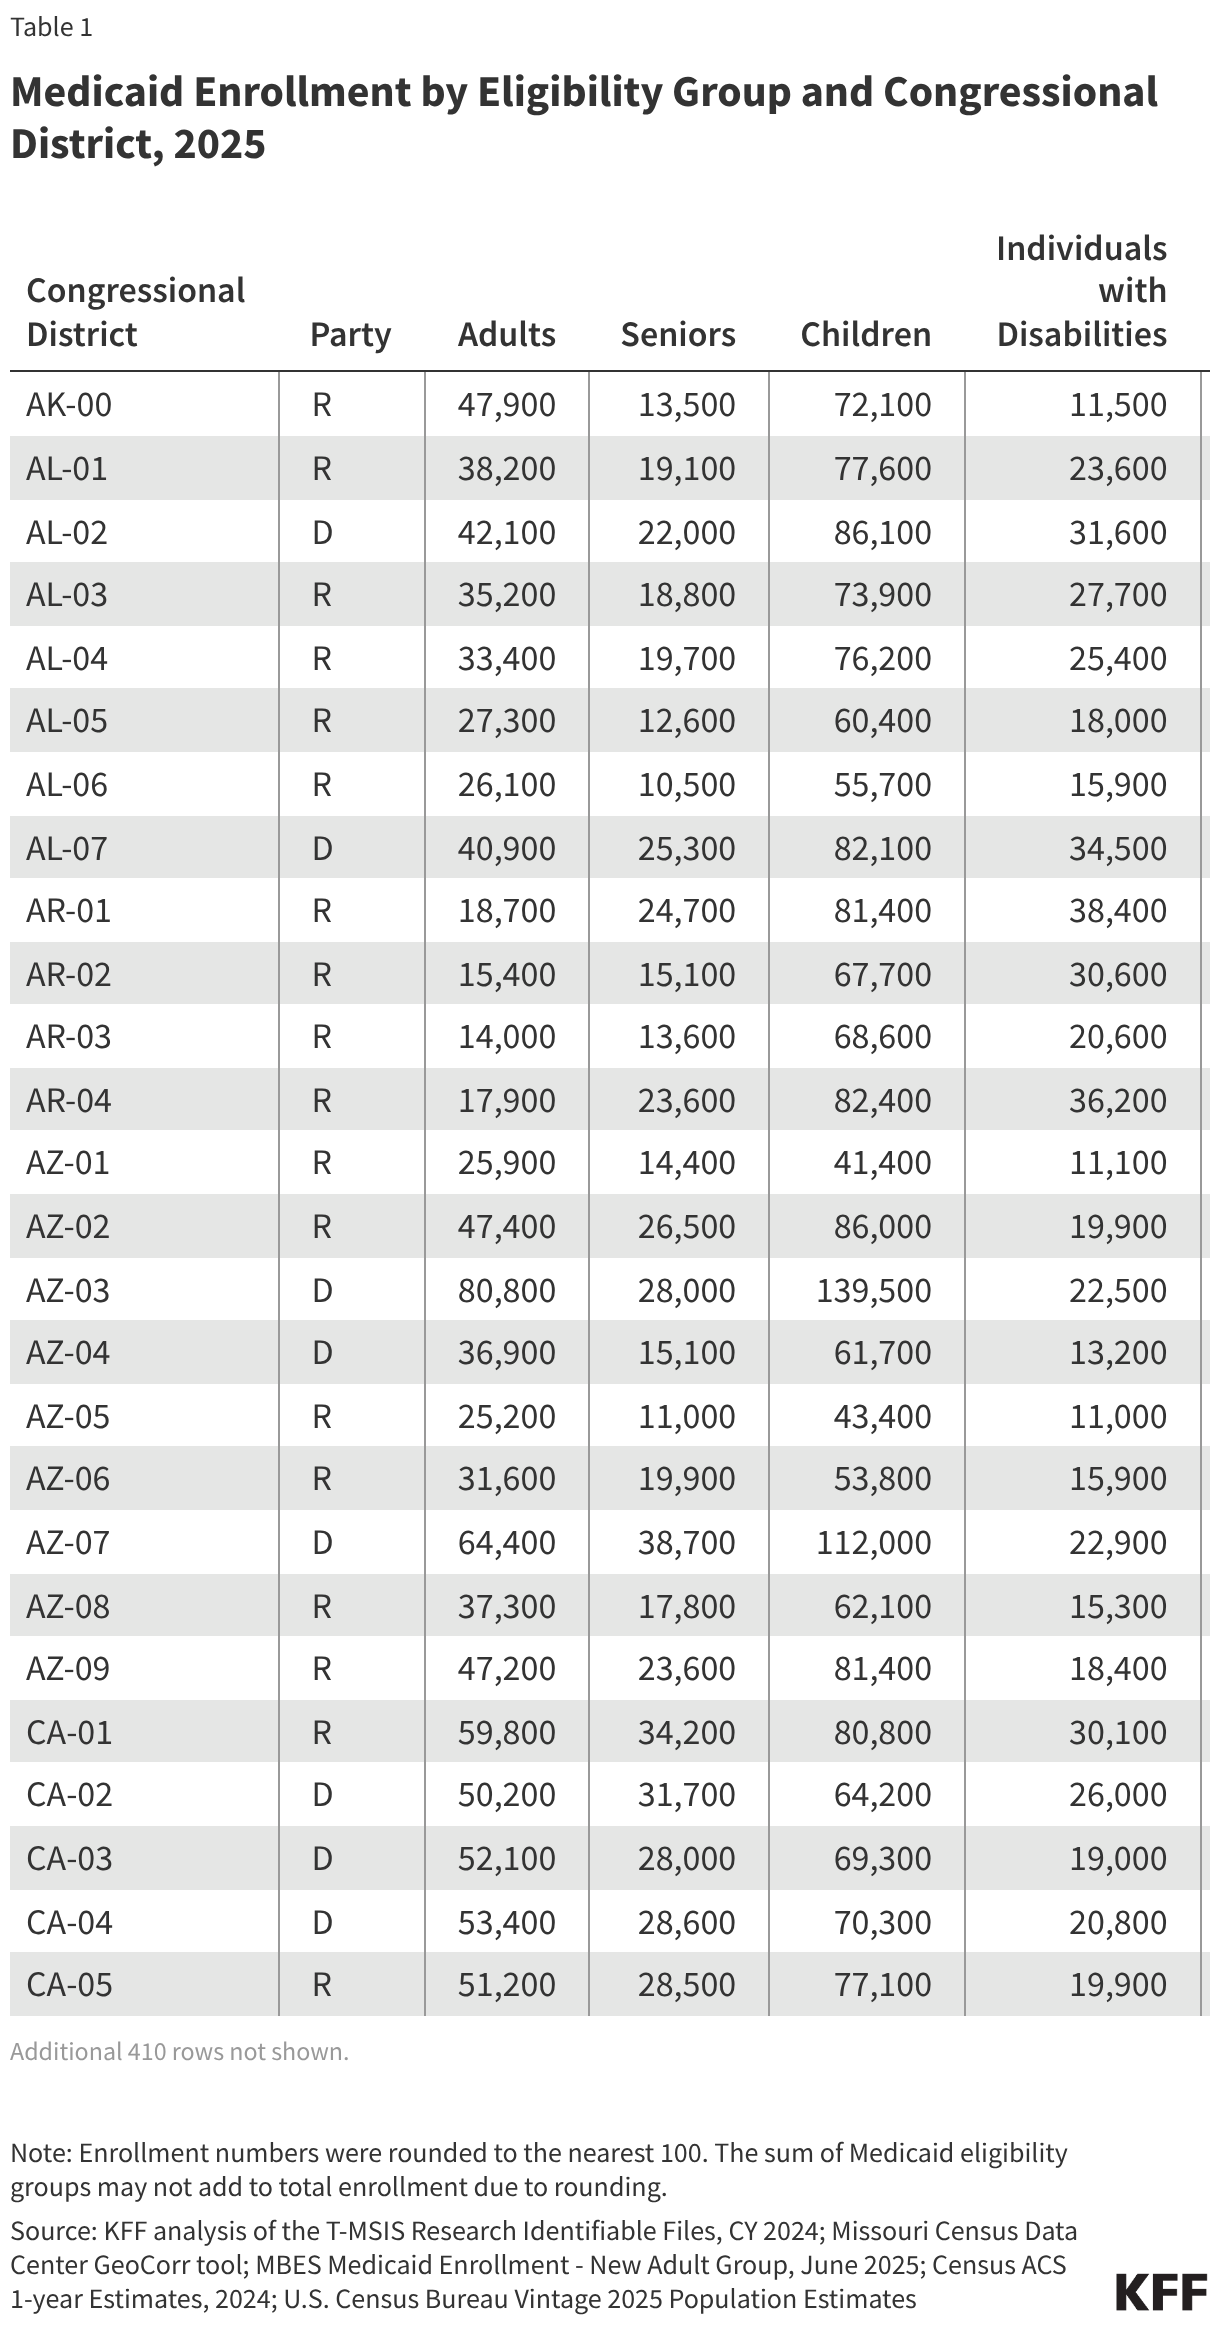
The current state of Medicaid enrollment is a reflection of local economic conditions and political priorities. New interactive mapping tools—which utilize the 2024 Transformed Medicaid Statistical Information System (T-MSIS) and Census data—reveal the geographic concentration of Medicaid dependence.
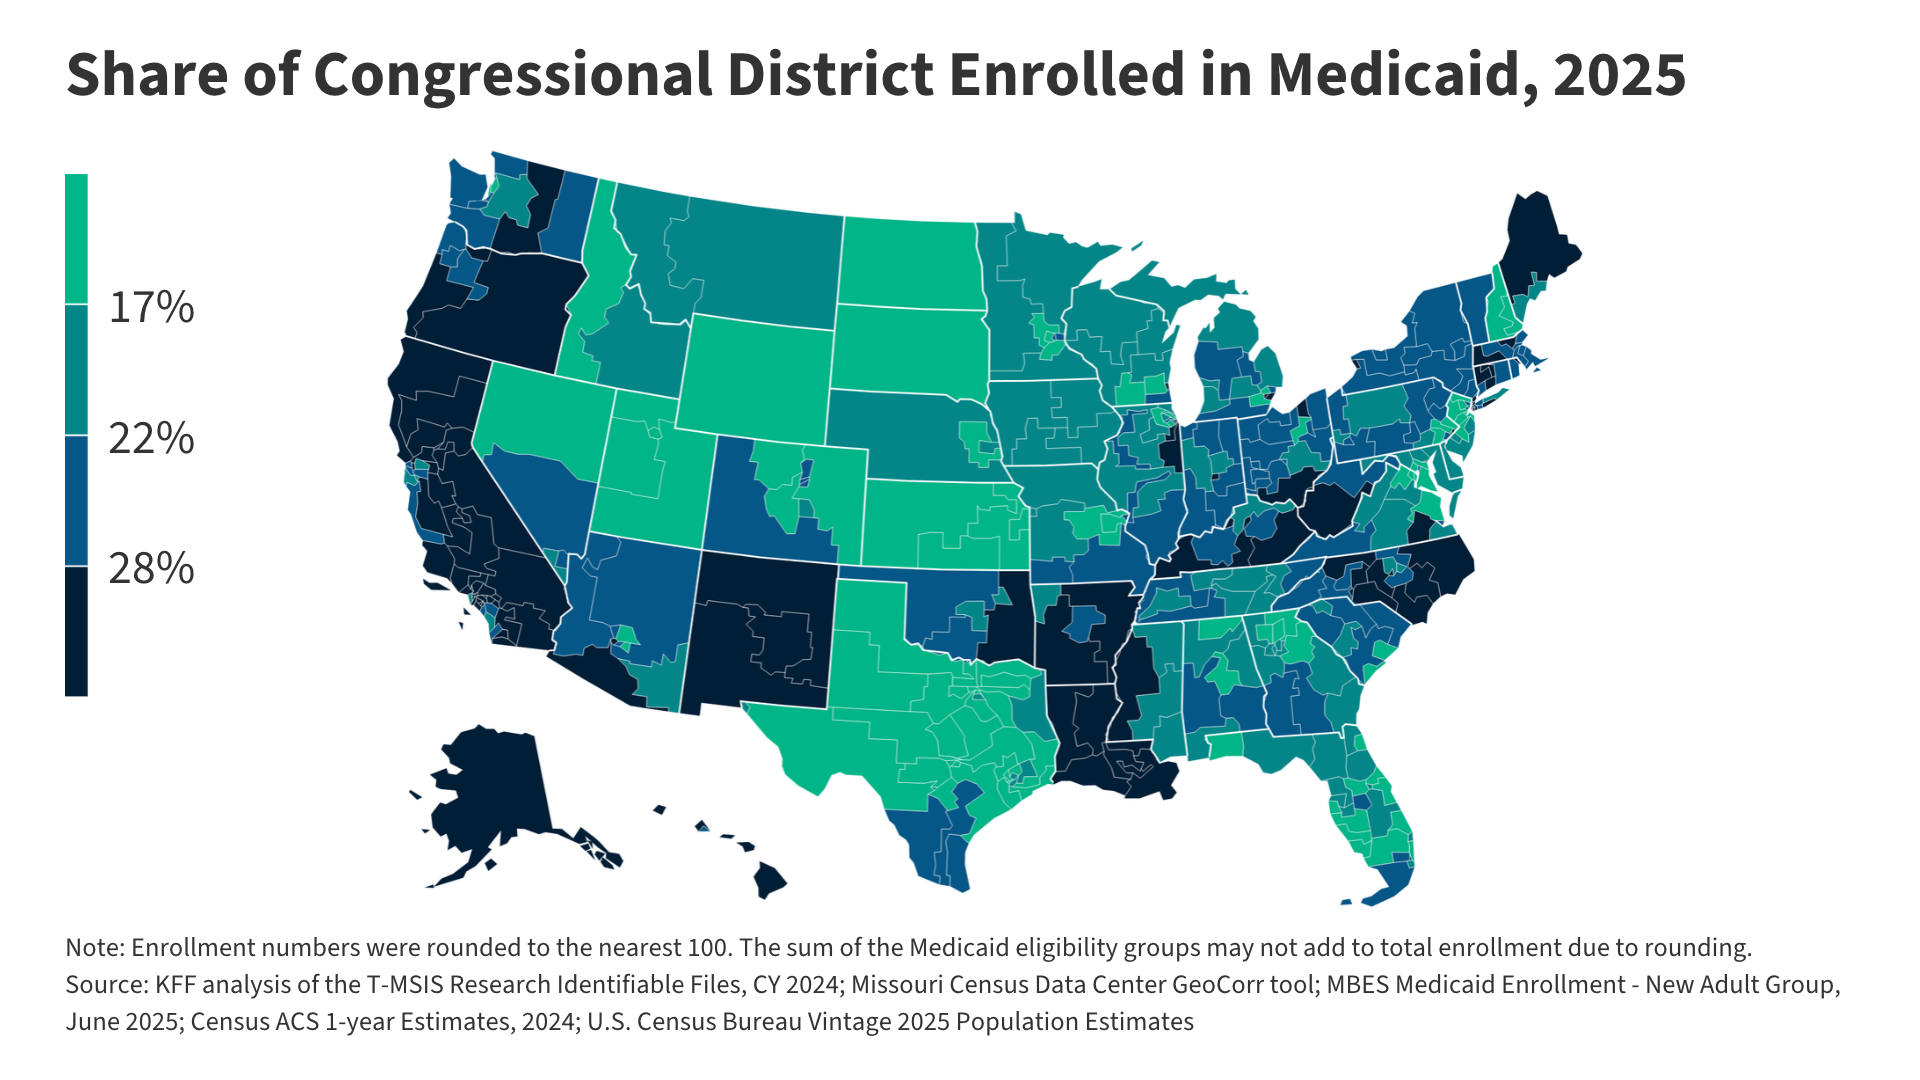
In some congressional districts, particularly in the rural South and the urban centers of the Northeast, Medicaid serves nearly 40% of the total population. These maps illustrate a clear correlation between lower median household incomes and high Medicaid enrollment, highlighting the vital nature of the program as a buffer against poverty-induced health crises.
The data confirms that the enrollment numbers vary significantly by eligibility group—children, the disabled, the elderly, and the "new adult" group added under the ACA expansion. The analysis reveals that in districts where the "new adult" group represents a large share of the local economy, the 2025 law’s impact is likely to be disproportionately severe.
The Methodology Behind the Numbers
The complexity of assessing Medicaid’s reach requires a multi-layered analytical approach. Because Medicaid is managed at the state level but tracked by federal administrative systems, calculating the impact on a specific congressional district is a rigorous data-science challenge.
The analysis provided here synthesizes several high-level data sources:
- T-MSIS (Transformed Medicaid Statistical Information System): Used to capture granular, person-level enrollment data.
- GeoCorr 2022: A critical tool for reconciling zip code-based health data with political boundaries (congressional districts).
- Census American Community Survey (ACS): Used to estimate the total population of districts to determine the percentage of residents covered by Medicaid.
- MBES (Medicaid Budget and Expenditure System): Used for real-time reporting on the "new adult" expansion group.
For states that underwent redistricting (such as Texas, Florida, and Ohio), the researchers utilized county-to-district crosswalks, as census data is more robust at the county level. In states without recent redistricting, 1-year ACS estimates provided the foundation. By assigning a political party to each district based on the current incumbent, the research provides a transparent view of which parties may face the most political pressure regarding these healthcare outcomes in the 2026 midterms.
Official Responses and Political Implications
The political response to the 2025 reconciliation law has been deeply polarized. Supporters of the legislation argue that the $911 billion reduction is a necessary correction to prevent federal overspending and to encourage states to implement more efficient, market-based healthcare solutions. They contend that the program had become bloated and that the changes force states to innovate rather than relying on a "blank check" from Washington.
Conversely, critics and health policy analysts warn of a looming public health crisis. They argue that by stripping coverage from 10 million people, the law will lead to delayed care, increased emergency room utilization, and worse health outcomes for chronic conditions.
"The choices states are being forced to make are not merely administrative," says one senior analyst. "They are existential. When you cut Medicaid, you aren’t just saving money—you are effectively removing the safety net from the working poor and the disabled."
As the 2026 midterms approach, voters are increasingly scrutinizing the voting records of their representatives. In districts where Medicaid enrollment is high, the "cost of care" has evolved from an abstract economic metric into a lived reality. Candidates who voted for the reconciliation package are now defending those votes against accusations that they prioritized deficit reduction over the health of their constituents.
Looking Ahead: The Future of the Safety Net
The implications of this law extend well beyond the current election cycle. The decade-long window of the CBO projections means that the impact of the 2025 reconciliation law will be felt by the American healthcare system until 2034.
State legislatures are currently in a race against time. Some are exploring public-private partnerships to fill the coverage gap, while others are bracing for significant increases in uncompensated care costs—the expenses incurred by hospitals when they treat uninsured patients. These costs are often passed on to private insurers, which may lead to higher premiums for the broader workforce, creating a ripple effect that touches those not even enrolled in Medicaid.
As we move toward the 2026 elections, the debate over Medicaid is no longer just about federal spending; it is a debate about the social contract. With 81 million lives directly impacted, the question for voters is clear: Is the fiscal stability of the federal government worth the potential instability of the nation’s health? The answer to that question will likely define the political map for years to come.
For more detailed research, polling, and ongoing coverage of healthcare policy in the 2026 election cycle, visit the KFF "Health in the 2026 Midterm Elections" series.
About the Author