Since the Supreme Court’s landmark decision in Dobbs v. Jackson Women’s Health Organization on June 24, 2022, the American reproductive healthcare landscape has undergone a seismic and permanent shift. By overturning Roe v. Wade, the Court effectively dismantled the federal constitutional right to abortion that had stood for nearly half a century. In its wake, the United States has devolved into a patchwork of state-level policies, where a person’s ability to access essential reproductive care is determined almost entirely by the state in which they reside.
As of late 2026, the nation remains deeply divided. For many, this has meant the total loss of local access to abortion; for others, it has meant navigating an increasingly complex legal and logistical maze to secure care.
The New Reality: A State-by-State Breakdown
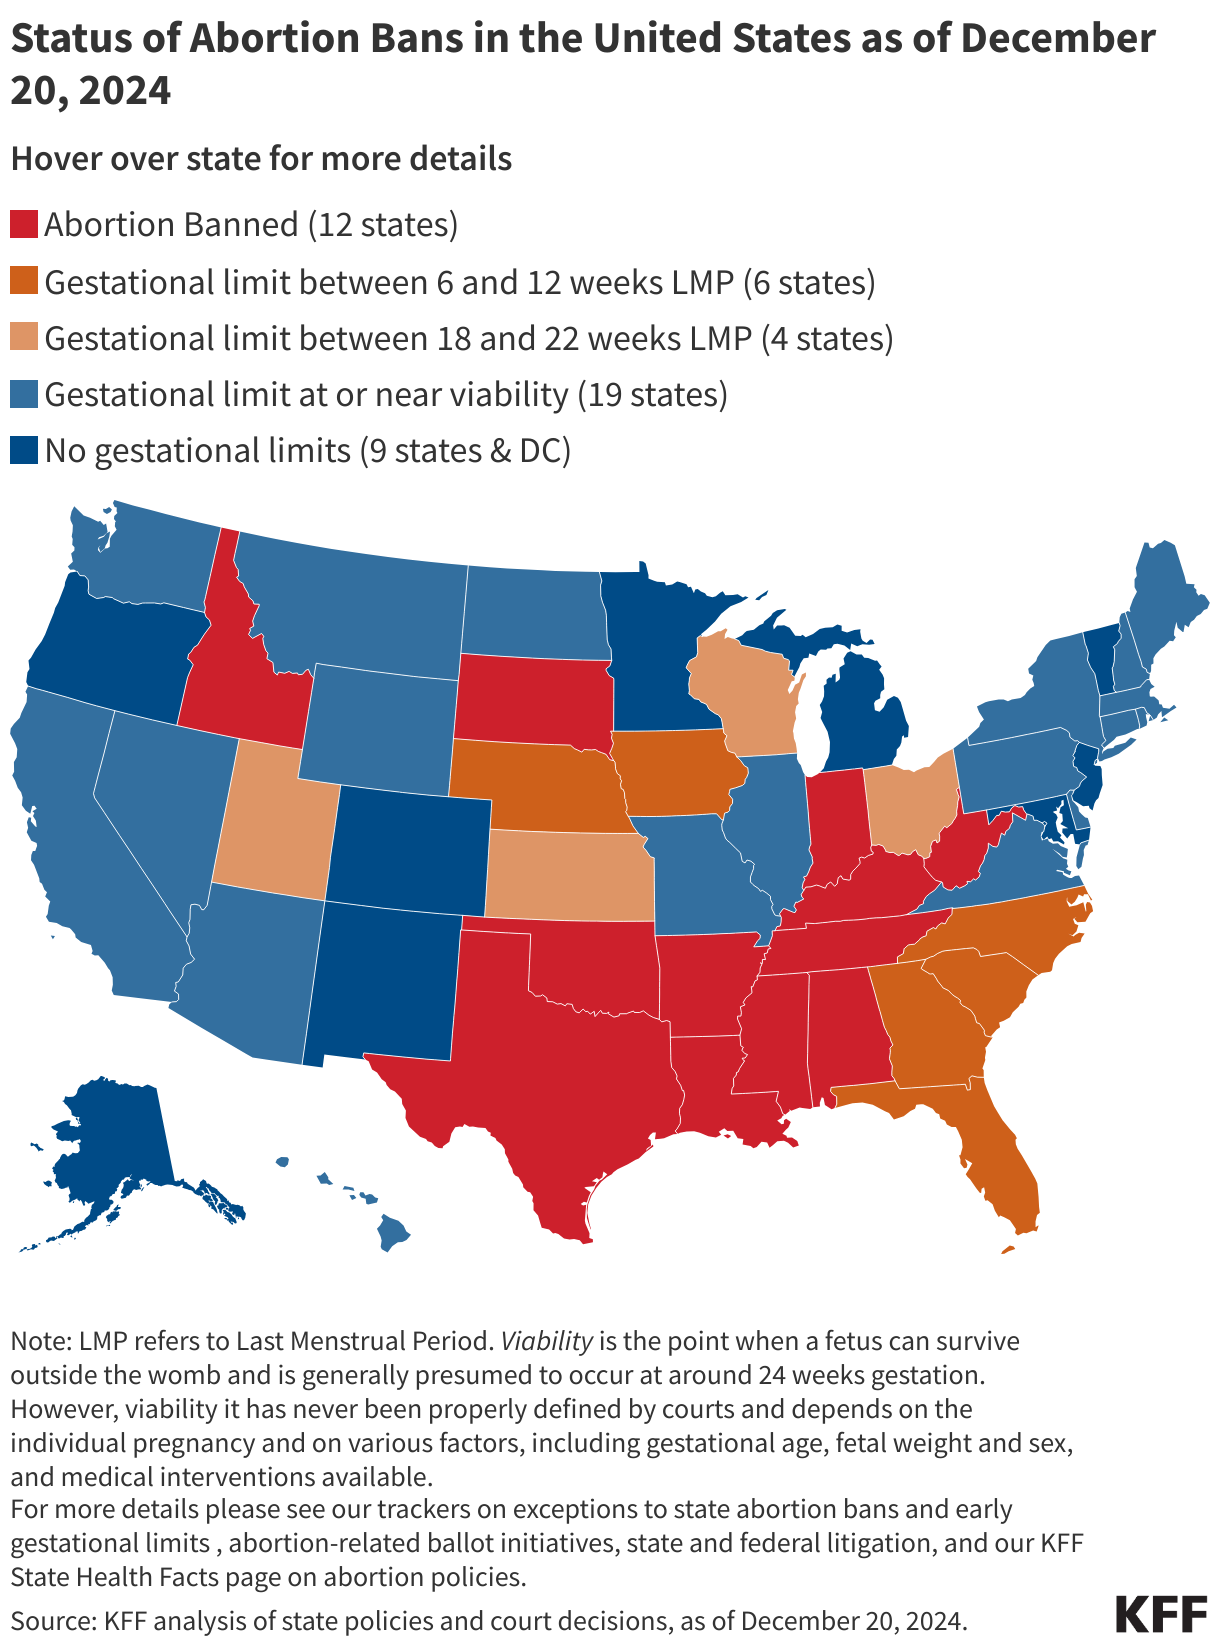
The current legislative environment is characterized by stark regional disparities. According to the latest data from the Abortion in the United States Dashboard, the nation can be categorized into several distinct tiers of access.
Total Bans and Strict Limitations
In 13 states—including Alabama, Texas, Tennessee, and Idaho—abortion is effectively banned, with few to no exceptions. These bans have forced clinics to shutter, leaving residents to travel hundreds of miles to the nearest facility that offers legal services.
A second tier of states has implemented "early gestational" limits, typically ranging from 6 to 12 weeks of pregnancy. In states like Florida, Georgia, Iowa, and South Carolina, the 6-week mark acts as a functional ban for many, as patients often do not know they are pregnant until after that window has closed.
The Middle Ground and Protective Havens
A smaller cohort of states, including Kansas, Ohio, and Utah, maintains gestational limits between 15 and 22 weeks. Meanwhile, 17 states—ranging from California to New York and Illinois—have codified protections for abortion access up to the point of fetal viability. Finally, a group of 10 states, including Colorado, Massachusetts, and Oregon, alongside the District of Columbia, have no gestational limits, effectively ensuring that abortion remains a legal medical option throughout pregnancy.
A Chronology of Legal and Policy Shifts
The timeline of this transition has been marked by continuous litigation and emergency judicial intervention.
- June 24, 2022: The Supreme Court issues its ruling in Dobbs, removing federal protections for abortion.
- June 27, 2024: In Moyle v. United States, the Supreme Court sidestepped a definitive ruling on whether the federal Emergency Medical Treatment and Labor Act (EMTALA) preempts state bans. By dismissing the case and returning it to lower courts, the justices reinstated a temporary order allowing doctors in Idaho to provide emergency abortion care if a patient’s health is in immediate jeopardy, though the broader legal conflict remains unresolved.
- Late 2024–2026: Throughout this period, states have aggressively contested the scope of the Comstock Act—an 1873 law that, if interpreted broadly by a hostile administration, could be weaponized to criminalize the mailing of abortion medication and supplies across state lines, effectively creating a national ban through regulatory enforcement.
Supporting Data: Understanding Patient Experiences
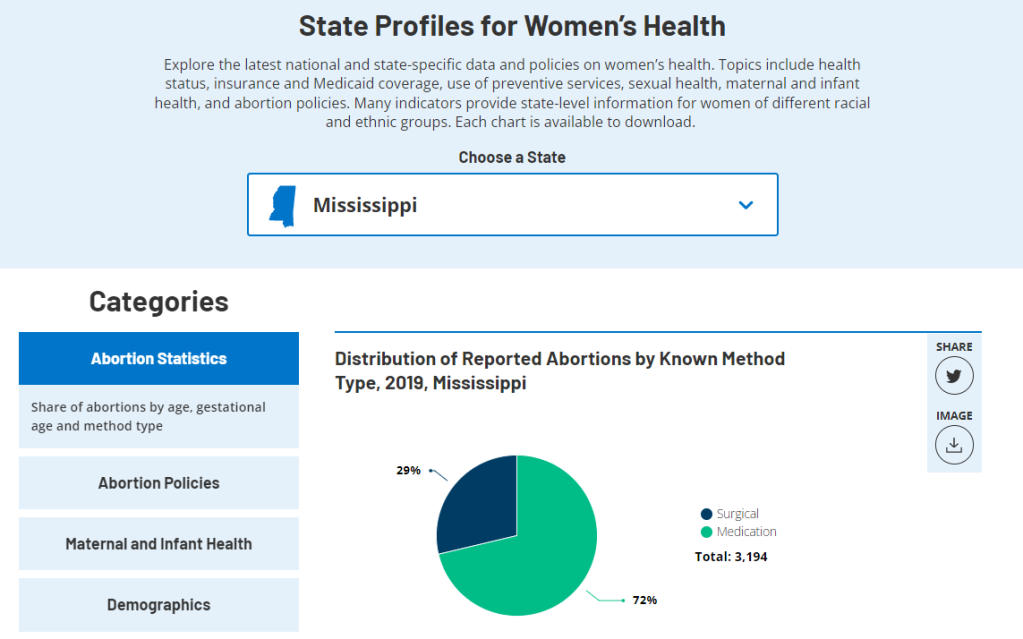
Recent data from the 2026 KFF Women’s Health Survey offers a grim portrait of the current climate. Despite the political noise, the medical reality of abortion remains consistent: the vast majority of procedures occur early. Statistics show that 45% of abortions occur by six weeks of gestation, and 36% occur between seven and nine weeks. Only 7% of abortions occur after the first trimester, typically involving complex medical circumstances.
However, awareness of these realities is declining. KFF polling indicates that the public’s knowledge of mifepristone—the primary medication used for abortion—is waning. As of late 2026, fewer than half of all adults believe abortion pills are safe, a significant drop from public sentiment just two years prior. This shift suggests that misinformation campaigns and ongoing FDA reviews have successfully muddied the waters regarding standard reproductive medical practices.
Official Responses and Institutional Impacts
The legal, medical, and corporate worlds have struggled to adapt to the post-Roe reality.
The Crisis Pregnancy Center Proliferation
A burgeoning area of concern is the rise of Crisis Pregnancy Centers (CPCs). These organizations, which often lack the regulatory oversight of medical clinics, are increasingly receiving state and federal funding. Their legal status and their ability to provide medically accurate counseling remain points of intense scrutiny, as advocates worry that these centers often prioritize ideological goals over patient health.
The Corporate Dilemma
The private sector has also been drawn into the fray. Many large employers have attempted to offer travel benefits to employees residing in states with restrictive laws. However, this has triggered a wave of "legal jeopardy." Employers now face questions about the privacy of their employees’ health records, with the Health Insurance Portability and Accountability Act (HIPAA) potentially proving insufficient to protect patient data from states seeking to criminalize out-of-state travel for care.

Professional Risks for Physicians
Physicians are perhaps the most impacted, facing an unprecedented level of legal risk. In many jurisdictions, providing care that falls into a legal "gray zone" can result in not only the loss of a medical license but also criminal prosecution. This has led to the "chilling effect," where doctors delay life-saving care for fear of being charged with a felony, even in instances where the pregnancy poses a clear threat to the patient’s life.
Implications: The Future of Reproductive Health
The cumulative effect of these policies is a two-tiered healthcare system in the United States.
The Erosion of Equity
The most immediate implication is the widening gap in health equity. Low-income individuals, people of color, and those living in rural areas are disproportionately affected by travel requirements and the rising costs of care. For these populations, a 6-week ban is not a regulation; it is an absolute prohibition.
The Battle Over Sexual Assault Exceptions
The discourse surrounding rape and incest exceptions has proven to be largely performative. Analysis shows that in many of the 11 states that claim to have such exceptions, the administrative hurdles—such as requiring a police report, navigating narrow gestational windows, and finding a provider willing to perform the procedure—make accessing care nearly impossible.
The Looming Threat of the Comstock Act
Perhaps the most significant looming issue is the potential revival of the Comstock Act. If future federal administrations choose to enforce this archaic law, they could effectively bypass state laws that protect abortion. By targeting the supply chain—the mail, the pharmacies, and the shipping companies—the federal government could restrict access to medication abortion nationwide, regardless of a state’s own protective statutes.
Conclusion
The post-Roe era is not merely a legal debate; it is a profound transformation of the American healthcare landscape. As states continue to diverge in their legislative approaches, the burden of navigating this uncertainty falls squarely on the patients. With the intersection of medical care, legal liability, and political ideology becoming increasingly volatile, the coming years will likely see continued litigation, further degradation of the medical-patient relationship, and a persistent, high-stakes battle over the fundamental right to bodily autonomy.
The data is clear: while the legal status of abortion has been upended, the demand for reproductive care remains a constant. As we look toward the next chapter of this conflict, the divide between the states that protect access and those that restrict it will continue to define the health and safety of millions of Americans.
About the Author