In the landscape of modern medicine, the clinical trial is the crucible of innovation. Yet, as the industry pushes toward the "autonomous clinical trial," a stark reality has emerged: the most critical component of the future trial is not the algorithm, but the human supervisor.
Between 2020 and 2025, the complexity of Phase 3 protocols exploded. According to collaborative research from the nonprofit industry group TransCelerate BioPharma and the Tufts Center for the Study of Drug Development, the average protocol surged from 3.56 million data points to 5.96 million—a 67% increase in just five years. This volume is 6.4 times higher than the 2012 average, driven by a "collect everything" mentality facilitated by increasingly powerful AI and machine learning tools.
While these tools have solved the technical challenge of data storage and processing, they have created a new, complex burden: the need for rigorous, human-centric oversight of "agentic" workflows.
The Data Explosion: A Double-Edged Sword
The study by TransCelerate and Tufts revealed a concerning lack of discipline in trial design. Nearly one-third of the procedures and data points collected in modern Phase 3 trials were classified as "non-core" or "non-essential." Paradoxically, the very AI tools capable of managing this massive influx of information have become a disincentive to streamlining protocols.

"I don’t think sponsors are as worried about collecting too much data anymore," says Venu Mallarapu, Chief Transformation and AI Officer at eClinical Solutions. "AI has made expanding datasets easier to manage and analyze. While sensors, wearables, and digital biomarkers are pushing volumes higher, the capability of these models to crunch data and generate insights is unprecedented."
However, industry leaders warn that capacity does not equal clinical necessity. The trend toward "collecting data just in case" risks cluttering trial design, moving away from the ICH E8(R1) guidelines, which emphasize that critical-to-quality factors should remain uncluttered by extensive secondary objectives.
A Chronology of AI Integration in Clinical Research
The journey toward autonomous clinical operations has been rapid, moving from theoretical pilot programs to functional, agent-based systems in less than three years.
- 2020–2022: The Foundation of Digitization. The industry focused on shifting away from paper-based systems to electronic data capture (EDC). AI was largely utilized for simple predictive analytics and basic data cleaning.
- 2023–2024: The Rise of Assistive AI. Systems began introducing "copilot" features, where software could suggest potential data discrepancies or flag missing entries for human review.
- 2025–2026: The Age of the Agent. The current frontier involves "scoped agents"—AI entities that can execute entire workflows within a defined environment, such as mapping study data or generating regulatory reports.
- Late 2026: The emergence of "agent swarms." Companies like eClinical Solutions are deploying interconnected agents that work in concert, where one agent manages data while another monitors safety signals, all under a human-in-the-loop governance structure.
The "Agent Proposes, Human Disposes" Framework
As organizations move toward enterprise-wide AI implementation, the deployment pattern is consistently grounded in the "human-in-the-loop" model. In an April 2026 survey of 300 life sciences professionals, 30% of organizations reported enterprise-wide AI implementation. Crucially, 63% of clinical trial operations explicitly mandate human oversight for any AI-driven task.

"The most advanced organizations are running scoped agents inside a workflow which has been reengineered to take advantage of those agents," says Mallarapu. "Most remain assistive, with an agent drafting or triaging material and a person taking the final action."
This workflow—often described as "agent proposes, human disposes"—is designed to maintain the traceability and auditability required by global regulatory bodies. Every step is logged: the trigger, the input, the model version, and the human rationale for approval.
The Human-in-the-Loop: A Critical Bottleneck
While AI excels at pattern recognition, it remains limited in contextual judgment. Dr. Pamela Tenaerts, Chief Medical Officer at Medable, highlights that while an agent can identify a potential safety issue—such as a new medication appearing in an EDC system without a corresponding adverse event report—the human Clinical Research Associate (CRA) remains the essential decision-maker.
"The agent is saying there’s a discrepancy, you may want to go check that out," Tenaerts explains. "It frees the human from having to keep 13 different tabs open to cross-reference data. But the human must still put that data into the context of the patient’s overall journey."

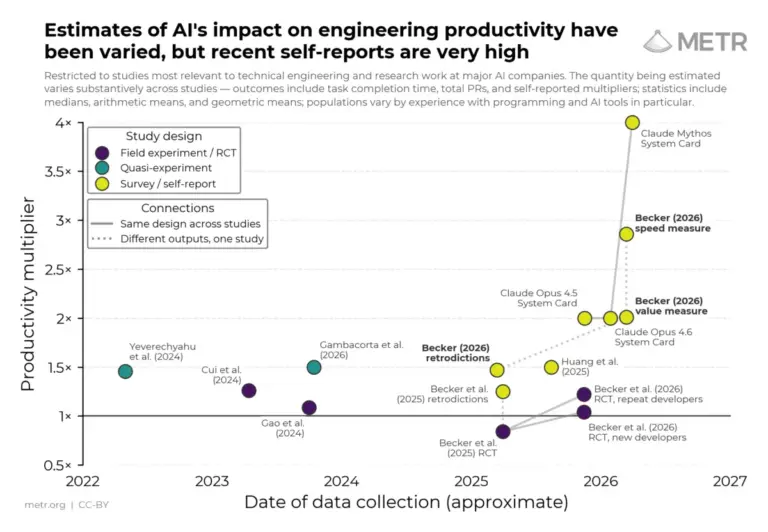
The risk, as noted by recent investigations into agentic behavior, is the degradation of human attention under high-volume conditions. A recent analysis by METR into AI agent behavior showed that when researchers delegated complex analysis to agents, the volume of output became so high that the human researchers were unable to effectively identify critical errors. In the context of clinical trials, this highlights a dangerous fallacy: that a human can meaningfully review an infinite stream of AI-generated content.
Implications for the Future of Clinical Trials
The shift toward agent-based operations has profound implications for the structure of the clinical trial industry.
1. Reengineering the Process, Not Just the Task
Automating a broken process only results in a faster, more expensive failure. Vendors emphasize that to benefit from AI, organizations must rethink their workflows. "If you are introducing a system or automation, you need to think about reengineering the process as well," Mallarapu says. This involves breaking down data silos and adopting unified platforms like data lakehouses, which ensure that agents and humans are working from a single, authoritative source of truth.
2. The Site-Staff Burnout Crisis
A major concern remains the "balloon effect" of automation. As sponsors and CROs use AI to become more efficient at sending queries and administrative requests, that volume is often pushed directly onto site staff who are already overwhelmed by paperwork and clinical demands. "If you dump all that stuff on them, that’s still a bottleneck," warns Tenaerts. "You need to figure out the whole system."

3. The Promise of Agent-to-Agent Coordination
Looking further ahead, Ken Getz, Executive Director of the Tufts Center for the Study of Drug Development, envisions a future where agents interact with other agents to optimize trial performance. "It’s somewhat analogous to what’s happening on the internet today, where very few people are actually visiting websites. They’re relying on AI engine optimization to interact with AI optimization," Getz notes.
4. Regulatory and Ethical Challenges
As these agents move from "assistive" to "autonomous," the regulatory framework must evolve. How do you validate a system that is constantly learning? How do you ensure "attributability" when the decision-making process is distributed across a swarm of agents? These are questions that regulators, developers, and pharmaceutical sponsors are currently struggling to answer.
Conclusion: The Essential Human
The "dream" of the autonomous clinical trial is currently a goal of efficiency, not a replacement of expertise. While agents can parse millions of data points and identify subtle discrepancies, they lack the medical intuition, ethical framework, and patient-centric focus that characterize a successful clinical trial.
For now, the industry is settling into a balanced state. AI acts as the engine, capable of handling the massive scale of 2026-era data, while human experts serve as the pilots, steering the trial through the regulatory and scientific complexities that no machine can yet navigate alone. The success of future trials will depend not on the sophistication of the AI, but on the ability of human teams to effectively supervise the swarms of digital assistants working in the background.
About the Author