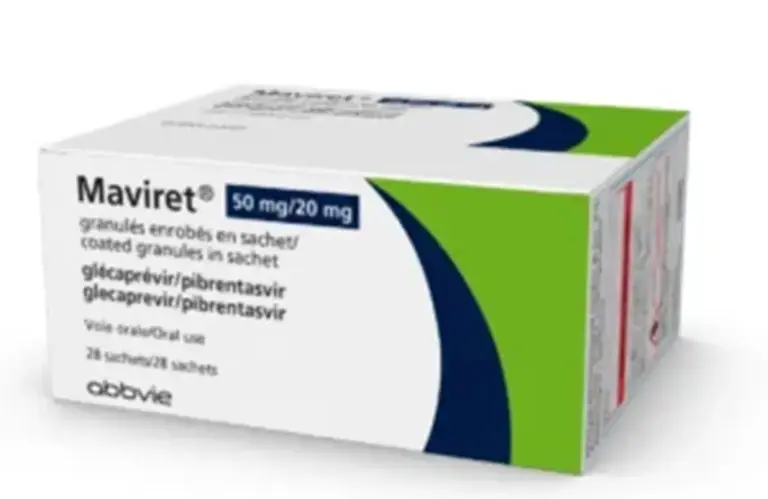
Despite the existence of potent, short-course oral antivirals capable of curing Hepatitis C virus (HCV) in nearly all patients, the disease remains a persistent public health crisis. In 2023 alone, an estimated 69,000 Americans contracted the virus—a figure that effectively doubles the infection rates observed in the mid-2010s. This paradox of high efficacy versus rising incidence has placed a spotlight on AbbVie’s direct-acting antiviral, Maviret (glecaprevir/pibrentasvir).
While clinical trial data boasts a 96% success rate, the transition from controlled study environments to the chaotic, often fragmented reality of patient populations at highest risk of transmission remains the primary hurdle for global elimination efforts.
The Evolution of HCV Treatment: A Chronology
The journey to eradicate Hepatitis C has been characterized by significant medical breakthroughs, yet it has been hampered by administrative and structural inertia.
- 1991: The FDA approves the first alpha interferon injection for HCV. At the time, it was the only option, but it carried a dismal viral eradication rate of approximately 10%, often accompanied by debilitating side effects.
- 2017: A new era begins as the European Union and the U.S. FDA grant approval for Maviret to treat chronic HCV across all major genotypes. The treatment paradigm shifts toward a short, 8-to-12-week oral course.
- June 2025: The U.S. FDA approves a landmark label expansion for Maviret, making it the first and only antiviral cleared specifically for acute Hepatitis C infections.
- June 2026: The European Commission follows suit, granting extended approval for Maviret to treat acute HCV, signaling a global shift toward early intervention.
Efficacy vs. Effectiveness: The Data Breakdown
The clinical efficacy of Maviret is undeniable. In the pivotal Phase 3 clinical trial supporting its acute indication, the drug demonstrated a sustained virologic response (SVR) of 96.2% at 12 weeks in the intention-to-treat population. When excluding non-virologic failures, the success rate climbed to a near-perfect 100%.
Critically, the study found no instances of on-treatment virologic failures or post-treatment relapses. This data is particularly encouraging for patients who have already navigated the system once. Nearly 18% of the study’s participants were undergoing treatment for at least their second HCV infection, and approximately 40% of those individuals had a history of two or more prior infections. In some extreme cases, participants had survived as many as six prior bouts with the virus.
Crucially, the data suggests that prior exposure to the virus—or even prior exposure to the same drug regimen—does not compromise the body’s response to subsequent treatment. “The study found that a history of prior HCV infection did not appear to affect the SVR,” says Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and a co-author of the trial. “These findings suggest that neither prior infection nor previous exposure to the same regimen compromised the virologic response to treatment of the current episode.”
The Administrative and Structural Barrier
For years, the "wait-and-see" approach dominated clinical practice. Patients diagnosed with acute HCV were often required to wait for the infection to transition into a chronic state before insurance providers or health systems would authorize treatment.
"Before the acute indication, patients could be required to wait for confirmation of chronicity, even though current clinical guidelines support treatment as soon as acute infection is diagnosed," explains Dr. Gentile. "That delay can add unnecessary visits, create administrative barriers and, most importantly, increase the risk that patients disengage from care."
By removing the requirement for chronicity, the new FDA and EU labels empower clinicians to act immediately. This shift is not merely about clinical expediency; it is a tactical necessity to keep patients tethered to the healthcare system, thereby reducing the likelihood of community transmission.
The "Hard-to-Reach" Population: A Gap in Evidence
While the clinical data is robust, experts caution that the trial environment differs vastly from the reality of the street. In the Phase 3 trial, only 14.3% of participants were classified as individuals who currently or recently injected drugs. Furthermore, nearly half of the participants were HIV-positive, but all were already stabilized on antiretroviral therapy and fully connected to professional healthcare services.
This suggests that the trial was heavily populated by individuals who were already "in the system." The real-world challenge lies in reaching those who are not. Individuals experiencing homelessness, those with active substance use disorders, and those living in regions with limited infrastructure remain largely absent from these success statistics.
"This study provides strong evidence of antiviral efficacy, but it does not fully answer the question of effectiveness in populations that are least engaged in care," Dr. Gentile admits. The high dropout rates often associated with these populations mean that a drug’s success in a clinic does not guarantee its success in the community.
Integrating Prevention with Treatment
The reality of HCV is that medical treatment does not change the environmental factors—such as access to sterile injecting equipment or sexual health support—that lead to reinfection. For those at high risk, the reinfection rate is estimated at 5.9 per 100 person-years, compared to just 1.27 per 100 person-years in the general population.
"Antiviral treatment does not modify the underlying exposure," notes Dr. Gentile. "Repeated treatment must therefore be integrated into a broader prevention strategy, including harm-reduction services, treatment for substance-use disorders, and regular HCV RNA testing."
There is a growing consensus among public health officials that the perception of reinfection must change. Rather than viewing a patient with multiple infections as a "failed" candidate for therapy, providers are being urged to see them as the most critical targets for intervention. Treating these individuals is the fastest way to break the chain of transmission and protect the broader public health.
The Path Forward: Defining Success
As the medical community looks to the future, the metrics for success must evolve. It is no longer enough to measure SVR in a controlled trial. Instead, researchers and public health departments must track:
- The Diagnosis-to-Treatment Interval: Measuring the time elapsed between the initial diagnosis and the first dose of medication.
- Retention Rates: Tracking the percentage of patients who complete the full course of treatment without being lost to follow-up.
- Retreatment Efficacy: Documenting how quickly and effectively the system responds when a patient presents with a reinfection.
The expansion of Maviret’s label is a significant tool in this broader strategy. By simplifying the path to treatment, it removes a critical administrative hurdle. However, the drug is only one component of a much larger, more complex puzzle.
"Reinfection should not be seen as a reason to delay or even withhold therapy," says Dr. Gentile, "but as a signal that treatment and prevention services need to be delivered together. From an elimination perspective, people with repeated infections may actually be among those for whom rapid treatment has the greatest potential individual and public-health value."
As the world continues to grapple with rising HCV infection rates, the focus must shift from the laboratory to the field. The clinical tools to end the Hepatitis C epidemic are already in our hands; the challenge now lies in ensuring those tools reach the people who need them most, regardless of the complexity of their circumstances. Only through a combination of rapid, barrier-free treatment and robust harm-reduction infrastructure can the 96% success rate seen in trials become a 96% success rate for the population at large.
About the Author