The pharmaceutical industry, long characterized by high capital intensity and protracted development timelines, stands at a critical technological inflection point. As the complexity of clinical protocols continues to skyrocket—with Phase 3 trials now managing an average of 5.9 million data points—the industry is increasingly turning to agentic AI to bridge the gap between massive data accumulation and actionable decision-making.
A groundbreaking new analysis from the Tufts Center for the Study of Drug Development (CSDD) and clinical trial platform provider Medable has finally provided the financial justification for this shift. The study estimates that implementing a specialized Clinical Monitoring Agent could yield an 82x return on investment (ROI) for Phase 3 oncology trials and a 64x return for Phase 2, equating to $21 million and $7.5 million in added Expected Net Present Value (eNPV) per study, respectively.
The Financial Case for Agentic AI
For years, the promise of AI in clinical trials remained largely theoretical, often discussed in the abstract as a "productivity booster." The Tufts-Medable collaboration represents a pivotal departure from vague optimism toward hard-nosed investment modeling.
"We’ve known for some time that companies have been piloting AI enablement tools, but what they’ve often been lacking is any kind of quantification of the actual ROI, the value proposition," said Ken Getz, executive director of the Tufts CSDD. "We were interested in doing a study where we could put some hard numbers around a specific AI enablement solution."
The findings are stark: for sponsors with large-scale oncology portfolios, the cumulative financial impact is staggering. When modeled across 20 active indications, the incremental eNPV reaches approximately $226 million. For larger organizations managing 50 indications, the potential value add scales to $565 million. This isn’t merely about administrative cost-cutting; it is about protecting the value of high-stakes drug development programs that are historically prone to failure.
Chronology: From Pilot Programs to Predictive Models
The integration of AI into clinical workflows has evolved rapidly over the past 24 months.
- Late 2025: Industry sentiment began to shift from general "Generative AI" experimentation to specific "Agentic" workflows. Reports from IBM and McKinsey highlighted that while AI budgets were often exceeded, the productivity gains were material, with developers reporting an average saving of one to two hours per day through agentic assistance.
- Early 2026: A seminal Tufts CSDD analysis revealed that across 36 industry-reported use cases, AI/ML tools contributed to an average 18% reduction in trial cycle time. The most significant gains were observed in patient monitoring and enrollment assessments.
- August 2026: The current Tufts-Medable analysis was released, marking the first time these operational efficiencies were formally translated into the language of finance (eNPV and ROI). This report serves as a benchmark for how modern sponsors should evaluate the "Agentic Operating Model."
The Mechanics of Monitoring: Wrangling Data at Scale
Modern clinical research is defined by the "data explosion." In 2012, a typical Phase 3 protocol required the collection of roughly 929,000 data points. Today, that number has grown six-fold to nearly 6 million.
For a Clinical Research Associate (CRA), this volume is humanly overwhelming. They must synthesize data from Electronic Data Capture (EDC) systems, Clinical Trial Management Systems (CTMS), and Trial Master Files (TMF) to maintain protocol integrity.
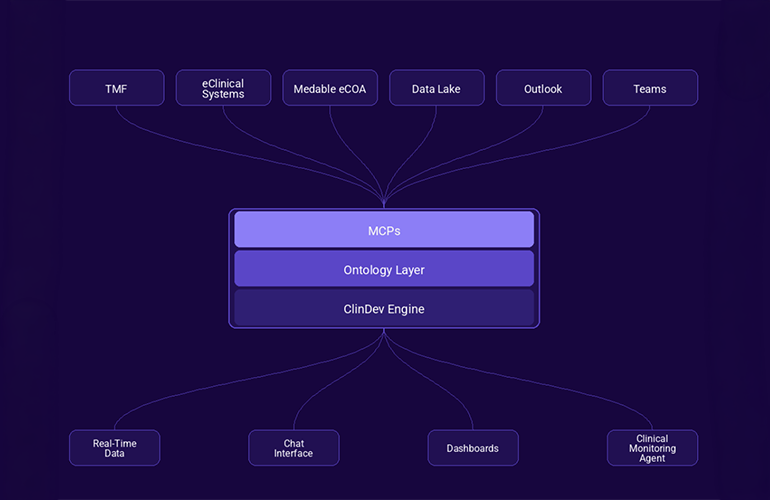
Medable’s approach to this complexity involves a modular architecture. They deploy prebuilt agents that connect to roughly 40 disparate enterprise systems—including Oracle, Veeva, Snowflake, and Databricks. While these agents arrive "pre-trained," Dr. Pamela Tenaerts, Chief Medical Officer at Medable, notes that "a lot of those agents still need about 20% tweaking, because systems are different and it has to be configured to the specific protocol."
In practical operation, these agents act as an "always-on" auditor. In one demonstration, the agent successfully cross-referenced adverse event reports with concomitant medications, flagging a site where an error was occurring in real-time. By spotting patterns—such as a site falling behind on enrollment or a lab value consistently trending toward a protocol deviation—the agent allows the human CRA to intervene days or weeks earlier than they might have through manual review.

Official Perspectives: The Human-in-the-Loop Imperative
While the numbers suggest a paradigm shift, industry leaders are careful to temper expectations regarding full autonomy. The current deployment strategy is rooted in "recommend-and-review" rather than "unattended execution."
Dr. Tenaerts emphasizes that the goal is not to replace the CRA, but to elevate their role. "The agent doesn’t suspend the CRA from thinking," she says. "The CRA still needs to be there to make the high-level judgment calls."
Venu Mallarapu, Chief Transformation and AI Officer at eClinical Solutions, echoes this sentiment, noting that even among the most advanced organizations, agents are used to draft and propose, while humans retain the "acting" authority. "There’s nobody that is running fully autonomous agents that not only process the data but also make decisions without human involvement," Mallarapu explains.
This "human-in-the-loop" requirement is also a matter of system-wide efficiency. If an AI agent speeds up the rate at which queries are generated and sent to clinical sites, there is a secondary risk of overwhelming the site staff. "You push the balloon and it goes somewhere else," Tenaerts cautions. "You need to figure out the whole system."
Implications for Drug Development and Trial Success
The broader implication of this technology is the potential mitigation of the "95% failure rate" that has plagued oncology drug development for decades. With a 43.4% success rate for Phase 3 oncology trials between 2007 and 2023, the industry is desperate for tools that can optimize design mid-stream.

Strategic Decision Support
The primary value of agentic AI may not be the automation of manual tasks, but the support of strategic pivots. As Ken Getz notes, the transition from tactical data wrangling to strategic oversight is the true benefit of the technology:
- Tactical: The agent detects a recurring protocol deviation or a site bottleneck. It alerts the human, who reviews the findings and approves an automated query.
- Strategic: Freed from the mundane, the clinical team can focus on larger questions: Should the trial design be modified? Is an amendment necessary? Does the data suggest the drug is not hitting the desired endpoint effectively?
Future Scalability
While the current analysis focused exclusively on oncology, the framework is highly transferable. The logic applied to oncology—where data density and the necessity for rapid, accurate monitoring are highest—is applicable to any complex therapeutic area. Medable is already signaling that the transition to other disease areas is a matter of configuration rather than invention.
Conclusion: A New Standard for Clinical Ops
The Tufts-Medable study serves as a wake-up call for the biopharmaceutical sector. It moves the conversation regarding AI away from "innovation theater" and toward the bottom line. By demonstrating that agentic AI can generate multi-million dollar value increases through the efficient management of trial data, the study provides a clear roadmap for sponsors.
As the industry moves toward 2027, the competitive advantage will likely belong to those who successfully integrate these agents into their core operating models. The question is no longer whether AI can handle the data, but how quickly organizations can adapt their internal culture and workflows to allow these agents to function effectively. The "balloon" of clinical trial complexity is being pushed; the companies that build the right systems to manage that pressure will be the ones that survive and thrive in an increasingly data-dense research environment.
About the Author