Editorial Note: This article, originally published on July 29, 2026, has been updated to incorporate the latest guidance from the Centers for Medicare & Medicaid Services (CMS) regarding the "medical frailty" exclusion criteria.
As the United States approaches a significant shift in its social safety net, a looming collision between federal policy and administrative reality threatens to leave hundreds of thousands of disabled Americans without health coverage. Under the 2025 reconciliation law, 44 states are mandated to implement work requirements for adults in the Affordable Care Act (ACA) Medicaid expansion group, effective January 1, 2027. While the legislation provides a critical safety valve for those deemed "medically frail," recent federal rulemaking has created a complex, high-stakes bureaucratic hurdle that may inadvertently strip coverage from those who need it most.
The Landscape of Coverage
For millions of low-income Americans, Medicaid serves as a vital bridge, particularly for those waiting to be approved for the Supplemental Security Income (SSI) program. SSI, administered by the Social Security Administration (SSA), provides essential cash assistance to individuals with disabilities who possess limited financial resources. Because the SSI application process is notoriously lengthy—often stretching across months or even years—these individuals frequently rely on Medicaid expansion programs to access life-saving healthcare while their disability claims are adjudicated.
However, the impending work requirements—requiring 80 hours of monthly "community engagement"—threaten to disrupt this delicate balance. Because SSI applicants must demonstrate an inability to engage in "substantial gainful activity" to qualify for benefits, they are inherently ill-equipped to meet the new work requirements. Their only path to retaining coverage is the "medical frailty" exclusion, a designation that is currently defined by a restrictive, two-part test that could prove impossible for many to satisfy within the strict timelines mandated by states.
A Chronology of Bureaucratic Complexity
The road to this potential coverage crisis is paved with administrative friction. The process for establishing disability eligibility is one of the most rigorous and time-consuming tasks in the federal government.
- The Five-Step Hurdle: Applicants under 65 must navigate a rigorous five-step disability determination process. This begins with an assessment of current earnings, followed by a classification of impairments into categories ranging from musculoskeletal disorders to mental health conditions.
- The Data Lag: A major point of contention is the SSA’s reliance on outdated tools. The agency currently uses the Department of Labor’s Dictionary of Occupational Titles, which was last updated in 1991. While the SSA has spent $300 million since 2012 attempting to develop a modernized occupational data system, it remains unimplemented.
- The 2026 Shift: In June 2026, the CMS issued an interim final rule that formally set the stage for state-level work requirements. This rule established the framework for "medical frailty," which requires applicants to document that their health conditions specifically impair their ability to meet the 80-hour work threshold.
- The 2027 Deadline: By January 1, 2027, states must begin enforcing these requirements. This creates a "dual-assessment" trap where an applicant is simultaneously fighting to prove disability to the SSA while scrambling to prove medical frailty to state Medicaid offices, often with vastly different timelines and evidentiary standards.
Supporting Data: The Medicaid-SSI Bridge
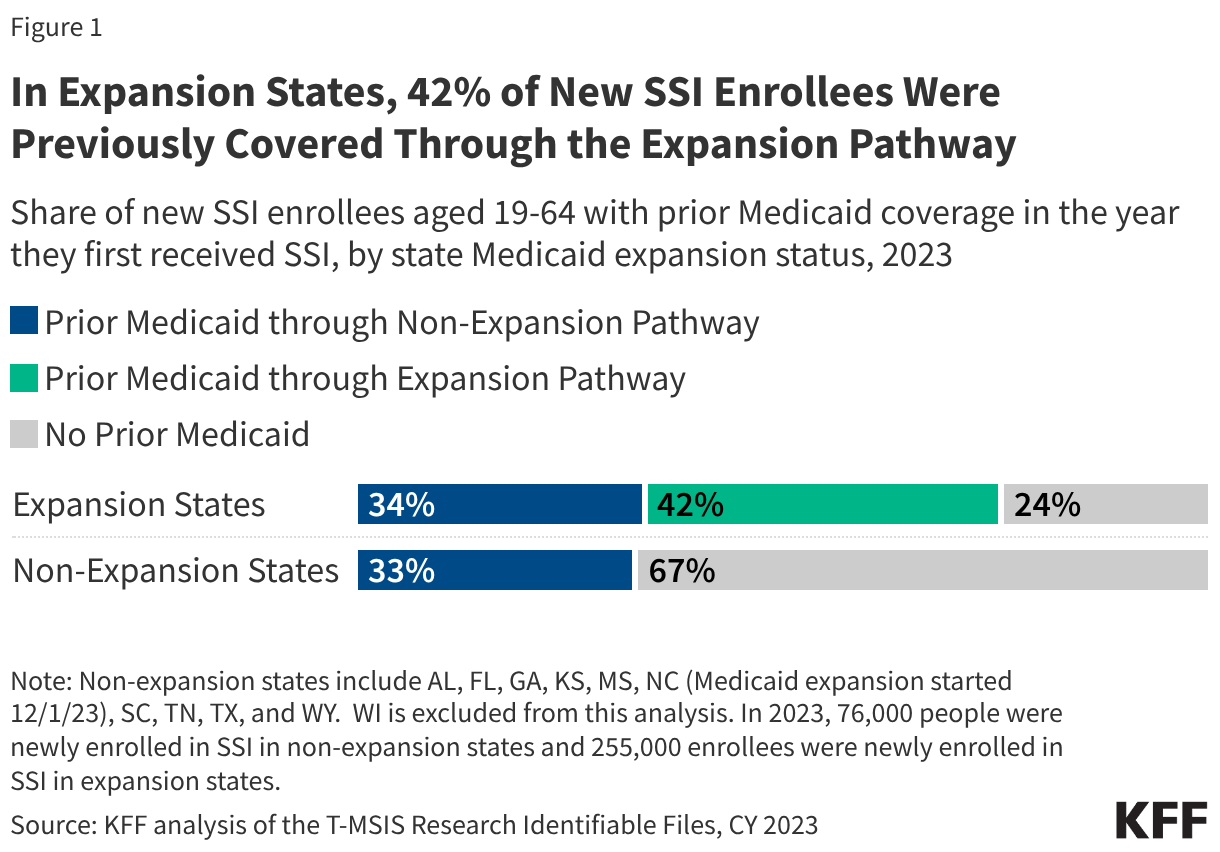
KFF’s analysis of 2023 administrative data underscores just how many people are caught in this transition. In 2023, approximately 337,000 individuals transitioned into the SSI program. Of those, over 200,000 had relied on Medicaid—many through the ACA expansion—prior to their disability approval.
In ACA expansion states, 76% of new SSI enrollees had Medicaid coverage through a different pathway prior to their disability determination. In stark contrast, that figure drops to 33% in non-expansion states. The data suggests that for over 100,000 people, the ACA expansion is the only reason they were insured during the grueling wait for an SSI decision. If these individuals lose their coverage due to an inability to navigate the "medical frailty" documentation requirements, they face a total loss of access to specialists, prescription drugs, and preventive care.
The Role of CMS and the "Tiered" Framework
Recognizing the potential for mass coverage loss, the Centers for Medicare & Medicaid Services (CMS) has released guidance to help states manage the identification of medically frail individuals. This guidance outlines a "tiered" framework designed to reduce the burden on patients:
- Tier 1: States identify medically frail individuals using existing claims data, which is the most efficient and least intrusive method.
- Tier 2: A combination of claims data and encounter data is used to identify those who may have been missed by initial filters.
- Tier 3: An individualized, manual process—the most labor-intensive path—requiring the submission of specific medical records or provider certifications.
While this framework provides a roadmap, it is not mandatory. States retain significant discretion in how they implement these tiers. Furthermore, while self-attestation of medical frailty will be permitted in 2027, the rules tighten in 2028, restricting self-attestation to once per continuous enrollment period. This means that even if a patient successfully gains an exemption in year one, they will face a mandatory, and potentially insurmountable, documentation barrier the following year.
Implications: A System at Risk
The implications of this policy shift are profound. By tying Medicaid eligibility to work requirements while simultaneously utilizing a rigorous and slow federal disability determination process, the government has created a "coverage gap" that threatens the most vulnerable.
Administrative Burden as a Barrier to Care
The primary concern for policy experts is that the "administrative burden" will act as a de facto work requirement. For a person struggling with chronic illness or cognitive impairment, gathering medical records, coordinating between their physician and the state Medicaid office, and meeting strict filing deadlines is a monumental task. The risk is not necessarily that these people are ineligible, but that they are unable to navigate the paperwork required to prove their eligibility.
The "Double Assessment" Problem
Because Medicaid eligibility renewals are moving toward a six-month cycle in many states, and initial application processing must occur within 45 days, the state will likely reach a decision on "medical frailty" long before the SSA reaches a decision on "disability." This forces patients into a defensive position where they must defend their health status in two separate forums, using two different sets of criteria.
The Human Cost
The human cost of these bureaucratic delays is measured in lost care. When a patient loses Medicaid, they often lose access to the very medical providers who would provide the documentation necessary to prove their disability or medical frailty. This creates a vicious cycle: the loss of insurance makes it harder to obtain the evidence needed to regain that insurance.
Conclusion
As the January 2027 deadline approaches, the success of these work requirement policies will hinge on the ability of state agencies to integrate, rather than replicate, the work done by the SSA. If states adopt flexible, data-driven approaches to identifying medical frailty—minimizing the need for individual documentation—they may prevent a catastrophic loss of coverage. However, if the focus remains on rigid, paperwork-heavy verification processes, the nation risks pushing thousands of disabled, low-income citizens out of the health system at the exact moment their needs are greatest.
The challenge ahead is to ensure that in the pursuit of labor participation, the basic promise of the Medicaid program—providing a safety net for those who cannot work due to illness or disability—is not discarded in the process. The coming months will be a critical testing ground for whether federal policy can adapt to the reality of the people it serves.
About the Author