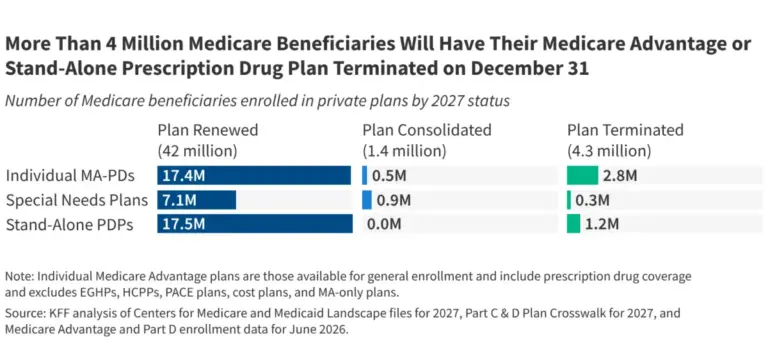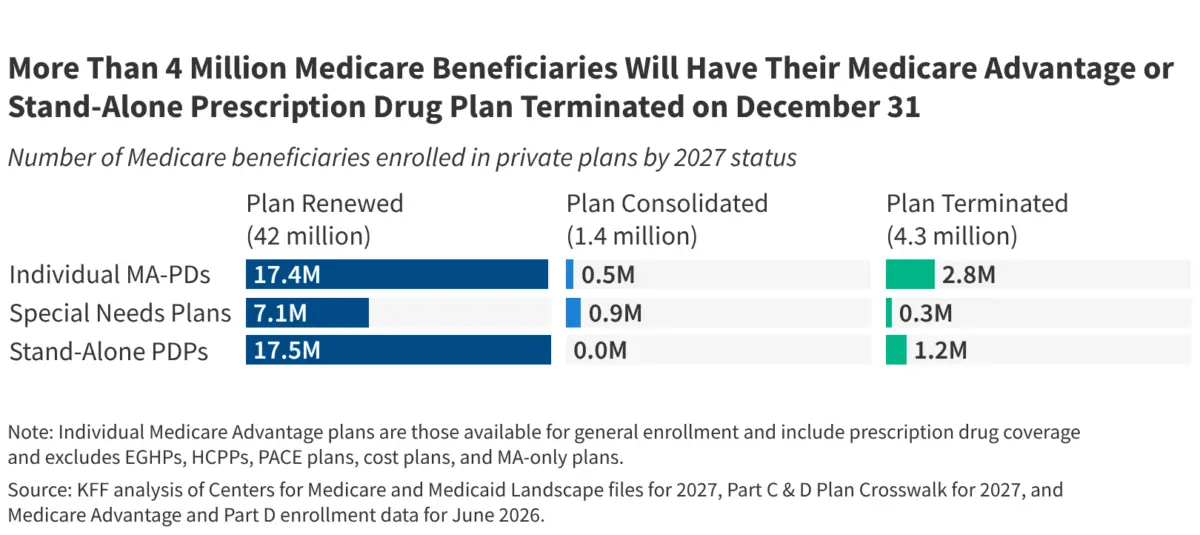
The American healthcare landscape is undergoing a period of profound instability for millions of older adults and individuals with disabilities. As the annual Medicare Open Enrollment period—which commenced on October 15—gets underway, new data from the Centers for Medicare & Medicaid Services (CMS) reveals that 4.3 million Medicare beneficiaries will see their current coverage plans terminated at the end of 2026. This mass disruption includes 3.1 million Medicare Advantage (MA) enrollees and 1.2 million participants in stand-alone prescription drug plans (PDPs), signaling a turbulent transition into the 2027 plan year.
The Core Facts: A Landscape of Disruption
For millions of Americans, the "open enrollment" window is no longer just a time to shop for better deals; it has become a necessary scramble to maintain basic coverage. The impending terminations are not merely administrative adjustments but a direct result of private insurers restructuring their offerings.
Specifically, the data indicates that 3.1 million Medicare Advantage prescription drug (MA-PD) enrollees will lose their plans on December 31, 2026. This group is split between 2.8 million individuals in general enrollment plans and approximately 300,000 enrollees in specialized Medicare Advantage Special Needs Plans (SNPs). Additionally, 1.2 million people enrolled in stand-alone PDPs—the primary drug coverage for those in traditional Medicare—will find their current plans discontinued.
The breadth of these terminations is significant. Roughly 14% of all general enrollment MA-PD participants are affected, a rate that aligns with 2026 levels but remains substantially higher than historical norms. Meanwhile, the disruption in the PDP market has doubled, impacting 6% of enrollees compared to 3% the previous year.
A Chronology of Uncertainty
The road to this mass termination began long before the October enrollment window opened. The industry has been grappling with a series of shifting financial incentives and regulatory decisions that have prompted insurers to re-evaluate their market participation.
- Mid-2026: Market analysts and industry observers began noting a trend of "plan exits" as major insurers faced pressure from rising costs and stricter regulatory oversight.
- Late Summer 2026: The Trump administration made the pivotal decision to conclude the Part D Premium Stabilization Demonstration one year early. This move effectively removed a temporary subsidy that had kept premiums artificially lower for stand-alone drug plans.
- August 2026: Major insurance carriers began publicly announcing their intent to prune their portfolios, withdrawing from specific geographic regions and consolidating redundant plan offerings to protect their profit margins.
- October 15, 2026: The official start of the Medicare Annual Open Enrollment Period. For millions, this date marked the beginning of a mandatory period to search for new coverage to avoid a gap in benefits.
- December 31, 2026: The date by which all terminated plans cease to provide coverage, necessitating that all affected beneficiaries be transitioned to new plans or returned to traditional Medicare.
Data-Driven Insights: Who is Leaving and Why?
The concentration of these terminations is not distributed evenly across the industry. Four major parent organizations are responsible for half of all individual MA-PD terminations. Humana leads the list, accounting for 19% (530,000) of affected enrollees, followed by UnitedHealth Group at 13% (367,000), CVS Health at 9% (254,000), and Aware Integrated, Inc., at 9% (249,000).
In the PDP market, the consolidation is even more localized. The termination of the SilverScript Choice PDP, sponsored by CVS Health, accounts for a staggering 81% (950,000) of all affected PDP enrollees. This massive exit has reduced the average number of PDP options available to beneficiaries from 11 in 2026 to just 9 in 2027.
Beyond outright terminations, another 1.4 million Medicare Advantage enrollees are subject to "plan consolidations." In these cases, the insurer is not exiting the market entirely but is merging a plan into another product line. While this prevents a total loss of coverage, it often forces beneficiaries into different provider networks, changing the drug formulary or the cost-sharing structure they have grown accustomed to.
The Regulatory Response and Strategic Shifts
The primary driver behind the 2027 shift in Special Needs Plans (SNPs) is a new regulatory requirement from CMS. Starting in January 2027, insurers offering both a dual-eligible SNP (D-SNP) and an affiliated Medicaid managed care plan in the same county are generally restricted to offering only one D-SNP for full-benefit dual-eligible individuals.
This rule is designed to simplify the fragmented landscape of dual-eligible coverage. However, the short-term result is a chaotic period of consolidation. Insurers have been forced to reconfigure their entire SNP strategy to comply with the "one plan per county" standard, leading to the massive movement of 900,000 SNP enrollees into different plans.
While CMS maintains that these changes promote long-term efficiency and market stability, critics argue that the burden of navigating these changes falls squarely on the shoulders of the most vulnerable seniors, many of whom have limited capacity to compare dozens of complex plan documents.
Implications for the Beneficiary
The implications for the average Medicare participant are multifaceted, ranging from financial strain to potential loss of access to preferred healthcare providers.
1. The Medigap "Guaranteed Issue" Opportunity
One of the few silver linings for those in terminated Medicare Advantage plans is the activation of "guaranteed issue" rights for Medigap (Medicare Supplement Insurance). Under federal law, those whose Medicare Advantage plans are terminated are protected from medical underwriting. This means they cannot be denied a policy or charged higher premiums due to pre-existing conditions. For many, this is a rare window to pivot from the restrictive networks of private Medicare Advantage plans back to the broader access of traditional Medicare.
2. The Burden of Choice
With the average beneficiary now choosing from 28 MA-PD options and 9 PDP options, the "paradox of choice" is a genuine barrier to care. Many seniors, overwhelmed by the volume of marketing materials and complex cost-sharing tables, may default to the "auto-enrollment" process. However, relying on automatic transitions is fraught with risk; the new plan may not cover the beneficiary’s specific medications, or their primary care physicians may be out-of-network.
3. Financial Volatility
For PDP enrollees, the ending of the Part D Premium Stabilization Demonstration means that even those who stay in their current plans may face sharp premium spikes. Because these plans are being re-bid, the "national average monthly bid amount" has fluctuated, leading to increased volatility in monthly premiums. Beneficiaries who fail to review their options during the open enrollment period risk being locked into a 2027 plan that is significantly more expensive than alternatives.
Conclusion: A System at a Crossroads
The 2027 plan year serves as a stark reminder that Medicare Advantage and Part D plans are private products subject to the whims of corporate strategy and shifting federal subsidies. While the program offers immense flexibility, the 4.3 million people facing plan terminations are experiencing the darker side of this market-based model: the instability of coverage.
As the enrollment period progresses, health advocates, social workers, and financial planners are urging beneficiaries not to assume that their current coverage will remain the same. The "set it and forget it" approach to Medicare is no longer a viable strategy in an era of mass plan exits and consolidations. For those affected, the task is clear: verify plan status, consult the Medicare Plan Finder tool, and prepare for a transition that may require new financial planning and, in some cases, a new relationship with a primary care provider.
The structural changes occurring for 2027 suggest that the era of aggressive, rapid growth for private Medicare plans may be reaching a point of market correction. Whether this leads to a more sustainable system or continues to impose excessive burdens on the aging population remains the central question for the coming year.
About the Author