Despite the existence of highly effective, short-course oral antivirals for over a decade, the landscape of Hepatitis C virus (HCV) infection remains a paradox of modern medicine. In the United States alone, an estimated 69,000 new infections were recorded in 2023—a figure roughly double the incidence rates observed in the mid-2010s. This surge persists even as medical science has refined treatment into an eight- to 12-week regimen that renders the virus virtually extinct in the host.
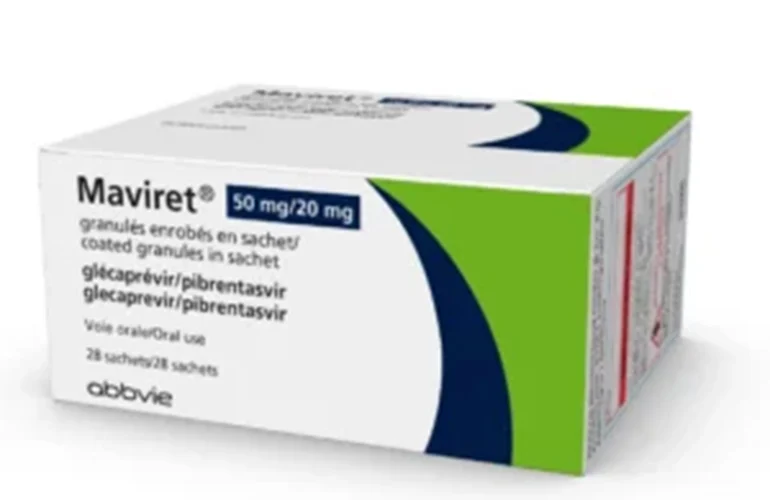
The recent regulatory expansion for AbbVie’s Maviret (glecaprevir/pibrentasvir) to include the treatment of acute HCV infections—cleared by the FDA in June 2025 and the European Commission in June 2026—represents a major clinical milestone. While the drug demonstrated a 96% cure rate in clinical trials, experts warn that moving from the sterile environment of a Phase 3 study to the chaotic reality of public health delivery is the true test of whether this disease can ever be fully eliminated.
The Evolution of HCV Treatment: A Chronology
The journey toward modern HCV management has been marked by a staggering leap in efficacy. For decades, the medical community was limited to alpha interferon injections, which were notoriously difficult for patients to tolerate and yielded viral eradication rates of only about 10%.
The shift toward direct-acting antivirals (DAAs) changed the calculus entirely. The trajectory of AbbVie’s therapeutic progress can be summarized through the following milestones:
- 2017: The European Union and the U.S. FDA grant initial approval for Maviret for the treatment of chronic HCV across all major genotypes (GT 1–6) in as little as eight weeks.
- June 2025: The FDA grants a landmark label expansion for Maviret, making it the first and only treatment specifically cleared for acute HCV infection in the United States.
- June 2026: The European Commission follows suit, authorizing the use of the drug for acute HCV, effectively aligning clinical guidelines with the urgent need to treat patients before the infection transitions to a chronic state.
By removing the requirement for clinicians to wait for confirmation of chronicity—a process that often led to administrative hurdles and patient disengagement—the new indication aims to catch the virus in its tracks, potentially breaking the cycle of transmission in high-risk communities.
Clinical Efficacy vs. Real-World Complexity
The Phase 3 trial data supporting the label expansion was undeniably robust. The study demonstrated a sustained virologic response (SVR) rate of 96.2% at 12 weeks in the intention-to-treat population. In the modified intention-to-treat cohort—which excluded non-virologic failures—the cure rate reached 100%. Perhaps most impressively, there were no reported on-treatment virologic failures or post-treatment relapses.
However, the "real-world" challenge lies in the demographics that were—and were not—represented in these trials.
The Persistence of Reinfection
One of the most significant findings in the recent trial was the resilience of the treatment regimen among patients with a history of prior infection. Approximately 18% of trial participants were being treated for at least their second HCV infection, and nearly 40% of that subset had experienced two or more prior infections. In some extreme cases, participants had been treated for as many as six prior infections.
Data showed that previous exposure to Maviret did not compromise the efficacy of the drug in subsequent episodes. As noted by Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and a co-author of the trial, "The study found that a history of prior HCV infection did not appear to affect the [SVR]. These findings suggest that neither prior infection nor previous exposure to the same regimen compromised the virologic response."
The "Hard-to-Reach" Gap
Despite these positive metrics, researchers are sounding a note of caution. The clinical trial environment is inherently structured: participants are monitored, supported, and connected to care. In the Phase 3 trial, only 14.3% of participants were classified as individuals who currently or recently injected drugs—a population that faces significantly higher reinfection rates. Furthermore, while nearly 50% of the participants were living with HIV, all were already receiving antiretroviral therapy, ensuring they were well-integrated into the healthcare system.
"This study provides strong evidence of antiviral efficacy, but it does not fully answer the question of effectiveness in populations that are least engaged in care," Gentile remarked.
The Public Health Imperative
The data underscores a sobering reality: medical treatment alone is not a panacea for a disease rooted in social and structural inequities. A systematic review of 36 studies revealed that among people who use drugs, the reinfection rate is approximately 5.9 per 100 person-years, compared to just 1.27 per 100 person-years in the general population.
Integrating Prevention and Care
Experts argue that treatment must be part of a comprehensive "wrap-around" service model. This includes:
- Harm-Reduction Services: Increasing access to sterile injecting equipment and safe consumption sites.
- Substance-Use Disorder Treatment: Addressing the underlying behavioral factors that may increase risk.
- Rapid Retreatment: Shifting the perspective of clinicians to view reinfection not as a failure of the patient, but as a sentinel event that necessitates immediate, low-barrier re-intervention.
"Antiviral treatment does not modify the underlying exposure," Dr. Gentile noted. "Reinfection should not be seen as a reason to delay or even withhold therapy, but as a signal that treatment and prevention services need to be delivered together."
Implications for Global Elimination Goals
The expansion of Maviret’s label is a victory for clinical medicine, providing doctors with the regulatory green light to act decisively. However, the path to global HCV elimination remains blocked by the "last mile" problem—reaching the populations that are disconnected from the traditional medical infrastructure.
Moving forward, the focus of the medical community must pivot from drug discovery to delivery innovation. Future studies must prioritize metrics that go beyond simple SVR rates. Researchers are calling for more granular data on the proportion of diagnosed patients who actually begin treatment, the average time elapsed between diagnosis and the first dose, and, crucially, the rate of successful retreatment after reinfection.
The Way Forward
The inclusion of acute HCV in the clinical label is a pragmatic step. It eliminates the "waiting game" that previously characterized HCV care, where patients were often forced to remain in a state of viral limbo while clinicians verified chronic status. By allowing for immediate intervention, the medical system can now treat the virus at the moment of discovery, effectively turning every diagnostic test into a therapeutic opportunity.
However, as the Coalition for Global Hepatitis Elimination suggests, the true potential of these antivirals will only be realized when the healthcare system is as efficient at reaching marginalized populations as it is at manufacturing the drugs themselves. The science is settled; the medicine works. The question now is whether the public health infrastructure can keep pace with the clinical innovation that promises to end the Hepatitis C epidemic.
Ultimately, the fight against HCV is no longer just a quest for a better molecule—it is a logistical and sociological challenge. If healthcare systems can adopt a "no-barrier" approach that treats reinfection as a routine part of public health maintenance rather than a clinical disappointment, the 96% cure rate observed in the lab may finally become the standard for society at large.
About the Author