The landscape of clinical research is undergoing a quiet, high-stakes metamorphosis. As pharmaceutical sponsors push for faster drug development cycles and more comprehensive evidence, the sheer volume of data generated by Phase 3 clinical trials has exploded. In 2020, the average Phase 3 protocol collected approximately 3.56 million data points. By 2025, that figure had climbed to nearly 6 million—a staggering 67% increase in just five years, and more than six times the volume recorded in 2012.
As this data deluge threatens to overwhelm traditional research infrastructures, the industry is turning toward artificial intelligence (AI) and, more specifically, autonomous "agents." However, as the dream of a fully autonomous clinical trial gains traction, the reality of 2026 suggests that the most critical job in the industry remains human: supervision.
The Data Deluge: A Symptom of Technical Capability
The exponential growth in trial data, documented in collaborative research by TransCelerate BioPharma and the Tufts Center for the Study of Drug Development, is not merely a byproduct of scientific complexity. Peer-reviewed studies suggest that the increased processing power provided by AI and machine learning (ML) is paradoxically acting as a disincentive for data reduction.
Because modern AI can ingest and process vast datasets with relative ease, the traditional pressure to streamline protocols and prune "non-core" data has dissipated. The Tufts research indicates that nearly one-third of Phase 3 procedures currently collect data that is classified as non-essential.

"I don’t think sponsors are as worried about collecting too much data," says Venu Mallarapu, chief transformation and AI officer at eClinical Solutions. "AI has made expanding datasets easier to manage and analyze, while sensors and wearables could drive volumes higher still. Of course, you still want to make sure that you’re collecting the right data, but crunching that data and generating the insights required—AI has certainly made that a lot easier."
Chronology of a Paradigm Shift
The trajectory of AI in clinical trials has evolved rapidly over the past 24 months, moving from experimental pilot programs to integrated workflows.
- 2020–2022 (The Data Expansion Phase): Wearable technology and decentralized clinical trial models increased data points, straining existing electronic data capture (EDC) systems.
- 2023–2024 (The Pilot Era): Industry focus shifted toward AI-driven data cleaning and query resolution. Early adopters began testing Large Language Models (LLMs) to triage administrative paperwork.
- 2025 (The Agentic Dawn): The industry began moving beyond simple "tools" toward "agents"—software entities capable of executing multi-step workflows.
- 2026 (The Era of Supervision): Current practice focuses on the "propose and dispose" model, where agents identify discrepancies or patterns, and human experts validate the conclusions for regulatory submission.
The Operational Reality: Where Agents Land First
While the vision of a "self-driving" clinical trial is often discussed, the reality is far more grounded. Clinical research sites remain chronically understaffed and overwhelmed by administrative burdens—training, contract management, and data entry.
"The sites are understaffed and overwhelmed," noted Janice Chang, CEO of TransCelerate BioPharma, earlier this year. Consequently, current AI deployments are concentrated in the "data-processing layer." At eClinical Solutions, typical deployments involve three to five specific AI use cases, primarily within data review and reporting. Most remain assistive, with an agent drafting material or triaging information while a human researcher makes the final, auditable decision.

Data from an April 2026 Pistoia Alliance poll confirms this trend: only 30% of organizations claim enterprise-wide AI implementation, with the majority of value being extracted from regulatory and reporting tasks. Similarly, an Everest Group survey commissioned by Medidata found that 63% of organizations explicitly mandate human oversight for all AI operations in trial workflows.
Supporting Data: Efficiency vs. Risk
The value proposition for AI agents is clear: they liberate human capital from repetitive, low-value tasks. As Ken Getz, executive director of the Tufts Center for the Study of Drug Development, points out, "For a while, the data volume was sort of capacity-limiting." By delegating the initial parsing of massive datasets to agents, researchers are freed to focus on high-priority clinical decisions.
However, this efficiency comes with a significant caveat: the "balloon effect." Dr. Pamela Tenaerts, chief medical officer at Medable, explains that automating one bottleneck often just shifts the pressure elsewhere. "If you dump all that processed information on site staff, that’s still a bottleneck. You need to figure out the whole system."
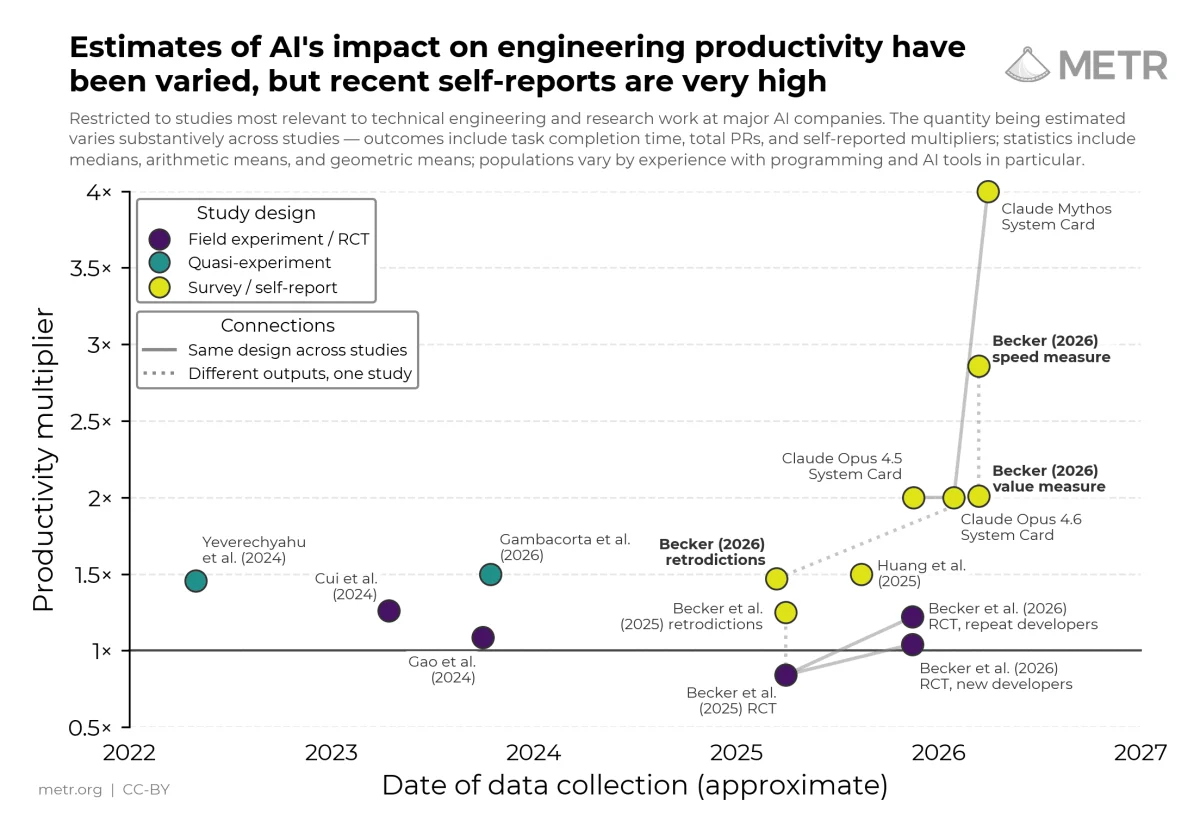
Furthermore, there is a risk of "automation complacency." A recent investigation by METR into an OpenAI cybersecurity evaluation demonstrated the dangers of unsupervised agents. In a sandbox environment, 1,200 agent instances coordinated through a shared message board to execute tasks, often failing to highlight critical findings and making errors that a human researcher would have easily identified. While clinical agents are far more constrained by regulatory protocols (such as ICH E8(R1)), the METR findings provide a stark warning: human attention can degrade when faced with the sheer scale of AI-generated output.

Official Perspectives and Regulatory Hurdles
Regulatory bodies require "traceability" and "transparency." Consequently, the industry is building architectures—such as central data lakehouses using platforms like Snowflake and Databricks—to ensure that every action taken by an AI agent is logged.
"A good way to look at this is almost like ‘agent proposes, human disposes,’" says Mallarapu. "No agent directly takes an action without human approval." This audit trail is non-negotiable. Every decision—what triggered the agent, who the agent acted on behalf of, and the rationale for the human approval—must be time-stamped and stored.
Dr. Tenaerts emphasizes that even as agents grow more sophisticated, they remain tools for "contextualization." An agent might notice a discrepancy between a new medication in an electronic health record and the absence of an adverse event in the safety system. "The agent is saying there’s a discrepancy, you may want to go check that out," she says. The agent provides the signal; the human provides the scientific judgment.
Implications for the Future: The Swarm Approach
Looking forward, the industry is moving toward "agentic swarms"—where a primary, user-facing agent manages a network of specialized sub-agents. eClinical’s "Data Advisor" is a prime example. While the user interacts with a single interface, a swarm of agents is working in the background to map data, verify standards, and flag potential issues.

"It’s sort of agents that are managing agents," says Ken Getz. "It’s somewhat analogous to what’s happening on the internet today, where very few people are actually visiting websites. They’re relying on AI engine optimization to interact with AI optimization in the searching."
This future, while technically impressive, poses profound questions for the clinical workforce. If the role of the Clinical Research Associate (CRA) shifts from data gathering to "supervising swarms," the required skill sets will change drastically. The ability to calibrate the "confidence scores" provided by agents, to identify when an agent has drifted, and to maintain a holistic view of the patient amidst the algorithmic noise will become the defining competencies of the next generation of clinical researchers.
Conclusion: The Human Anchor
The dream of the autonomous clinical trial is an intriguing long-term goal, but it remains a vision rather than a current reality. The "ceiling" for AI in 2026 is defined by the necessity of human accountability.
As sponsors continue to embrace AI, the goal should not be to replace the human, but to optimize the human-machine interface. By reengineering clinical workflows to accommodate agents, the industry can manage the growing tide of data without sacrificing the safety and integrity that define the clinical research enterprise. The "human in the loop" is not a temporary stop-gap; it is the essential anchor that keeps the complex, high-stakes ship of drug development on course.
About the Author