Editorial Note
Originally published on July 29, 2026, this brief has been updated to reflect newer guidance on the medical frailty exclusion from the Centers for Medicare & Medicaid Services (CMS).
Introduction: A Collision of Policies
As of January 1, 2027, the landscape of American public health coverage is undergoing a seismic shift. Under the 2025 reconciliation law, 44 states are now mandated to tie Medicaid eligibility for adults—specifically those in the Affordable Care Act (ACA) expansion group and certain waiver programs—to stringent work requirements. While the legislation includes specific protections for vulnerable populations, including those deemed "medically frail," recent regulatory developments have sparked intense debate.
The core conflict lies in the friction between these new, time-sensitive work requirements and the notoriously slow, bureaucratic process of applying for Supplemental Security Income (SSI). For the hundreds of thousands of Americans who rely on Medicaid as a bridge while waiting for their disability status to be confirmed, these new mandates threaten to dismantle a vital safety net, potentially leaving some of the nation’s most vulnerable citizens without health coverage at their moment of greatest need.
The Chronology of Coverage: How SSI Applicants Fall Through the Cracks
The Supplemental Security Income (SSI) program is a federal lifeline administered by the Social Security Administration (SSA). It provides monthly cash assistance to individuals with limited resources who are unable to engage in "substantial gainful activity" due to a disability. Crucially, in many states, approval for SSI acts as an automatic gateway to Medicaid.
However, the path to SSI approval is a marathon, not a sprint. The application process frequently spans months or even years. During this interim period, many applicants are medically unable to work but have not yet received an official disability designation from the federal government. For those living in ACA expansion states, Medicaid has historically served as the bridge, providing essential coverage during this limbo.
The new mandate, however, creates a collision course. While the law provides an exemption for those who are "medically frail," the June 2026 interim final rule issued by the Centers for Medicare & Medicaid Services (CMS) establishes a rigorous, multi-tiered verification process. Because states are required to process Medicaid renewals for expansion enrollees every six months, many SSI applicants will face an assessment of their "work readiness" long before the SSA completes its exhaustive disability determination.
Supporting Data: The Scale of the Crisis
The reliance on Medicaid during the SSI application period is statistically significant. According to a recent KFF analysis of 2023 administrative data, approximately 337,000 individuals transitioned into SSI eligibility during that calendar year. Of these, over 200,000 had already been enrolled in Medicaid through a different pathway, with more than half of that group—roughly 106,000 people—relying specifically on the ACA expansion.
The geographic disparity is equally striking. In states that expanded Medicaid, 76% of new SSI enrollees between the ages of 19 and 64 had prior Medicaid coverage. In non-expansion states, that figure drops to just 33%.
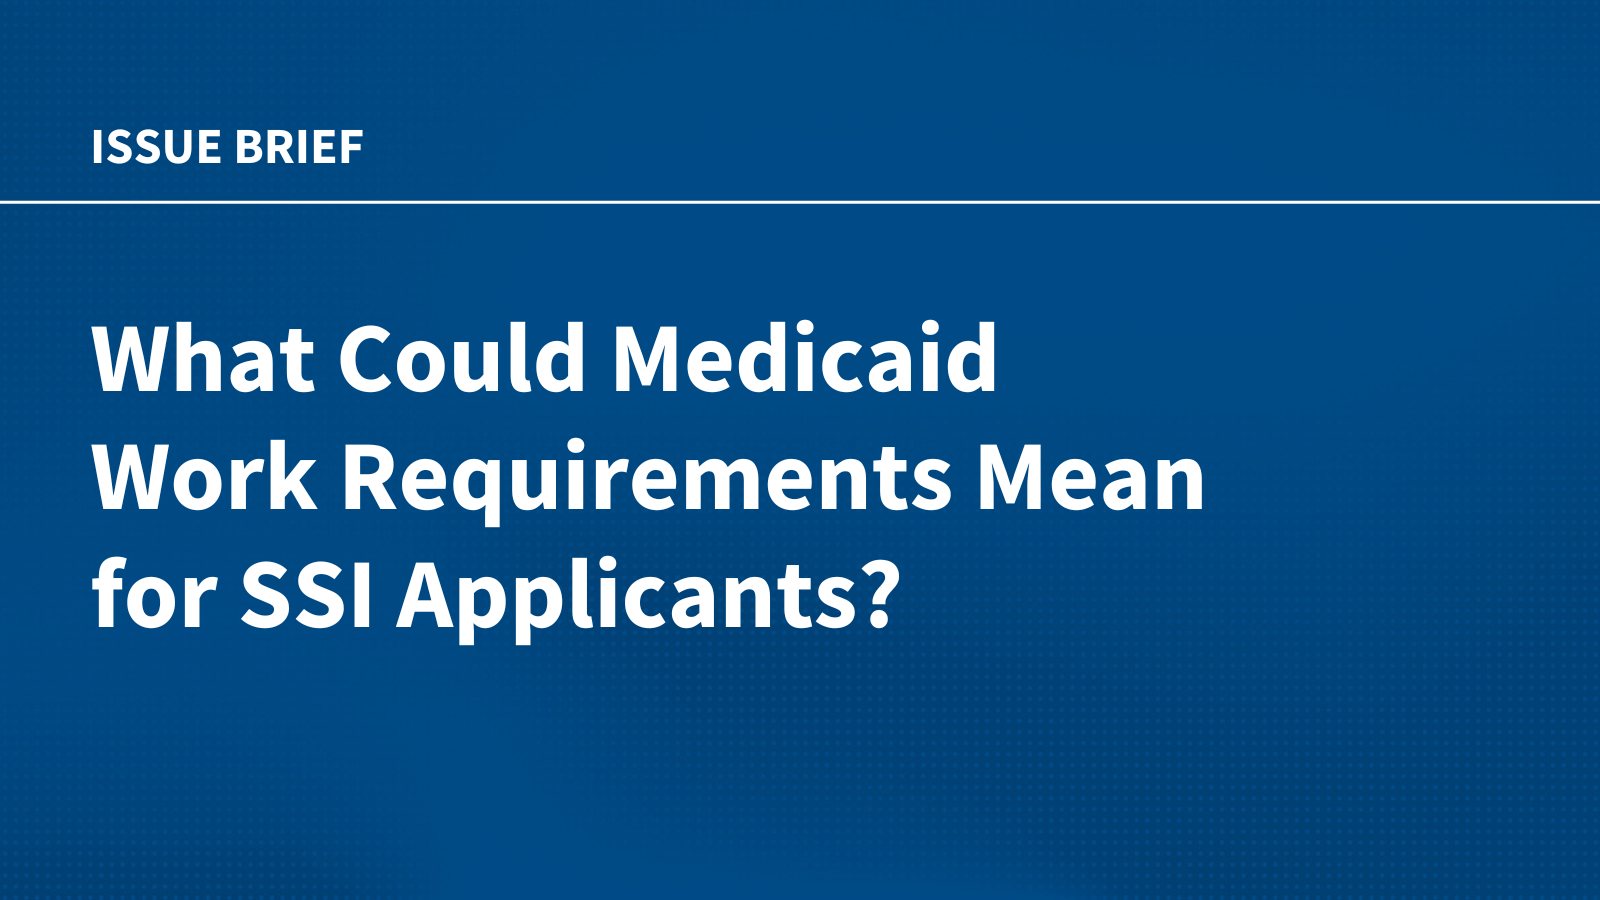
The data highlights a clear reality: the ACA expansion has become the primary mechanism by which the U.S. health system supports people with disabilities who are currently stuck in the federal disability determination "waiting room." Without this coverage, these individuals—who by definition have limited income and restricted physical or mental capacity—would likely remain uninsured, exacerbating their health conditions and increasing long-term costs to the public system.
The Anatomy of the Disability Determination Process
To understand the burden placed on these applicants, one must look at the five-step process required by the SSA to prove a disability:
- Substantial Gainful Activity (SGA): The applicant must prove they are earning less than $1,690 per month (as of 2026).
- Severity Assessment: The SSA evaluates whether the individual suffers from a "severe impairment" across specific body systems (e.g., neurological, cardiovascular, or mental health disorders).
- The "Blue Book" and Compassionate Allowances: Some conditions qualify automatically or through the "compassionate allowance program," which fast-tracks applicants with terminal or degenerative conditions like ALS.
- Past Relevant Work: The agency evaluates the applicant’s ability to perform work they have done in the last 15 years.
- National Economy Assessment: The final hurdle involves determining if the applicant can perform any job in the national economy, factoring in age, education, and residual functional capacity.
The process is hindered by the use of the Department of Labor’s Dictionary of Occupational Titles, which has not been updated since 1991. Despite the SSA investing $300 million since 2012 in developing a modern replacement, the agency still relies on obsolete data, making the determination process both lengthy and frequently disconnected from the modern labor market. As of May 2026, the average processing time for an initial application was 184 days, with 862,000 people currently in the queue.
Official Responses and Regulatory Guidance
Recognizing the potential for mass coverage loss, CMS has attempted to mitigate the impact through a "tiered medical frailty framework." This framework encourages states to use existing claims data to identify medically frail individuals, thereby automating the exemption process for those with documented chronic health needs.
Under this guidance:
- Tier 1: States identify frailty using existing claims data (the most efficient method).
- Tier 2: A combination of claims data and encounter data.
- Tier 3: An individualized, manual process for those with insufficient data on file.
While this tiered approach is intended to reduce the administrative burden, it remains at the discretion of the states. Furthermore, the rule creates a "documentation cliff." While self-attestation will be permitted in 2027 to help bridge the gap, starting in 2028, this will only be allowed once per continuous enrollment period. Consequently, states will be required to demand formal medical documentation at every renewal cycle, placing the burden of proof squarely on individuals who may struggle to navigate complex healthcare systems.
Implications: The Risk of Uninsurance
The implications of these conflicting requirements are profound. By imposing strict work requirements on individuals who are actively seeking federal disability status, the government is essentially asking people to prove they are "too disabled to work" for the SSA, while simultaneously proving they are "able to work" (or "medically exempt") for Medicaid.
The lack of alignment between these two federal processes creates three distinct risks:
1. Administrative Churn
The six-month renewal cycle for Medicaid expansion enrollees is significantly shorter than the average time to receive an initial SSI determination. This misalignment ensures that many applicants will be forced to re-verify their "medically frail" status while their SSI claim is still pending. Even a minor clerical error or a delayed medical record could result in a lapse in coverage.
2. The Cost of Being Uninsured
For an individual with a disability, a gap in Medicaid coverage is rarely just a lapse in paperwork; it is a lapse in treatment. Interruptions in care can lead to the worsening of chronic conditions, increased reliance on emergency rooms, and a total disruption of the very medical history needed to win an SSI appeal.
3. The "Double-Assessment" Burden
Perhaps most concerning is the requirement for concurrent, yet non-harmonized, assessments. An applicant may be required to undergo a consultative medical examination for the SSA while simultaneously securing documentation for their state’s Medicaid work exemption. For individuals with cognitive or severe physical disabilities, this dual-track bureaucratic burden is often insurmountable without significant legal or case-management support—resources that are rarely available to those in poverty.
Conclusion: A System in Need of Synchronization
The 2025 reconciliation law aims to encourage workforce participation, but its application to those waiting for disability benefits reflects a lack of synchronization between federal agencies. If the goal of the Medicaid expansion was to provide a stable floor for the most vulnerable, the current implementation of work requirements threatens to turn that floor into a trapdoor.
To protect the health of these individuals, policymakers must prioritize the seamless integration of SSI and Medicaid data. If a person is deemed "potentially eligible" for SSI by the SSA, they should be categorically excluded from work requirements until a final determination is reached. Without such common-sense integration, the nation risks thousands of citizens losing access to the essential care they need to maintain the very health required to eventually participate in the workforce.
As the calendar turns toward 2027, the focus must shift from administrative enforcement to the protection of those who are, by all definitions of the federal government, unable to participate in the labor market.
Methods Note
This analysis utilized data from the 2023 Transformed Medicaid Statistical Information System (T-MSIS) Analytic Files (TAF) Research Identifiable Files (RIF). National estimates cover 49 states and the District of Columbia. Data for Wisconsin were excluded due to unique 1115 waiver structures that complicate the identification of expansion-equivalent enrollees. All identified "new SSI enrollees" were analyzed based on their monthly eligibility codes and their status in the months preceding their SSI entitlement.
About the Author