For over 70 million Americans, Medicare serves as the essential cornerstone of healthcare security. Designed to support those aged 65 and older, as well as younger individuals living with long-term disabilities, the program is a complex ecosystem of federal insurance and private-market alternatives. However, as the 2026 fiscal landscape settles, beneficiaries are finding that the cost of maintaining this coverage is becoming increasingly burdensome. With premiums, deductibles, and cost-sharing requirements on a steady upward trajectory, understanding the financial architecture of Medicare has never been more critical for the aging population.
Main Facts: The Economic Reality of Medicare Enrollment
The financial health of the average Medicare beneficiary is under significant pressure. Recent data indicates that the fiscal commitment required to maintain coverage is disproportionate to the income levels of many enrollees. In 2024, one in four Medicare beneficiaries subsisted on annual incomes below $24,600. When these modest earnings are weighed against the reality that out-of-pocket costs for premiums and medical services consumed more than 36% of the average beneficiary’s Social Security income in 2023, the vulnerability of this demographic becomes clear.
Beneficiaries today face a bifurcated path: they may opt for Traditional Medicare, typically supplemented by a stand-alone Part D prescription drug plan and a private Medigap policy, or they may choose Medicare Advantage (MA), a privately administered alternative that often bundles medical and drug coverage. While Medicare Advantage plans offer annual out-of-pocket limits—a feature notably absent in Traditional Medicare—they frequently impose stricter provider networks and utilization management tools like prior authorization.
Chronology and Evolution of Medicare Costs
The structure of Medicare has evolved significantly over the last decade, transitioning from a straightforward government-run insurance model to a hybrid system where private plans play a dominant role.
- Initial Enrollment Period: This remains the critical window for all new beneficiaries. Failure to sign up for Part A or Part B during this initial window, without qualifying employer-based coverage, triggers lifetime late-enrollment penalties.
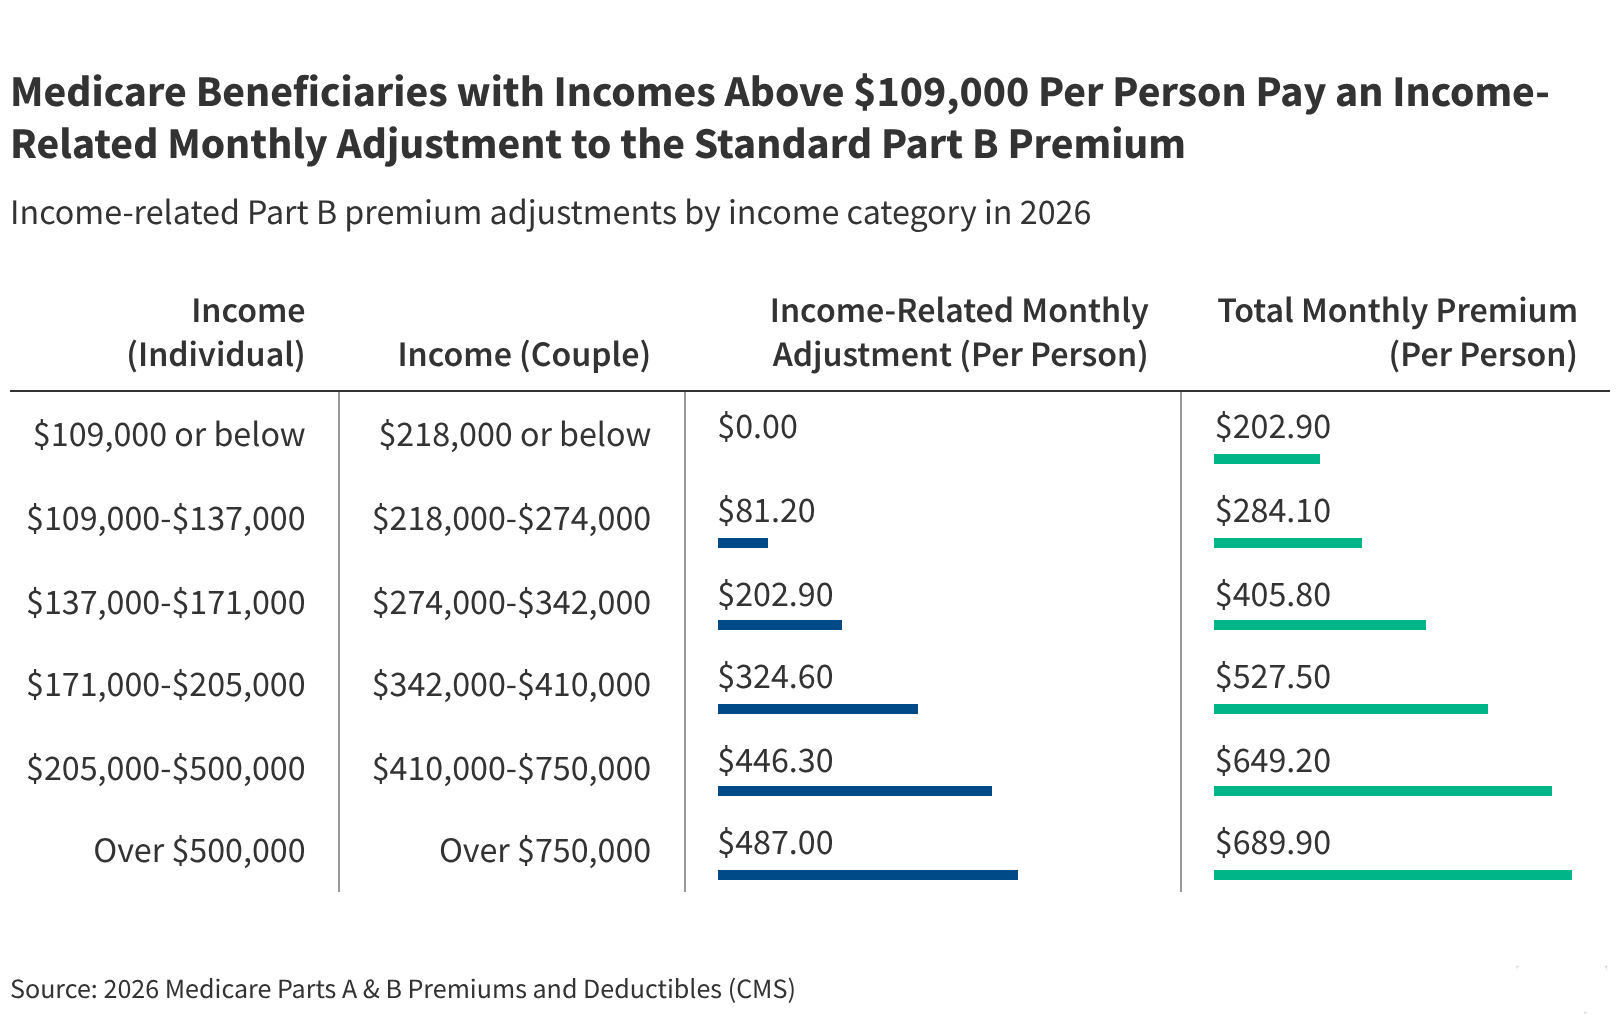
- The 2026 Shift: As of 2026, the standard Part B premium has been set at $202.90 per month, though this figure scales significantly for high-income earners.
- The Introduction of the Part D Cap: Perhaps the most significant change in recent years is the solidification of the $2,100 annual out-of-pocket cap for prescription drugs under Part D, providing a much-needed ceiling for those with chronic, high-cost medication needs.
Supporting Data: Breaking Down the Expenses
Part A and Part B: The Foundation
Most beneficiaries qualify for premium-free Part A coverage, provided they or their spouse paid into the system through payroll taxes for at least 40 quarters. For those who do not meet this threshold, the cost is substantial: $311 per month for those with 30–39 quarters of work history, and $565 per month for those with fewer than 30.
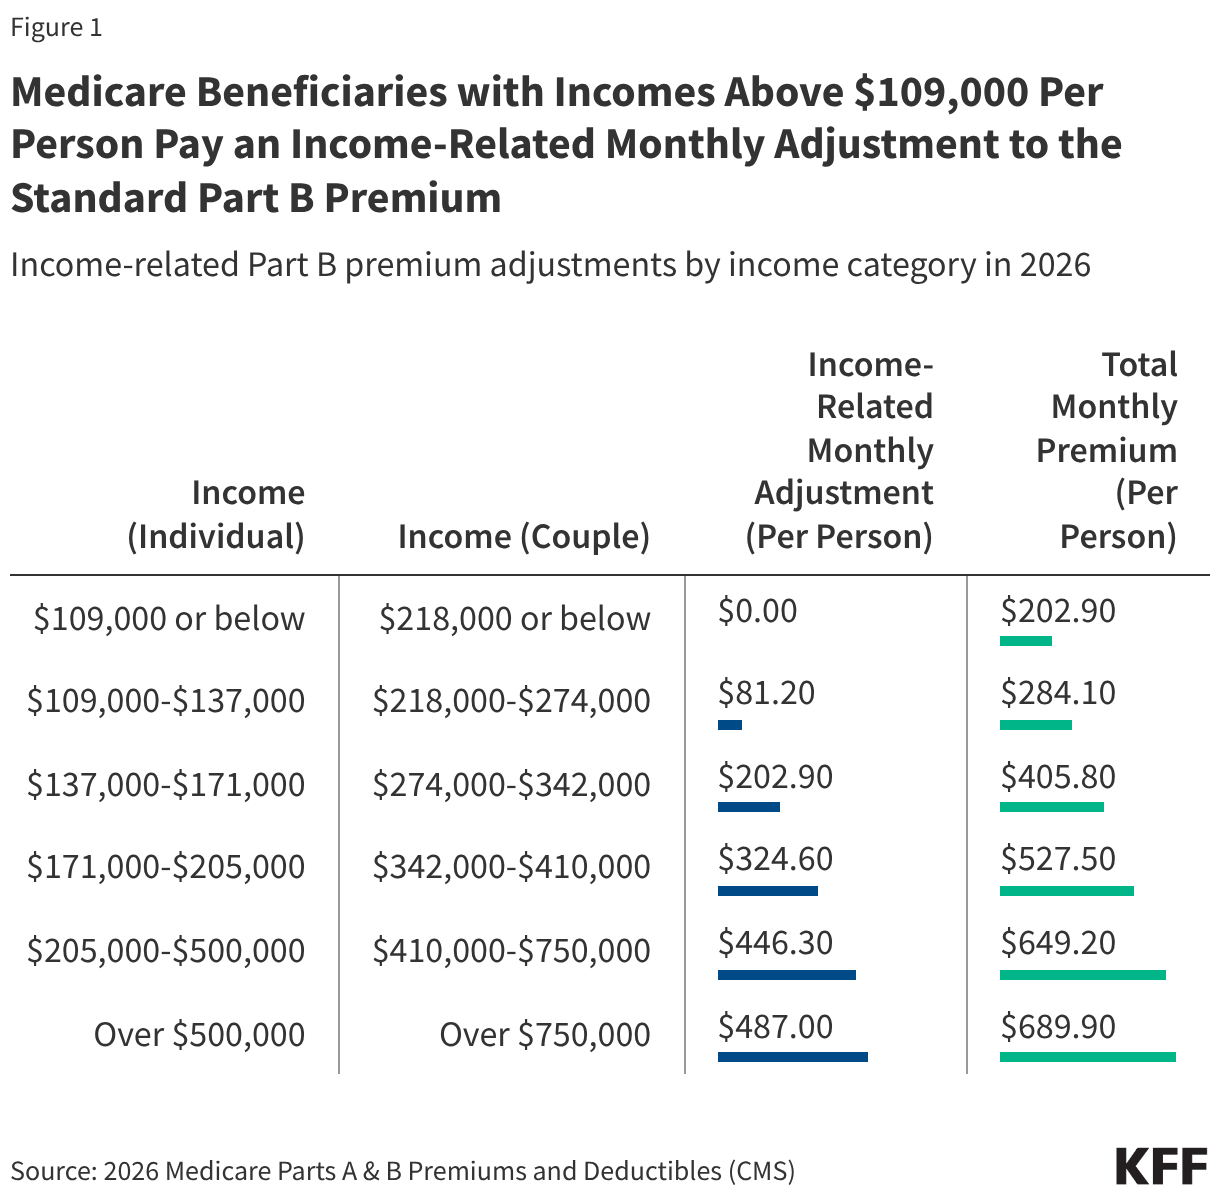
Part B remains a mandatory monthly expense for virtually all enrollees. The standard premium is $202.90, but the "Income-Related Monthly Adjustment Amount" (IRMAA) ensures that higher-income individuals pay significantly more, with monthly premiums scaling as high as $689.90 for the wealthiest cohorts.
Traditional Medicare vs. Medicare Advantage
In Traditional Medicare, the financial risk is largely uncapped. The 2026 Part A hospital deductible is $1,736 per benefit period, and beneficiaries are subject to a 20% coinsurance for most Part B services after a $283 annual deductible. Because there is no ceiling on these costs, many seek Medigap coverage—at an average cost of $217 per month—to prevent catastrophic financial loss.
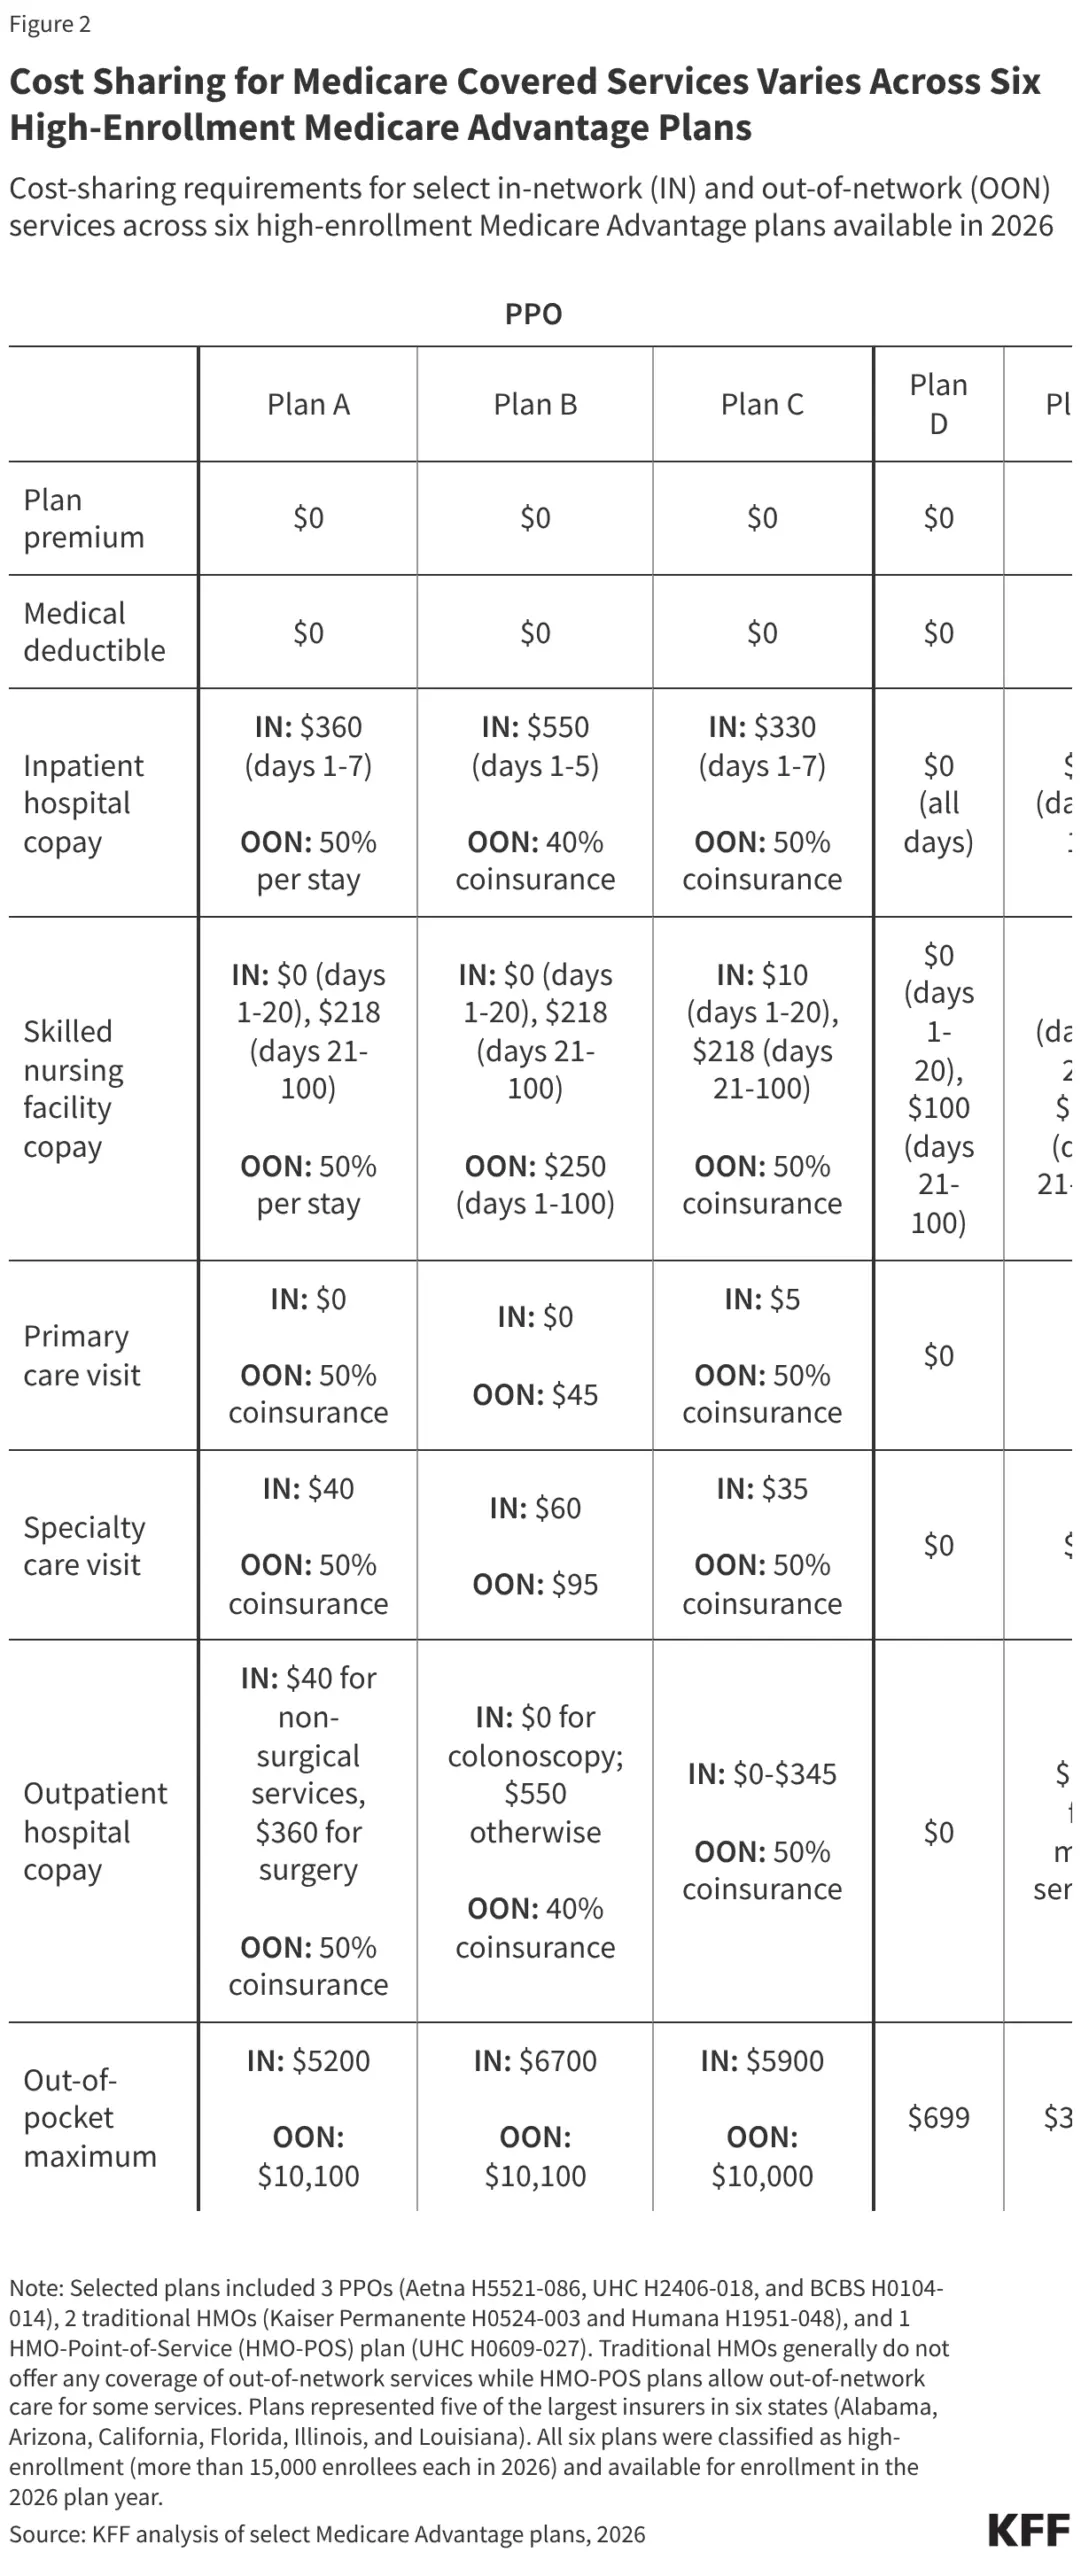
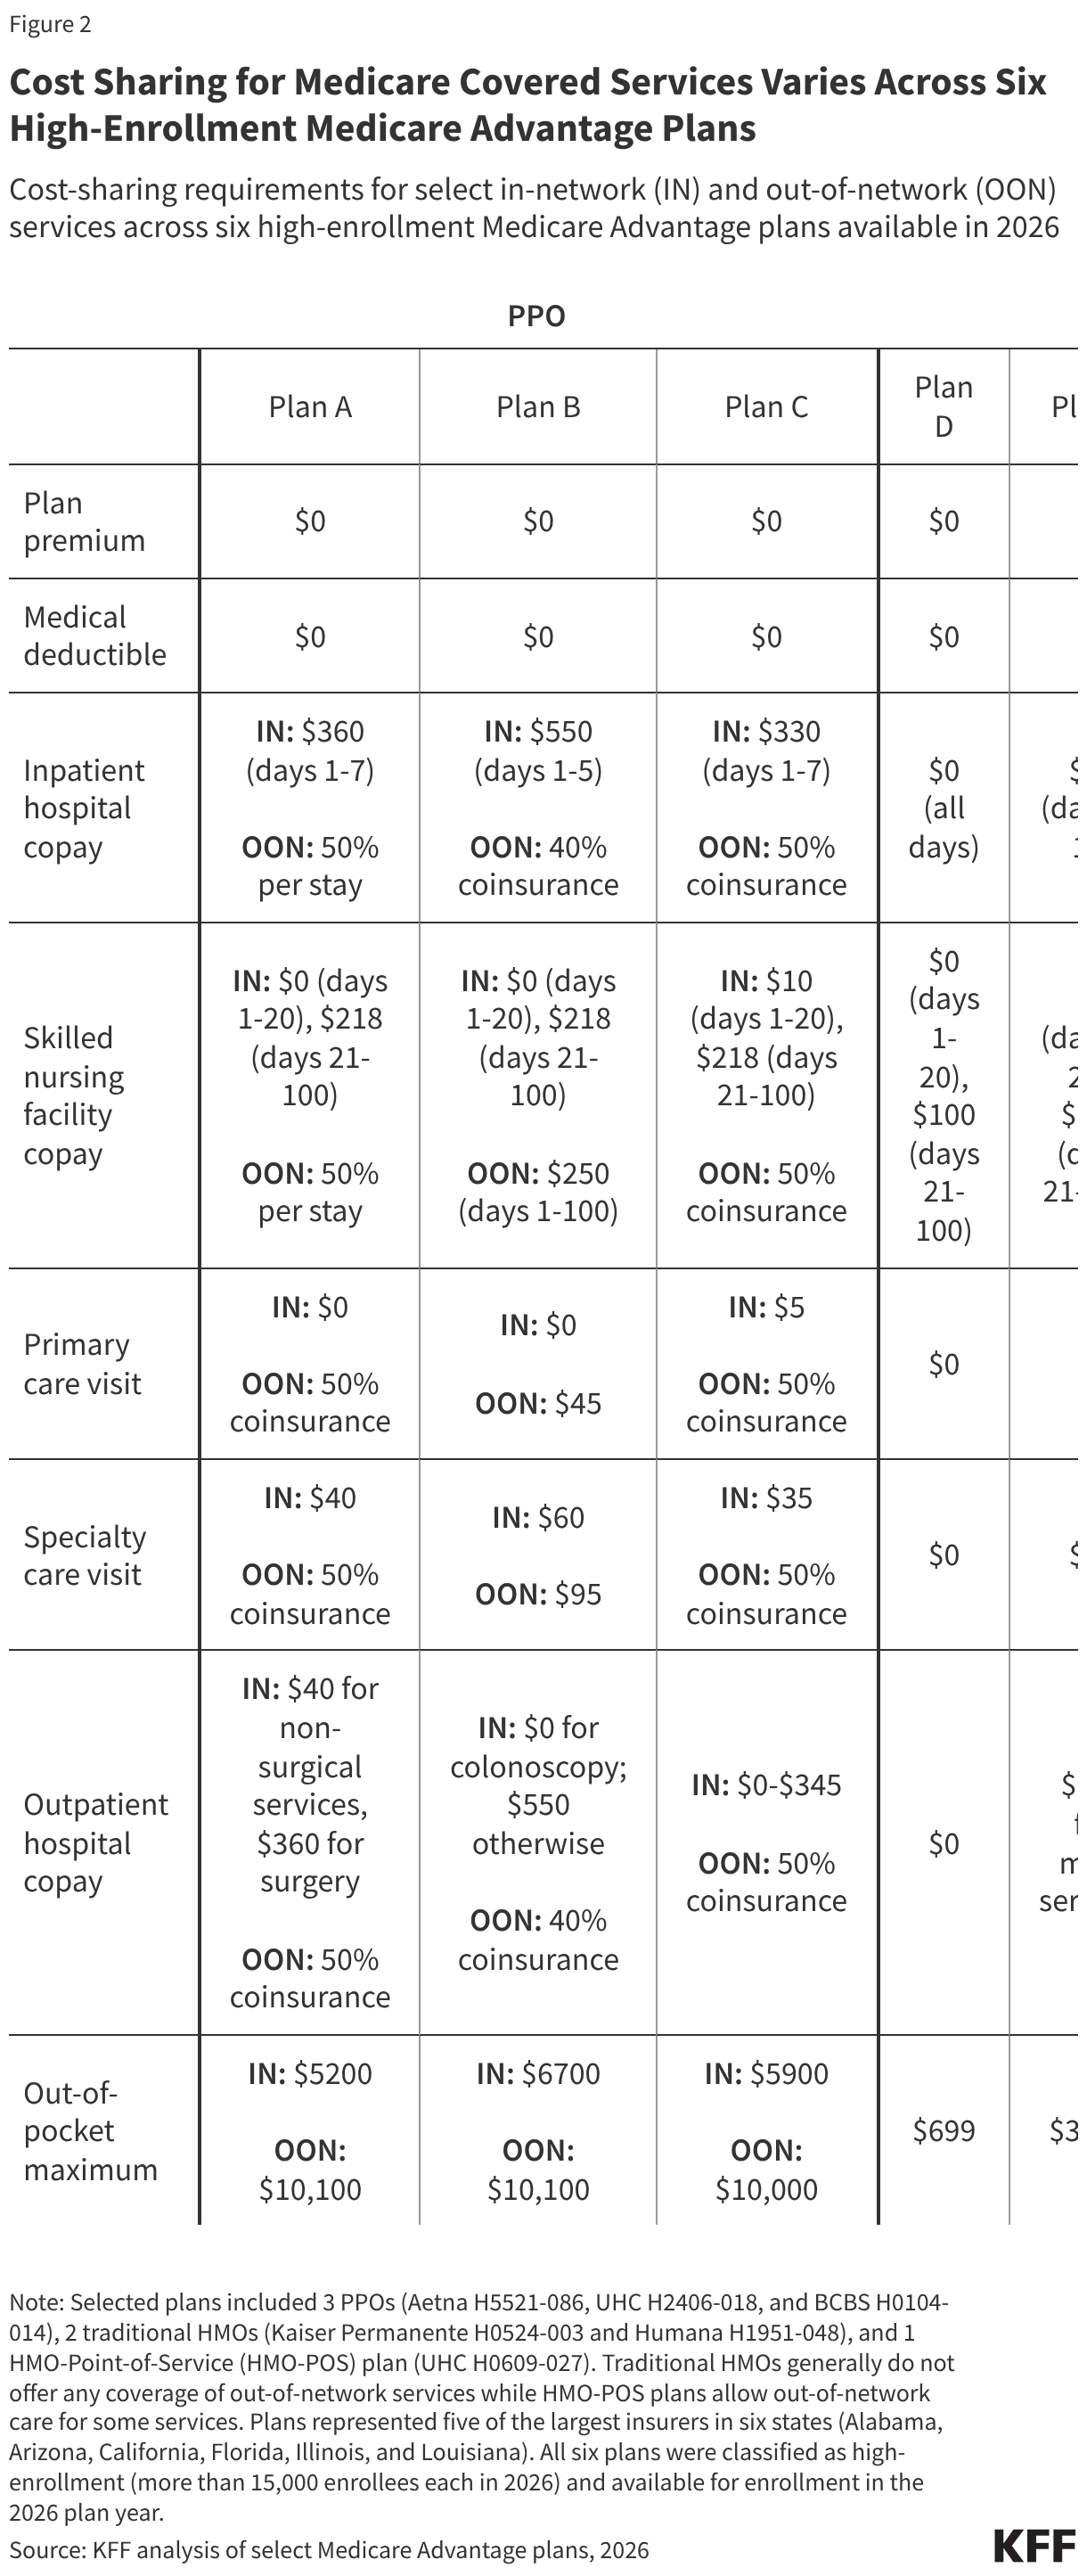
Conversely, Medicare Advantage (MA) plans present a different value proposition. While 75% of MA enrollees pay no additional monthly premium beyond their standard Part B cost, they trade flexibility for the plan’s cost-sharing structure. In 2026, MA plans are capped at $9,250 for in-network out-of-pocket spending, though the average limit is significantly lower, at $5,421.
Part D Drug Coverage
Prescription drug costs are no longer a "bottomless pit" thanks to the $2,100 out-of-pocket limit. However, the path to that limit involves navigating complex formularies. The standard Part D deductible is $615, though many plans reduce this to attract enrollees. The median copay for a generic drug stands at $3 to $5, while specialty drugs often carry coinsurance rates of 25% to 28%.
Official Perspectives and Regulatory Stance
The Centers for Medicare & Medicaid Services (CMS) continues to emphasize the importance of "Extra Help"—the Low-Income Subsidy (LIS) program—which remains the most effective tool for protecting low-income seniors from the rising tide of healthcare costs. By eliminating the drug deductible and reducing copayments, this program serves as a critical safety net.
However, industry experts and policy advocates often highlight the friction between cost-saving measures and access. While Medicare Advantage plans use rebate dollars to "buy down" premiums for enrollees, regulators are increasingly scrutinizing the use of prior authorization and limited provider networks. The government’s goal is to ensure that the competition between private insurers in the MA market results in lower costs for consumers, rather than just higher profits for the insurers.
Implications: The Long-Term Outlook
The trajectory of Medicare costs suggests a difficult decade ahead. As the baby boomer generation continues to age, the pressure on the Medicare Trust Fund will likely lead to further adjustments in premiums and cost-sharing tiers. For the average beneficiary, the implications are three-fold:
- Complexity is a Tax: The sheer number of choices—between stand-alone plans, Advantage plans, and supplemental policies—acts as a barrier to optimal financial health. Beneficiaries who do not actively review their plans during the annual enrollment period are likely to overpay or face gaps in coverage.
- The Rise of Managed Care: As Traditional Medicare remains without an out-of-pocket limit, more enrollees are being funneled toward Medicare Advantage. While this protects against catastrophic expenses, it shifts the healthcare experience toward a model defined by network restrictions and administrative approval processes.
- The Necessity of Financial Planning: Medicare is no longer "free" or "fully covered." It is a subsidized insurance product that requires significant out-of-pocket budgeting. Future beneficiaries must account for the reality that healthcare spending will likely consume an increasing share of their retirement income.
Conclusion
The 2026 Medicare landscape is characterized by a push-pull dynamic between enhanced consumer protections—such as the Part D out-of-pocket cap—and the rising baseline costs of participation. While the program continues to provide vital access to care, the financial burden is increasingly placed on the beneficiary. Navigating this system requires more than just enrolling; it requires an active, informed, and continuous evaluation of one’s health needs and financial resources. As the government continues to refine these programs, the onus remains on the individual to leverage available subsidies, understand their plan’s network constraints, and prepare for the long-term economic realities of aging in the United States.
About the Author