Editorial Note: Originally published on January 13, 2026, this report has been continuously updated to reflect the most recent policy developments, with the latest comprehensive data review conducted on October 8, 2026.
Introduction: A Paradigm Shift in Global Health
In a significant departure from decades of traditional U.S. foreign aid policy, the United States government (USG) officially launched its "America First Global Health Strategy" on September 18, 2025. This pivot marks a fundamental transition in how Washington engages with international partners, moving away from long-term, open-ended assistance toward a model defined by bilateral Memorandums of Understanding (MOUs) and a mandated "pathway to ownership."
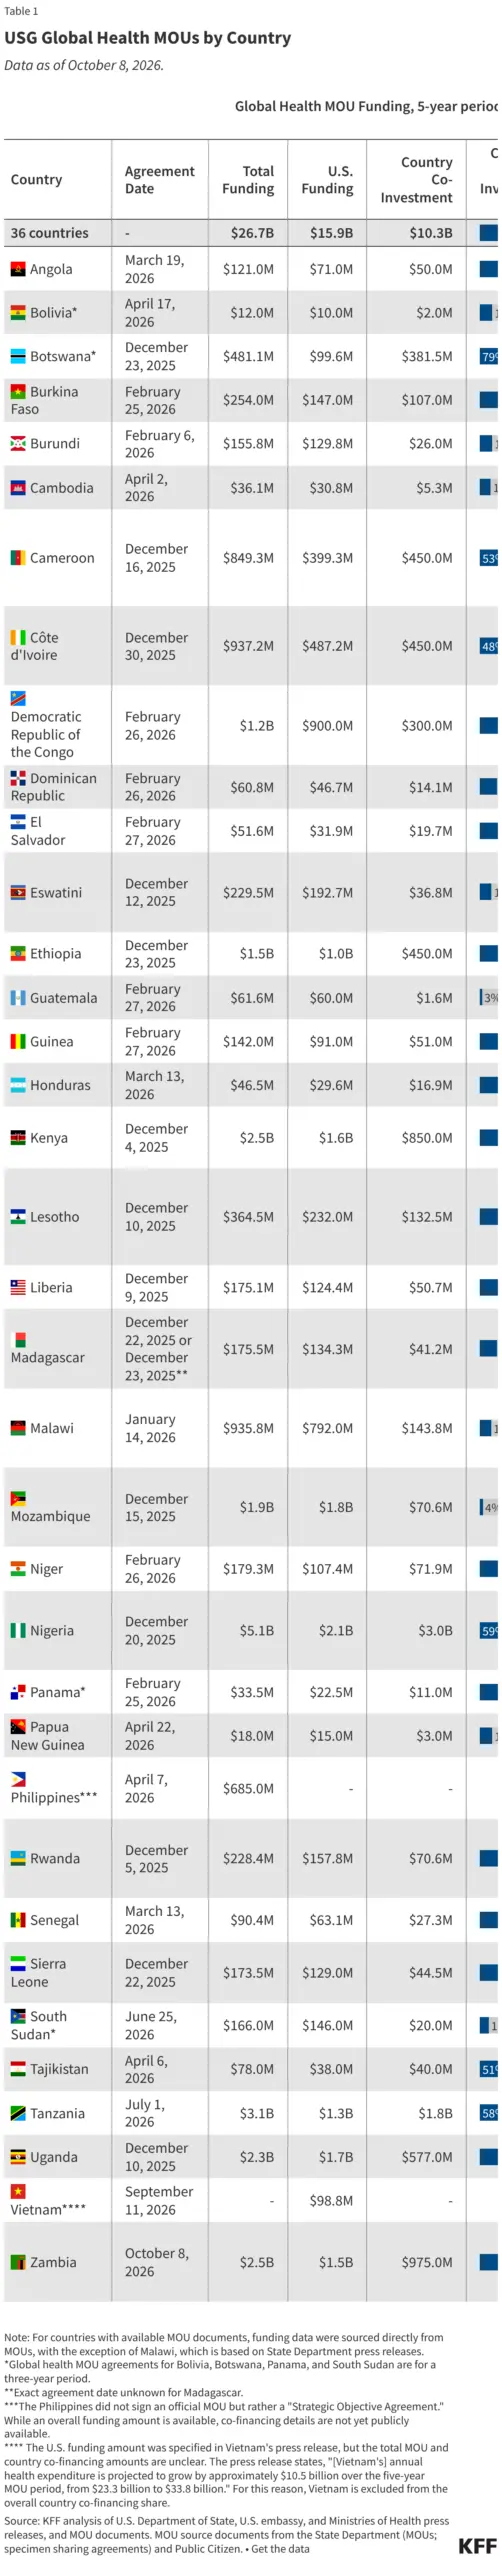
The core objective of this strategy is the cultivation of "resilient and durable health systems" that are ultimately funded and managed by host nations. As the U.S. systematically reduces its direct financial footprint, it is requiring partner countries to commit to a five-year co-investment schedule. This report provides an in-depth look at the structural changes, the current landscape of the 36 signed agreements, and the broader implications for global health security.

Chronology of the Policy Shift
The transition to the "America First" model did not occur in a vacuum; it follows years of internal debate within the U.S. foreign policy establishment regarding the sustainability of the Global Health Programs (GHP) account.
- Early 2025: Conceptualization of the "America First" doctrine for health, emphasizing fiscal responsibility and host-country sovereignty.
- September 18, 2025: Formal publication of the America First Global Health Strategy Report, outlining the transition away from indefinite aid.
- Late 2025: Initial signing of bilateral MOUs with the first wave of partner countries.
- January 2026: Official launch of the tracker and public disclosure of the initial wave of five-year agreements (2026–2030).
- October 8, 2026: Most recent update to the program data, confirming that 36 countries have now formalized their participation under the new framework.
Supporting Data: The Anatomy of the 36 MOUs
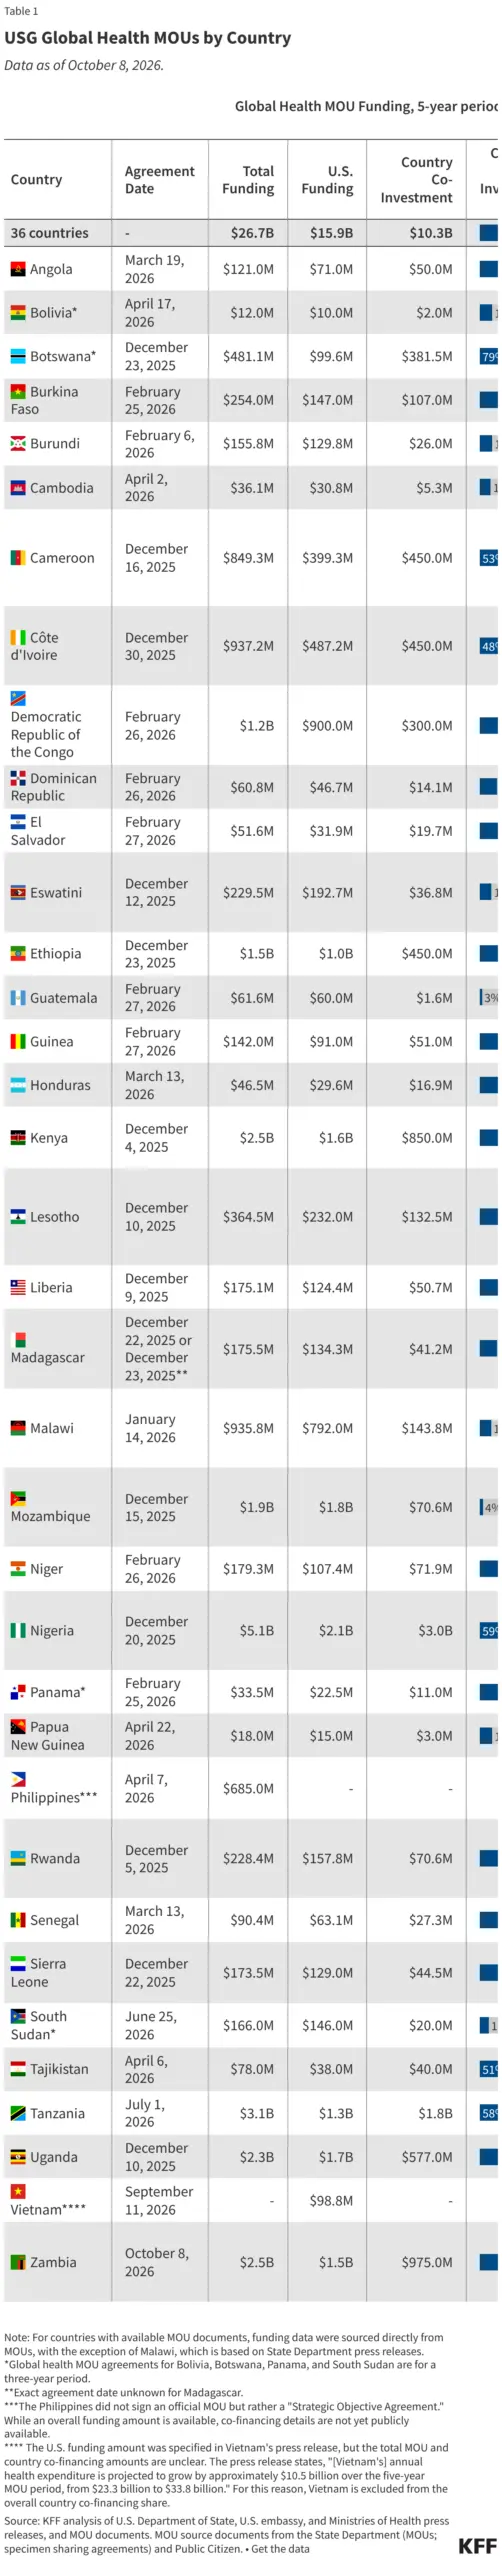
As of October 2026, the U.S. has successfully negotiated agreements with 36 nations. The data highlights a stark reality: the era of U.S.-funded global health dominance is contracting.
Funding Trends and the "Co-Investment" Mandate
The most striking figure emerging from the data is the total reduction in U.S. financial support. Among the countries currently under agreement, there has been a projected total reduction of $8.1 billion in U.S. funding over five years, representing a 34% decrease compared to historical benchmarks (FY21–25).

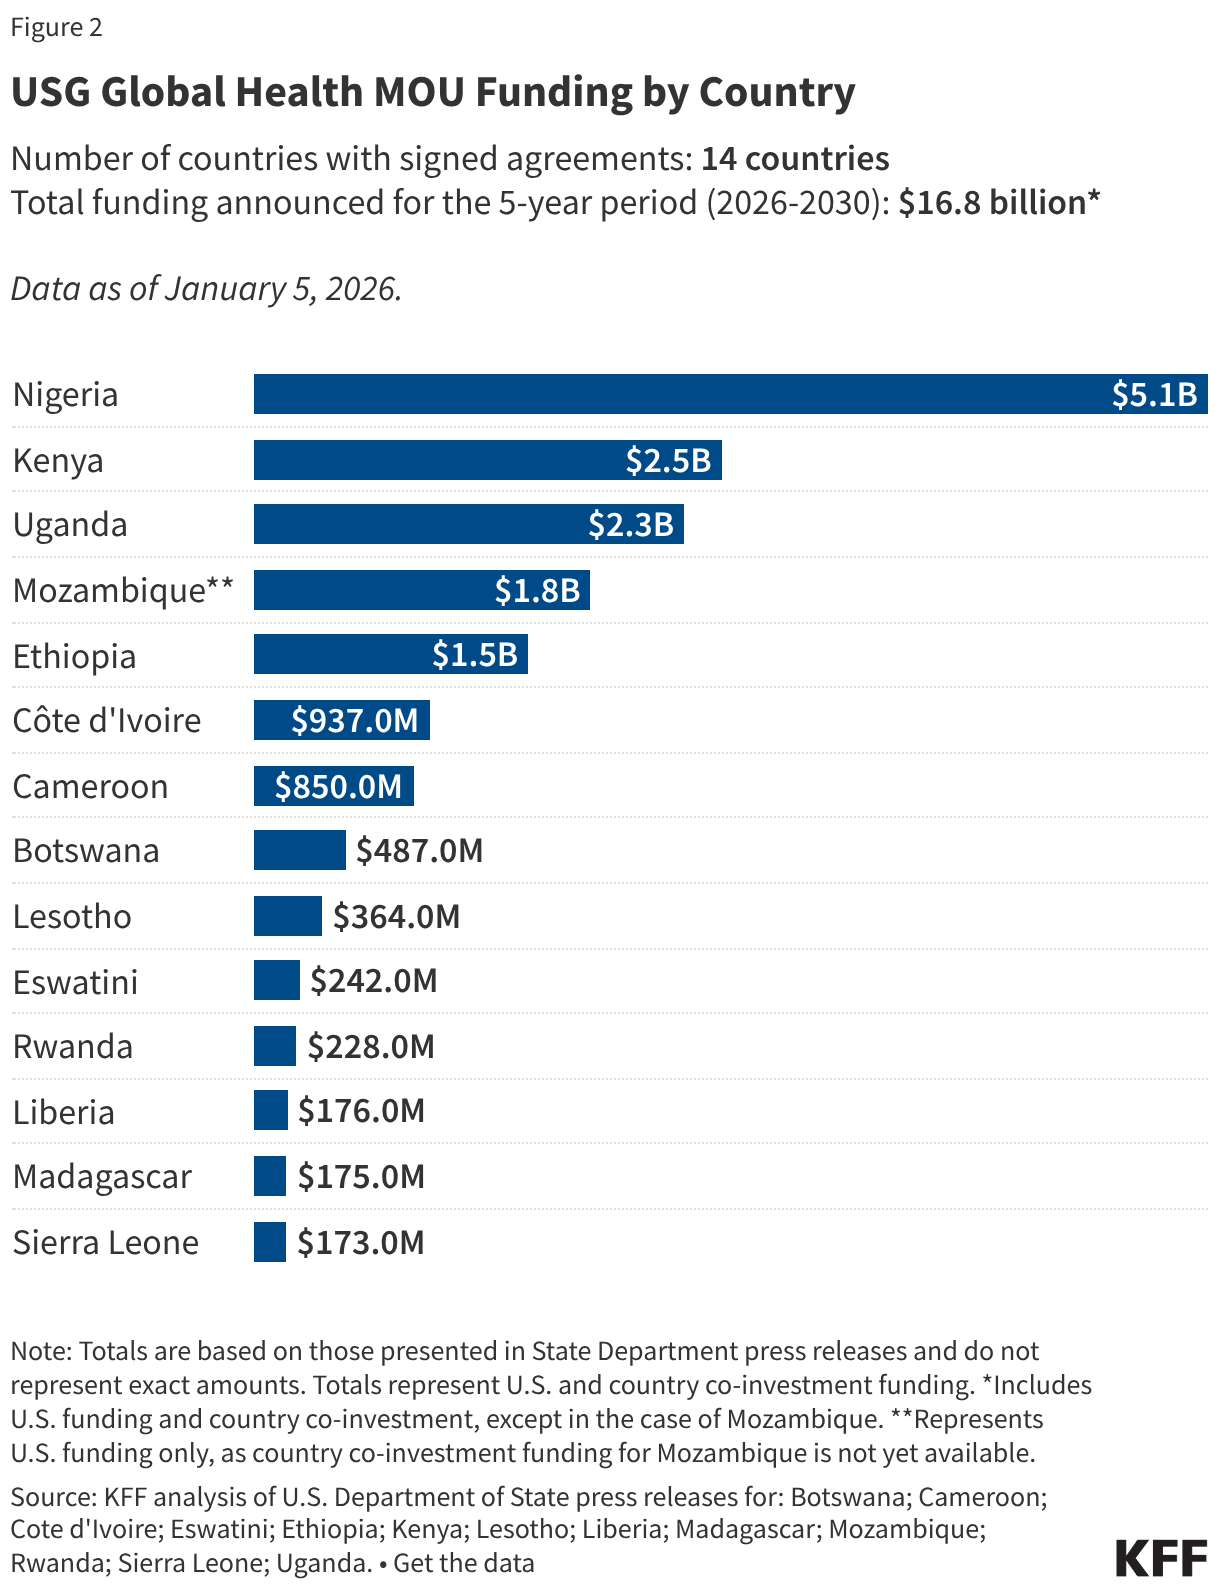
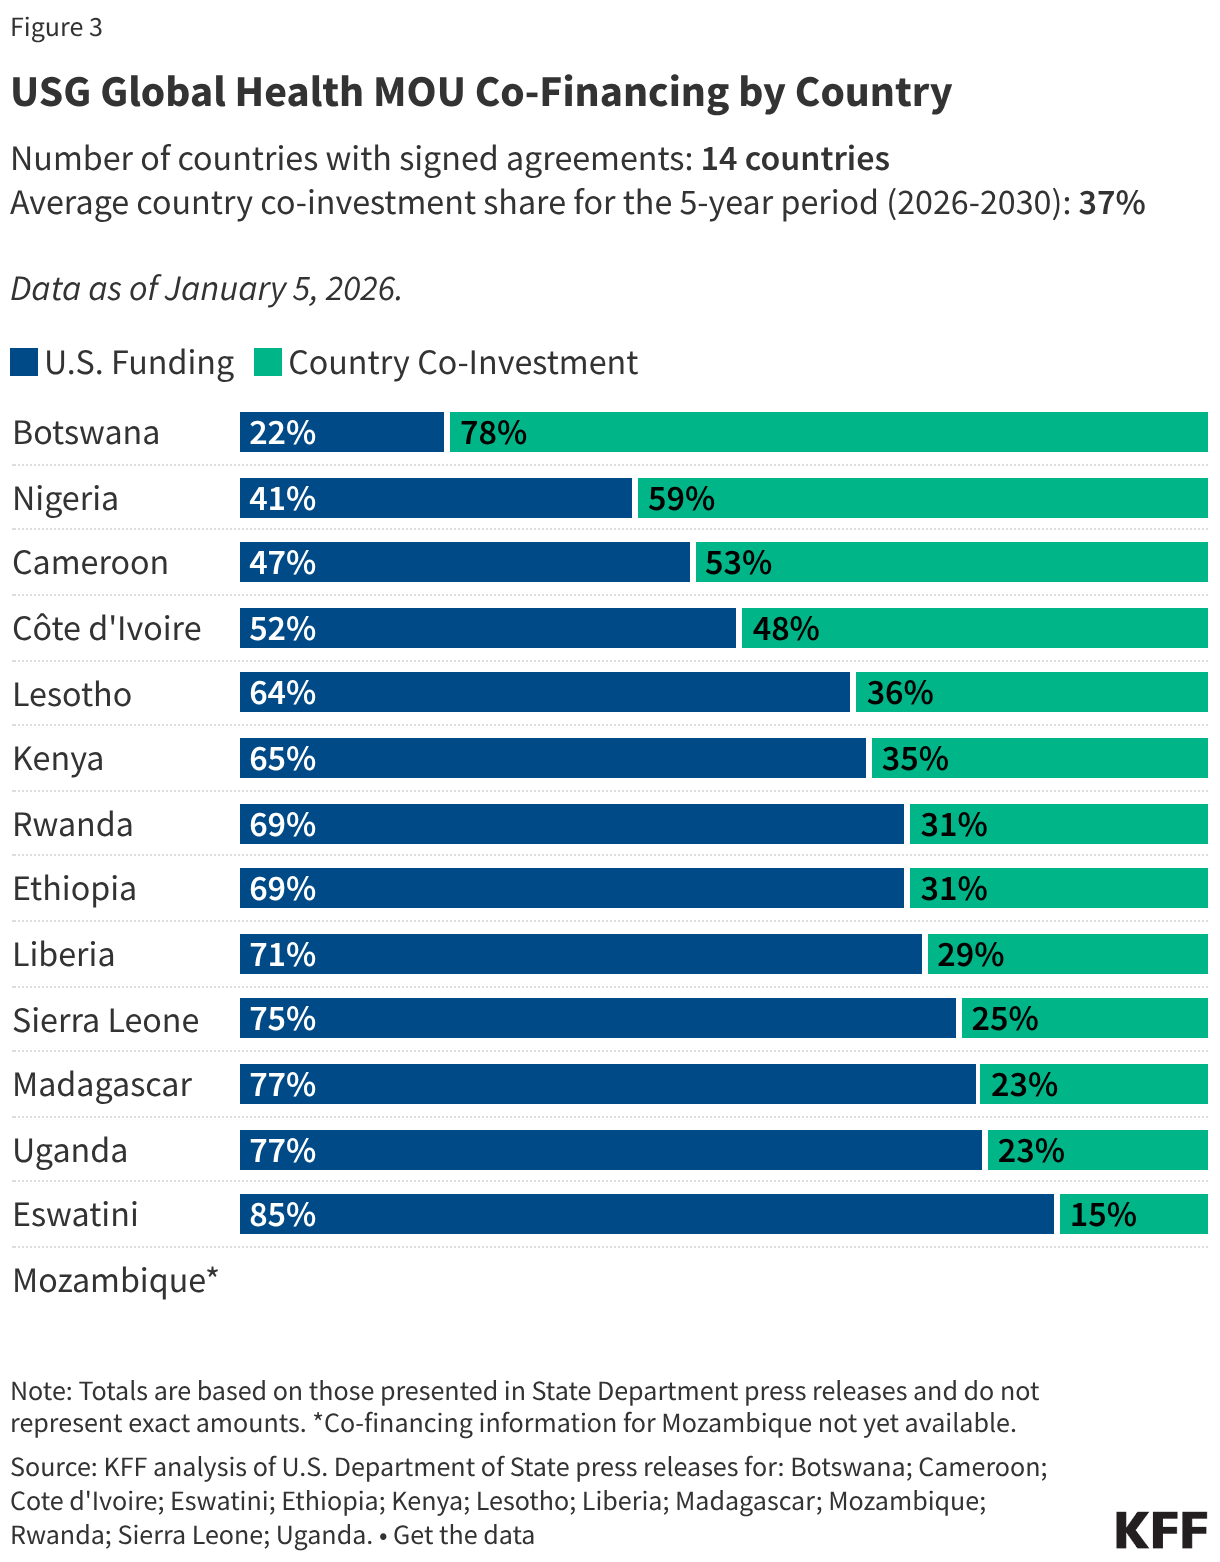
This reduction is not presented by the State Department as a withdrawal, but as a strategic "hand-off." The MOUs require partner nations to increase their domestic health expenditure—a "co-investment" strategy designed to fill the void left by the departing U.S. dollars.
For instance, in the case of Vietnam, while the U.S. has pledged a specific, capped amount for its MOU, the State Department explicitly highlights that the country’s annual health expenditure is projected to grow by approximately $10.5 billion over the five-year period. This encapsulates the "America First" logic: the U.S. acts as a catalyst, but the host nation becomes the primary financier.
Geographical and Programmatic Distribution
The MOUs vary significantly in scope. While some countries have entered into standard five-year plans, others—specifically Bolivia, Botswana, Panama, and South Sudan—have opted for three-year timelines. Furthermore, the nature of these agreements is not uniform. The Philippines, for example, opted for a "Strategic Objective Agreement" rather than a traditional MOU, indicating that the U.S. government is willing to demonstrate flexibility in its legal terminology to maintain regional security partnerships.

Programmatic focus remains centered on health systems strengthening, though the "Global Health Security" (GHS) tag is being applied more stringently. To be categorized under GHS in the current tracker, a nation’s agreement must explicitly reference outbreak preparedness or the containment of health threats, moving away from broad, nonspecific aid packages.
Official Responses and Diplomatic Positioning
The U.S. State Department has framed this strategy as an act of empowerment. In official press releases, spokespeople emphasize that "dependency is the enemy of sustainability." By forcing a transition to local ownership, the U.S. argues that it is helping countries build the political and economic infrastructure necessary to survive without external intervention.
However, reactions from partner countries remain mixed. Ministries of Health in several partner nations have publicly welcomed the "sovereignty" aspect of the agreements, noting that domestic control over health priorities allows for better alignment with local cultural and epidemiological needs. Conversely, behind closed doors, many health officials express concern about the "fiscal cliff" that looms in 2030. If a partner country fails to meet its co-investment targets, the lack of a "safety net" clause in these MOUs leaves the long-term viability of their health systems in jeopardy.
Implications: The Risks and Rewards of the "America First" Approach
The Risk of Fragility
The primary criticism of this strategy is the risk of systemic collapse in lower-income countries. Global health experts have noted that while the goal of self-reliance is noble, the timeline—five years—may be insufficient for nations with limited tax bases to absorb the loss of billions in U.S. aid. If domestic economic growth does not meet the optimistic projections cited by the State Department, these nations may be forced to choose between debt and the degradation of essential medical services.
Strategic Realignment
From the U.S. perspective, the strategy is a necessary adjustment to a multipolar world. By focusing resources on fewer, more targeted interventions, the U.S. aims to preserve its ability to project soft power while reducing the federal deficit. This is, in effect, a strategic retreat from being the "global insurer" of health toward being a "global partner" in capacity building.
The Future of Global Health Security
Perhaps the most critical implication of this policy is its impact on pandemic preparedness. The world learned in 2020 that global health is only as strong as its weakest link. By tying future funding to explicit performance metrics and shifting the financial burden to local governments, the U.S. is betting that countries will be more vigilant in maintaining their own health security if they are paying for it themselves. Whether this bet pays off in the face of the next global health crisis remains the most significant unanswered question of the 2026–2030 period.
Methodology and Data Integrity
The findings presented here are synthesized from a rigorous analysis of:
- Primary Documentation: Official MOU texts, where publicly available.
- Government Communications: Press releases from the U.S. State Department, U.S. Embassies abroad, and partner country Ministries of Health.
- Keyword Categorization: Program areas were determined via keyword mapping. Specifically, "Global Health Security" was only applied to agreements that explicitly cited outbreak response, pathogen surveillance, or threat containment.
It is important to note that because many MOUs remain classified or internal, this data should be viewed as a "living" snapshot. The tracker is updated as more agreements move from negotiation to public disclosure. Limitations exist, particularly regarding co-financing transparency in countries like the Philippines and Vietnam, where the nuances of private-public sector health funding remain opaque.
Conclusion: A New Era
The "America First Global Health Strategy" represents the most significant change in U.S. health diplomacy in the 21st century. As the 36 signatory nations embark on this five-year transition, the international community is watching to see if this model of "managed independence" succeeds in creating sustainable health systems or if it creates a vacuum of leadership that other global powers may be all too eager to fill. The path to 2030 is set; its success will be measured not in the billions of dollars spent, but in the resilience of the systems that remain when the U.S. assistance eventually ceases.
About the Author