As the United States approaches the 2026 midterm election cycle, state legislatures and gubernatorial administrations are bracing for a seismic shift in public health infrastructure. The 2025 federal reconciliation law has set in motion a profound restructuring of Medicaid, the nation’s primary safety-net insurance program. With the Congressional Budget Office (CBO) projecting a staggering $911 billion reduction in federal Medicaid spending through 2034, the program faces its most significant transformation since the inception of the Affordable Care Act (ACA).
For state officials, the challenge is twofold: managing the immediate fiscal strain of declining federal support while navigating the administrative complexities of implementing new, more restrictive eligibility requirements. As the uninsured population is expected to grow by 7.5 million by 2034, the pressure on state budgets and health care providers is reaching a critical inflection point.
Main Facts: The Scope of the Transformation
The 2025 reconciliation law serves as a watershed moment for state-level health policy. By tightening the purse strings on federal contributions, the law forces states to choose between raising taxes, cutting provider reimbursement rates, or reducing the number of citizens eligible for coverage.

The Fiscal Reality
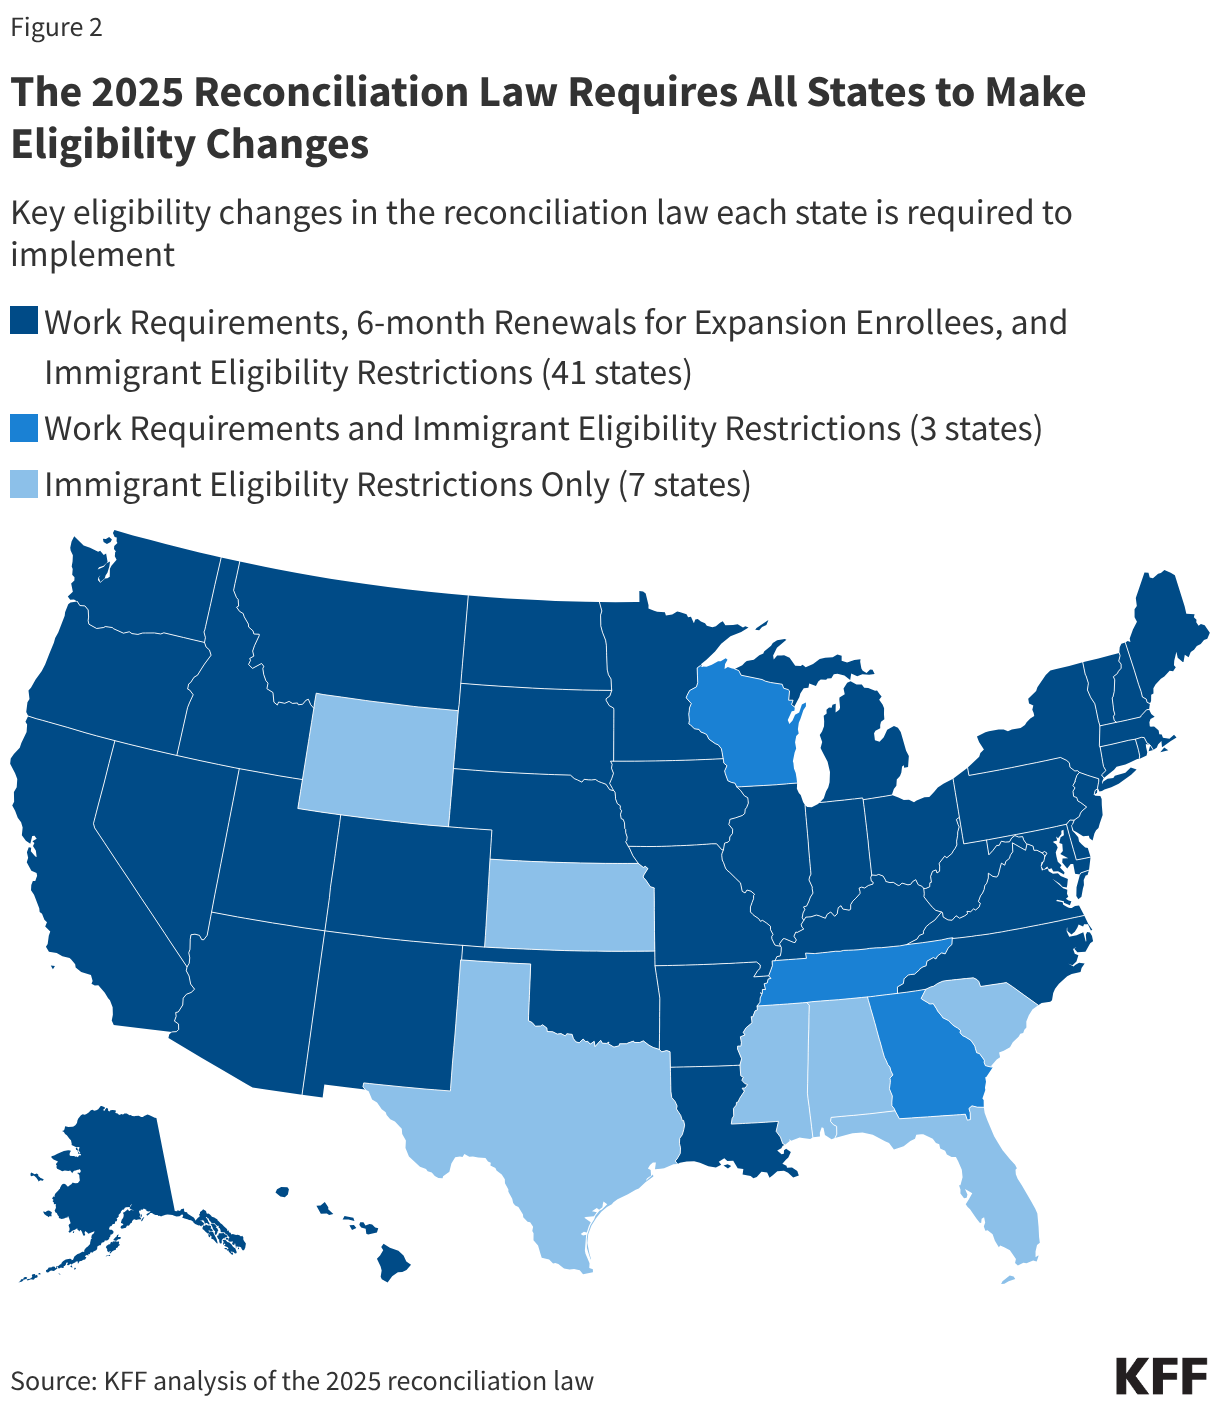
The CBO’s $911 billion estimate represents a massive contraction in the federal government’s commitment to state health programs. This reduction is not merely a budgetary exercise; it represents a fundamental change in the social contract for millions of low-income Americans. States that previously opted for the ACA Medicaid expansion find themselves on the front lines, as the new law imposes stricter eligibility hurdles and limits the financing mechanisms—such as provider taxes—that states have long used to bridge funding gaps.
The Rural Health Fund
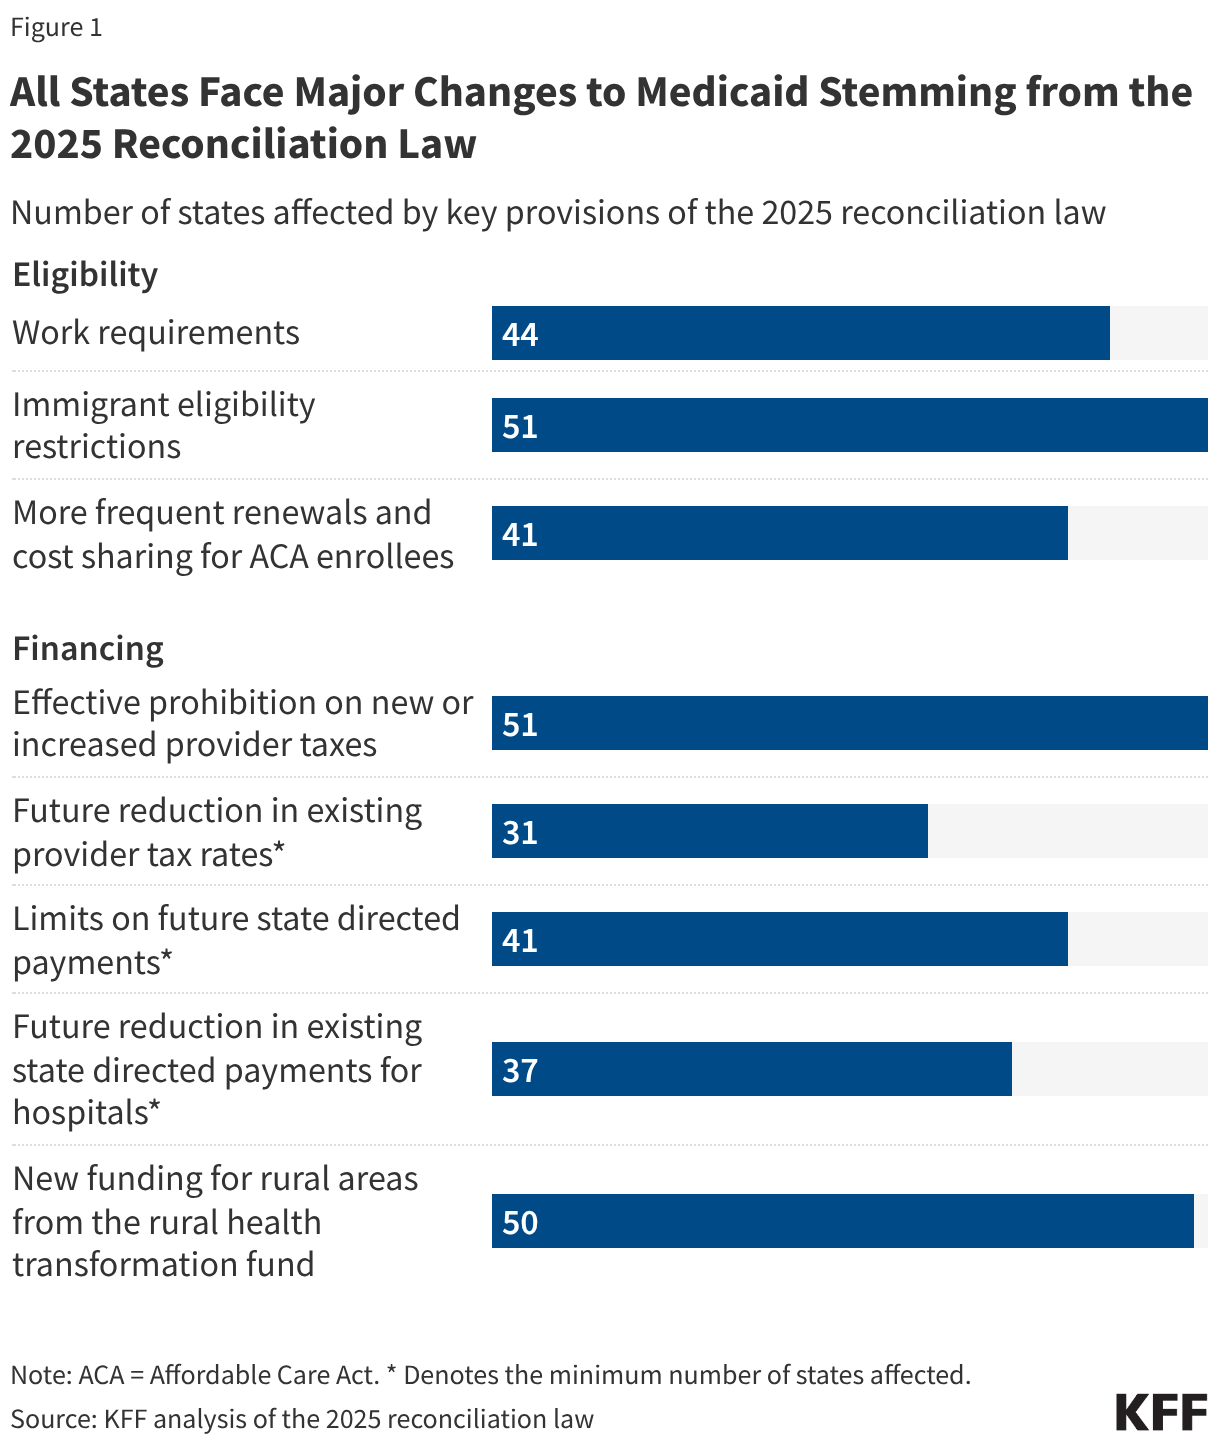
Recognizing the potential for systemic collapse in rural health care, where hospitals already operate on razor-thin margins, policymakers included a $50 billion "Rural Health Transformation Program." While this fund provides a necessary infusion of capital to all 50 states, experts warn that it is a time-limited measure that fails to offset the permanent, long-term erosion of Medicaid revenue.
Chronology: A Roadmap of Implementation
The transition to the new Medicaid regime is not an overnight event but a staggered rollout that complicates long-term planning for state health departments.
- 2025 (Initial Enactment): The reconciliation law is signed into effect. All 50 states receive their initial allotments from the Rural Health Fund to begin planning structural transitions.
- 2026 (The Election Year): 36 states hold gubernatorial elections. Political volatility is expected to hinder the smooth implementation of complex administrative changes, particularly in the 19 states anticipating a change in executive leadership.
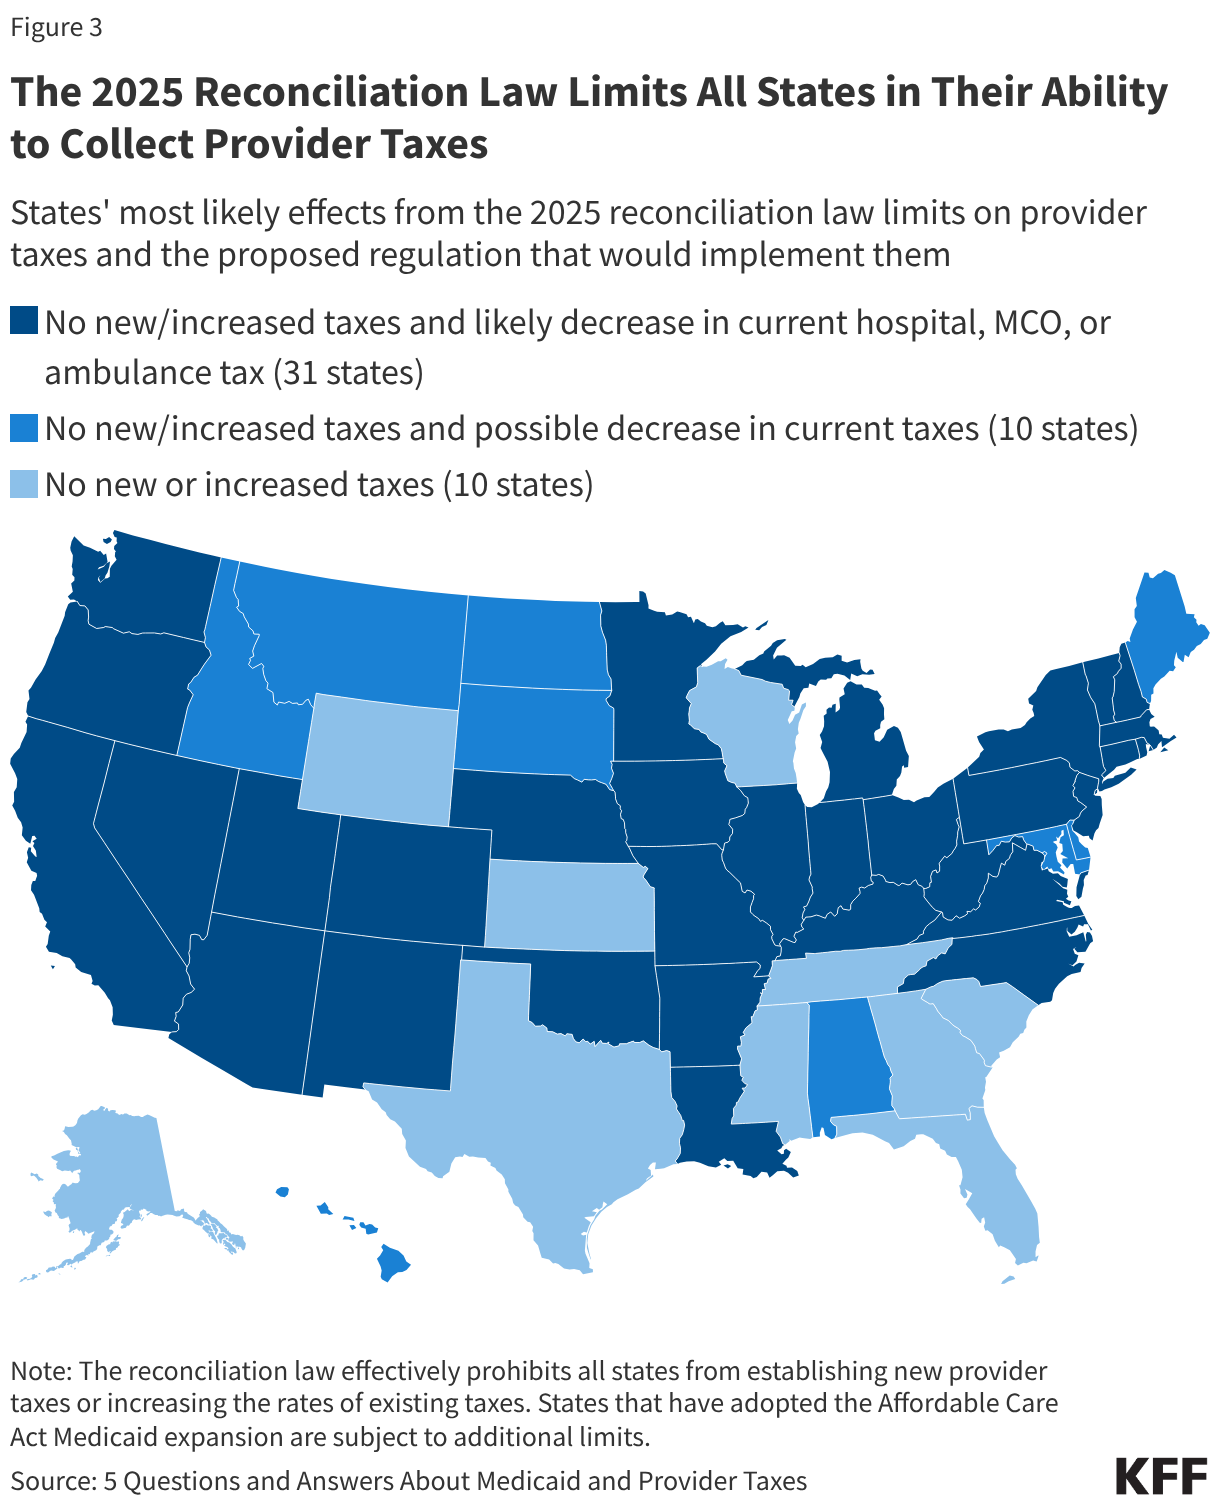
- October 1, 2027: The "provider tax" cliff begins. The permissible threshold for net patient revenue collections drops by 0.5% annually, eventually landing at 3.5%. This will squeeze state coffers in at least 31 states that currently rely on these taxes for budget stability.
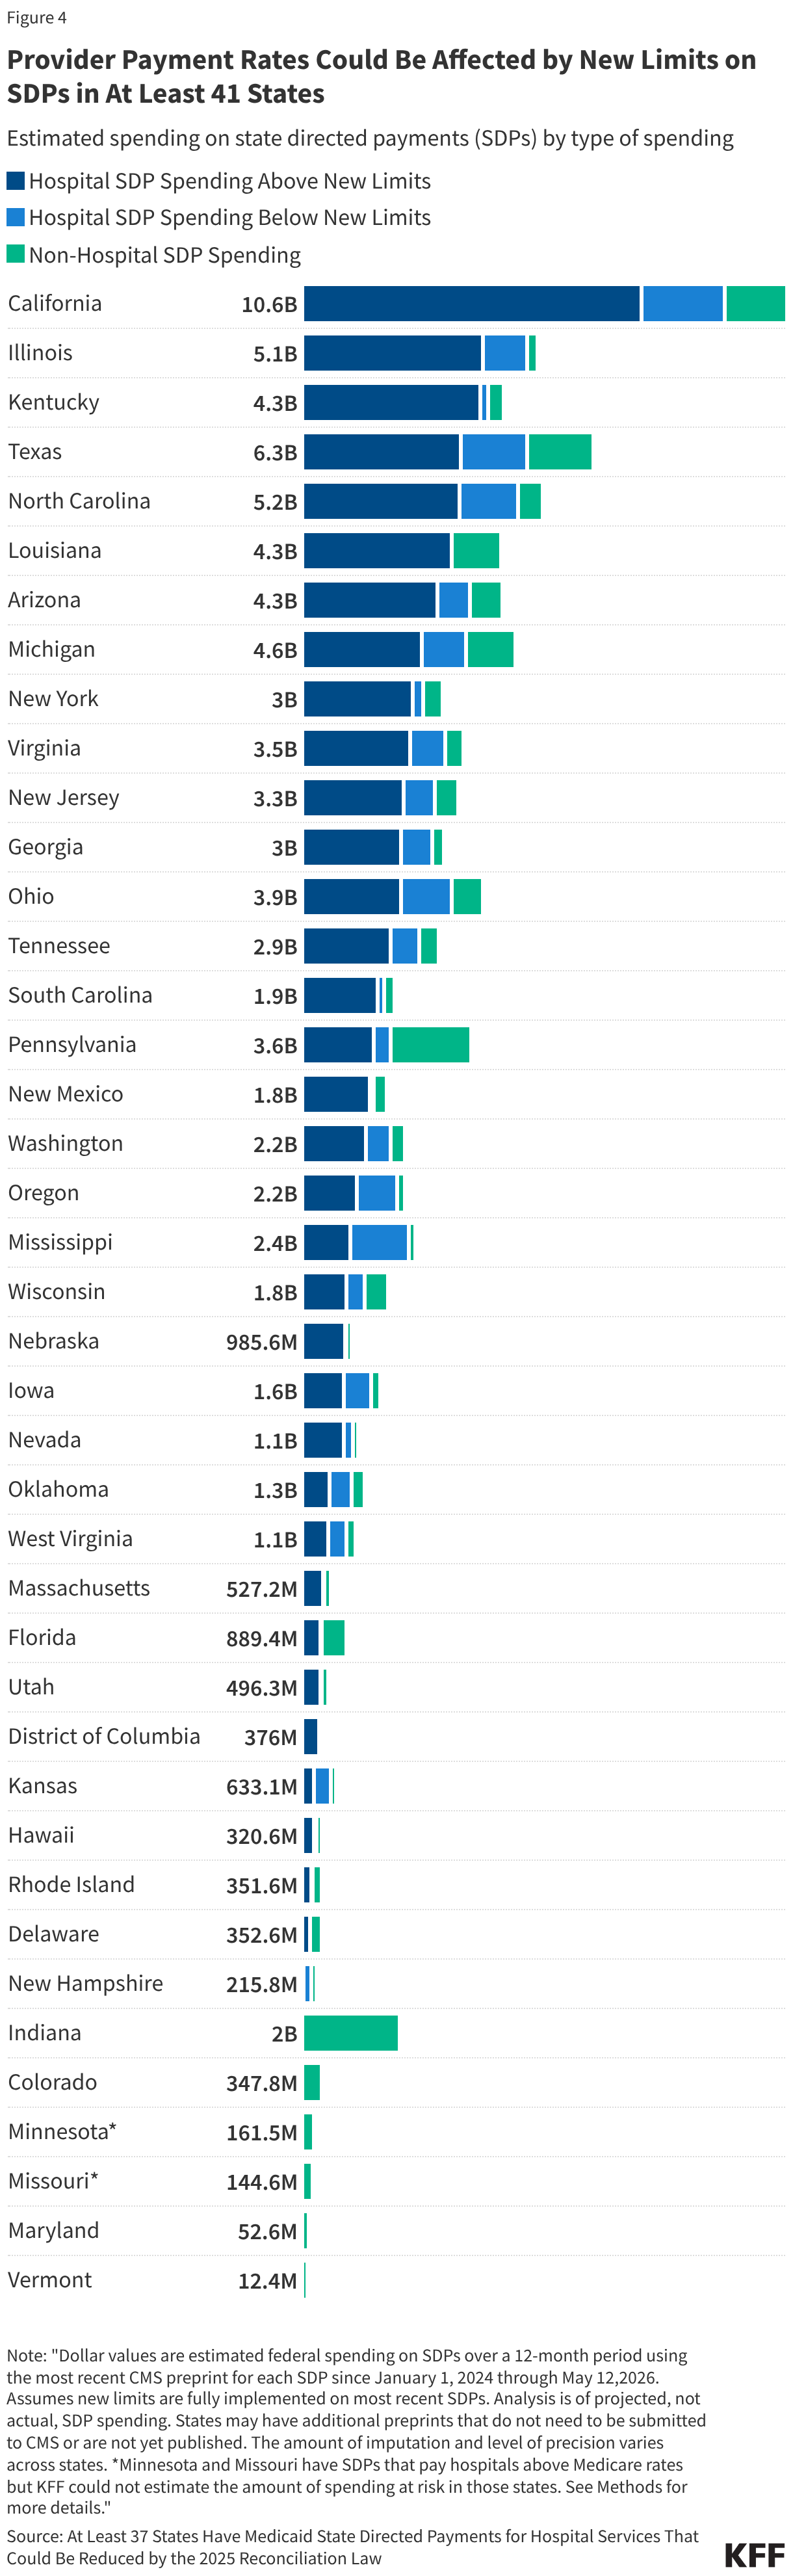
- January 1, 2028: New federal limits on State Directed Payments (SDPs) take effect. This will severely curtail the ability of states to provide supplemental payments to hospitals, effectively capping reimbursement rates at Medicare levels.
- 2034 (The Long-Term Horizon): CBO projections estimate a peak impact, with an additional 7.5 million people nationwide lacking health insurance due to the cumulative effect of the law’s provisions.
Supporting Data: Disparities and Dependencies
The impact of the 2025 law is not uniform; it is geographically and structurally dependent. Data analysis reveals a landscape of winners and losers defined by existing state policy choices.
The Provider Tax Squeeze
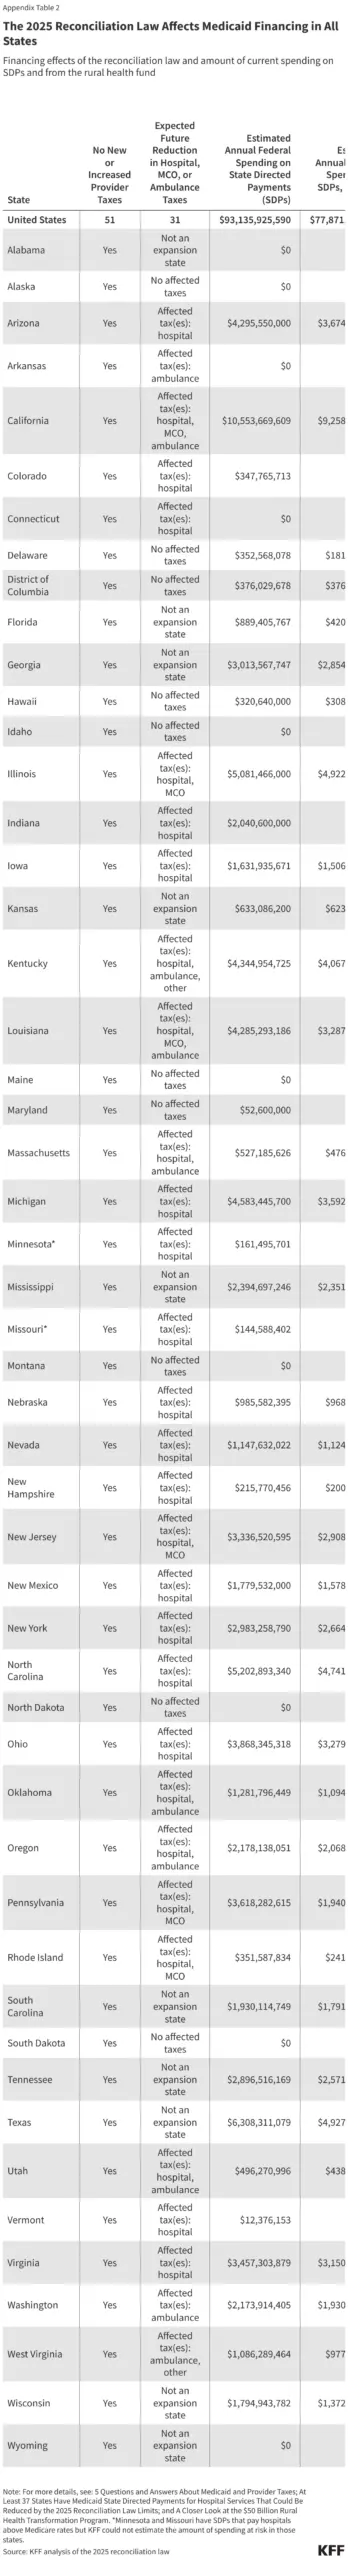
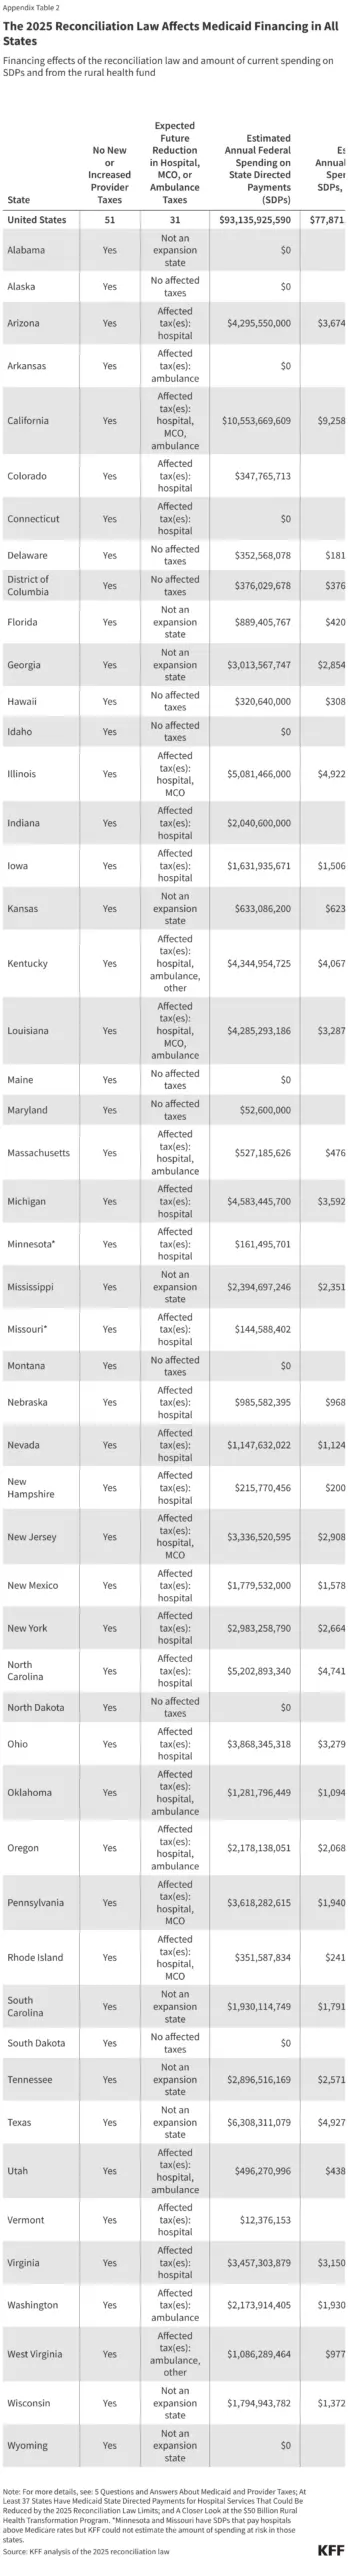
Provider taxes have been a vital tool for states to generate the "state share" of Medicaid funding. By limiting these taxes, the federal government is effectively removing a primary lever of fiscal autonomy. Currently, 31 states maintain taxes on hospitals, managed care organizations, or ambulances that exceed the incoming 3.5% ceiling. The impending reduction will necessitate painful adjustments to state budgets or force a decline in provider services.
The SDP Reduction
State Directed Payments (SDPs) have allowed states to keep safety-net hospitals solvent by paying rates closer to private insurance levels. With $60 billion of the $78 billion currently spent on hospital-related SDPs at risk of being cut, the financial viability of rural and urban public hospitals is in jeopardy. Eight states—California, Illinois, Kentucky, Texas, North Carolina, Louisiana, Arizona, and Michigan—are poised to absorb more than 50% of these specific losses, creating an intense regional concentration of financial stress.
Disparities in Rural Support
While all states received funding from the $50 billion Rural Health Fund, the distribution per rural resident reveals stark inequities. Rhode Island, for example, received $6,305 per rural resident, while Texas received only $66. This disparity, rooted in a complex funding formula that balances "state need" with political initiative proposals, suggests that the "transformation" will look vastly different depending on the state’s political maneuvering and demographic profile.
Official Responses and Administrative Challenges
The administrative burden of these changes cannot be overstated. States are currently being asked to implement more frequent eligibility redeterminations, enforce new work requirements, and manage the complexity of restricted retroactive coverage.
The "Political" Variable
The fact that 36 states face gubernatorial elections in 2026 adds a layer of extreme uncertainty. Health policy analysts argue that in states where a change in administration is likely, the continuity of Medicaid management is at risk. A new governor may bring a different ideological approach to the law’s implementation, further complicating the already difficult task of coordinating with federal regulatory bodies.
The Provider Perspective
Health care providers, particularly in rural settings, have expressed alarm. The combination of falling Medicaid reimbursement rates and an increasing number of uninsured patients creates a "double-jeopardy" scenario. Hospitals that were already struggling to remain open may face bankruptcy, leading to "medical deserts" in regions that rely solely on these facilities for emergency and primary care.
Implications: The Future of the Safety Net
As we look toward the next decade, the implications of the 2025 reconciliation law are profound. The reduction of $911 billion in federal spending is effectively a federal divestment from the health of the American public.
The Shift to the Uninsured
The most alarming implication is the projected 7.5 million increase in the uninsured population. This shift represents more than just a statistic; it signals a return to a pre-ACA landscape where the cost of uncompensated care is pushed back onto hospitals and, ultimately, onto the private insurance market in the form of higher premiums.
The Administrative "Work-Around"
States are currently scrambling to find administrative work-arounds to these mandates. However, the federal government’s proposed rules—such as expanding limits to include health insurer taxes—suggest that there will be little room for states to maneuver. The era of flexible Medicaid financing is drawing to a close, replaced by a more rigid, constrained model.
Long-Term Sustainability
While the Rural Health Fund offers a temporary lifeline, its expiration in five years leaves a void. Without a permanent solution to replace the lost Medicaid revenue, states will be forced to confront the reality that they cannot maintain the current level of health coverage without significant tax increases or further service degradation.
In conclusion, the 2025 reconciliation law has fundamentally altered the Medicaid landscape. Whether the result will be a more "efficient" program or a hollowed-out shell remains the central question for the 2026 election cycle. As voters go to the polls, the debate over who deserves coverage and how states should pay for it will remain a defining, and likely divisive, feature of American political life. The data is clear: the era of expansion has ended, and a new, more difficult era of fiscal contraction and administrative austerity has begun.
About the Author