As the Medicare open enrollment period approaches, beneficiaries are bracing for a landscape of prescription drug coverage that is increasingly defined by consolidation and volatility. The Centers for Medicare & Medicaid Services (CMS) has released its projections for 2027, painting a picture of a "stable" market—a term that masks significant underlying shifts in how millions of Americans will access and pay for their medications. While the agency anticipates only a modest $1 increase in the average monthly premium for stand-alone Prescription Drug Plans (PDPs), moving from $35 to $36, the reality for individual enrollees is far more complex.
The Main Facts: A Shrinking Marketplace
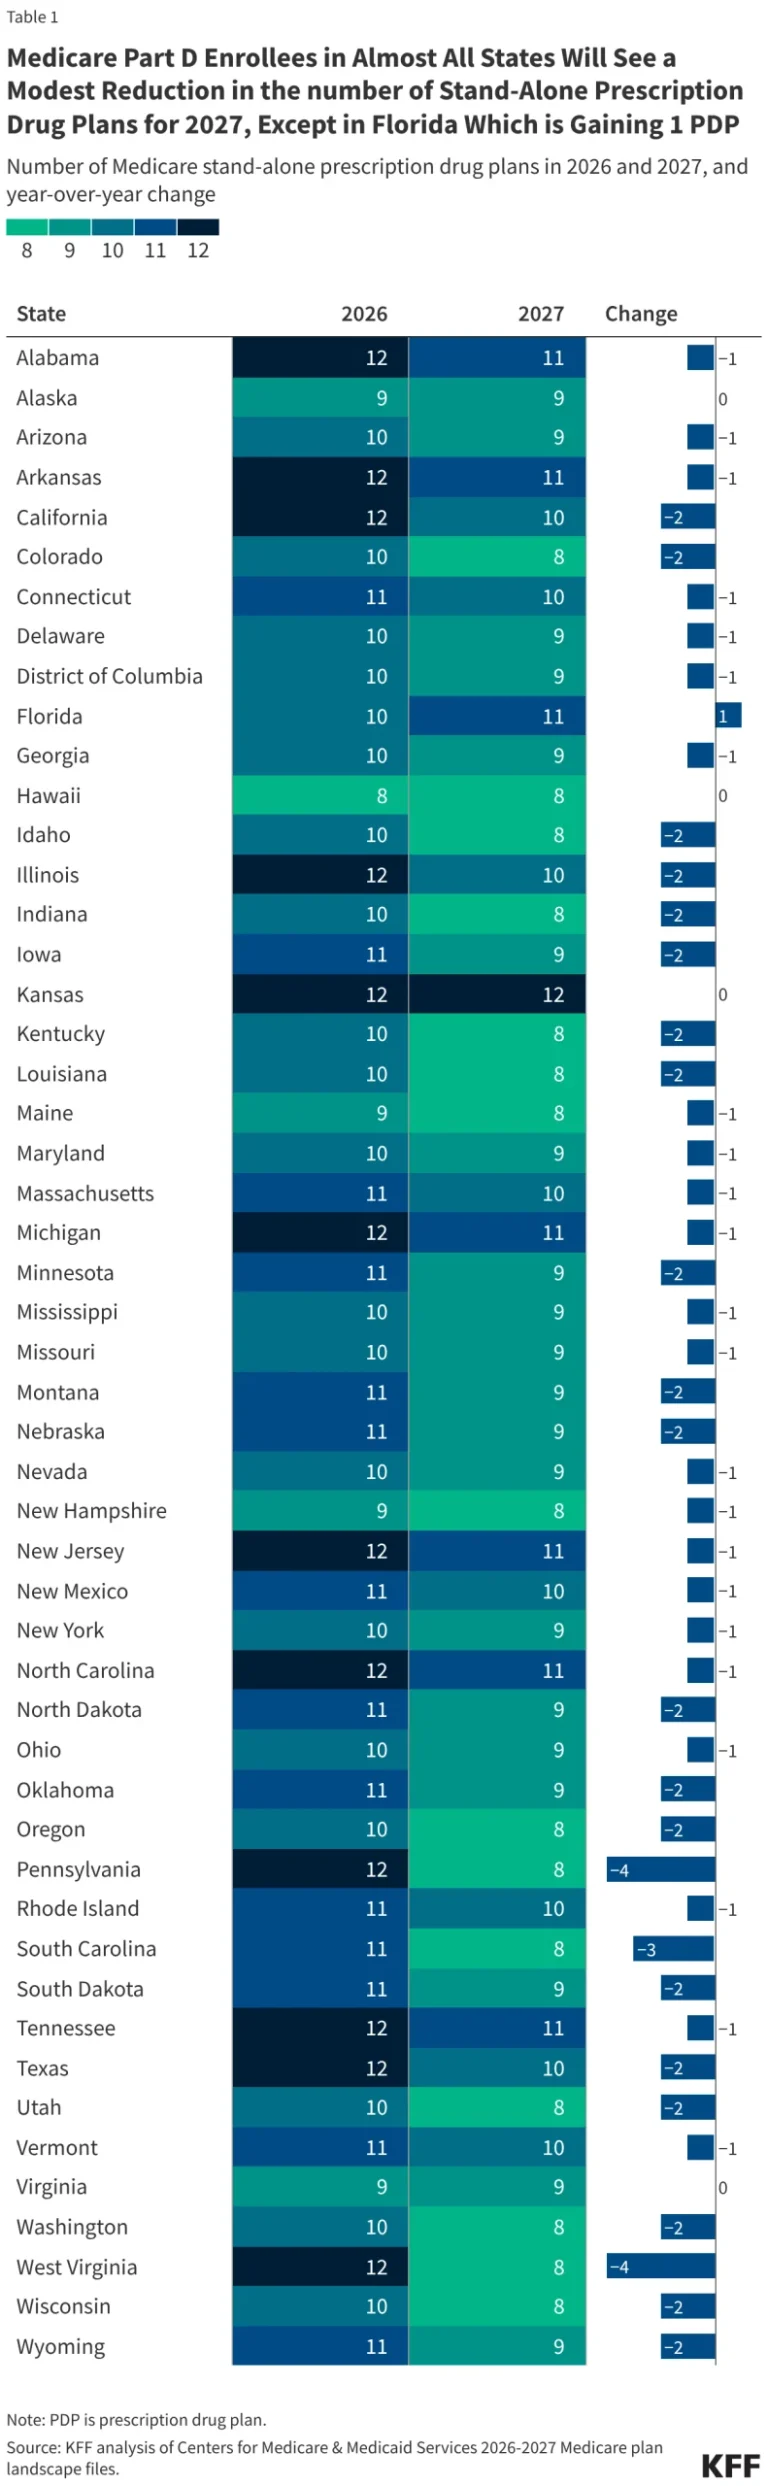
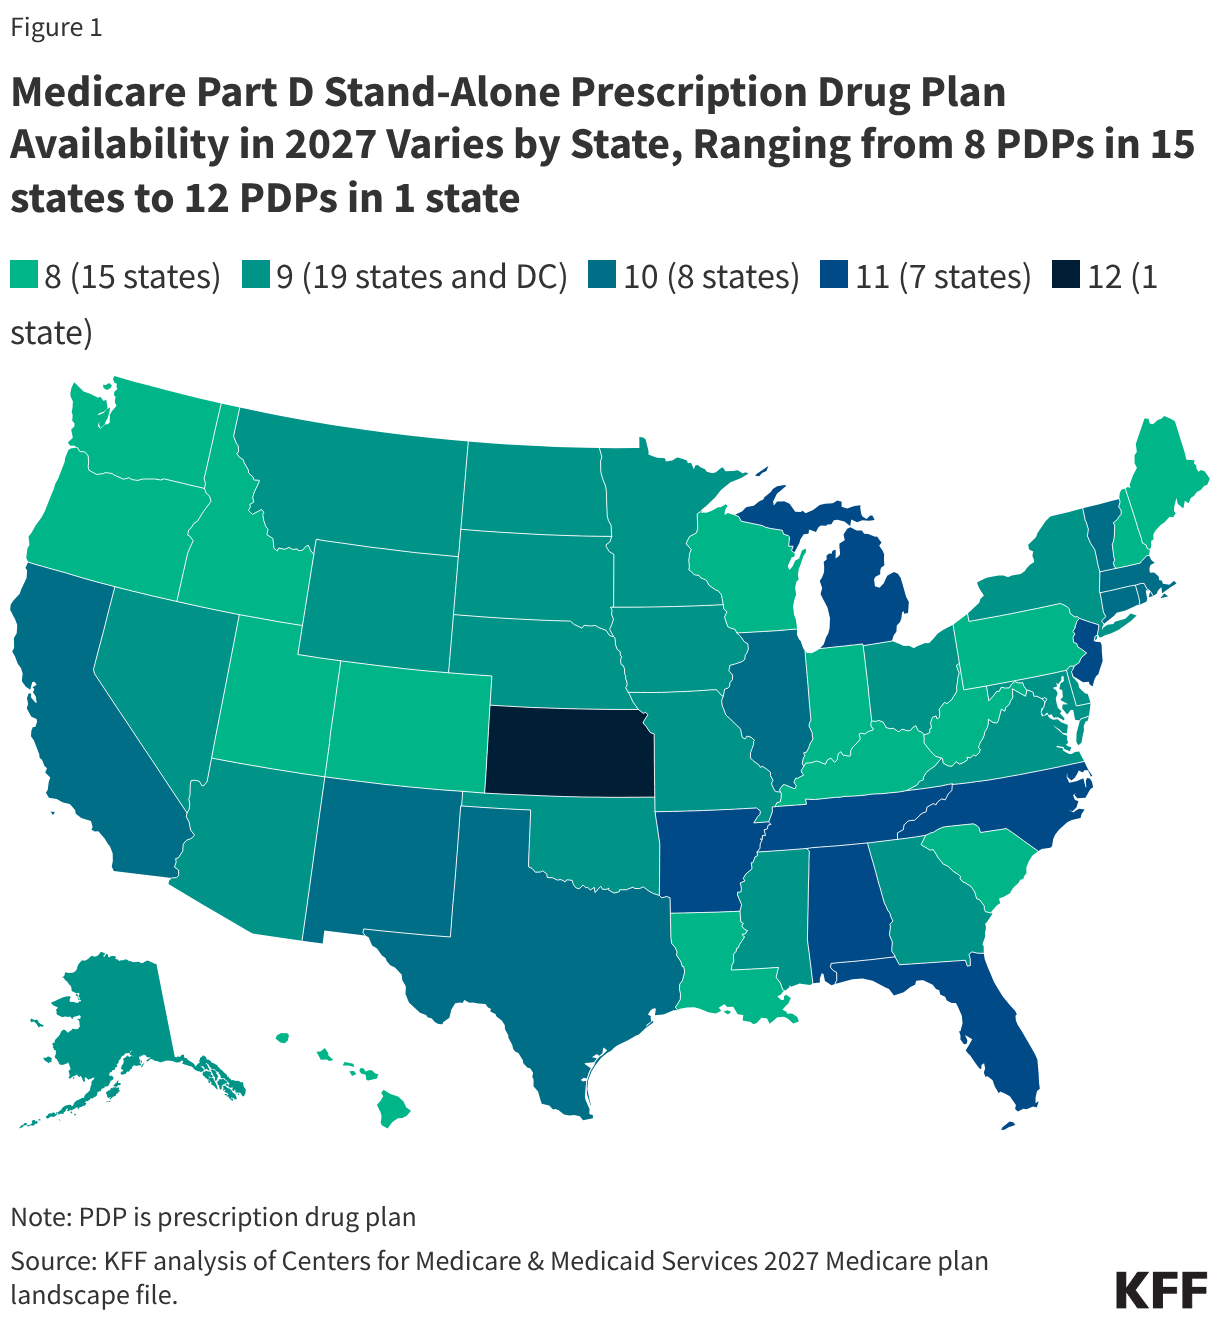
The most striking trend heading into 2027 is the continued contraction of the stand-alone drug plan market. For the fourth consecutive year, the number of PDP options available to the average beneficiary is set to decline. In 2026, the average enrollee had 11 plan options; by 2027, that number will drop to nine.
This reduction is not merely a statistical anomaly but a reflection of a fundamental shift in insurer strategy. Nationwide, the total number of stand-alone drug plans is falling from 360 to 316. This consolidation is driven by major players scaling back their footprint. Health Care Service Corporation is withdrawing its HealthSpring Extra Rx PDP from 22 regions, and CVS Health is pulling the Silverscript Choice PDP from 13 regions. As a result, the market is becoming less diverse, with most states now offering only eight or nine plans, a stark contrast to the broader variety seen just a few years ago.
Chronology: Four Years of Contraction
To understand the 2027 landscape, one must look at the trajectory of the Medicare Part D market since 2024. The program has undergone a steady, consistent thinning of competition:
- 2024: The industry began signaling a shift away from stand-alone plans, prioritizing the growth of integrated Medicare Advantage Prescription Drug (MA-PD) plans.
- 2025: Market consolidation accelerated as regulatory pressures and changing reimbursement models made it harder for smaller, independent PDPs to remain profitable.
- 2026: The stability of the market was maintained in part by temporary government interventions, including the Part D Premium Stabilization Demonstration, which capped year-over-year premium increases.
- 2027: The current year marks a turning point. With the termination of the Premium Stabilization Demonstration, the "safety net" that kept premiums from spiking has been removed. While a massive across-the-board hike was avoided, the removal of these protections has introduced new, localized volatility for millions of seniors.
Supporting Data: The Cost of Coverage
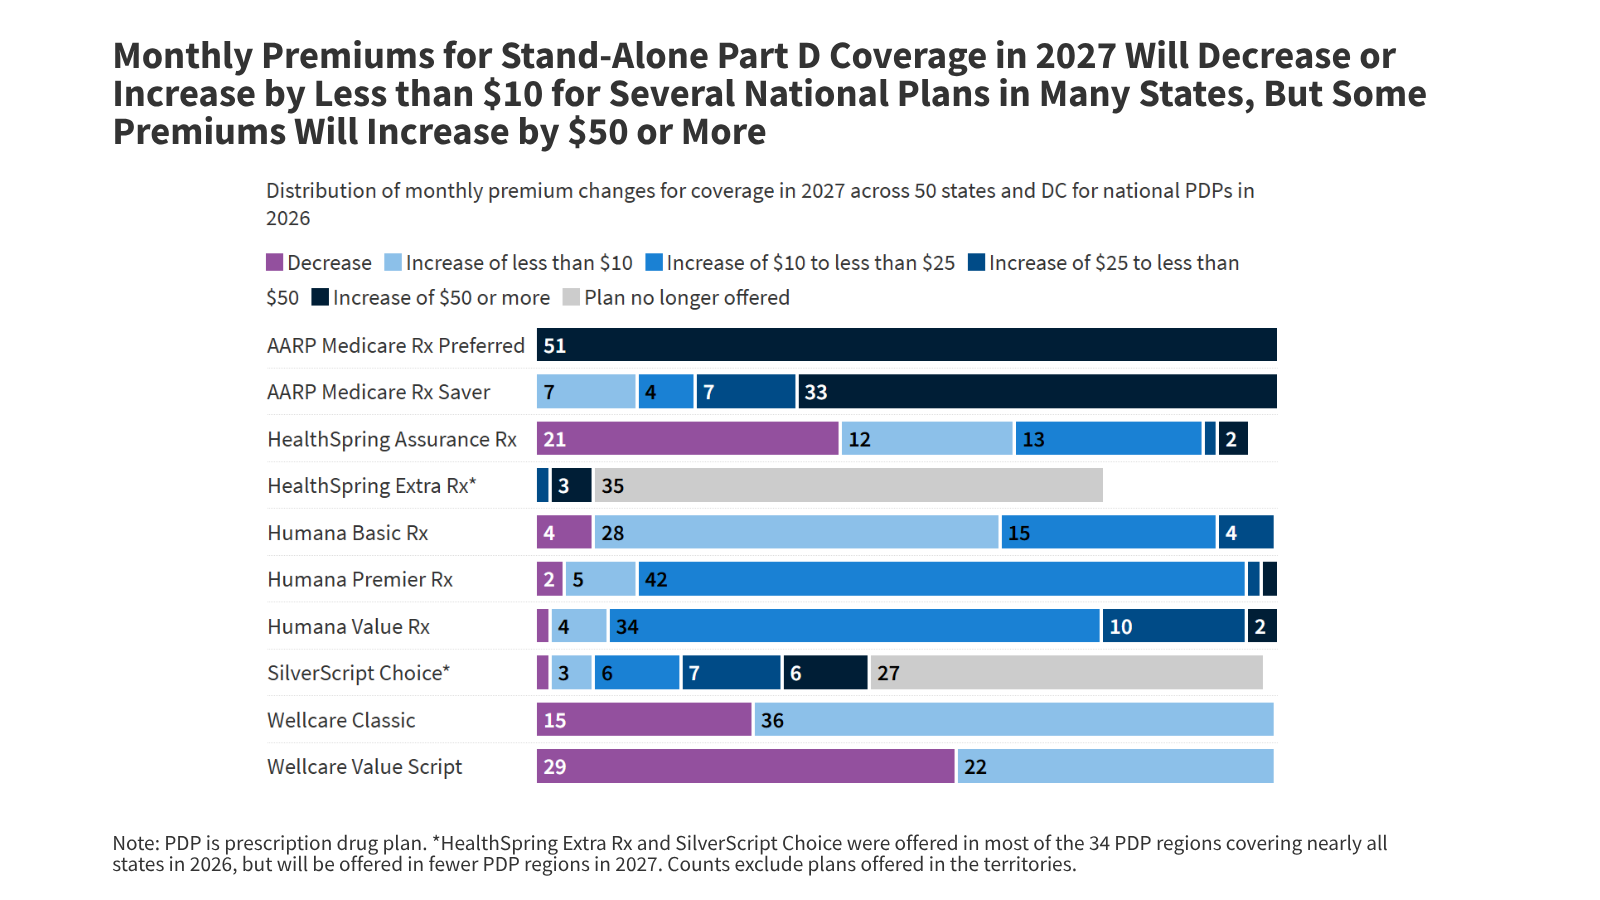
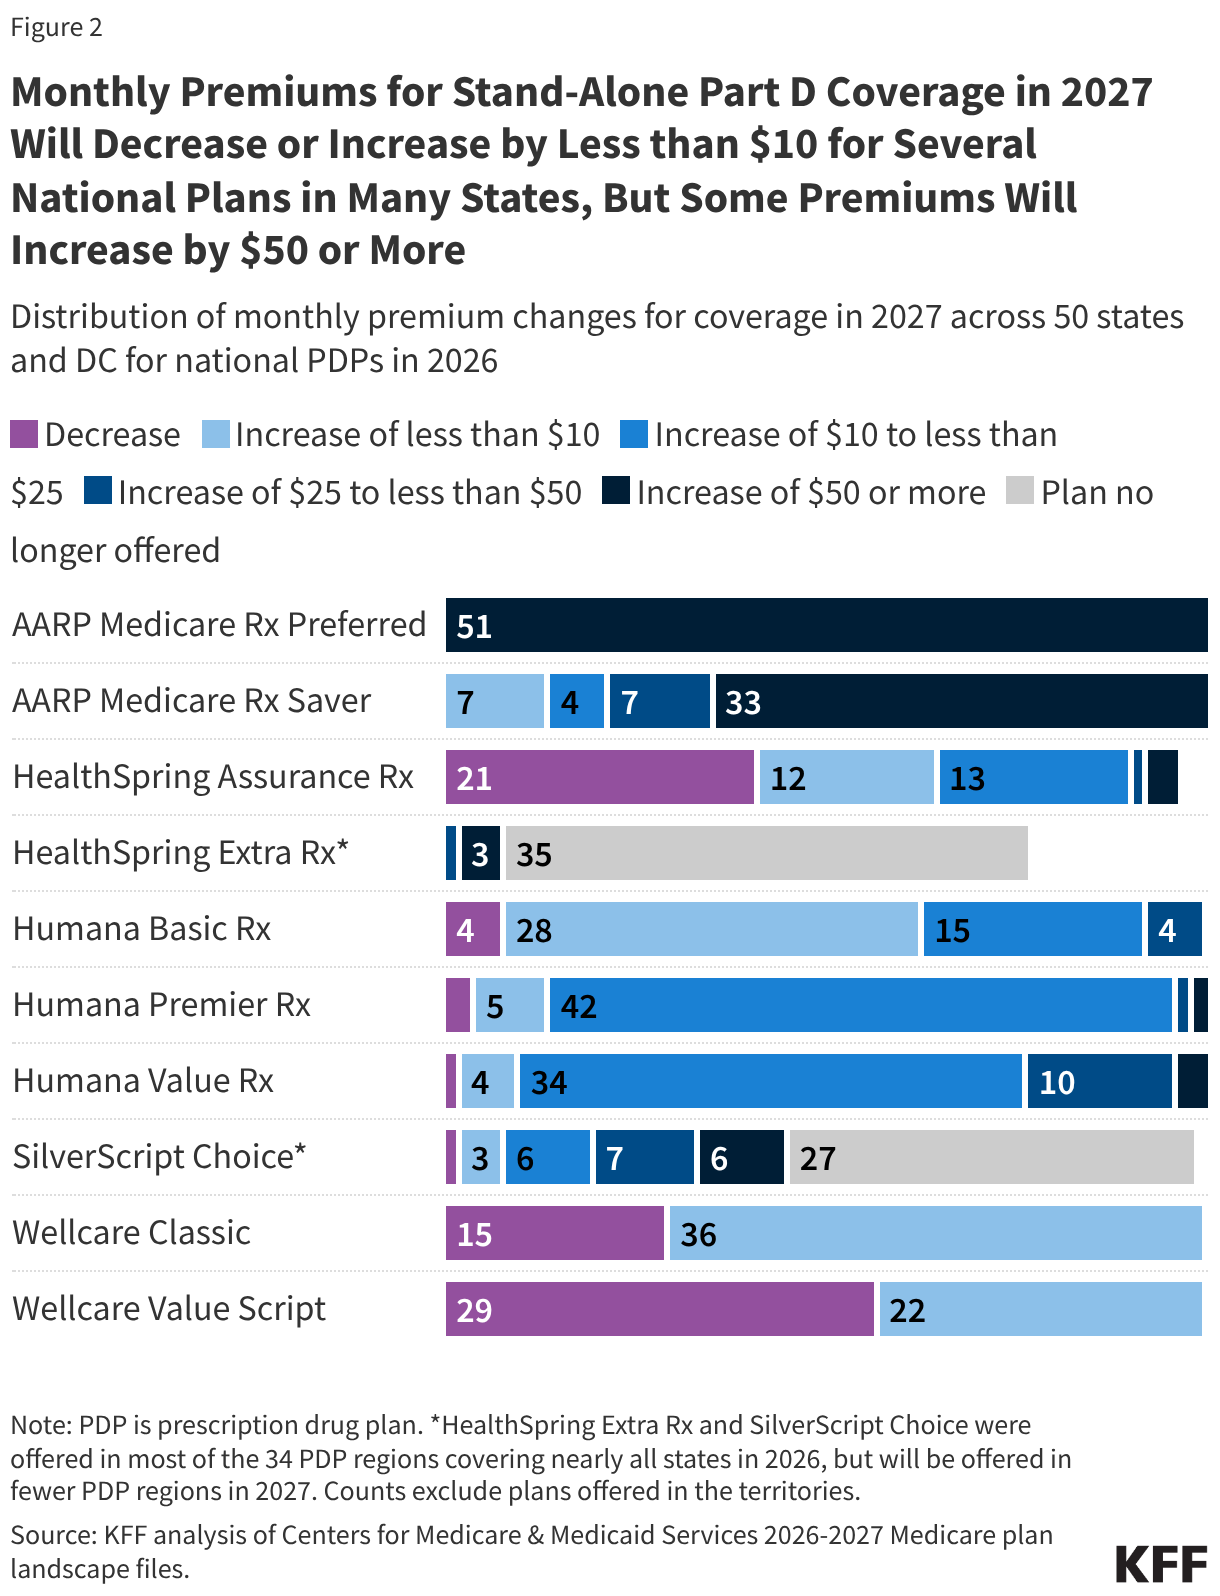
Data analysis from the Kaiser Family Foundation (KFF) reveals that the "average" premium increase hides a tale of two enrollees. While some beneficiaries will see their premiums decrease or stay stagnant if they remain in their current plan, others are facing significant, double-digit percentage increases.
Geographic and Structural Disparities
The availability of plans remains highly dependent on geography. While Florida stands as a rare exception, gaining one additional PDP, almost every other state is seeing a reduction in options. This creates a "lottery effect," where the quality and cost of a beneficiary’s healthcare are increasingly dictated by their zip code.
Furthermore, the divide between stand-alone PDPs and Medicare Advantage drug plans (MA-PDs) is widening. Approximately 56% of Part D enrollees are currently in Medicare Advantage plans, which often boast zero-premium options. Because these plans can leverage federal rebate dollars—funds unavailable to stand-alone PDP sponsors—to subsidize drug coverage, they are becoming the default choice for millions, leaving stand-alone PDP enrollees to shoulder the full burden of market fluctuations.
Official Responses and Regulatory Strategy
CMS has been vocal in its defense of the current trajectory, emphasizing that the market remains stable. In its official communications, the agency maintains that the termination of the Premium Stabilization Demonstration was a calculated move, suggesting that the extra subsidies were no longer necessary to maintain a functional market.
However, critics and policy analysts point out that while the average premium increase was kept to $1, the termination of the demonstration has removed the cap on annual premium growth. This means that for some enrollees, premiums could jump by more than $50 per month. CMS argues that the lack of widespread, massive premium hikes confirms their strategy was sound, but the agency’s focus on national averages may be providing a false sense of security for those in specific plans or regions facing sharp cost increases.
Implications: The "Hidden" Costs of Stability
For the average Medicare beneficiary, the most critical implication of the 2027 report is that premiums are no longer the most important metric to watch.
The Quality Trade-Off
When a plan keeps its premium low despite rising drug costs, it must find savings elsewhere. This often results in a "coverage gap" in quality. Beneficiaries must look beyond the monthly premium to evaluate three critical components:
- Formularies: What drugs are actually covered?
- Tier Placement: Are the medications you take being moved to higher cost-sharing tiers?
- Utilization Management: Are there new requirements for prior authorization, step therapy, or quantity limits that make it harder to access necessary treatments?
As the cost of drugs rises, insurers are increasingly using utilization management as a tool to control their own expenses. This means that even if a beneficiary’s premium remains stable, their out-of-pocket costs at the pharmacy counter could rise significantly if their medication is subjected to stricter coverage rules.
The Erosion of "Zero-Premium" Options
The end of the Premium Stabilization Demonstration has also jeopardized the existence of zero-premium plans. For beneficiaries without low-income subsidies, the disappearance of these options is a significant blow to their financial planning. Many seniors on fixed incomes rely on these plans to keep their healthcare costs predictable. The 2027 environment effectively forces these individuals to either pay more for their existing coverage or navigate a complex, shrinking market to find a more affordable, yet potentially less comprehensive, alternative.
Conclusion: Navigating the 2027 Open Enrollment
As beneficiaries prepare for the upcoming enrollment period, the message from experts is clear: "Set it and forget it" is no longer a viable strategy for Medicare Part D. The 2027 marketplace requires active engagement.
Beneficiaries should not be swayed by headlines regarding "modest" national average premium increases. Instead, they must perform a granular review of their specific health needs. This includes:
- Checking their plan’s 2027 formulary to ensure their current prescriptions remain covered at a reasonable tier.
- Comparing total annual costs, which include premiums, deductibles, and co-pays, rather than looking at premiums alone.
- Considering the shift to Medicare Advantage, if the local market for stand-alone PDPs has become prohibitively expensive or offers limited coverage.
The 2027 Medicare Part D landscape is a testament to the ongoing tension between market stability and the rising cost of pharmaceuticals. While the system has managed to avoid a catastrophic collapse in competition, the burden of navigating this increasingly fragmented and costly landscape has shifted squarely onto the shoulders of the beneficiaries. As the market continues to consolidate, the need for clear, objective, and individualized guidance for seniors has never been more pressing.
About the Author