Section 1115 Medicaid demonstration waivers serve as the primary laboratory for American healthcare policy. By granting states the authority to bypass certain federal statutory requirements, the Department of Health and Human Services (HHS) allows state governments to test innovative delivery models—provided those models are deemed likely to "promote the objectives of the Medicaid program." However, as federal administrations shift, so too does the philosophy governing these waivers, transforming them from tools of expansion into instruments of restriction and vice versa.
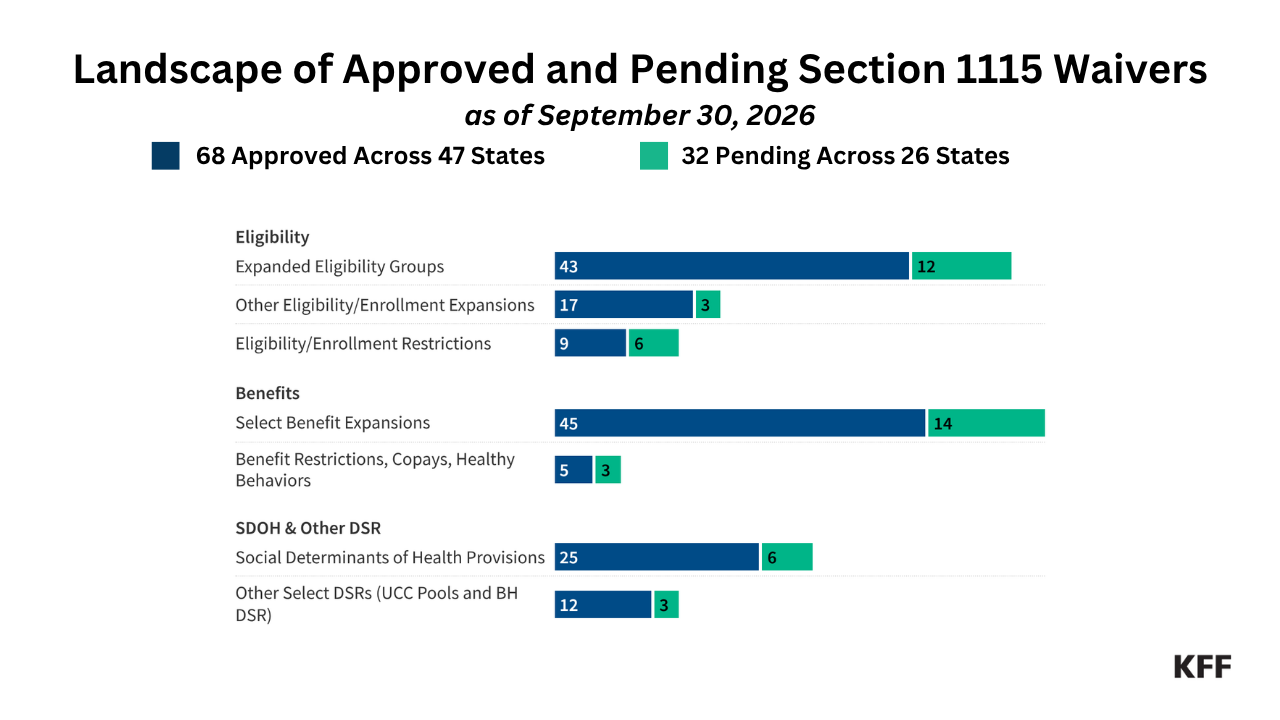
As of late 2026, the landscape of Medicaid is undergoing a profound recalibration. With nearly every state managing at least one active Section 1115 waiver, these instruments have become the central battleground for competing visions of social safety nets, healthcare eligibility, and the role of the state in addressing the social determinants of health (SDOH).
The Mechanics of Flexibility: What are Section 1115 Waivers?
At its core, Section 1115 of the Social Security Act allows states to deviate from the rigid rules of federal Medicaid law. This flexibility is intended to encourage innovation in areas such as coverage expansion, care delivery, and benefit design. Because these waivers require approval from the HHS Secretary, they act as a direct reflection of presidential priorities.
Under the Biden-Harris administration, the focus was heavily placed on expanding access, addressing health-related social needs (HRSN)—such as housing and food security—and ensuring continuity of coverage, particularly for children and justice-involved populations. In contrast, the current Trump administration has begun to pivot, emphasizing fiscal discipline, work requirements, and a more restricted interpretation of what constitutes a "Medicaid-covered" service.
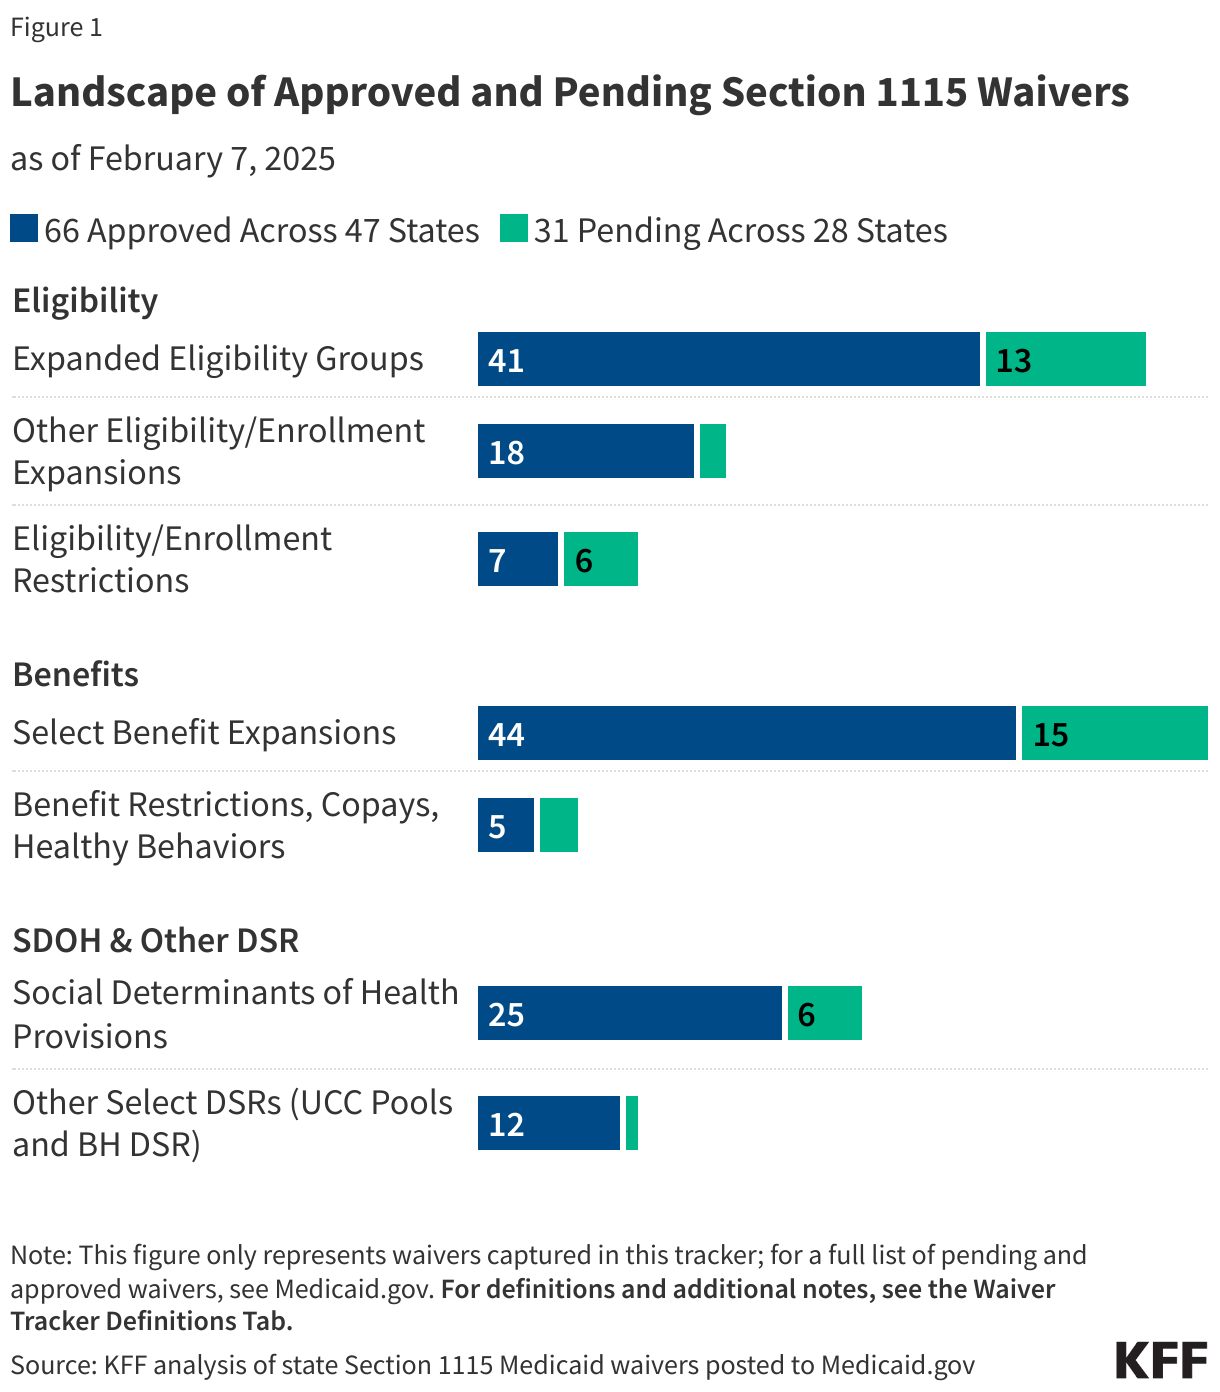
Chronology: A Policy Pivot (2022–2026)
The trajectory of recent Medicaid policy can be mapped through a series of key regulatory shifts:
- 2022–2023: The Era of Social Determinants. The Biden administration issued groundbreaking guidance encouraging states to address "health-related social needs" (HRSN) through Section 1115 waivers. This included targeted support for housing and nutrition. Simultaneously, the administration encouraged states to provide pre-release Medicaid coverage to incarcerated individuals to facilitate smoother transitions to community care.
- January 2024: The Consolidated Appropriations Act, 2023 mandate took effect, requiring all states to implement 12-month continuous eligibility for children.
- March 2025: The Trump administration formally rescinded the Biden-era HRSN guidance. While existing approvals remained intact, the administration signaled that future requests would be evaluated on a stricter, "case-by-case" basis.
- April 2025: A significant fiscal shift occurred as the administration announced the phasing out of federal funding for "Designated State Health Programs" (DSHP), which had previously been used to support various waiver-funded initiatives.
- July 2025: In a major reversal of previous coverage trends, the administration issued guidance stating it would neither approve new applications nor extend existing waivers for continuous eligibility for children and adults. Furthermore, it began phasing out federal support for initiatives aimed at strengthening the primary care and behavioral health workforce.
- September 2026: While maintaining a more restrictive stance on most fronts, the administration approved four new reentry waivers for incarcerated individuals, suggesting a potential selective interest in criminal justice reform, even as broader social support programs are curtailed.
Supporting Data: Eligibility, Benefits, and Work Requirements
The data tracking these waivers highlights a clear divide between states pushing for broad coverage and those aligning with federal efforts to restrict eligibility.
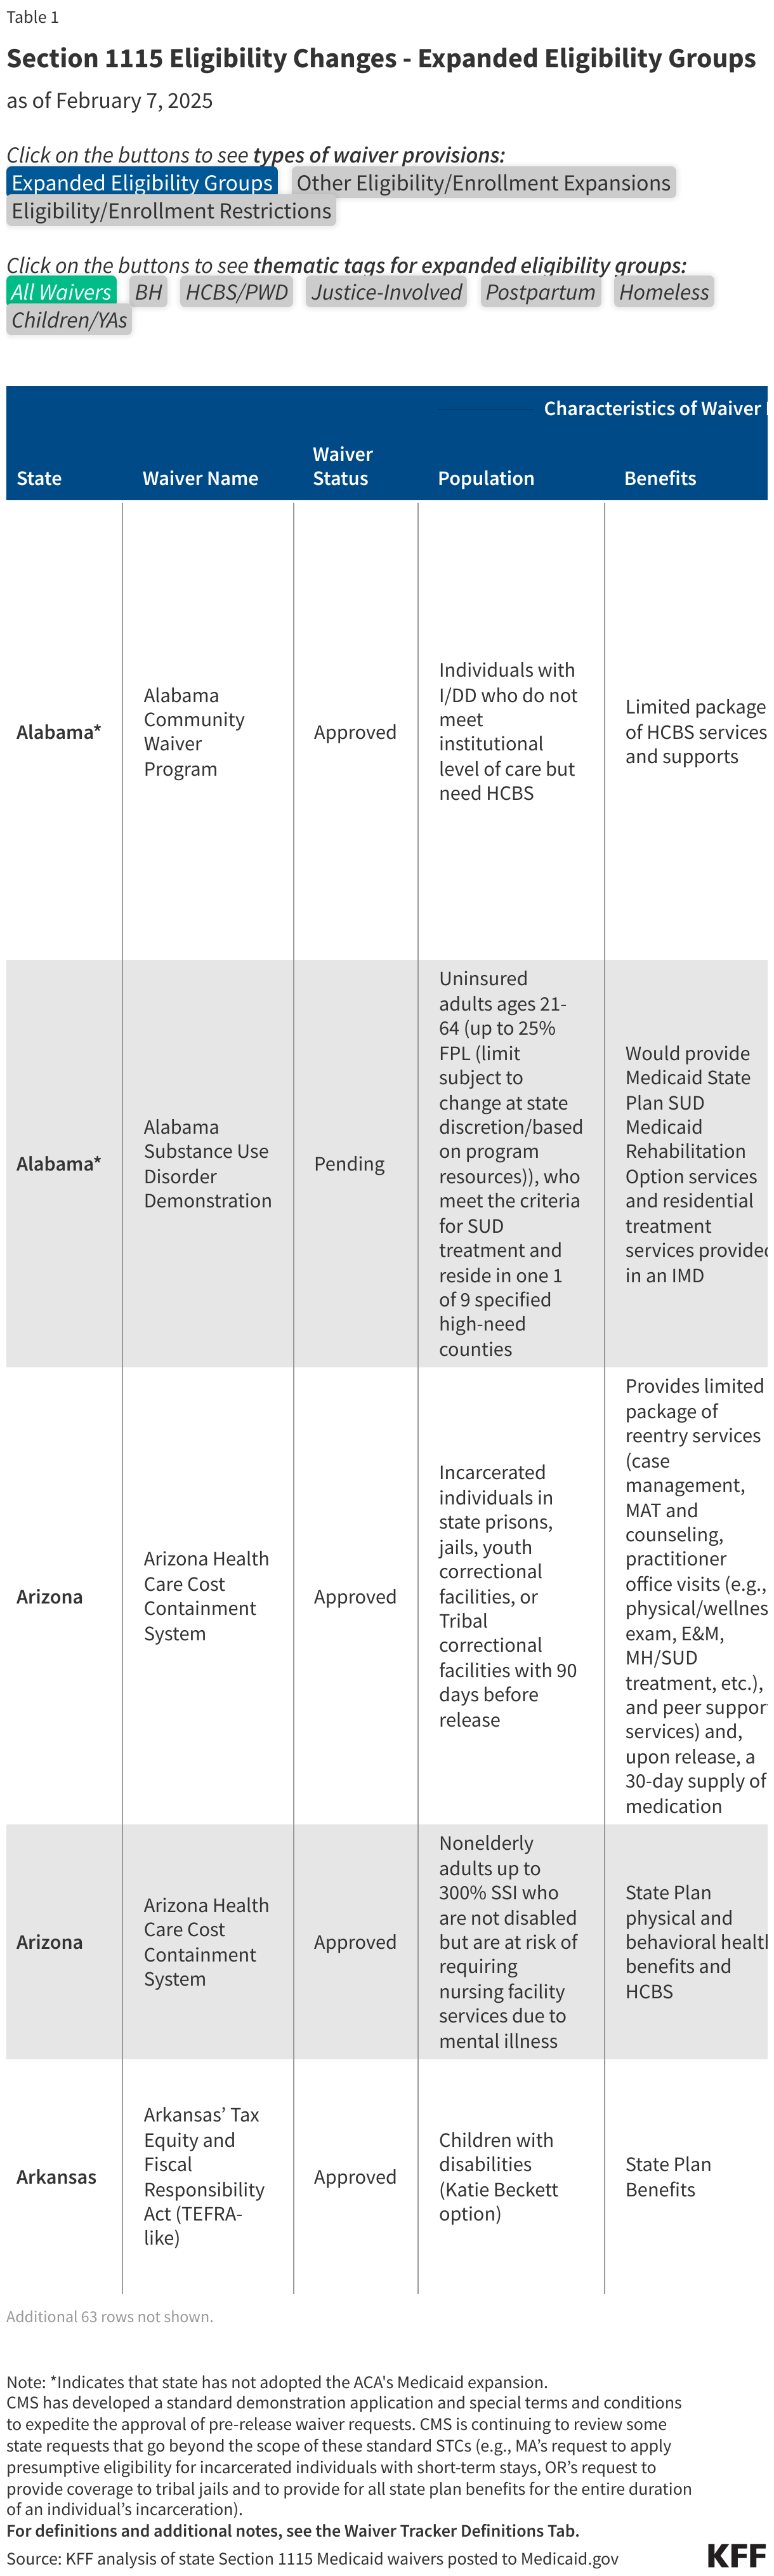
The Return of Work Requirements
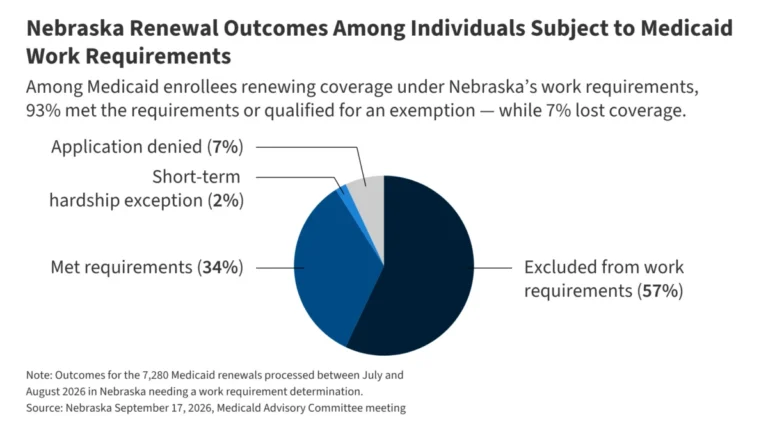
Perhaps the most contentious issue in modern Medicaid policy is the implementation of work requirements. While the 2025 federal budget law mandates work requirements for ACA expansion adults effective January 1, 2027, several states are moving to implement these measures early.
Nebraska, Montana, Iowa, and Arkansas have initiated plans to enforce these requirements through State Plan Amendments (SPAs) ahead of the federal deadline. Meanwhile, Georgia stands as a unique case—the only state currently operating a work requirement under an 1115 waiver following protracted litigation. As of late 2026, the administration’s focus has shifted away from using 1115 waivers for this purpose, as the federal law now provides a more direct statutory pathway for implementation.
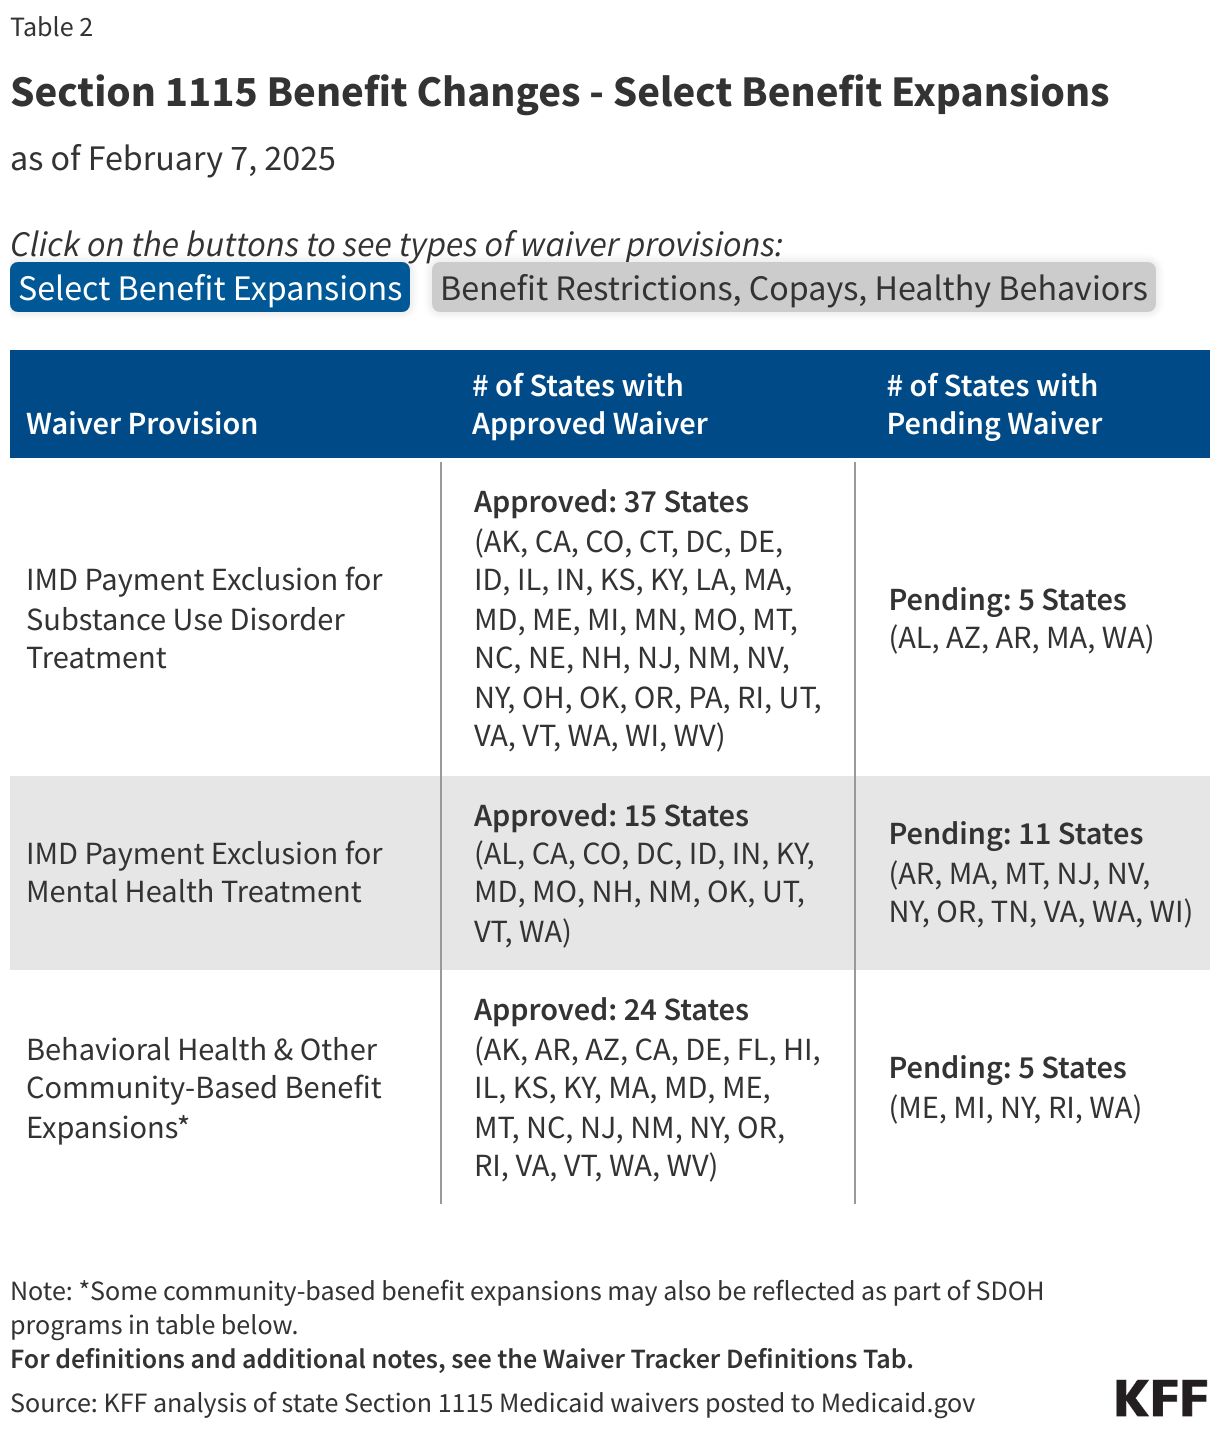
Eligibility and Benefit Contractions
The legal landscape is also shifting. In June 2024, the U.S. District Court for the District of Columbia vacated federal approval for Indiana’s "Healthy Indiana Plan 2.0." The court’s decision effectively struck down the state’s authority to impose premiums beyond federal limits and to waive retroactive eligibility and non-emergency medical transportation (NEMT). The case remains under appeal, but it underscores the ongoing legal volatility surrounding state attempts to limit benefit access.
Furthermore, the cessation of continuous eligibility waivers represents a significant contraction. Studies from the Medicaid and CHIP Payment and Access Commission (MACPAC) have consistently shown that continuous eligibility significantly reduces "churn"—the phenomenon where enrollees lose and regain coverage due to administrative hurdles. By ending these waivers, the current administration is effectively shifting the burden of maintaining coverage back onto individual enrollees.

Official Responses and Administrative Stance
The current administration maintains that its policies are designed to restore the "traditional" intent of Medicaid. In its communications, the Centers for Medicare & Medicaid Services (CMS) has argued that the rescission of broad HRSN frameworks and the end of continuous eligibility waivers are necessary steps to ensure fiscal sustainability and to prevent the program from drifting beyond its original statutory mandate.
Conversely, public health advocates and several state leaders argue that these reversals will lead to a surge in uncompensated care costs and a decline in health outcomes for the most vulnerable. They contend that by removing the flexibility to address housing and nutrition, the federal government is ignoring the reality that these factors are the primary drivers of healthcare costs.
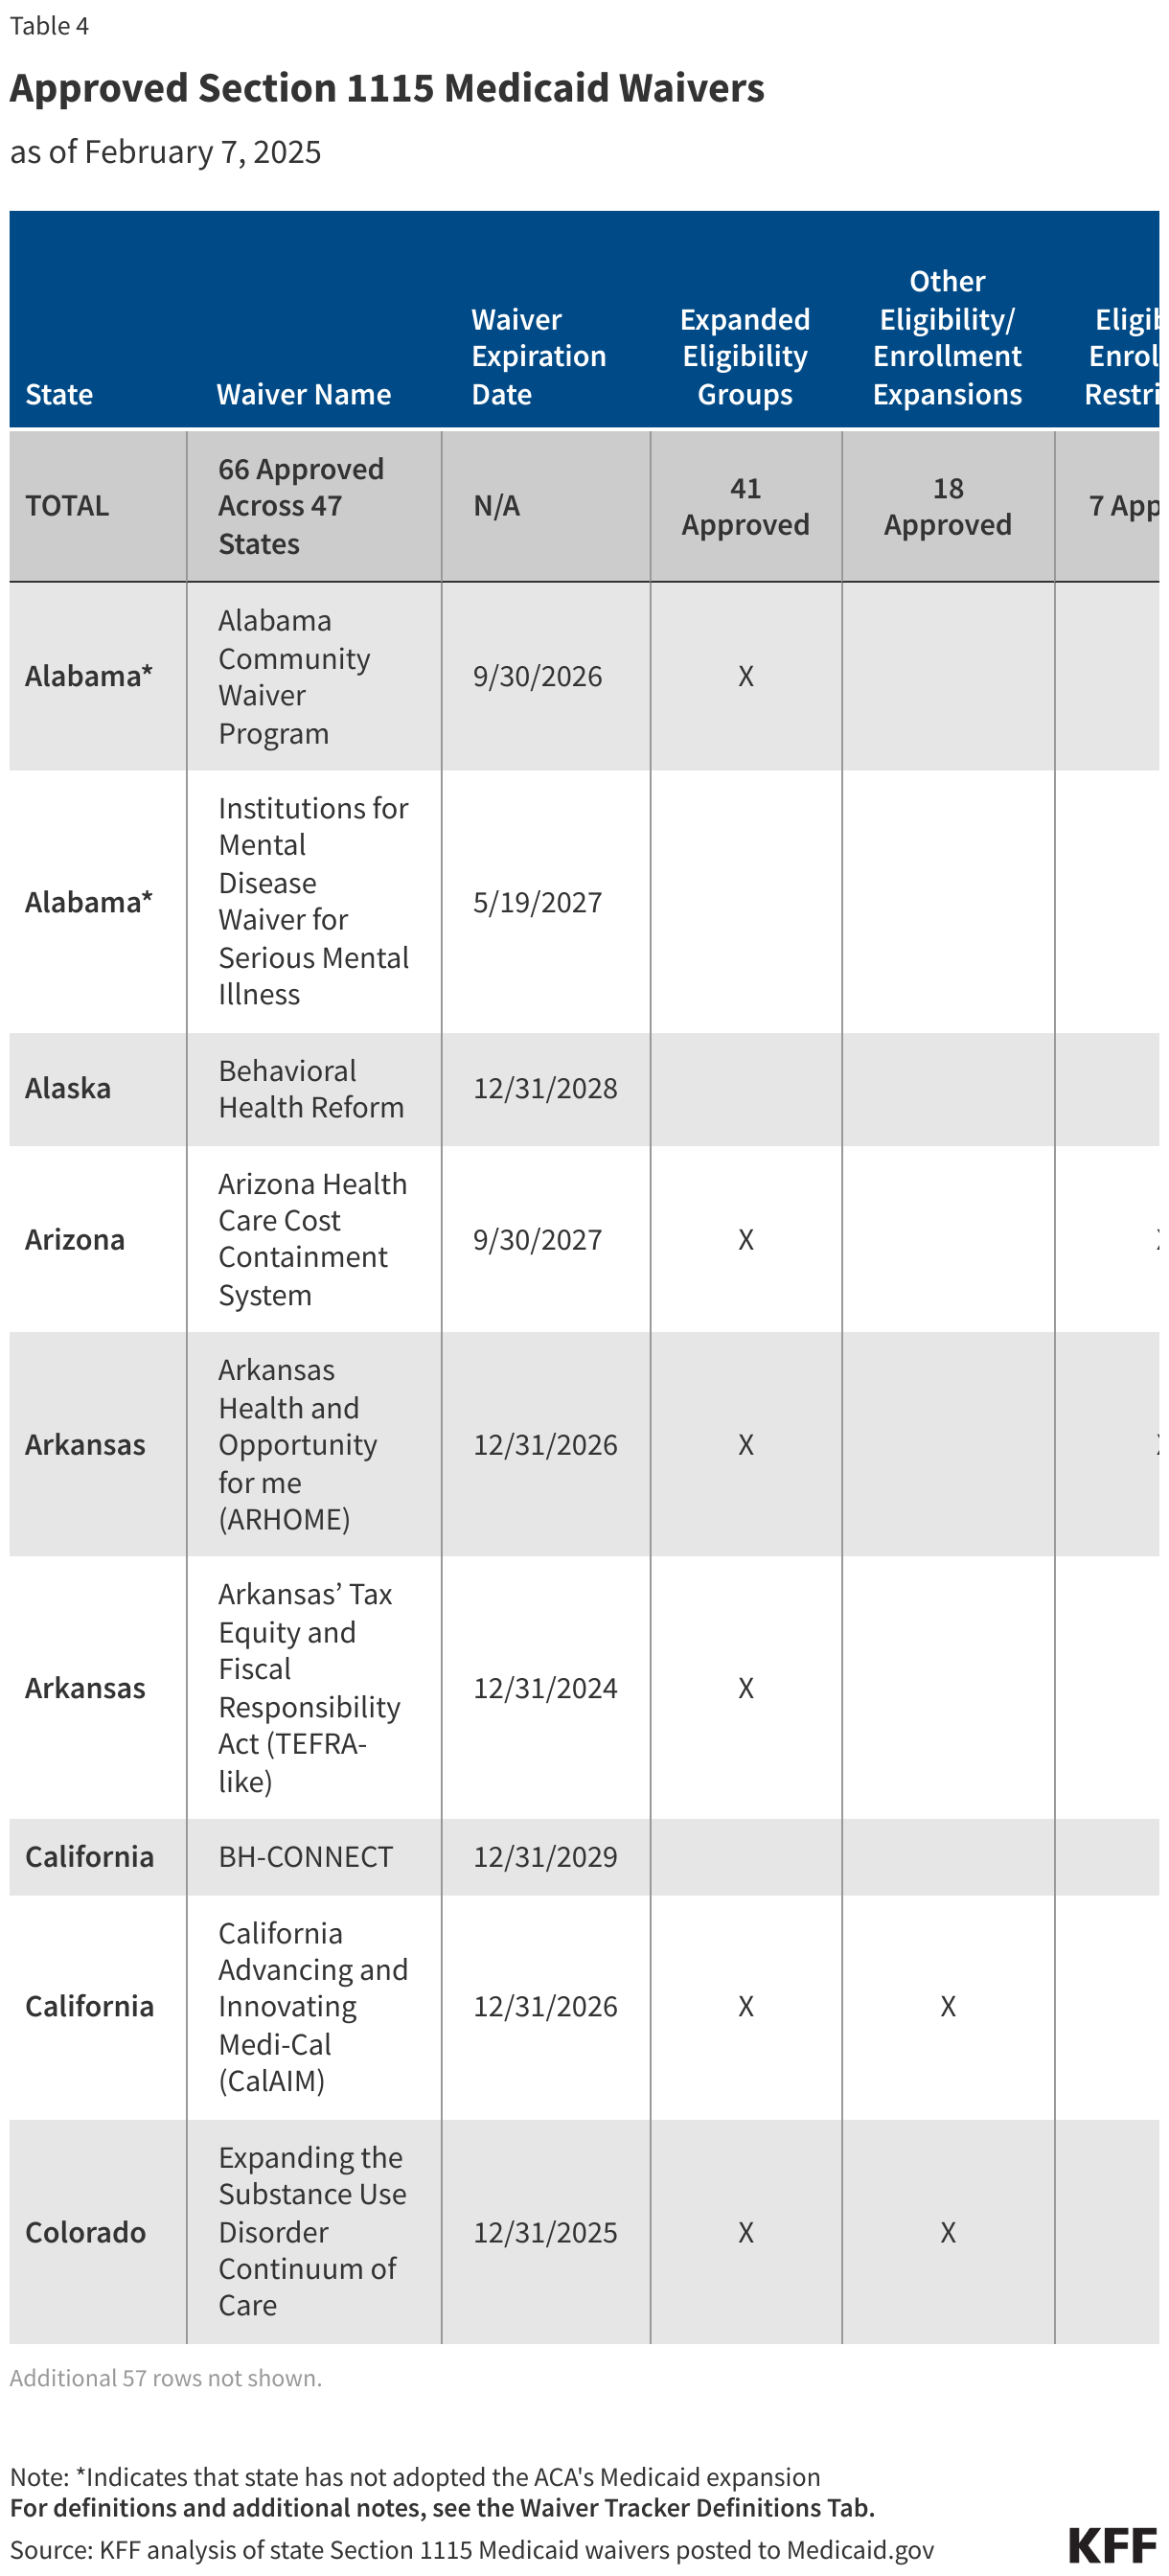
Implications: A Fragmented Future for Medicaid
The implications of these shifts are far-reaching and suggest a fragmented future for the U.S. healthcare system:
- The End of Uniformity: As states pursue different paths—some clinging to the remnants of the Biden-era expansions and others aggressively implementing work requirements and eligibility restrictions—the Medicaid program will become increasingly unequal across state lines. A citizen’s access to care will depend more heavily on their zip code than ever before.
- Increased Administrative Churn: The end of continuous eligibility waivers for children will likely increase the administrative burden on states and families alike. As enrollment cycles shorten, providers can expect higher rates of billing errors and gaps in care, which may ultimately increase the long-term cost of managing chronic conditions that go unmonitored during periods of coverage loss.
- Legal and Regulatory Uncertainty: The ongoing litigation in states like Indiana, combined with the "case-by-case" review policy for SDOH services, suggests that the next several years will be defined by courtroom battles. States will face significant uncertainty when trying to plan long-term health initiatives, as their federal funding sources remain subject to the whims of shifting federal leadership.
- The "Safety Net" Redefined: The current administration’s pivot toward the "work-first" model signals a return to a philosophy that ties public health coverage to labor market participation. This marks a departure from the "coverage as a right" framework that dominated the previous administration.
Conclusion
Section 1115 waivers were designed to be a tool for innovation, but they have increasingly become a tool of political and ideological expression. As the U.S. moves toward 2027—a year that will see the mandatory implementation of federal work requirements—the Medicaid program faces its most significant transition in over a decade. Whether this shift will result in the promised fiscal efficiency or a systemic crisis in care access remains the defining question of the current healthcare era. For policymakers, the task is now to navigate a landscape where the rules of the game change not just with the law, but with every change in the occupant of the White House.
About the Author