As the United States grapples with its most significant measles resurgence in 35 years, the White House has initiated a sweeping transformation of federal immunization policy. On August 10, 2026, President Donald Trump signed an executive order titled “Delivering gold standard childhood vaccine recommendations for Americans,” a directive that mandates a fundamental restructuring of how the U.S. approaches the childhood immunization schedule.
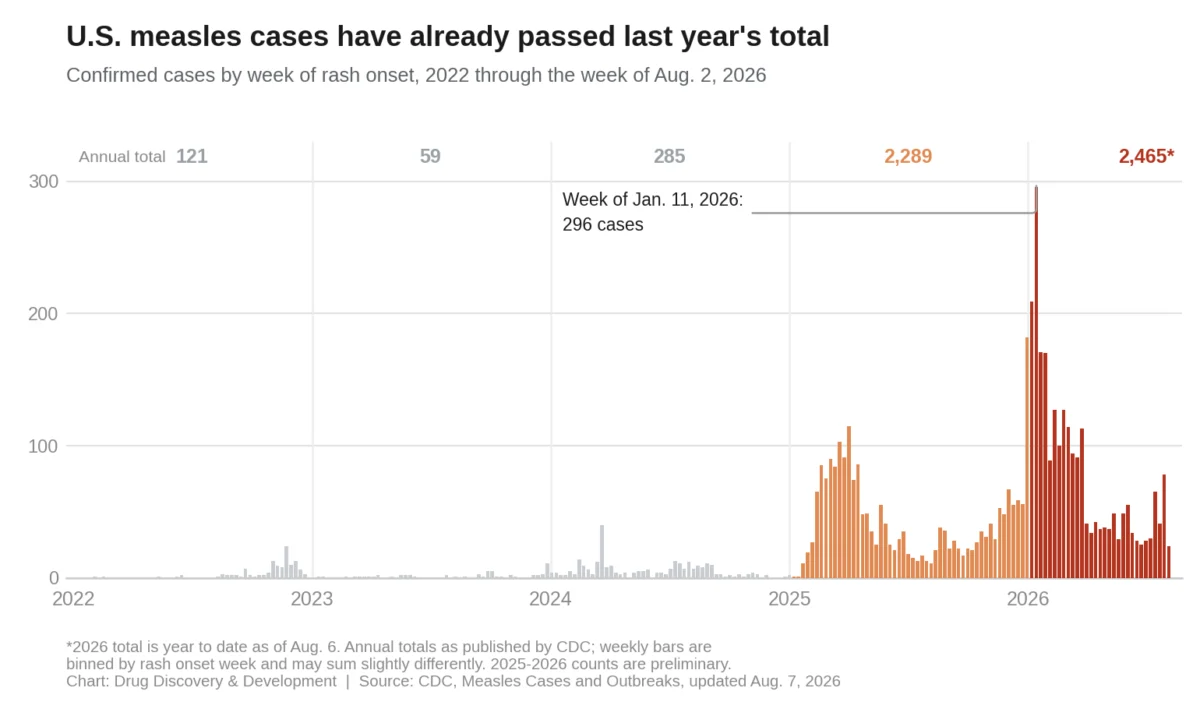
This policy pivot comes at a precarious moment for public health. As of August 6, 2026, the CDC has reported 2,465 confirmed measles cases—a figure that has already eclipsed the 2,289 cases recorded during the entirety of 2025. With kindergarten MMR (measles, mumps, and rubella) vaccination coverage falling to 92.5%, down from 95.2% pre-pandemic, public health experts are increasingly alarmed by the potential for once-eliminated diseases to regain a permanent foothold in the American population.
A Fundamental Shift in Vaccine Strategy
The executive order grants the Department of Health and Human Services (HHS) a 90-day window to formulate a plan that effectively decentralizes the current immunization model. Central to this directive is the mandate to offer MMR vaccines as separate, single-dose formulations. Furthermore, the order tasks HHS with assessing the timing and sequencing of vaccines to align with what the administration terms “gold standard science,” while simultaneously initiating development of alternatives to aluminum-based adjuvants.
The rationale provided by the administration focuses on the volume of the current U.S. schedule. Proponents of the order argue that American children receive more than twice the number of vaccine doses compared to their counterparts in several European nations. By “maximizing parental choice,” the administration seeks to grant families more autonomy, even suggesting the potential for federal legal action against states that impose mandates deemed overly restrictive by the White House.
Historical Chronology of the Current Crisis
The current tension between federal mandates and public skepticism is not new, but it has reached a critical juncture.
- 1971: The combined MMR vaccine is introduced in the United States, becoming the standard for public health immunization.
- 1989–1991: The U.S. experiences a major measles resurgence, with over 55,000 reported cases. This prompted the ACIP and the American Academy of Pediatrics (AAP) to recommend a mandatory second dose of the MMR vaccine.
- 1998: The publication of a now-debunked paper in The Lancet claimed a link between the MMR vaccine and autism. Despite its subsequent retraction in 2010 and the permanent revocation of the lead author’s medical license, the paper became a foundational text for the modern anti-vaccine movement.
- 2009: The U.S. officially phases out single-disease measles, mumps, and rubella vaccines, cementing the reliance on the combined MMR formulation.
- 2026 (March): A federal judge blocks a proposed HHS childhood vaccine schedule that sought to remove several vaccines from the universal recommendation list.
- 2026 (August 10): President Trump signs the executive order, seeking to bypass standard regulatory channels to implement changes to the vaccine schedule.
The Autism Debate and Scientific Scrutiny
A primary driver of the current administration’s policy is the contention—repeatedly stated by HHS Secretary Robert F. Kennedy Jr.—that the current vaccination schedule is intrinsically linked to rising autism rates.
During the announcement, President Trump remarked on the incidence of autism, noting it has become “progressively worse” as the number of recommended vaccines has increased. Secretary Kennedy pointed to historical data from the 1970s, specifically a study by psychiatrist Darold Treffert, to argue that autism rates were once significantly lower. However, public health researchers point out that the dramatic increase in recorded autism cases is heavily influenced by evolving diagnostic criteria, improved screening, and expanded access to early intervention services.
The administration’s focus on aluminum adjuvants—used to enhance immune response in vaccines such as DTaP, HPV, and hepatitis B—remains a point of intense friction. While Secretary Kennedy characterizes these compounds as neurotoxic, the broader scientific community, including researchers from the CDC and the Vaccine Safety Datalink, maintains that there is no causal link between vaccine-derived aluminum and neurodevelopmental disorders. A 2025 Danish cohort study, which examined millions of records, found no association, though the administration has dismissed such findings as “bought” or “flawed.”

Official Responses and Institutional Pushback
The reaction from the medical establishment has been swift and condemnatory. The American Academy of Pediatrics (AAP) officially branded the executive order as “disheartening and dangerous.”
“Dozens of studies involving millions of people show there is no link between vaccines and autism, and yet federal leaders continue to promote this outdated, disproven idea to scare families,” said AAP President Andrew Racine.
Legal scholars, including UC Law professor Dorit Reiss, have questioned the constitutional and administrative validity of the order. Reiss noted that federal statutes explicitly vest the power to make immunization recommendations in the CDC’s Advisory Committee on Immunization Practices (ACIP). While a president can direct the CDC to convene, an executive order cannot legally supersede the established regulatory process, setting the stage for a prolonged legal battle between the executive branch and public health agencies.
Implications: The Japan Comparison
A central pillar of the administration’s argument for separate vaccines is the Japanese model, which allows for individual doses. However, public health experts argue that this comparison omits critical historical context. Japan moved away from the combined MMR vaccine in the 1990s following safety concerns regarding a specific mumps strain, which resulted in a catastrophic drop in immunization rates.
The consequences were severe: a 2001 measles epidemic in Japan resulted in an estimated 265,000 cases. It took the nation over two decades—until 2015—to achieve measles elimination status, and it did so only by eventually re-adopting a combined measles-rubella (MR) vaccine. The administration’s plan to move back to single shots, according to infectious disease experts, risks mirroring the very failures that led to Japan’s decades-long battle with preventable outbreaks.
Future Outlook: A Public Health Paradox
The implications of this policy shift are vast. By moving vaccines for COVID-19, influenza, rotavirus, and hepatitis A and B into "high-risk-only" or "shared clinical decision-making" categories, the U.S. is signaling a departure from the universal immunization standards that have historically protected the population from endemic disease.
Stanford modeling published in JAMA suggests that at current rates of vaccine hesitancy and coverage decline, measles could become endemic in the U.S. within 20 years. The administration’s push for smaller, more targeted vaccination schedules is presented as a "gold standard" approach to protect individual autonomy. Conversely, epidemiologists warn that this could lead to a fragmented national health landscape, where herd immunity is eroded, potentially exposing the most vulnerable populations—infants, the elderly, and the immunocompromised—to diseases that were once considered relics of the past.
As the 90-day deadline for the HHS plan approaches, the nation faces a defining moment. The tension between the executive branch’s vision of "parental choice" and the consensus of the medical community regarding population-level immunity will likely dictate the course of American public health for the remainder of the decade. Whether this shift succeeds in restoring public trust or instead accelerates the resurgence of vaccine-preventable diseases remains the central question of the 2026 health policy agenda.
About the Author